Author: ModernMedia

With over 3 600 Western Cape Users, Lenacapavir is “Cool”
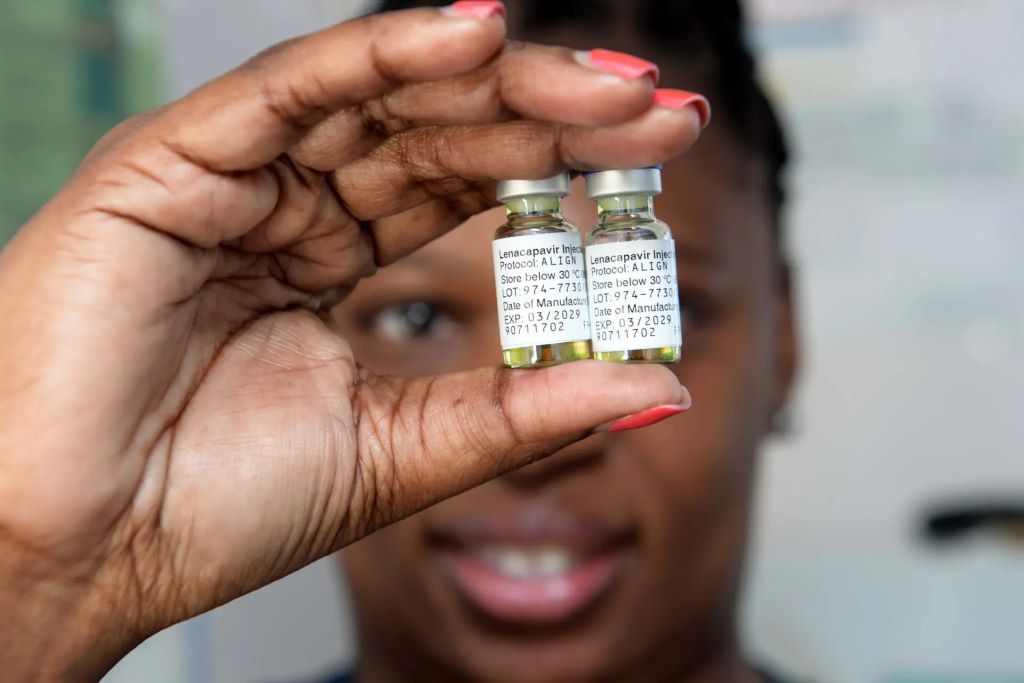
Lenacapavir is administered via two injections of 1.5ml each in the buttocks, thigh, abdomen or upper arm. (Photo: Nasief Manie/Spotlight)

By Biénne Huisman for Spotlight

From counselling about small nodules to overcoming people’s fears of needles, Spotlight takes the pulse of a new HIV prevention injection’s rollout in the Western Cape.

At Cape Town’s Philippi Village, beside a rainbow-emblazoned mobile clinic, Olwam Plaatjie says she switched from the two-monthly cabotegravir HIV prevention injection to the six-monthly injectable lenacapavir. Despite small nodules forming at the two jab sites on her abdomen, the 20-year-old is delighted with the new HIV prevention medicine.

Plaatjie, who is from Crossroads and who started taking cabotegravir injections three years ago, says: “I see many people who are HIV positive. Many of them are girls. Guys often don’t even want to be tested; my boyfriend didn’t want to go for HIV tests. So that’s why I started to have a fear. I was like, you know, maybe there is something he is hiding.”

Plaatjie is one of a stream of young women now taking their health in their own hands as they personally implement HIV prevention strategies, thanks to national government and research campaigns aimed at this vulnerable group.

According to Foster Mohale, spokesperson for the National Department of Health, as of 23 August, there have been 3 641 initiations of lenacapavir, or LEN for short, across the 22 government clinics in the province that are offering the injection. Nationally, the number stood at 47 934.

Due to severely constrained supply, lenacapavir is for now only being rolled out to 360 health facilities across six provinces (Free State, Limpopo, and Northern Cape are not currently included). Gauteng accounts for over a third of facilities and KwaZulu-Natal for around a quarter. The Western Cape’s 22 facilities makes up only around 6% of the total. The selection of facilities was in part informed by how well facilities had been doing in the provision of HIV prevention pills, currently available in almost all the country’s public sector health facilities.

Mohale said the three clinics with the highest administrations in the Western Cape as of August 26, were the Khayelitsha Community Health Centre, Michael Mapongwana Community Health Centre, in Khayelitsha, and Nolungile Community Health Centre, also in Khayelitsha.

Uptake in adolescent girls and young women

Asked about the high uptake in this area, Director of Service Priorities Coordination for the Western Cape Government Department of Health and Wellness, Hilary Goeiman, pointed out the community’s large population of adolescent girls and young women, who are being targeted in the medicine’s roll-out strategy.

“Nolungile Community Day Centre has demonstrated strong clinical leadership and effective implementation of the programme, successfully integrating lenacapavir into routine HIV prevention services,” she said.

On the demographics of the administrations, Goeiman said: “Most recipients are women, in line with the initial rollout focus on adolescent girls and young women, women of reproductive age, and pregnant and breastfeeding women who are at substantial risk of HIV acquisition.”

Mohale said 258 pregnant women had been initiated on lenacapavir at the 22 clinics across the Western Cape, since June.

Science in tandem with government

Meanwhile, Plaatjie was part of an initial cohort of 15- to 35-year-olds who received lenacapavir jabs in February, as part of a study spearheaded in the area by the Desmond Tutu Health Foundation. The study, called ALIGN, will evaluate implementation strategies for lenacapavir and how to encourage continued use.

The research is unfolding in collaboration with the Western Cape Department of Health and Wellness and the National Department of Health, but with a separate stock of the drug, independently sourced by the scientists. Social behavioural expert at the foundation, Elzette Rousseau, says their goal is to enrol at least 1 500 people on lenacapavir and to follow them for 18 months. She adds that at this stage, their data is still too limited to have any clear findings.

Cool, but a fear of needles

At Philippi Village, next to Plaatjie, Lutho Windvoel reflects on lenacapavir. He says that to his knowledge, men can be afraid of injections, and thus of HIV prevention through jabs. But, to him the benefit of protection over six months outweighs a fear of needles. “It’s just cool,” says Windvoel, who is wearing a black T-shirt with a pink teddy bear graphic.

At Philippi Village in Cape Town, a rainbow-emblazoned mobile clinic operated by the Desmond Tutu Health Foundation provides Lenacapavir injections. From left to right: Olwam Plaatjie, Sinovuyo Plaatjie, Lutho Windvoel, and Okuhle Trinity Potelwa. (Photo: Nasief Manie/Spotlight)

“LEN makes life easier. People are excited. Before, I took PrEP tablets daily but I worried that I would forget.”

Also in the conversation is Sive Mphambaniso, youth reference engagement facilitator at the Desmond Tutu Health Foundation. On a fear of injections, particularly among men, Mphambaniso agrees: “Most of them [men], when we talk about injections, they’re like, ‘nah.’ Many men are afraid of needles. Especially when we talked about cabotegravir when it arrived. So many of them preferred to take the oral PrEP, actually. Until the six month injection came in. Now people are saying, ‘it’s better for me to just have the guts to take the injection, rather than taking pills every day’. It’s the promise of six months that makes you just say, ‘Now let me have the guts to do this thing’.”

On some men being resistant to HIV testing or prevention, he says: “To be honest, it’s a struggle. And talking to men about HIV prevention, it’s quite a challenge, but it is happening. And I would say it is better for them to come to the mobile clinic rather than to go to a traditional clinic. Sometimes men don’t like people to think that they are sick. So they come here, it’s quite quick and it’s efficient.”

From the researchers’ side, Rousseau pointed out that one in four of their clients for lenacapavir had been men, “similar numbers to those accessing oral PrEP,” she says.

Small nodules that disappear

Speaking to Spotlight, Plaatjie and Windvoel, along with Sinovuyo Plaatjie, 22, and Okuhle Potelwa, 19, who were also in the initial cohort in the study led by the Desmond Tutu Health Foundation, agree that small nodules formed under the skin where the lenacapavir was injected. “It was like small bumps,” said Plaatjie. “It’s not even visible, but you can just feel it when you touch yourself. And it’s not sore.”

Lenacapavir is administered via two injections of 1.5ml each in the buttocks, thigh, abdomen or upper arm. Speaking to Spotlight, the four recipients say the nodules had not been painful, and that the bumps started growing smaller after about a month and eventually disappeared. They did not experience any other side effects.

Inside the “Tutu teen truck” mobile clinic parked at Philippi Village, nurse Zimasa Zwide elaborates on the nodules. “Most of the time they form immediately, especially on the slimmer people,” she says. “So what I normally do when I’m injecting people, I ask them to feel the nodules so that they won’t be surprised at home later. They get smaller with time and they disappear depending on the body of each participant. And most of them are not reporting any pains.”

However, at a workshop hosted by the Bhekisisa Centre for Health Journalism at the end of August, Spotlight heard from two lenacapavir users, who did report initial pain along with “bumps” at the injection sites – for a few weeks following administration. At some facilities, icepacks are used to numb the injection site, either before or after the injection is administered, or both.

Glass vials of pale yellow liquid

During our conversation, Zwide opens a lenacapavir dosing kit. Inside there are two syringes, two glass vials of pale yellow liquid, and a plastic container with tablets.

She says: “It’s two injections. One on each side of the abdomen, well depending on the injection site that they are choosing. And two tablets which are taken on the day of the injection, plus two tablets that I give them to take home, and which needs to be taken exactly 24 hours later. The tablets, it’s a form of speeding up the absorption process of the lenacapavir.”

If these steps are followed, she says, a recipient is fully protected against HIV three days later. The recipient needs to visit the clinic a month later for an HIV test and follow-up treatment. Zwide says the most patients she have injected with lenacapavir in her mobile clinic in a day were around six or seven people. This is her maximum capacity, she says, as the required administration takes around two hours per person.

Demand for the jab

On demand for the jab, Zwide says: “On a daily basis, there are a lot of people who are interested in lenacapavir. When we started rolling out LEN, there were a couple of participants who were coming in, even ones who were older than 35. Unfortunately, in our service, we take from 15 to 35 years, so we couldn’t give them. But luckily as it was now rolled out at the local clinics, we can refer them to Phumlani Clinic [three kilometres away].” Phumlani Clinic is one of the 22 facilities in the Western Cape offering the injection.
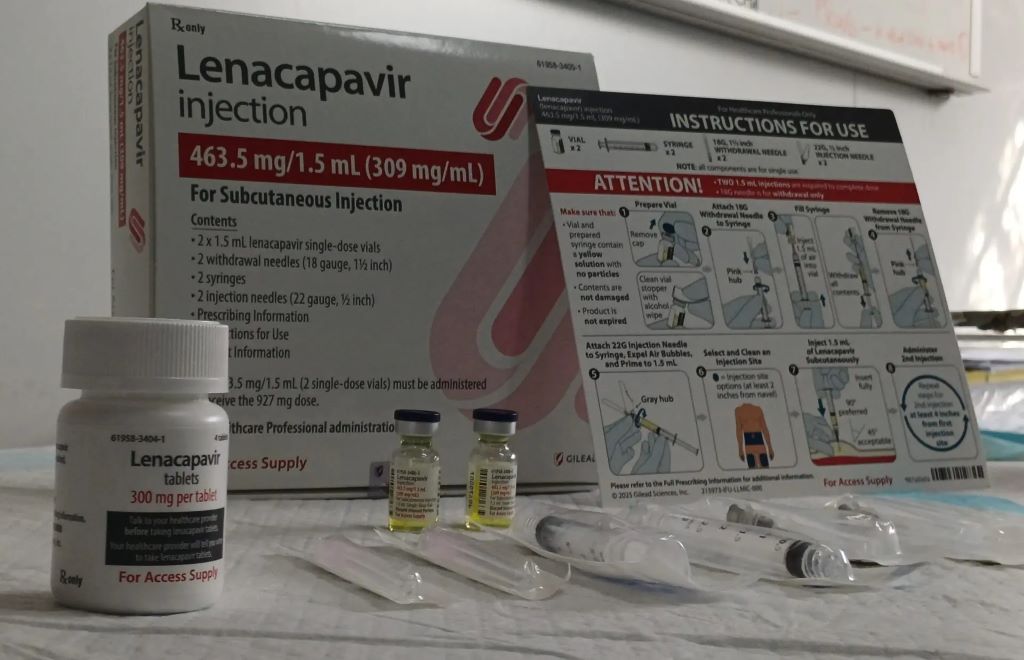
Contents of a Lenacapavir injection kit, including the drug vials, syringes, needles and instruction pamphlet, alongside a plastic pill container holding lenacapavir tablets. (Photo: Elri Voigt/Spotlight)

Responding to Spotlight’s questions around education on lenacapavir and demand creation in South Africa, Rousseau spoke highly of government’s rollout efforts.

“The national launch of lenacapavir in early June has created great demand and awareness of lenacapavir,” she says.

In addition, Mphambaniso points out the value of creating awareness about HIV prevention strategies and lenacapavir on channels that reach young people, specifically social media like TikTok.

Goeiman explained distribution of the medicine around the country. “Lenacapavir is procured centrally by the National Department of Health and distributed to provinces through phased deliveries. The Department continues to actively manage available stock to ensure equitable access throughout the phased rollout.” Technically, the department is procuring the medicines from the pharmaceutical company Gilead Sciences using money from the Global Fund (a large multinational donor).

For now, lenacapavir supply in South Africa remains highly constrained. That is expected to change once generic versions of the drug are registered and marketed in South Africa. Gilead have granted several companies licenses to produce generics. One of those, the Indian pharmaceutical company Hetero, has already filed a lenacapavir generic with the South African Health Products Regulatory Authority.

It seems plausible that the first lenacapavir generics will be approved in the first half of 2027 and indications are that the Department of Health will be quick to move to procuring lenacapavir generics on tender. Once that happens, the programme should expand rapidly with the aim of eventually covering all public healthcare facilities in the country.

This article was first published by Spotlight – health journalism in the public interest. Sign up to the Spotlight newsletter.

Patients are Missing out on the Cardiovascular Benefits of Antihypertensives

Credit: Pixabay CC0

The true impact of missing doses of blood pressure-lowering medication will be demonstrated in a presentation at ESC Congress 2026.[1] 

Approximately 1.4 billion adults worldwide aged 30–79 years are estimated to have high blood pressure (hypertension),[2] one of the most significant risk factors for disease burden.[3] Despite the proven benefits of blood pressure-lowering medication in reducing cardiovascular events, around half of patients do not take them as prescribed.[4] 

“We have evidence that poor adherence to antihypertensive medication is associated with worse outcomes,[5]” explained presenter, Miss Qianqian Yang from the University of Oxford, UK. “However, previous data has come from observational studies and could be confounded by other factors. We undertook an analysis of randomised trial data to assess the true impact of adherence on the benefits of antihypertensive treatment.” 

A meta-analysis was conducted of patient-level data from 91 339 participants in nine trials where an antihypertensive regimen (intervention group) was compared with another treatment (comparator group: either placebo or a less-intensive regimen). Participants who took at least 80% of their assigned treatment were classified as having higher adherence, while those who took less than 80% were classified as lower adherence. 

“A decline in adherence over time was apparent, even in the structured setting of trials,” noted Miss Yang. Overall, the proportion of patients classified as having higher adherence was 88% in the first year and only 79% by year five. 

In patients with higher adherence, systolic blood pressure was reduced by 5.2mmHg in the intervention group vs. the comparator group. In patients with lower adherence, the reduction was only 3.0mmHg. 

Next, the researchers studied the impact of adherence on major cardiovascular disease defined as stroke, myocardial infarction or ischaemic heart disease and heart failure causing death or hospitalisation.  

The incidence of major cardiovascular disease was significantly reduced by 11% in the intervention group vs the comparator group in patients with higher adherence, but there appeared to be no significant reductions in patients with lower adherence. 

“Notably, our results reinforce the saying that ‘drugs don’t work in patients who don’t take them.’ Patients with lower adherence derived little or no cardiovascular benefit, whereas those with higher adherence had greater reductions in blood pressure and prevention of cardiovascular events,” said Miss Yang. 

According to the authors, adherence assessment and education should be more prominent in hypertension management. In addition, strategies that help improve adherence should be promoted. These include simplifying regimens, using single-pill combinations to reduce the medication burden and using longer-acting agents where the effect of an occasional missed dose is less. 

Commenting on the findings, Professor Felix Mahfoud, Chair of the ESC Communication Committee, said: “For years, we have neglected non-adherence to medication as a cause for uncontrolled hypertension. Assessment of adherence should become a routine part of hypertension care so patients do not miss out on life-saving benefits. As healthcare providers, we are here to have open, non-judgemental conversations with our patients about any barriers they may have to taking medication, to help improve adherence.” 

References

[1] ‘Adherence to antihypertensive therapy and cardiovascular outcomes: an individual participant data meta-analysis of randomised controlled trials’ presented during the New therapeutic strategies targeting renin-angiotensin-aldosterone system in hypertension session at ESC Congress 2026 on 30 August from 08:15 to 09:45 in Room Vienna (ICM). 

[2] World Health Organization, 2025. Global report on hypertension 2025-High stakes: turning evidence into action.  

[3] GBD 2023 Disease and Injury and Risk Factor Collaborators. Burden of 375 diseases and injuries, risk-attributable burden of 88 risk factors, and healthy life expectancy in 204 countries and territories, including 660 subnational locations, 1990−2023: a systematic analysis for the Global Burden of Disease Study 2023. Lancet. 2025;406:1873−1922. 

[4] Abegaz TM, Shebab S, Gebreyohannes EA, et al. Nonadherence to antihypertensive drugs: A systematic review and meta-analysis. Medicine (Baltimore). 2017;96:e5641. 

[5] Chowdury R, Khan H, Heydon E, et al. Adherence to cardiovascular therapy: a meta-analysis of prevalence and clinical consequences. Eur Heart J. 2013;34:2940−2948. 

Source: European Society of Cardiology

Women’s Health Matters Conference 2026 Puts Women’s Health at the Centre Of South Africa’s Healthcare And Workplace Agenda

The inaugural Women’s Health Matters Conference 2026, sponsored by Discovery Health, will take place on Thursday, 3 September 2026, at GIBS Business School in Johannesburg. Supported by Spar Group, the event will bring together leaders from healthcare, business, academia and civil society to tackle some of the most pressing health issues facing women in South Africa today.

Across a full-day programme, delegates will explore women’s health at every stage of life, from reproductive health, pregnancy and childbirth to menopause, cancer prevention and mental wellbeing. Discussions will also shine a spotlight on critically important issues that continue to receive insufficient attention, including period poverty, endometriosis and the health impact of gender-based violence.

Dr Noluthando Nematswerani, Chief Clinical Officer at Discovery Health and headline sponsor of the conference, will open the programme with an address on Women’s Health Through the Life Course. Her presentation will highlight the importance of data-driven insights, prevention, early intervention and equitable access to care in improving health outcomes for women across their lifespan.

“Supporting women’s health requires a life-course approach. Improved outcomes are achieved through a strong focus on health promotion, disease prevention, early intervention, and timely access to appropriate care. It also demands a coordinated response from healthcare systems, employers, and communities that reflects the changing needs and challenges women experience throughout their lives. Discovery is proud to support a platform that unites these stakeholders around meaningful, action-oriented solutions,” says Dr Nematswerani.

The conference programme will move beyond awareness and explore the practical actions required to transform healthcare systems, workplaces, communities, and public policy in support of women’s health.

Key conference discussions will include:

Women’s Health Across the Life Course Exploring prevention, early intervention and access to care across reproductive health, maternity care, cancer, mental health and midlife health.

Pregnancy and Birth in South Africa Addressing high-risk pregnancies, preventable complications, informed decision-making and respectful maternity care.

Period Poverty and Access to Dignity Examining the affordability of menstrual products, menstrual health education, stigma, and the role of schools, workplaces, government and public-private partnerships in improving access.

The Endometriosis Diagnosis Gap Exploring the impact of delayed diagnosis on chronic pain, fertility, treatment outcomes and women’s participation in the workplace.

The Menopause-Ready Workplace Focusing on manager education, employee support, healthcare benefits and practical workplace interventions to better support women during menopause.

Closing the Women’s Cancer Care Gap Covering screening, early diagnosis, treatment access, survivorship and the role of employers and healthcare funders in improving outcomes.

GBV Is a Women’s Health Crisis Examining the physical and mental health consequences of gender-based violence, and the importance of survivor-centred healthcare, support services and prevention strategies.

SPAR will place a special focus on period poverty through a session led by Mpudi Maubane, National PR, Communications and Sponsorship Manager at SPAR, titled “Period Poverty: Dignity Should Not Depend on Income.”

“Period poverty extends far beyond access to menstrual products. When girls and women are unable to manage menstruation safely and with dignity, it affects school attendance, workplace participation, confidence and future opportunities. Addressing this challenge requires solutions that combine access, education and sustained partnerships to ensure that menstruation never becomes a barrier to full participation in society,” says Maubane.

The discussion will continue in a panel session titled “From Products to Policy: What It Will Take to End Period Poverty,” which will explore how business, government, educational institutions and community organisations can collaborate to develop sustainable, long-term solutions.

The programme features contributions from leading experts and advocates in women’s health, including clinical psychologist and founder the CBT group Dr Colinda Linde, obstetrician and gynaecologist Dr Sumayya Ebrahim, menstrual health activist Candice Chirwa, reproductive medicine specialist Prof Zozo Nene, menopause researcher and practitioner Dr Nicole Jaff, Co-CEO Tiko Benoit Renard, and  head of oncology risk management and care coordination, discovery health Dr Kagiso Seripe.

The Women’s Health Matters Conference is expected to bring together between 200 and 250 stakeholders, including healthcare professionals, medical schemes and insurers, corporate and HR leaders, government representatives, NGOs, academics, researchers, workplace wellbeing practitioners and women leaders.

The conference will conclude with a forward-looking session, “From Awareness to Action,” focused on identifying practical commitments and collaborative actions that healthcare providers, employers, policymakers and communities can take forward beyond the event to create meaningful and lasting change in women’s health.

Event Details

Event: Women’s Health Matters Conference 2026 Date: Thursday, 3 September 2026 Registration: 08:30 Conference: 09:00 – 17:00 Venue: GIBS Business School, Johannesburg Headline Sponsor: Discovery Health

Discovery Health’s registered wellness providers will be on-site from 08:00 to 19:00, offering a complimentary Wellness Health Screening Experience for all attending delegates and guests. This includes glucose, cholesterol, blood pressure and BMI checks. Conference delegates will have the opportunity to gain valuable insights into their health and wellness throughout the day.

To buy tickets please email James@creativespacemedia.co.za

GLP-1s do not Cause Major Psychiatric Harm, Review Shows

Photo by Haberdoedas on Unsplash

There is no link between the widely used diabetes and obesity medications known as GLP-1 receptor agonists and increased suicidal thoughts, depression or other serious psychiatric harm based on an integrative review of current scientific evidence conducted by researchers at New Mexico State University and the University of Nevada, Las Vegas.

The review, published in the journal Diabetology, traced the earliest concerns raised over GLP-1 RA therapies and found that after subsequent investigations, the medications do not increase psychiatric risk.

“GLP-1 RAs have become a cornerstone treatment for Type 2 diabetes and obesity, now used by tens of millions of patients worldwide,” said Jagdish Khubchandani, a professor of public health at NMSU, who co-authored the study with Kavita Batra, executive director of medical research and scholarly activities at the UNLV Kirk Kirkorian School of Medicine.

Reports that GLP-1s might trigger suicidal ideation, depression or anxiety began appearing  soon after the medications gained mainstream popularity. Those reports then prompted formal safety reviews by the U.S. Food and Drug Administration and the European Medicines Agency, beginning in 2023.

The research team analyzed five years of mechanistic, pharmacovigilance, observational and regulatory evidence to trace how early reports were investigated and how the scientific and regulatory consensus shifted over time. Earlier this year, the FDA removed its suicidality warning from GLP-1 medications.

“When reports of depression and suicidal thoughts first surfaced with GLP-1 RA use, they came from patients and doctors voluntarily reporting what they saw, and such reports can raise a question, but can’t answer it,” Batra said. “Since then, studies following millions of patients, including a pooled analysis of 91 clinical trials, have found no increase in psychiatric risk. But an answer for millions isn’t an answer for everyone. The right response is to screen and check in with each patient, not to take an effective treatment off the table.”

The review found that early warning signals were largely tied to one drug from selected patient groups, while larger controlled studies often pointed in contradictory directions – something the research team attributes to study design rather than the drugs themselves.

Khubchandani said spontaneous adverse-event reports can be skewed by media attention, by the fact that people with obesity and diabetes already have higher baseline rates of depression and suicidality, and by more frequent medical visits among treated patients that create more opportunities for symptoms to be reported. Controlled studies that account for these factors do not show exceptionally high risks, he added.

Still, the review found that some groups using GL-P1s may need closer monitoring. Patients already taking antidepressants or benzodiazepines showed a substantially amplified reporting signal for suicidal ideation, suggesting that any residual risk may be concentrated among those with pre-existing psychiatric vulnerability rather than the general patient population.

“Depression is more common in people with Type 2 diabetes than in the general population, and it works in both directions: Depression makes diabetes harder to manage, and diabetes makes depression more likely,” Batra said. “So, the mood symptoms a patient reports on any diabetes medication may have been there long before the prescription. That’s exactly why asking about mental health should be a routine part of diabetes care, not a special step reserved for when a drug is under suspicion.”

Khubchandani said the pace of research on GL-P1 medications needs to catch up with their pace of usage, particularly among groups like adolescents, those with serious mental illnesses and other groups underrepresented in clinical trials to date.

 “Just like for several other medications, the decision to use GLP-1 RA should include individualized screening of patients for psychiatric history and suicidality before starting treatment, watching more closely for patients with a history of mood disorders or concurrent psychiatric medication use, and educating patients and caregivers to report mood changes promptly,” Khubchandani said.

To read the review, visit https://www.mdpi.com/2673-4540/7/8/144.

Source: New Mexico State University

Targeted Therapy for Metastatic Pancreatic Cancer Receives Approval in US

Pancreatic cancer. Credit: Scientific Animations CC BY-SA 4.0

The US Food and Drug Administration has approved daraxonrasib, to be sold under the brand name Rasonque, for the treatment of adults with metastatic pancreatic adenocarcinoma who have received at least one prior systemic therapy or who are not candidates for multiagent systemic therapy. The approval follows results from an international phase 3 study co-led by UCLA that showed the targeted therapy significantly extended overall survival and reduced the risk of death by 60% compared with standard chemotherapy.

In the study, patients who received daraxonrasib, an oral RAS(ON) multi-selective inhibitor designed to block active RAS signaling, one of the primary drivers of pancreatic cancer, lived a median of 13.2 months compared with 6.7 months for those who received investigator’s choice chemotherapy.

The FDA approval provides a new treatment option for patients with metastatic pancreatic cancer, a disease that remains among the most lethal cancers and has historically had limited effective therapies.

The results were published in the New England Journal of Medicine and presented earlier this year at the annual meeting of the American Society of Clinical Oncology in Chicago.

“This FDA approval represents an important milestone for patients with metastatic pancreatic cancer, who have needed new and more effective treatment options,” said Dr. Zev Wainberg, professor of medicine and investigator at the UCLA Health Jonsson Comprehensive Cancer Center and co-first author of the study. “The results of this trial demonstrate that targeting RAS can meaningfully extend survival and improve disease control, and it is exciting to see these findings translated into an approved treatment for patients.”

More than 90% of tumours are driven by alterations in the RAS signalling pathway, particularly mutations in KRAS, a gene that helps regulate cell growth. When mutated, the gene can lock cells into a constant growth state, fuelling tumour development. Despite decades of research, RAS proteins have proved notoriously difficult to target with drugs.

Unlike earlier targeted therapies that focused on a single mutation subtype, daraxonrasib is part of a new class of therapies designed to inhibit multiple RAS mutations, including G12, G13 and Q61 alterations that dominate pancreatic cancer.

The study involved 500 patients with metastatic pancreatic cancer whose disease had already progressed after one previous treatment from 60 clinical sites across six countries. Participants were randomly assigned to receive either daraxonrasib orally once daily (248 patients) or standard chemotherapy chosen by their doctor (252 patients). About 92% of patients had RAS G12 mutations.

In addition to improved overall survival, patients treated with daraxonrasib experienced significantly longer disease control. Median progression-free survival was 7.2 months compared with 3.6 months for chemotherapy, effectively doubling the time before cancer progression, in the overall study population.

Tumour shrinkage was also more frequent in the daraxonrasib group, with approximately 30% of patients achieving an objective response in the overall study population compared with about 11% in the chemotherapy group. Patients receiving the targeted therapy also experienced slower worsening of pain and better preservation of quality of life over time.

“While most patients had RAS G12 mutations, the benefit appeared generally consistent across different patient groups and mutation types,” said Wainberg, who is also the co-director of the UCLA GI Oncology Program. “These findings support the idea that blocking active RAS signaling will become an important treatment strategy for pancreatic cancer.”

The most common side effects of daraxonrasib include rash, diarrhoea, stomatitis, nausea, fatigue, vomiting, abdominal pain, enema, decreased appetite and haemorrhage. The prescribing information also includes warnings and precautions for dermatologic and soft tissue toxicity, stomatitis and oral disorders, diarrhoea, gastrointestinal perforation, interstitial lung disease or pneumonitis and embryo-foetal toxicity.

Rasonque is manufactured by Revolution Medicines.

Source: UCLA Health

Cortisone Eye Drops can Save the Sight of Extremely Premature Babies

Photo by Hush Naidoo on Unsplash

Researchers at the University of Gothenburg and Sahlgrenska University Hospital have conducted the first randomised clinical trial in the world to test cortisone eye drops to slow the progression of serious eye disease in extremely premature babies. The results suggest that the intervention can reduce the need for invasive treatment for Retinopathy of prematurity (ROP), a disease that causes blindness in 35 000 children worldwide each year.

ROP occurs when the blood vessels in the retina develop abnormally in very premature babies. In severe cases, laser treatment or injections into the eye are currently required to prevent vision loss and blindness. These treatments are invasive and destructive, and children who require treatment are at the greatest risk of blindness and visual impairment.

The Swedish multicentre study DROPROP involved 100 children born before 30 weeks of pregnancy. The children had a severe but not yet treatment-requiring form of ROP and were randomised to receive either dexamethasone eye drops or placebo.

Large clinical effect

The results showed that 20 percent of the children who received dexamethasone developed treatment-requiring ROP, compared with 38 percent in the placebo group. This corresponds to a 47 percent reduction in relative risk. The difference did not reach statistical significance but showed a large clinical effect.

“The results are very promising because the treatment is simple, inexpensive and non-invasive. In a significant proportion of children, we were able to reduce the need for laser and ocular injections in very fragile premature babies”, says Ann Hellström, professor at the University of Gothenburg and chief physician at Sahlgrenska University Hospital.

The researchers also closely monitored any side effects. No clinically significant difference in complications was seen between the groups. No clear signs of serious hormonal or metabolic side effects were observed.

Long-term follow-ups

The study, funded by the Swedish Research Council, was conducted at six university hospitals and eight county hospitals in Sweden between 2022 and 2025 and is the first double-blind randomized clinical trial of dexamethasone eye drops in ROP.

The researchers are now planning long-term follow-ups of the children to investigate vision development and possible late effects of the treatment.

“There is a great global need for simpler treatments for ROP, especially in parts of the world where access to specialist care is limited. If eye drops can prevent severe ROP, it could save the sight of many children around the world”, says Ann Hellström.

Study: Dexamethasone Eye Drops to Prevent Treatment-Requiring Retinopathy of Prematurity: The DROPROP Trial (JAMA Pediatrics)

Source: University of Gothenburg

Brain Activity Patterns may “Tag” Experiences for Later Memory Making During Sleep

Theta oscillations during learning predicted which experiences were remembered after sleep

Photo by Cottonbro on Pexels

The brain may “tag” experiences during learning to better consolidate the memory of them during sleep, according to a study published August 27th in the open access journal PLOS Biology by Dan Denis from the University of York, United Kingdom, and colleagues.

Most people do not remember every experience they’ve ever had. Instead, the brain consolidates some experiences – but not others – into long-term memory during sleep, suggesting that some experiences are “tagged” during learning for later encoding into memory.

To better understand how the brain selected experiences for later memory consolidation during sleep, the authors of this study collected data from 31 participants using electroencephalography (EEG) to measure patterns of brain activity. The participants learned sets of object-word pairs and were tested on them immediately and after a two-hour break. During one visit, participants were allowed to sleep, and in the other, they remained awake. As they learned and rested, the scientists analysed their EEG readings, matching the repetitive oscillations of brain activity during learning to those that were remembered after the participants’ sleep period.

The authors found that word-object pairs associated with theta oscillations between 3-8Hz during learning were more likely to be remembered after a period of sleep, but not after staying awake. The theta activity during learning predicted more coupling between slow neural oscillations during sleep and sleep spindles – bursts of brain activity. The slow oscillations and the sleep spindles were in turn associated with better memory performance after sleep. While the study only tested memory after two hours, and further studies would be needed to determine if memories persisted, the authors suggest that theta oscillations may indicate a mechanism by which the brain identifies experiences to consolidate into memories during sleep. 

The authors add, “How the brain decides what is important to remember and what can be forgotten is still a mystery. These new findings help to answer that question, by uncovering for the first time a signature of neural activity which instructs the brain which experiences to process during sleep and form into long-term memories.

“If we remembered everything that we experienced, our brains would quickly reach system overload. By selectively prioritising important events in our lives, be they emotionally salient or important for the future, we are able to use our past experiences to help guide our interactions in the world.

“Although it is typically adaptive to prioritise certain kinds of information, there are cases where this becomes maladaptive. For example, in depression, individuals tend to over allocate attentional resources to negative information, whilst disregarding or downplaying more positive experiences. Our new findings shed new light on the brain processes that dictate what is ultimately remembered, and may open new avenues for understanding and treating common mental health problems such as depression.”

Provided by PLOS

Statins Cut Heart Attack and Stroke Risk in Older People by 30%

Photo by Kampus Production

A world-first clinical trial conducted by Monash University researchers has shown that cholesterol-lowering medication can reduce heart attack and stroke in people aged over 70 years.

Statins are commonly prescribed to manage high cholesterol in people up to 75 years, and are known to reduce the risk of heart attack and stroke. But until now it was unclear whether they were effective in older people.

New research from Monash University, published in the New England Journal of Medicine and presented concurrently at the European Society of Cardiology Congress 2026, found the medication decreases the risk of a first major cardiovascular event by 30 per cent for adults aged over 70 living independently.

The Statins in Reducing Events in the Elderly (STAREE) Trial is the first randomised controlled trial of statin therapy to examine whether the drugs could help in older people who have historically been overlooked in clinical trials.

This landmark, ten-year trial analysed the cardiovascular outcomes of almost 10 000 participants while they took either a statin or placebo.

Lead researcher Adjunct Professor Sophia Zoungas, from the Monash School of Public Health and Preventive Medicine, said the findings will change the way clinicians manage cardiovascular risk in older people.

“What we hope to see, now that we have provided such strong evidence, are updated treatment guidelines to help clinicians make use of this new finding,” Professor Zoungas said.

The global prevalence of cardiovascular disease is expected to almost double from 600 million in 2025 to more than one billion affected adults in 2050. An estimated 2 ,000 older Australians suffer from major cardiovascular events, like heart attack and stroke, each year. The risk increases with age, so people aged over 70 are automatically in a high risk category regardless of lifestyle or other factors.

“The risk of heart attack and stroke is a major concern for older people,” Professor Zoungas said. “Knowing there is a safe and effective measure for lowering that risk will be a huge reassurance to older people and their families.

“Anyone who has seen a loved one impacted by cardiovascular disease will know just how important prevention is.”

Co-author Professor Mark Nelson, a prominent general practitioner, Adjunct Professor at the Monash School of Public Health and Preventive Medicine and Research Fellow at Menzies Institute for Medical Research at the University of Tasmania, said this is critical evidence to support GPs in their decision-making around cardiovascular health in older people.

“This was a particularly important trial because it was conducted in the community, with more than 3400 GPs taking part across Australia,” Professor Nelson said. “In light of this new evidence, older patients should have a conversation with their GP about whether statins are an appropriate treatment for their cardiovascular health to help them remain fit and healthy.”

Read the research paper: http://doi.org/10.1056/NEJMoa2607314

Source: Monash University

Doctors Often Disagree on Auscultation Findings in Paediatric Pneumonia

Photo by cottonbro studio

For generations, a stethoscope has been one of the most essential tools for diagnosing pneumonia. But a new study suggests that what doctors hear through it may depend on who is listening.

In this cohort study, US investigators who are part of the Pediatric Emergency Care Applied Research Network analysed data from children and teens diagnosed as having community-acquired pneumonia (CAP). The findings showed that clinicians often disagreed about their findings on physical exam, including decreased breath sounds, crackles (wet, bubble-likes sounds when air flow is blocked), and rhonchi (abnormal breathing that sounds like snoring or rattling) – symptoms frequently associated with pneumonia. 

Current US guidelines recommend diagnosing CAP based on clinical findings rather than chest X-rays in children who are treated as outpatients. 

Same patient, different findings

For the study, published in JAMA Network Open, researchers analysed data from 252 participants, ages 3 months to 17 years, diagnosed with CAP at one of seven academic paediatric emergency departments across the United States. Two clinicians independently examined each patient within 60 minutes of one another and recorded their findings.

None of the physical exam findings met the researchers’ predetermined threshold for acceptable interrater reliability, a measure of how much different clinicians agree when analysing the same data or event. Wheezing (kappa value [κ], 0.50) and chest retractions (κ, 0.49) were the exam findings clinicians agreed on the most. Even so, agreement was modest.

Agreement was significantly lower for decreased breath sounds and crackles, which both had κ values under 0.25.

The findings raise questions about how heavily clinicians should rely on listening to the lungs when diagnosing pneumonia. 

“This variability is not a trivial concern,” write Susan Lipsett, MD, of Boston Children’s Hospital, and Mark Neuman, MD, MPH, of Harvard Medical School, in an accompanying commentary. When examination findings vary depending on the observer, “their utility as diagnostic anchors is diminished” and their ability to appropriately guide treatment is compromised.

“If physicians cannot consistently agree on the presence of auscultatory findings, treatment decisions may hinge more on examiner interpretation than underlying pathology,” Lipsett and Neuman write. “This variability may contribute to well-documented differences in antibiotic prescribing and chest radiograph use across institutions.”

Why lung sounds can be hard to interpret

Several factors could explain the disagreement. Accurately interpreting lung sounds can depend on background noise, patient cooperation, and clinician experience—factors that “become even more challenging in a busy emergency department,” write Lipsett and Neuman. Children also have more flexible chest walls, which may make it harder to determine exactly where the sounds originate. What’s more, clinicians may also use terms like “crackles” to refer to slightly different things.

The commentators argue that the results strengthen the case for objective risk-assessment tools that combine factors such as fever, oxygen saturation, demographics, and selected clinical findings rather than relying on individual lung sounds. 

“By quantifying risk and reducing dependence on subjective auscultatory interpretation, clinical prediction tools may mitigate interobserver variability and promote more consistent decision-making regarding imaging and antibiotic therapy,

By Laine Bergeson

Source: University of Minnesota

SA is One Step Closer to a New TB vaccine, but There is a Lot of Work Ahead

By Russell Rensburg

Russell Rensburg is the Divisional Director of the Rural Health Advocacy Project which hosts the TB Accountability Consortium. (Photo: Supplied)

In March 2024, a pivotal clinical trial was launched to evaluate what might well become the first new tuberculosis vaccine on the market in more than a century. As anticipation mounts for the trial to deliver results, Russell Rensburg argues that we need to start preparing for a rollout of the jab, but that we should think of preparation more widely than just the technicalities of regulatory approval and drug supply.

Over the past few weeks, there have been ongoing discussions about a potential new TB vaccine coming to South Africa.

The leading new vaccine candidate M72/AS01E TB or M72 for short is currently being evaluated in a large phase three clinical trial that started in March 2024. The trial has been running ahead of schedule and it is possible that results might be ready in the next year. If those results are positive, registration with the South African Health Products Regulatory Authority should follow quite soon after.

As all this happens, preparations for possible future manufacturing of the jab are already underway. In July, the Serum Institute of India announced an agreement with the Gates Medical Research Institute to prepare for large-scale production should the trial be successful and the vaccine approved.

And at the same time South Africa’s National Department of Health has started to engage in discussions about the roadmap for a possible vaccine rollout.

The optimism is high, and rightly so. It’s the first time in more than 100 years that we have reached this point with a new TB vaccine. Given the size of South Africa’s population at approximately 63 million people, its share of TB deaths worldwide is striking. WHO data shows that of the over 1.2 million TB deaths, around 54 000 were reported in South Africa. The idea that a new jab can arrest the alarming death rate of this curable disease and change the trajectory of TB in the country is exciting.

But the point that we are at should also prompt an urgent question. If a new TB vaccine proves successful, will South Africa actually be ready to use it?

For a country carrying one of the world’s highest TB burdens, a successful vaccine could fundamentally change our response to the disease. But the regulatory approvals that we will hopefully see next year or the year after would only be the beginning.

Getting community buy-in

To effectively roll out this vaccine, South Africa would need the buy-in of communities who trust that this vaccine could help them and are willing to encourage their fellow community members to take it up.

This negotiation could be harder than we think.

The country does not have to wait for the vaccine to be approved to begin this work. The opportunity to start building the community trust already exists. How? With the current rollout of a new TB test.

The National Department of Health is implementing a demonstration project to assess the health system’s readiness to introduce a new near point-of-care TB diagnostic test into the public healthcare system. The test would mean that people can get TB tests done at the clinic and get a result virtually immediately.

Many of South Africa’s TB deaths are due to late diagnosis. The new test presents the opportunity to shorten the gap between testing and diagnosis (samples don’t have to be sent off to labs) and could result in earlier initiation into care, which will potentially contribute to reduced mortality.

The near point-of-care testing sites are being deployed across the country in district hospitals, community health centres and primary healthcare clinics.

But a very important part of that work is not simply understanding whether the health system is ready for this diagnostic approach, it’s how communities are engaged and mobilised to understand and use it.

Testing community engagement

The community mobilisation and demand-creation component allows us to work directly with communities to understand what it takes to introduce a new TB intervention in a way that does not simply place a new technology into the health system and assume that people will use it.

Alongside measuring diagnostic performance, we should be deliberately testing models of community engagement: working with community health workers, TB survivors, civil society organisations and trusted local leaders; building people’s understanding of TB; listening to their concerns; identifying misinformation early; and understanding which messages, platforms and messengers people trust.

If we do this well, when a TB vaccine eventually becomes available, we will not be starting the conversation from zero. We will already have communities that have been part of the journey of TB innovation, systems for listening and responding to their concerns, and trusted people who can help communities navigate new information. That is what genuine vaccine preparedness should look like. It is not only preparing the regulatory pathway, procurement systems and cold chain. It is preparing the people and communities for whom the vaccine is ultimately intended.

Yet community engagement is too often treated as something that happens at the end of the process: develop the intervention, approve it, procure it and then ask civil society to persuade people to use it.

Trust cannot be manufactured through a communications campaign launched three months before rollout. Trust in a vaccine is inseparable from trust in the health system delivering it. That is why community investment should be considered part of vaccine preparedness itself—not an optional communications budget added later.

The civil society bridge

Civil society has a particularly important role here. Government develops policy, researchers generate evidence and health workers deliver services. Civil society often provides the bridge between those systems and communities.

Community organisations understand local languages, stigma, misinformation, barriers to accessing care and, importantly, the questions people may be reluctant to ask government or healthcare providers.

We should therefore begin strengthening community systems now: building the capacity of trusted community leaders; developing TB vaccine literacy; establishing mechanisms for community-led monitoring; and integrating conversations about vaccination into existing TB, HIV and primary healthcare services.

This is not about convincing people to take a vaccine that has not yet been approved. It is about creating the conditions in which people can eventually make informed decisions.

Ultimately, the measure of success will not be how quickly South Africa approves or procures a new TB vaccine. It will be whether the people who stand to benefit from it understand it, trust the systems delivering it, and are able and willing to access it.

The scientific breakthrough may happen in a laboratory. But whether it changes the trajectory of TB in South Africa will be decided in our communities.

– Rensburg is divisional director of the Rural Health Advocacy Project, which hosts the TB Accountability Consortium.

Disclosure: This piece was published by Spotlight – health journalism in the public interest. The Gates Medical Research Institute mentioned in this article is a non-profit organisation and subsidiary of the Gates Foundation. Spotlight receives funding from the Gates Foundation but is editorially independent – an independence that the editors guard jealously. Spotlight is a member of the South African Press Council.