Category: Vaccines

SA is One Step Closer to a New TB vaccine, but There is a Lot of Work Ahead

By Russell Rensburg

Russell Rensburg is the Divisional Director of the Rural Health Advocacy Project which hosts the TB Accountability Consortium. (Photo: Supplied)

In March 2024, a pivotal clinical trial was launched to evaluate what might well become the first new tuberculosis vaccine on the market in more than a century. As anticipation mounts for the trial to deliver results, Russell Rensburg argues that we need to start preparing for a rollout of the jab, but that we should think of preparation more widely than just the technicalities of regulatory approval and drug supply.

Over the past few weeks, there have been ongoing discussions about a potential new TB vaccine coming to South Africa.

The leading new vaccine candidate M72/AS01E TB or M72 for short is currently being evaluated in a large phase three clinical trial that started in March 2024. The trial has been running ahead of schedule and it is possible that results might be ready in the next year. If those results are positive, registration with the South African Health Products Regulatory Authority should follow quite soon after.

As all this happens, preparations for possible future manufacturing of the jab are already underway. In July, the Serum Institute of India announced an agreement with the Gates Medical Research Institute to prepare for large-scale production should the trial be successful and the vaccine approved.

And at the same time South Africa’s National Department of Health has started to engage in discussions about the roadmap for a possible vaccine rollout.

The optimism is high, and rightly so. It’s the first time in more than 100 years that we have reached this point with a new TB vaccine. Given the size of South Africa’s population at approximately 63 million people, its share of TB deaths worldwide is striking. WHO data shows that of the over 1.2 million TB deaths, around 54 000 were reported in South Africa. The idea that a new jab can arrest the alarming death rate of this curable disease and change the trajectory of TB in the country is exciting.

But the point that we are at should also prompt an urgent question. If a new TB vaccine proves successful, will South Africa actually be ready to use it?

For a country carrying one of the world’s highest TB burdens, a successful vaccine could fundamentally change our response to the disease. But the regulatory approvals that we will hopefully see next year or the year after would only be the beginning.

Getting community buy-in

To effectively roll out this vaccine, South Africa would need the buy-in of communities who trust that this vaccine could help them and are willing to encourage their fellow community members to take it up.

This negotiation could be harder than we think.

The country does not have to wait for the vaccine to be approved to begin this work. The opportunity to start building the community trust already exists. How? With the current rollout of a new TB test.

The National Department of Health is implementing a demonstration project to assess the health system’s readiness to introduce a new near point-of-care TB diagnostic test into the public healthcare system. The test would mean that people can get TB tests done at the clinic and get a result virtually immediately.

Many of South Africa’s TB deaths are due to late diagnosis. The new test presents the opportunity to shorten the gap between testing and diagnosis (samples don’t have to be sent off to labs) and could result in earlier initiation into care, which will potentially contribute to reduced mortality.

The near point-of-care testing sites are being deployed across the country in district hospitals, community health centres and primary healthcare clinics.

But a very important part of that work is not simply understanding whether the health system is ready for this diagnostic approach, it’s how communities are engaged and mobilised to understand and use it.

Testing community engagement

The community mobilisation and demand-creation component allows us to work directly with communities to understand what it takes to introduce a new TB intervention in a way that does not simply place a new technology into the health system and assume that people will use it.

Alongside measuring diagnostic performance, we should be deliberately testing models of community engagement: working with community health workers, TB survivors, civil society organisations and trusted local leaders; building people’s understanding of TB; listening to their concerns; identifying misinformation early; and understanding which messages, platforms and messengers people trust.

If we do this well, when a TB vaccine eventually becomes available, we will not be starting the conversation from zero. We will already have communities that have been part of the journey of TB innovation, systems for listening and responding to their concerns, and trusted people who can help communities navigate new information. That is what genuine vaccine preparedness should look like. It is not only preparing the regulatory pathway, procurement systems and cold chain. It is preparing the people and communities for whom the vaccine is ultimately intended.

Yet community engagement is too often treated as something that happens at the end of the process: develop the intervention, approve it, procure it and then ask civil society to persuade people to use it.

Trust cannot be manufactured through a communications campaign launched three months before rollout. Trust in a vaccine is inseparable from trust in the health system delivering it. That is why community investment should be considered part of vaccine preparedness itself—not an optional communications budget added later.

The civil society bridge

Civil society has a particularly important role here. Government develops policy, researchers generate evidence and health workers deliver services. Civil society often provides the bridge between those systems and communities.

Community organisations understand local languages, stigma, misinformation, barriers to accessing care and, importantly, the questions people may be reluctant to ask government or healthcare providers.

We should therefore begin strengthening community systems now: building the capacity of trusted community leaders; developing TB vaccine literacy; establishing mechanisms for community-led monitoring; and integrating conversations about vaccination into existing TB, HIV and primary healthcare services.

This is not about convincing people to take a vaccine that has not yet been approved. It is about creating the conditions in which people can eventually make informed decisions.

Ultimately, the measure of success will not be how quickly South Africa approves or procures a new TB vaccine. It will be whether the people who stand to benefit from it understand it, trust the systems delivering it, and are able and willing to access it.

The scientific breakthrough may happen in a laboratory. But whether it changes the trajectory of TB in South Africa will be decided in our communities.

Rensburg is divisional director of the Rural Health Advocacy Project, which hosts the TB Accountability Consortium.

Disclosure: This piece was published by Spotlight – health journalism in the public interest. The Gates Medical Research Institute mentioned in this article is a non-profit organisation and subsidiary of the Gates Foundation. Spotlight receives funding from the Gates Foundation but is editorially independent – an independence that the editors guard jealously. Spotlight is a member of the South African Press Council.

Sepsis Survivors Don’t Respond to Vaccines in the Same Way

Image from Rawpixel

People who have survived intensive care unit admission with sepsis don’t respond to vaccines in the same way as those who haven’t had sepsis, according to new clinical trial results. The findings suggest that more work is needed to understand why the vaccine-related immune response is altered in sepsis survivors, so that vaccination programmes can be tailored to reduce sepsis survivors’ risk of infections and improve long-term health outcomes.

Sepsis survivors can have a weakened or altered immune system, which can increase the risk of new infections and death. Fifteen per cent of sepsis survivors die within a year of leaving hospital, with a further six to eight per cent dying every year over the next five years.

The VACIRiSS trial, led by King’s College London and Guy’s and St Thomas’ NHS Foundation Trust and funded by the National Institute for Health and Care Research (NIHR), found that a vaccine that helps protect against serious illnesses like pneumonia and meningitis in the general population did not reduce the risk of future infections or re-hospitalisations in adults who had survived sepsis.

The findings were published in Science Translational Medicine.

The long-term health impacts of sepsis survivors may not be receiving enough attention in health care. In the UK, one in three sepsis survivors are re-hospitalised within 90 days, with the majority of these re-hospitalisations from infections, and one in six patients are no longer alive at the end of the first year after recovering from sepsis. Despite this, there is no routine long-term follow up care for sepsis survivors in the NHS.

Professor Manu Shankar-Hari, Professor of Critical Care Medicine at King’s College London and Principal Investigator on the trial

Sepsis, a misfiring of immune responses to infection, can cause failure of vital organs and death if not treated quickly. Globally, it’s estimated that there are about 166 million sepsis cases and 21 million deaths from sepsis each year. Those who survive (approximately 145 million patients globally every year) are at increased risk of long-term ill health, including from recurrent infections.

While sepsis survivors may receive vaccinations as part of established vaccination programmes (such as flu or pneumonia vaccinations for older adults), vaccinations are not part of standard of care for sepsis survivors.

In the trial, 214 sepsis survivors were randomly assigned to receive a vaccine, called PCV13, or a placebo injection. Participants were followed up for a year to see whether the vaccine reduced their risk of re-hospitalisation with infection or death.

Overall, the vaccine did not reduce re-hospitalisation with infection or death in sepsis survivors. While blood tests showed that many participants did produce immune responses to the vaccine, the responses varied widely from person to person. The differences in vaccine responses were linked to factors such as age, body weight, sex, and levels of altered immune system before vaccination.

The findings suggest that established vaccination programmes may need to be modified to provide better protection to sepsis survivors. However, more needs to be done to understand the varied responses in sepsis survivors to inform what changes are needed.

Source: King’s College London

Fridge-free Tetanus-diphtheria Vaccine Shows Promise of Reaching Millions Worldwide

Nurse and participant in the vaccine trial.

The world-first trial of a fridge-free tetanus-diphtheria vaccine has produced encouraging results that could improve access worldwide to crucial treatments, while reducing carbon emissions.

Around half of vaccines are wasted globally each year, according to the World Health Organization. Millions of doses are lost because of temperature changes during storage and transport. Fridge-free vaccines have the potential to transform vaccine delivery by reducing this dependence on refrigeration. This would improve access in more isolated communities and cut the environmental impact by reducing vast amounts of energy that lead to emissions.

This phase I study, led by the University of Southampton and University Hospital Southampton NHS Foundation Trust, found the vaccine was well tolerated, with no vaccine-related serious adverse events. Results are published in The Lancet group’s eClinicalMedicine.

Saul Faust , Professor of Paediatric Immunology and Infectious Diseases at the University of Southampton and Director of the NIHR Clinical Research Facility in Southampton, who led the study, said: “Keeping vaccines cold from the factory to the patient is one of the biggest challenges facing immunisation programmes worldwide. Our study suggests that this vaccine can remain safe and effective without refrigeration.

“If larger studies confirm these findings, this technology could help transform the way vaccines are stored and delivered around the world.”

The trial

The trial took place in the National Institute for Health and Care Research (NIHR) Clinical Research Facility at University Hospital Southampton and was delivered through the NIHR Biomedical Research Centre: Southampton . The reformulated vaccine, known as SPVX02, was developed by UK-based biotech company Stablepharma using its StablevaX technology.

The research shows that SPVX02 can be stored at temperatures of up to 30°C for at least two years without losing its effectiveness. Scientists are now investigating whether it can remain stable for as long as four years. Researchers have also demonstrated that the vaccine remains stable, and fully potent, after three cycles of extreme temperature fluctuation from -20°C to +40°C.

The randomised trial, which also involved the Medicines Evaluation Unit (MEU) in Manchester, enrolled 60 healthy adults. By 28 days after vaccination, all participants receiving SPVX02 achieved protective antibody levels against both tetanus and diphtheria, demonstrating immune responses comparable to licensed vaccines.

Next steps

The eClinicalMedicine publication follows the launch of a Phase 2b trial that will further assess the vaccine in a larger group of participants. Stablepharma’s technology platform, StablevaX, can be applied to vaccines, small molecules, peptides and biologics. They are currently working with a partner to thermostabilise small molecule oncology and anti-infective products, in addition to other vaccines.

Özgür Tuncer, Stablepharma CEO and Executive Director, said: “This peer reviewed validation represents a pivotal moment for our StablevaX platform and the future of thermostable vaccines. These findings strengthen the scientific and global health case for a new generation of fridge free vaccines, particularly in regions where cold chain limitations hinder equitable access.”

Health and Social Care Minister Diana Johnson said: “This pioneering research demonstrates how British innovation is helping to tackle some of the biggest challenges in global healthcare, and providing life-saving breakthroughs for use around the world.

“Right now, people are dying of preventable diseases all over the world, not due to a lack of vaccines, but a lack of refrigeration. Fridge-free vaccines have the potential to be a game-changer for global health, especially for people in remote communities, or regions affected by conflict.

“Backed by NIHR’s world-leading research, this breakthrough shows once again how our investment in science and life sciences is driving better health outcomes, while supporting economic growth and reinforcing the UK’s position at the forefront of medical innovation.”

Stablepharma’s SPVX02 vaccine has been developed with support from Innovate UK, part of UK Research and Innovation (UKRI). It is a reformulated version of the WHO-prequalified Tetadif tetanus-diphtheria vaccine. Scientists from the UK Health Security Agency (UKHSA) provided specialist laboratory testing.

Stablepharma expects to complete the clinical development programme for SPVX02 by 2027.

Source: University of Southampton

Wits VIDA Globally Advances Maternal Vaccine to Protect Newborns from GBS

Wits VIDA plays central role in global effort to help protect newborns from sepsis due to Group B Streptococcus (GBS).

Photo by ManuelTheLensman on Unsplash

Researchers from the Wits Vaccines and Infectious Diseases Analytics (Wits VIDA) Research Unit at the University of the Witwatersrand (Wits) have played a leading role in a landmark international phase 1 / 2 clinical trial demonstrating the safety and immunogenicity of an investigational maternal vaccine against Group B Streptococcus (GBS) – a major cause of life-threatening infections in newborn babies worldwide. The findings have been published in Nature Medicine.

The study evaluated Pfizer’s investigational hexavalent Group B Streptococcus conjugate vaccine candidate (GBS6) in both non-pregnant women and pregnant women, together with their infants. The trial found that the vaccine was generally well tolerated, generated robust immune responses against all six clinically important GBS serotypes, and resulted in efficient transfer of GBS-specific antibodies from vaccinated mothers to their babies.

Wits VIDA was central to the implementation and successful conduct of the clinical trial. South Africa was the primary recruiting country, contributing the overwhelming majority of study participants across both the early and later stages of the trial, reflecting the country’s internationally recognised expertise in maternal and infant vaccine research.

Group B Streptococcus is one of the leading causes of neonatal sepsis, meningitis and pneumonia, accounting for approximately 300 000 serious infections, including 100 000 deaths, in young infants globally each year. The greatest burden of GBS disease in infants occurs in Africa and other low- and middle-income countries, with South Africa reporting among the highest incidence globally (approximately 2-3 cases for every 1000 births). Also, maternal GBS infection could predispose to preterm labour and stillbirths.  Current prevention strategies based on intrapartum antibiotics have important limitations, particularly in resource-constrained settings, and do not protect against late-onset disease. Consequently, the WHO has designated a vaccine against GBS, to be given to women during pregnancy aimed at protecting their young infant, as a priority vaccine for development.

Professor Shabir Madhi, Director of Wits VIDA and one of the study’s senior investigators, said: “This publication represents another important milestone in the decades-long effort to develop an effective maternal vaccine against Group B Streptococcus. Maternal immunisation offers the opportunity to protect newborns during the most vulnerable first months of life, when they are at greatest risk of severe infection. These encouraging findings provide further evidence supporting continued development of this vaccine.”

The trial demonstrated comparable safety outcomes between vaccine and placebo recipients. Among pregnant participants, rates of adverse events, serious adverse events and delivery outcomes were similar between the two groups. Infants born to vaccinated mothers likewise had similar safety outcomes to those born to mothers receiving placebo. Importantly, vaccinated mothers developed high concentrations of antibodies that crossed the placenta efficiently, resulting in robust antibody levels in their infants at birth.

The publication builds on Wits VIDA’s longstanding leadership in vaccine research, which has contributed to the development and evaluation of vaccines against respiratory syncytial virus (RSV), rotavirus, pneumococcal disease, influenza virus, COVID-19 and now Group B Streptococcus. The unit continues to play a pivotal role in generating evidence that informs global maternal and child health policy.

The study also highlights the importance of South Africa’s clinical research infrastructure and its contribution to advancing vaccines designed to address diseases that disproportionately affect African populations.

While additional studies are required before the vaccine can be licensed, the results provide strong support for continued clinical development of maternal GBS vaccination as a strategy to reduce newborn deaths and severe infections worldwide.

Wits is currently enrolling in a phase 3 trial for GBS6 (NCT: NCT07160244).

About Wits VIDA

The Vaccines and Infectious Diseases Analytics (VIDA) Research Unit at the University of the Witwatersrand is one of the world’s leading centres for vaccine and infectious disease research. VIDA conducts internationally recognised clinical trials, epidemiological studies and translational research focused on reducing the burden of infectious diseases, particularly among mothers, infants and children in Africa. Its research has contributed to the development and implementation of several life-saving vaccines globally.

Unprecedented Success for HIV Vaccine in Preclinical Study

Vaccine approach yields high numbers of HIV-neutralising antibodies in non-human primates

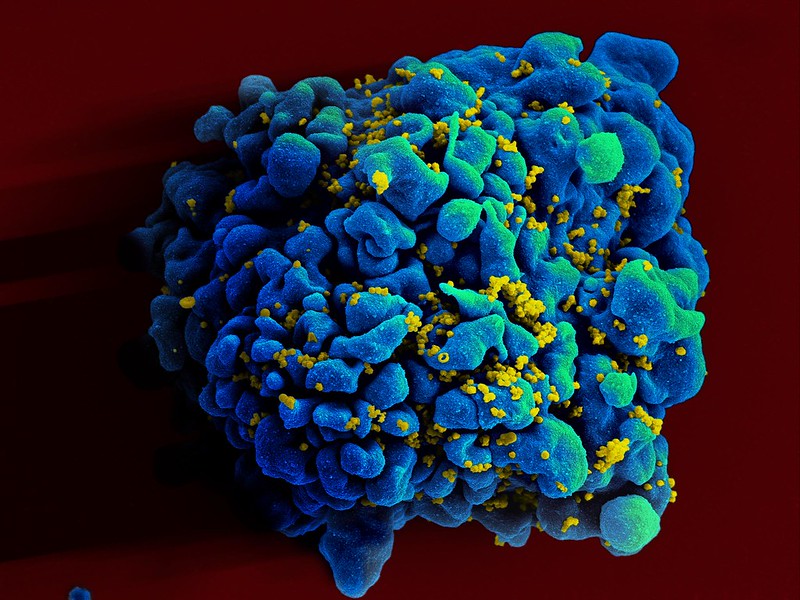
Colourised scanning electron micrograph of HIV (yellow) infecting a human T9 cell (blue). Credit: NIH

A new HIV vaccine developed by La Jolla Institute for Immunology (LJI), Scripps Research scientists, and IAVI has the potential to protect humans from developing HIV infection and AIDS. This HIV vaccine is the first to generate a high number of ‘broadly neutralising’, virus-fighting antibodies in primates.

“This feels like a huge success,” says LJI Professor and Chief Scientific Officer Shane Crotty, PhD, who co-led the research with Scripps Research Professor William Schief, PhD. “We constructed a successful vaccine from the ground up, which required a deep understanding of the immune system.”

This groundbreaking research, published in Nature, is the result of 14 years of collaboration between La Jolla Institute for Immunology and Scripps Research, as part of the Scripps Consortium for HIV/AIDS Vaccine Development (CHAVD). “This has been one of those Apollo moon mission-type projects, where there is an exceptional goal and the team has to accomplish a myriad of discoveries and inventions along the way,” says Crotty.

Outsmarting HIV

The new vaccine works by intervening in a process called B cell maturation. B cells make antibodies. Like many immune cells, B cells have an early ‘naïve’ stage before they are ready to make antibodies. B cells start to mature once they get the signal that a pathogen, such as a virus, is trying to attack. B cells see pieces of that pathogen’s molecular structure and start producing antibodies that can bind to that structure and halt infection.

It can take a little while for B cells to find the right “bullseye” on a pathogen. But B cells keep trying. As they mature, B cells tweak their antibody production, refining antibody structures to bind to a pathogen in just the right, vulnerable spots.

Scientists describe B cell development as a training process or bootcamp. In most cases, the body is left with a well-honed B cell army.

HIV is hard to beat because it doesn’t give B cells a chance to develop effective antibodies. The first problem is that HIV disguises itself from the immune system. The virus is wrapped in an ever-shifting cloak of sugar molecules, called glycans. This lets HIV sneak undetected past human cells, which are also covered in glycans.

The second big problem is that HIV mutates very quickly. “The worldwide diversity of HIV mutations is extraordinary. Even the diversity within one individual person living with HIV is dramatic,” says LJI Instructor Patrick Madden, Ph.D., who served as study co-first author with Jon Steichen, Ph.D., an institute investigator at Scripps Research.

The third problem is that HIV changes its shape when it infects human cells. Even if B cells get a glimpse of its viral structure – snap! – the structure changes.

Taken together, these problems rarely give B cells a chance to hone their antibody responses against HIV. Even if a B cell manages to make neutralising antibodies, the virus can mutate or change its shape, rendering those antibodies useless.

The LJI and Scripps Research teams spent years hunting for ‘broadly neutralising’ antibodies that can actually bind to HIV and recognise key viral structures, even if the rest of the virus mutates. These antibodies are very, very rare, but they can be found in blood samples from a small number of people living with HIV.

An effective HIV vaccine would need to prompt the immune system to make these same broadly neutralising antibodies. “How could we flip the whole immune response on its head so the rare responses become the common responses? That was a critical challenge we faced,” says Crotty.

Testing the new vaccine

It was time to go back to B cell bootcamp. The scientists studied what made the HIV-fighting B cells special. Then they reversed the process to see exactly how those B cells matured. By looking back at the maturation process, the researchers could track how the B cells changed when they saw specific pieces of the HIV structure.

The team discovered that B cells matured to make broadly neutralising antibodies after they got an early look at parts of HIV’s outer “envelope” protein. Because these viral sites sparked an immune response, scientists would call them “antigens.” 

An effective HIV vaccine would likely need to include models of these antigens. The antigens would work like mugshots of America’s most wanted. If B cells saw those antigens early and often, they would get really good at recognising and even neutralising HIV. “We were trying to mimic the progression of those neutralising antibodies,” says Madden.

In a feat of molecular engineering, the Schief Lab developed vaccine molecules that resembled the real HIV antigens. The scientists then worked with Emory National Primate Research Center, to test this potential HIV vaccine in a non-human primate species called rhesus macaques.

The researchers first administered a “priming” vaccine meant to activate each animal’s naïve B cells. The animals then received a series of “shepherding” booster shots to help their B cells develop along the right path. 

“This series of vaccinations will guide, or ‘walk’, a B cell from its naïve state to its broadly neutralising state,” says Madden.

This new type of vaccine approach is called “germline targeting” because it targets naïve B cells in their ‘germline’ or naïve form, before they begin their training process.

The scientists found that around 44 percent of the animals went on to produce broadly neutralising antibodies against HIV in their blood. These antibodies were impressively abundant. 

“We succeeded in taking ultra-rare antibody responses and turning them into common responses by the end of the vaccination process,” adds Crotty. In other research recently published, they reported a new strategy to accelerate related vaccine antibody responses [See Nature Immunology paper].

The team didn’t test whether these antibodies could prevent infection, but it’s significant that these antibodies could be found in the blood, where they could encounter and potentially block HIV.

Bringing the HIV vaccine to humans

The Crotty Lab plans to investigate how they might change the booster shot regimen to make the HIV vaccine even more effective. “It was incredible to get those results, but of course we’d like to see a response in 100 percent of the animals,” says Madden. 

Importantly, the antibodies found in the animal subjects resembled the exact kinds of broadly neutralising antibodies seen in those rare humans who made their own neutralising antibodies. It’s clear that our immune systems can make these powerful antibodies, given the right training.

“We believe this vaccine approach is even more likely to succeed in humans, because of the immunogenetics,” Crotty says.

The priming immunogen used in this study was evaluated in humans in the HVTN 144 trial and is currently being tested in the Phase 1 trial IAVI G004. IAVI, Scripps Research, the HIV Vaccine Trials Network, and partners are now advancing plans to further evaluate the full immunisation regimen in a future human clinical study.

Source: La Jolla Institute

New Shingles Vaccine to Be Launched in SA Private Sector, but Affordability May Limit Access

A more effective vaccine against shingles – an often painful and debilitating condition caused by the same virus that causes chickenpox – will soon be available in South Africa’s private sector. Photo by Mufid Majnun on Unsplash

By Marcus Low and Catherine Tomlinson

Ten years after its launch in the United States, a new, more effective shingles vaccine is finally set to hit the market in South Africa. While the vaccine, called Shingrix, should soon be available at private sector pharmacies, it seems unlikely that it will be provided in the country’s public healthcare system any time soon.

A more effective shingles vaccine is finally set to hit the market in South Africa. Shingles is a common and painful condition that mostly affects the elderly and people with weakened immune systems. It generally appears with a telltale red rash and cluster of red blisters on one side of one’s body, often in a band-like pattern.

“Shingles is pretty awful to get – it’s extremely painful, and some people can get strokes, vision loss, deafness and other horrible manifestations as complications,” infectious disease specialist Professor Jeremy Nel previously told Spotlight. “Shingles really is something to avoid, if at all possible.”

One way to prevent the viral infection, is to get vaccinated against it. Unfortunately, getting hold of shingles vaccines have been a challenge in South Africa.

A vaccine called Zostavax, from the pharmaceutical company MSD, was approved by South Africa’s medicines regulator in 2011, but taken off the market here in 2024. It was only around 50% effective at preventing shingles.

A more effective vaccine, called Shingrix, was introduced by GlaxoSmithKline (GSK) in the United States in 2016. Shingrix is estimated to be around 90% effective in preventing shingles.

But, as Spotlight reported last year, access to Shingrix in South Africa has been severely constrained. That was partly because the vaccine had not been registered by the South African Health Products Regulatory Authority (SAHPRA). Because of this, the only way to get the vaccine in the country was via a Section 21 application – a mechanism in the Medicines Act that allows for the limited importation of unregistered medicines.

That situation changed earlier this month when Shingrix was registered by SAHPRA, thus opening the door for the jab to be imported at scale and sold at pharmacies.

“GSK’s vaccine against shingles (herpes zoster) is expected to be available in South Africa by the end of June 2026,” a GSK spokesperson told Spotlight this week.

It will be launched at a price of R2 783 per dose, including VAT. The total price charged by pharmacies will be slightly higher due to extras like the cost of administration.

Shingrix vaccination requires two doses administered two to six months apart. Since Shingrix is a schedule 4 product, you will need a prescription from a doctor to get it. (You can see more technical details about the vaccine as released by SAHPRA here.)

What about public sector access? 

After a vaccine is registered by SAHPRA, the next step on the road to potential public sector access is typically for that vaccine to be considered by the National Advisory Group on Immunisation (NAGI). NAGI then makes a recommendation to the National Department of Health on whether or not the vaccine should be procured for the public sector.

“The decision for the public health sector to offer any vaccine, including Shingrix, is based on the recommendations by NAGI, which considers a number of factors, including availability of [the] registered health product, effectiveness and safety, operational feasibility, alignment with public health priorities, and whether sufficient funding is available,” Foster Mohale, spokesperson for the National Department of Health, told Spotlight.

He said the department has not yet received NAGI’s assessment outcomes and recommendations regarding Shingrix.

It seems likely that an asking price of over R2 000 per dose will be considered unaffordable for the public sector. That said, the price will have to be weighed up against the savings that will result from fewer people developing shingles and requiring treatment.

Spotlight asked GSK whether the company has engaged with the health department regarding the potential supply of Shingrix to the public sector and what price they might offer the government (the department of health often procures medicines at lower prices than what is asked in the private sector).

A GSK spokesperson responded: “As Shingrix is expected to become available in South Africa by the end of June 2026, we anticipate its initial introduction within the private sector. GSK is open to relevant discussions regarding the availability of this vaccine in the public sector.”

What about medical scheme coverage?

For now, it is unclear to what extent medical schemes in South Africa will cover the jab.

“For a vaccine to be considered for funding by the medical scheme, it must be registered with SAHPRA, have a valid NAPPI code, and be commercially available in South Africa,” Dr  Noluthando Nematswerani, Chief Clinical Officer at Discovery Health, told Spotlight.

Nematswerani pointed out that Shingrix is not yet commercially available in the country. Spotlight received her comments on 25 June 2026.

When Shingrix does become commercially available, that is to say when it’s available in pharmacies, it seems likely that at least some medical scheme members will be able to access it using their medical savings accounts.

“Discovery Health Medical Scheme funds vaccines that are registered with SAHPRA from the member’s available Medical Savings Account (MSA) on plans that include an MSA benefit,” said Nematswerani.

“Until Shingrix becomes commercially available locally, Discovery Health Medical Scheme members can only access Shingrix via a Section 21 authorisation process. Medicines accessed under Section 21 are treated as a general scheme exclusion and are therefore not funded from scheme benefits,” she said.

Who should get the vaccine?

As we previously reported, South Africa does not have guidelines regarding who should receive the shingles vaccine and when they should receive it. The US Centers for Disease Control and Prevention recommends that all adults over 50 receive the two-dose Shingrix vaccine. They also recommend that people whose immune systems can’t defend their body as effectively as it should, like those living with HIV, should get the vaccine starting from age 19.

In March 2025, the World Health Organization (WHO) recommended that countries where shingles is an important public health problem consider the two-dose shingles vaccine for older adults and people with chronic conditions.

“The vaccine is highly effective and licensed for adults aged 50 years and older, even if they’ve had shingles before,” according to the WHO. It advised countries to look at how much the vaccine costs compared to the benefits before deciding to use it.

Republished from Spotlight under a Creative Commons licence.

Read the original article.

Study Finds RSV Vaccination During Pregnancy Cuts Infant Hospitalisations by Nearly 70%

Source: Pixabay CC0

A study led by researchers at the University of Pittsburgh and UPMC published in JAMA Network Open, a peer-reviewed journal of the American Medical Association, found that vaccination against respiratory syncytial virus (RSV) during pregnancy reduced the risk of hospitalisation in young infants by nearly 70%.

This study provides early real-world evidence from US clinical care, showing that administering one dose of the maternal RSV vaccine (RSVpreF vaccine) reduces hospitalisation related to RSV in young infants. The results are consistent with findings from RSVpreF vaccine clinical trials. The RSVpreF vaccine was approved by the US Food and Drug Administration in 2023.

Among infants younger than 3 months, maternal vaccination was associated with approximately 68% effectiveness against hospitalisation for respiratory illness caused by RSV, and 69% effectiveness against more severe lung infections also caused by the virus.

“We designed this study to focus on what matters most to families: whether their baby might end up in the hospital,” said lead author of the study, Anne-Marie Rick, MD, PhD, assistant professor of paediatrics and clinical and translational science at Pitt School of Medicine and a physician at UPMC Children’s Hospital of Pittsburgh and UPMC Magee-Womens Hospital. “The findings show a significant impact for families and for the health system, and it highlights how effective this intervention can be during the most vulnerable months of life.”

RSV is the leading cause of hospitalisation among infants in the United States. According to the Centers for Disease Control and Prevention (CDC), about 2 to 3 out of every 100 babies younger than 3 months are hospitalised each year due to RSV, with severe cases sometimes requiring oxygen support or mechanical ventilation. Until the RSVpreF vaccine’s approval, there was no reliable way to protect healthy newborns from RSV starting at birth.

The study analysed health records from infants 90 days old or younger who were hospitalised for respiratory illness in Western Pennsylvania during the 2023–2024 and 2024–2025 RSV seasons. Researchers focused on infants who were tested for RSV and compared outcomes between those whose mothers received the vaccine during pregnancy and those whose mothers did not. Infants who received monoclonal antibody protection – a separate RSV prevention option administered after birth – were excluded.

The results are part of an ongoing four-year study to evaluate the effectiveness of maternal RSV vaccination across multiple seasons. Researchers will continue to follow patients during the 2025–2026 and 2026–2027 RSV seasons, expanding the analysis to include infants up to 180 days old and assessing how long protection lasts.

“We’re continuing to follow patients to understand how well this protection holds over time and across different groups,” said Rick. “These kinds of real-world data are critical for helping families, clinicians, and policymakers make informed decisions about how best to protect infants.”

Source: University of Pittsburgh

Cipla Secures Vaccine Tender Across Key Immunisation Categories

Photo by Mufid Majnun on Unsplash

Cipla has been awarded a public sector vaccine tender, reaffirming the company’s commitment to strengthening South Africa’s immunisation program through the equitable supply of high‑quality, affordable vaccines.

Cipla submitted bids across several critical paediatric and childhood immunisation categories, including Pneumococcal Conjugate Vaccine (PCV‑10), Rotavirus vaccine, Hepatitis B (Paediatric formulation). These vaccines play a vital role in preventing life‑threatening childhood illnesses and reducing the burden on healthcare systems.

CEO of Cipla Africa, Paul Miller, said: “This tender award marks an important milestone for Cipla as we continue to expand our vaccine footprint in support of national immunisation priorities. We can meaningfully contribute to comprehensive immunisation programmes and long‑term disease prevention efforts.

“Our participation across multiple vaccine categories demonstrates our commitment to addressing critical public health needs and strengthening health outcomes for children and communities.”

Cipla’s vaccine portfolio is underpinned by stringent quality standards and a focus on ensuring continuity of supply reliability. Cipla has a long history of partnering with the Department of Health to support equitable access to quality healthcare, including the supply of antiretrovirals and various vaccines.

Cipla South Africa focus will be ensuring reliability of supply, consistency, and responsible partnership with the public health sector, particularly in communities where access to healthcare remains uneven. CEO of Cipla Africa, Paul Miller, said: “This tender reaffirms our ongoing partnership with the state, as part of Cipla’s mission of ensuring access to quality, affordable healthcare.”

As part of our ethos of “Caring for Life”, we strongly believe in the importance of robust routine immunisation programmes that save lives, reduces inequality and delivery lasting benefits for society as a whole. In public health, progress often comes down to getting the basics right – ensuring vaccines are available, delivered on time, and reach every child who needs them.”

Participation in the Expanded Programme on Immunisation (EPI) aligns with Cipla’s broader mandate to support preventative healthcare and long‑term public health sustainability, said Miller.

Cipla South Africa continues to work closely with healthcare partners and has invested in initiatives to strengthen vaccines knowledge and reduce vaccine hesitancy. For more information about vaccines, visit https://medinformer.co.za/?s=vaccines

Innovative Vaccine Approach Induces Broadly Neutralising HIV Antibodies

Colourised transmission electron micrograph of an HIV-1 virus particle (yellow/gold) budding from the plasma membrane of an infected H9 T cell (purple/green).

Researchers at Karolinska Institutet, in collaboration with colleagues at The Scripps Research Institute and Emory University, have developed a new vaccine strategy that has generated antibodies capable of neutralising highly divergent HIV variants. The study, published in the journal Nature, provides new insights into how the immune system can be guided towards a particularly protected part of the virus.

HIV mutates rapidly, making it difficult to develop an effective vaccine. One major challenge has been to stimulate the immune system to produce so‑called broadly neutralising antibodies that recognise parts of the virus shared by many HIV variants.

In the study, the researchers focused on a small structure located at the very top of the virus’s surface protein, known as the apex, which is important for the protein’s three-dimensional structure. The apex is similar across many HIV variants but is shielded by dense layers of sugar molecules, making such binding difficult to achieve.

“We developed a strategy in which specially designed HIV proteins were attached to tiny fat particles, known as liposomes. This enabled multiple copies of the virus’s surface protein to be presented to the immune system simultaneously, thereby strengthening the immune response”, says Mónika Ádori, researcher at Department of Microbiology, Tumor and Cell Biology, Karolinska Institutet. 

The vaccine strategy was tested in an animal model in which macaques were immunised with liposomes linked to a selected HIV protein and then given booster doses in which the protein was gradually altered. The aim was to train the immune system to recognise features that are shared across different HIV variants.

Resembles antibodies that develop in humans

With this strategy, all vaccinated animals developed antibodies that neutralised a wide range of HIV variants. When the researchers analysed the antibodies in more detail, they found that they bind to the virus’s apex in a way similar to antibodies that sometimes develop in humans after long‑term HIV infection.

“The study shows that it is possible, through vaccination, to steer the immune system towards this specific part of the HIV surface protein,” says Gunilla Karlsson Hedestam, professor at the Department of Microbiology, Tumour and Cell Biology at Karolinska Institutet and a shared senior author of the study.

“This is an important step towards understanding how an HIV vaccine could be designed. Discussions are now underway about how the strategy could be taken forward into clinical studies,” she continues.

The study was funded by the US National Institutes of Health (NIH). The researchers report no conflicts of interest.

Publication

Vaccine generates broadly cross-neautralizing antibodies to the HIV Env apex“, Javier Guenaga, Monika Adori, Shridhar Bale, Swastik Phulera, Ioannis Zygouras, Fabian-Alexander Schleich, Xaquin Castro Dopico, Sashank Agrawal, Miyo Ota, Richard Wilson, Jocelyn Cluff, Tamar Dzvelaia, Marco Mandolesi, Wen-Hsin Lee, Agnes A. Walsh, Mariane B. Melo, Laurent Verkoczy, Darrell J. Irvine, Martin Corcoran, Ian A. Wilson, Diane Carnathan, Guido Silvestri, Andrew B. Ward, Gabriel Ozorowski, Gunilla B. Karlsson Hedestam, Richard T. Wyatt, Nature, online 29 April, doi: 10.1038/s41586-026-10429-3 

Source: Karolinska Institutet

South Africa’s Vaccination Drive Needs Renewed Urgency

This African Vaccination Week Sanofi South Africa reaffirms its commitment to vaccine awareness, access and public health partnerships to close the immunisation gap

Photo by Mufid Majnun on Unsplash

Johannesburg, 20 April 2026 – Marked each year from 24 to 30 April, African Vaccination Week focuses on the need for equitable access to lifesaving vaccines across the continent.

It’s also a timely reminder that while vaccination remains one of the most effective tools in public health, gaps in coverage are a real concern, in South Africa and globally. UNICEF says immunisation prevents an estimated 4.4 million deaths every year,1 yet WHO reported that 14.3 million children worldwide missed out on all routine vaccines in 2024.2 Global coverage for the third dose of DTP-containing vaccine stood at 85% in 2024, while first-dose measles coverage was 84%.2

“Vaccination remains one of the smartest and most effective investments in public health,” says Jean-Baptiste Bregeon, Country Lead and Head of Vaccines, Sanofi South Africa. “Improving coverage is not only about having vaccines available. It’s about building trust, strengthening health systems, supporting healthcare workers and making sure people have the information they need to act. African Vaccination Week is a reminder that protecting lives takes sustained effort and strong partnerships, and Sanofi remains committed to playing its part in South Africa.

In South Africa, the need is clear. The National Department of Health reported in 2024 that 80% of children in the country had received all their vaccinations by the age of one.3 That is progress, but it also means one in five children had missed one or more doses and was not fully protected. UNICEF South Africa has separately highlighted the urgency of reaching children who have missed routine immunisation entirely. There were 58,000 more zero dose children in 2024 and 278,000 without vaccination, leaving them vulnerable to vaccine preventable diseases.Measles vaccination coverage, for example, declined from 80% in 2023 to 76% in 2024.4

Recurring outbreaks of measles, cholera, polio and diphtheria have added pressure to the health system, while disruption to routine immunisation has left more children vulnerable to vaccine-preventable diseases and increased the risk of further outbreaks.5

This year’s campaign aims to intensify vaccination and surveillance activities in districts with high numbers of under-vaccinated and unvaccinated children. Vaccines included in South Africa’s national immunisation schedule are available free of charge at primary healthcare facilities.

Sanofi says its focus in South Africa over the next two to three years will be to continue supporting the Department of Health to improve vaccine coverage across the country, with a focus on access, availability, education and awareness.

“Improving vaccine uptake requires a practical, local approach that recognises the realities of South Africa’s healthcare system, including uneven coverage, pressure on frontline services, and the challenge of reaching communities across both urban and rural settings,” says Bregeon.

That’s why partnership matters, he adds. “Improving immunisation outcomes takes coordinated action across government, healthcare providers, communities and industry. Strong supply is important, but so is public confidence, clear communication and consistent follow-through at clinic level.”

This African Vaccination Week, Sanofi calls on all South Africans to ensure their vaccinations are up to date and encourages healthcare providers to continue championing immunisation as a cornerstone of preventive health.”

References

1. UNICEF. Vaccination and immunization statistics. Available at: https://data.unicef.org/topic/child-health/immunization/
2. World Health Organization. Immunization coverage. Available at: https://www.who.int/news-room/fact-sheets/detail/immunization-coverage
3. Republic of South Africa, Department of Health. Overview of Expanded Programme on Immunisation in South Africa (EPI-SA). Available at: https://knowledgehub.health.gov.za/system/files/2024-05/VACCINE%20HESITANCY%20WEBINAR_OVERVIEW%20OF%20EPI_MAY_2024_FINAL.pdf
Moyo S, Ashok A, Myers L, Nyankieya R, Sharma S, Prasad R. The impact of COVID-19 on routine child immunisation in South Africa. BMC Public Health. 2024;24:3077. Available at: https://link.springer.com/article/10.1186/s12889-024-20591-w
5. Moyo S, Ashok A, Myers L, Nyankieya R, Sharma S, Prasad R. The impact of COVID-19 on routine child immunisation in South Africa. BMC Public Health. 2024;24:3077. Available at: https://link.springer.com/article/10.1186/s12889-024-20591-w