Category: Expert Opinion

Opinion Piece: Completing the Circle of Care

Putting Caregiver Wellbeing at the Heart of In-home Support

Photo by Kampus Production on Pexels

By Roxanne Cordes – National Homecare Administrator at Allmed Healthcare Professionals

When a loved one needs care, the focus is naturally centred on them. Are they safe? Are their needs being met? Do they have the right support? These questions are important, but there is another person at the heart of the care arrangement whose needs can sometimes be overlooked: the caregiver. Whether supporting an older person at home, caring for someone recovering from illness or working with people living with conditions such as dementia, caregivers carry significant physical and emotional demands of their own. The level of support they receive can have a direct impact on the quality of care provided.

The reality of caregiving

Caregivers play an indispensable role in healthcare, often becoming a constant presence in a client’s daily life. Their responsibilities can range from personal care, dressing and mobility to preparing meals and providing companionship. They may also support people living with dementia or recovering from major surgery, where patience and reassurance are as important as practical assistance. The physical demands of caregiving can be considerable. A typical day may involve lifting and transferring, assisting with mobility, managing equipment and responding to changes in a client’s condition. Needs and moods can also shift throughout the day, requiring constant attention and adaptability. For those providing live-in or in-home care, there may be little opportunity to step away when circumstances become challenging.

The emotional demands can be just as significant. Dementia can bring confusion, fear, frustration and distress, sometimes resulting in angry or hurtful responses. Caregivers need to recognise these reactions as part of the condition rather than taking them personally. Close relationships often develop over time, making illness, decline or loss particularly difficult to process.

Homecare can bring another challenge: isolation. Unlike caregivers in residential facilities, those working in private homes may spend much of the day without colleagues nearby to share concerns or seek advice. Regular contact and accessible support give caregivers a place to raise concerns, discuss changes and seek guidance before challenges become more difficult to manage.

Supporting the person behind the care

Caregiver wellbeing is closely linked to the realities of delivering care, which can be physically demanding and emotionally draining, particularly over time. While this does not mean a difficult day will compromise care, it does highlight the importance of having the right support in place.

That support needs to be practical. Regular check-ins give caregivers a chance to talk through concerns, ask questions and flag changes in a client’s needs before they become more difficult to manage. Clear access to appropriate healthcare professionals and support structures is just as important, particularly when something falls outside the caregiver’s responsibilities. This could include GPs, nurses or other healthcare professionals involved in the client’s care. In a private home, where there may be no colleagues nearby, knowing exactly who to contact can provide valuable reassurance.

Training provides another layer of support. Clear responsibilities, practical skills and ongoing development help caregivers understand what is expected of them and where they need to involve someone else. This is particularly important in homecare, where much of the work happens independently.

Caregiver wellbeing is part of quality care

Care does not happen in isolation. It is a circle involving the person receiving care, the caregiver, family members and the wider healthcare team. Each part of that circle affects the others, which means supporting the caregiver is also part of supporting the person in their care.

A caregiver with the right training, clear responsibilities and access to guidance is better positioned to respond when needs change or a situation becomes difficult. The same applies to emotional support. Having someone to turn to can make it easier to manage the pressures of the role rather than trying to carry every challenge alone.

For healthcare organisations and families arranging in-home support, this means looking deeper than whether immediate care needs are being met. Are caregivers able to raise concerns and ask questions? Do they know who to contact when professional guidance is needed? Are they receiving the training and support required for the role? These considerations are not separate from quality care. They are part of creating a care environment where everyone involved is supported.

Making a year-round commitment

Carers Week offers a vital moment to celebrate those who dedicate their lives to helping others. But caregiver wellbeing cannot be a once-a-year conversation. A truly sustainable care model starts with three simple principles:

  1. When caregivers are supported, care is stronger: The right training, guidance and support help caregivers respond to changing needs with confidence and compassion.
  2. Good support happens every day: Regular communication, professional guidance and ongoing learning give caregivers the practical support they need throughout their careers.
  3. The human side of caregiving matters: Care is built on patience, empathy and relationships as much as practical skills. Recognising the emotional demands of the role is part of recognising the work itself.

Good care ultimately depends on the people providing it. If we want to create safe, respectful experiences for our loved ones, we must also support the professionals who help hold the circle of care together.


Inside The Box with Dr Andy Gray | How Should Medicines Shortages be Managed in South Africa?

#InsideTheBox is a column by Dr Andy Gray, a pharmaceutical sciences expert at the University of KwaZulu-Natal and Co-Director of the WHO Collaborating Centre on Pharmaceutical Policy and Evidence Based Practice. (Photo: Supplied)

By Dr Andy Gray for Spotlight

Imagine you have been taking a medicine for years. Then one day you are told at the pharmacy that supplies have run out. In his latest Spotlight column, Dr Andy Gray zooms in on how governments can monitor and plan for such shortages.

The draft text of the United Nations High-Level Declaration on Pandemic Prevention, Preparedness and Response, which failed to get consensus support at the General Assembly on 25 September 2026, contained this paragraph:

“Deeply concerned by the inequities at national and international levels that hindered timely and equitable access to health products, including vaccines, diagnostics and therapeutics to address coronavirus disease (COVID-19), and recognizing the need to address serious shortcomings at the national, regional and global levels in prevention, preparedness, response and health system recovery for public health emergencies of international concern, including pandemic emergencies;”

However, it is not only during pandemics or public health emergencies that shortages of medicines and vaccines are experienced and have to be actively managed. In fact, in recent decades the issue has become so serious that several high-income countries have taken legal and regulatory steps to address it.

Global access to medicine shortage data

South African health and medicines law does not clearly define what is meant by a “medicines shortage”. By contrast, the US Federal Food, Drug, and Cosmetic Act simply defines it as a period of time when the demand or projected demand for a medicine exceeds its supply.

Since 2012, marketing authorisation holders in the US have been under a legal obligation to report shortages to that country’s medicines regulator. These obligations were strengthened during the COVID-19 pandemic and now require manufacturers to report any interruption in their manufacturing process that is likely to lead to a meaningful disruption in supply, as well as to disclose the reasons for the interruption. Manufacturers are also required to give advanced warning of permanent discontinuation of production, and the reasons for that decision. The US Food and Drug Administration (FDA) maintains a publicly accessible database of current resolved shortages and discontinuations. In addition, the American Society of Health-System Pharmacists maintains a separate database.

Medicines shortages have also been recognised as a critical public health issue by the European Medicines Agency (EMA) and its national agencies. Since 2022, manufacturers have been required to report shortages to the European Shortages Monitoring Platform. The EMA maintains an accessible database of current and resolved shortages, as do each of the national agencies.

A similar resource is provided by the Australian Therapeutic Goods Administration (TGA).

The gap in South Africa

The South African Health Products Regulatory Authority (SAHPRA) has no equivalent reporting requirement, nor does it make any such data publicly accessible.

SAHPRA’s online register includes not only those products with current registration, but also includes those where the status is noted as “Cancelled”. Unfortunately, while the date of registration is recorded, there is no date of cancellation stated, nor any reason provided for discontinuation of the product. Health professionals and patients only find out about product discontinuations after the fact and the regulator has no advanced warning of the decision, nor is it provided with the reasons for discontinuation. There is also no accounting for how many medicines have been withdrawn from the South African market.

Section 19(2) of the Medicines and Related Substances Act allows SAHPRA to request any information from manufacturers, sellers or prescribers of medicines, but the intent is to enable response to a specific request, within a stipulated time period. This provision does not create an ongoing obligation or a permanent reporting process, so cannot be used to impose the type of reporting demanded in the US, Europe or Australia.

A valuable resource – the health department’s “hotlist”

The National Health Department’s website includes a recent innovation, in the form of a “hotlist”, defined as “a list of all essential medicines on contract with stock availability of below 90% and with total orders exceeding supplier stock on hand and total provincial stock on hand less than two months of forecasted demand”. Importantly, the list also documents “the root cause for the supply challenge and proposed remedial actions for each listed item”. The list is updated on a monthly basis and the August 2026 version lists 29 “new” items, 98 described as “longer term” and 120 resolved items. Of particular note, a separate tab lists products which were not being supplied to particular provinces because of non-payment of accounts. The reasons for shortages vary considerably, from delays in quality assurance procedures to delays in accessing critical components, whether active ingredients, excipients or packaging materials. Global supply constraints were also identified, as were local regulatory actions (or delays in obtaining regulatory approval for changes in production).

The health department’s website also provides a link to the current Master Health Product List, which includes all medicines for which a tender has been awarded. One of the columns on the spreadsheet documents the “VEN” status of the medicine. This refers to a judgment on whether a medicine is considered “vital”, “essential” or “non-essential”, in terms of the immediate health consequences of a shortage. Lack of access to a vital medicine, for which alternatives might not exist, would be expected to have immediate and serious health consequences for patients. One way to mitigate that risk would be to contract multiple suppliers of a vital medicine. Such split tenders are used for some essential medicines, notably the first-line antiretrovirals used to treat HIV, but not for all medicines listed as vital.

The private sector – adrift

Not only is there no equivalent of the “hotlist” for the private sector in South Africa, but one of the key responses used by the public sector to manage shortages is also not available. The National Department of Health Contract Management Unit’s website lists the products for which SAHPRA has granted the public sector permission, in terms of section 21 of the Medicines and Related Substances Act, to import unregistered medicines in bulk. In the private sector, similar bulk approvals are not issued, and individual applications are required for every patient seeking access to an alternative product, should there not be a registered alternative on the local market.

Health professionals in the private sector are therefore at a distinct disadvantage, lacking access to timely information about medicine shortages and also denied access to a key mechanism for responding to shortages.

In Australia, the equivalent legal provision (section 19A) enables access to unregistered, imported medicines to manage a medicine shortage considered to be of public health importance. Access is enabled for the entire health system, not only for facilities operated by the state.

The concept of “critical medicines”

European authorities have extended the concept of VEN status to create a list of “critical medicines”. In May 2026, political agreement was reached on the Critical Medicines Act, which will enable a number of important interventions to promote resilience in the pharmaceutical market. One of these interventions will require manufacturers to hold contingency stocks of critical medicines and mandate sharing of data on such stocks when reallocation is required, triggering a call for solidarity between Member States. Procurement of medicines will also be required to promote regional manufacturing in the EU.

Many reasons, key gaps

There can be many reasons for medicines shortages, some related to the national market, others impacted upon by global shifts. Regulatory action by SAHPRA in response to non-compliance with good manufacturing standards has resulted in a number of disruptions in supply, notably in the small volume injectable market.

Although the second single exit price adjustment in 2026 will be welcomed by the pharmaceutical industry, other actions noted in the joint government-industry-regulator statement in August 2026 still require attention. Some immediate actions include a joint review of the pricing regulations, to improve transparency and predictability and also explore alternative reimbursement models for specific medicines. In the longer term, the industry is seeking appropriate incentives, including public sector procurement that supports local production and attracts new investment.

According to the FDA definition, a medicine such as lenacapavir is already showing signs of a shortage, with demand exceeding supply. Improved transparency, applied across both public and private sectors, is crucial if medicine shortages are to be prevented, identified and acted upon with the urgency they deserve.

 – Gray is a Senior Lecturer at the University of KwaZulu-Natal and Co-Director of the WHO Collaborating Centre on Pharmaceutical Policy and Evidence Based Practice.

Disclosure: Gray serves on three technical advisory committees at the South African Health Products Regulatory Authority.

*This column was published by Spotlight – health journalism in the public interest. Sign up to the Spotlight newsletter.

Beyond Dispensing: Why South Africa Needs to Make Better Use of Pharmacists to Improve Healthcare Access

Pharmacists are the most accessible healthcare professionals for many South Africans. Image created with AI.

Healthcare access in South Africa is increasingly shifting towards prevention, early intervention and more accessible primary healthcare. Yet for many communities, accessing healthcare can still mean long waiting times, travel and delays in receiving care.

As pressure on the healthcare system continues, there is an opportunity to make better use of healthcare professionals who are already accessible within communities.

For many people, the pharmacist’s role has traditionally been associated primarily with dispensing medication. But the profession has evolved significantly. Pharmacists are increasingly contributing to medicine optimisation and adherence, chronic disease support, health screening and other primary healthcare services within their scope of practice.

According to Tanya Ponter, Pharmacy Director at Dis-Chem, pharmacists are equipped with skills that extend well beyond the dispensing of medicines.

“Pharmacists are trained to interrogate symptoms, review evidence and metrics that identify risk and make life saving decisions under pressure. Their expertise places them in a unique position to support patients beyond the traditional dispensing function and contribute to earlier intervention and better health outcomes.”

This evolving role is particularly important as South Africa looks for ways to improve access to primary healthcare. Pharmacists are often accessible within communities and can provide guidance, identify potential health risks and, where appropriate, refer patients to other healthcare professionals. What’s more, they are the most accessible clinical touchpoint for consumers and are always available to provide expert advice at no cost to patients.

“Expanded pharmacist-led services have the potential to reduce existing pressure on the healthcare system, with these professionals often being a first point of contact for patients in communities. Their presence can help address appropriate healthcare needs earlier and potentially reduce unnecessary demand on higher levels of care,” says Ponter.

With rising rates of chronic conditions like diabetes, hypertension, and HIV, pharmacists play an ongoing role in long-term wellness. To support complex patients who often take multiple pills, they offer guidance and medication reviews to simplify regimens and eliminate unnecessary or duplicate treatments.

As South Africa marks World Pharmacists Day, Ponter states that the profession should increasingly be viewed as an integral part of the country’s primary healthcare ecosystem.

“Pharmacists should not simply be seen as the final step between patients and prescriptions. They can help bridge the gap between communities and healthcare by supporting prevention, identifying risks earlier and helping patients navigate the healthcare system, particularly when barriers make accessing other healthcare services more difficult,” Ponter concludes.

Opinion Piece: South Africans are Bringing Healthcare Home – But are they Doing it Safely?

By Dianne Boyd – Chief Operating Officer Frail Care at Allmed

Photo by Kampus Production on Pexels

There is a quiet shift happening in homes across South Africa. As the population ages and hospitals grapple with packed wards and immense strain, families are looking closer to home for answers. More seniors are choosing to stay right where they are, surrounded by their own memories, familiar furniture, and beloved pets, rather than moving into frail care or assisted living facilities. At the same time, because hospitals are discharging patients much faster following surgery, strokes, or cancer treatments, expert recovery support right in the living room has never been more important.

For most people, the thought of healing or growing older in a familiar space brings an unmatched sense of comfort and dignity. But for someone navigating the fog of dementia or the daily weight of a chronic illness, holding onto familiar routines is life changing. It reduces anxiety, keeps confusion at bay, and gives patients a deep-seated feeling of control that a clinical institution simply cannot match.

The hidden trap of doing it alone

As the need for home care grows, it becomes easy to see why some families turn to online platforms or informal word-of-mouth recommendations to find help. On the surface, hiring a caregiver directly feels simpler, quicker, and perhaps cheaper. But it often masks a maze of hidden responsibilities and risks that families are rarely prepared for.

Society tends to think of home care as simple companionship or a helping hand with daily tasks. In reality, caring for a vulnerable loved one safely requires a tremendous amount of unseen work. When individuals hire someone independently, they suddenly step into the role of an employer. Managing contracts, payroll, UIF contributions, and leave becomes an immediate reality. Worse still, what happens when a caregiver wakes up sick or resigns unexpectedly? Without a reliable agency behind the household, finding cover at 4am in the morning falls entirely on the family.

Even more concerning are the clinical visibility gaps in such an arrangement. Without professional oversight, missing the subtle early warning signs of trouble is remarkably easy; a tiny pressure sore starting to form, the early stages of dehydration, a missed medication, or a silent infection.

Why professional care changes everything

Treating home-based care as a true healthcare partnership rather than a domestic arrangement completely changes the experience for a family. Reputable, registered providers shoulder the heavy burden of care, so relatives do not have to carry it alone.

Instead of crossing fingers and hoping for the best, a professional approach brings real clinical governance into the home. Experienced clinical facilitators step in to assess patient needs, create tailored daily care plans, and check in regularly. They ensure that caregivers are thoughtfully matched to the individual, such as pairing someone with specialised dementia training with a patient who needs calm, skilled behavioural guidance.

Partnering with an established provider also puts a safety net around the entire household. Professional agencies cover personnel with medical liability insurance while handling all statutory requirements like workmen’s compensation, keeping families legally and financially protected from unforeseen accidents.

Finding peace of mind and financial relief

One of the greatest barriers families face with home care can be the financial weight. This is where working with a registered provider can make a profound difference. Because established agencies hold an official practice number, families can often submit claims directly to their medical aid schemes, subject to scheme rules and a specialist’s clinical motivation. This can be a powerful way to ease the financial strain of long-term support.

Bringing care into the home should bring peace of mind rather than sleepless nights. Leaning on a professional team for the vetting, the legalities, and the clinical oversight allows relatives to step back from being managers and return to being sons, daughters, or partners. That leaves space to focus on what truly matters: sharing meaningful, comfortable moments with a loved one, right where they belong.

GLP-1 RAs Will Not Solve Diabetes

“South Africa’s diabetes epidemic will not be solved by the next pharmaceutical breakthrough. It will be solved by fundamentally reshaping how healthcare is organised and paid for”

– Lungile Kasapato, CEO of PPO Serve.

Diabetes is now South Africa’s leading killer, accounting for more deaths than HIV and TB combined. Global headlines celebrate GLP-1 receptor agonists (RAs) as a breakthrough for metabolic disease and obesity. But this narrative ignores a fundamental reality: for most South Africans, these drugs are inaccessible. Priced between R3 000 and R6 000 per month, they remain unaffordable. Even as cheaper generics become widely available, they won’t solve the problem alone. Without the clinical infrastructure to support treatment, and the social support to access healthy food, access means little.

“We’re pushing an incomplete solution,” says Lungile Kasapato, CEO of PPO Serve, a healthcare management company implementing value-based care in South Africa for over a decade. “GLP-1 RAs offer real benefits – sustained weight loss, reduced inflammation, lower cardiac risk, protection against comorbidities. For someone facing diabetes, these outcomes matter. But we’re acting as if a drug alone can solve a system failure. It can’t. A medication prescribed into a broken healthcare system is just a product. It’s not a national health strategy.”

The scale of the crisis is staggering. Forty percent of low-income South Africans’ diet consists of ultra-processed foods. Across the broader population, nearly 30% have undiagnosed hypertension. Most discover their condition only after complications like strokes or heart attacks emerge. By the time they reach treatment, the system can only manage disease with medications, never addressing what caused it in the first place. When a GLP-1 RA is prescribed in this fractured environment, initial sustained progress stalls because the infrastructure to maintain results was never built.

“This fragmentation isn’t accidental,” says Kasapato. “It’s structural. Fee-for-service rewards volume, not health. A provider, working alone, gets paid for each visit, test, or procedure – regardless of whether the patient’s health improves. With no teamwork or incentive to coordinate, follow-ups become inconsistent and inadequate. Every encounter is transactional, continuity is impossible, and no one is accountable for the patient actually getting better. As long as we pay for activity instead of results, we won’t fix the system or build the infrastructure these medications need.”

PPO Serve’s The Value Care Team, implemented in partnership with the Government Employees Medical Scheme (GEMS), demonstrates what a different payment structure creates. GPs, nurses, dietitians, and care coordinators work together, sharing accountability for patient outcomes rather than billable procedures. Coordination becomes the norm, and prevention becomes profitable, meaning early intervention can stop complications before they escalate. Medication works better because the system supports it, including addressing the social issues that drive obesity in the first place. This is what reshaping incentives creates.

“The real choice isn’t just about drug access,” says Kasapato. “It’s about payment models, and the system it creates. Cheaper GLP-1 RAs could be available tomorrow – generics are already arriving. But availability achieves little without the organisation to deploy them. The conversation must progress from funding medications to funding the teams and systems that make them work. South Africa’s diabetes epidemic will not be solved by the next pharmaceutical breakthrough. It will be solved by fundamentally reshaping how healthcare is organised and paid for.”

Opinion Piece: Water is Running out – Why Corporate South Africa Must Rethink Risk, Resilience, and Responsibility

Robert Erasmus

By Robert Erasmus, Managing Director at Sanitech

For generations, corporate South Africa treated water like as an abundant utility. Facility managers turned on the tap, paid the monthly municipal bill, and gave the resource little further consideration. That luxury is gone. Today, deteriorating municipal infrastructure, frequent water cuts, and declining water quality have transformed water security from an operational concern into a strategic business risk. It is no longer an issue confined to factory floors or facilities departments, but it demands attention at board level. For modern companies, water stewardship is no longer a corporate social responsibility initiative. It is a core leadership duty that directly affects business survival, legal compliance, and long-term success.

Caught between strategic expectations and operational reality

Business leaders are under pressure from both ends of the value chain. From the top down, investors, banks, and strict environmental standards demand complete openness about how much water companies use and how they protect the environment. From the ground up, operational teams face mounting challenges as unreliable municipal supply, infrastructure failures, and water quality concerns disrupt daily activities.

When poor municipal water supply stops production lines or dirty wastewater breaks environmental laws, the financial hit is immediate. Businesses are constantly forced to choose between paying massive fines or spending large sums of money on emergency repairs. Because of this constant pressure, water has permanently shifted from a minor monthly expense into a top business risk.

Knowing your true water footprint

One of the biggest challenges for large organisations is the lack of accurate, consolidated water data. Many organisations operate without a comprehensive understanding, unified view of how much water they consume, where losses occur, how water quality changes across facilities, or what is ultimately discharged into the environment. Without this basic information, setting realistic reduction goals or meeting modern Environmental, Social and Governance (ESG) reporting requirements becomes exceptionally difficult.

To take back control, boards need to know exactly which of their facilities sit in water-stressed areas or depend on fragile local water supplies. Executive leaders must connect with site managers to truly understand how water shortages impact everything from daily manufacturing output to employee health and community relations.

Testing business resilience for a drier future

Protecting a business for the future requires serious planning at the executive level. Boards can no longer assume that municipal water services will remain reliable. Leadership teams must prepare for a range of scenarios, including long municipal outages, water quality that drops below safe working levels, and sharp increases in water tariffs and fines. As South Africa works to fix its national water infrastructure, factoring these rising costs and risks into financial planning is a basic duty for any director.

Forward-thinking companies are discovering that active water stewardship creates real business advantages beyond just avoiding risks. Moving toward a circular water model allows businesses to grow without relying entirely on fresh water. Investing in on-site water recycling, greywater systems, and advanced treatment technology is what enables companies to insulate themselves from municipal supply problems while turning environmental responsibility into operational strength.

Bridging the gap between policy and practice

Protecting a company’s right to operate means connecting high-level company goals with everyday actions on the ground. Effective water stewardship takes a holistic view of the entire water cycle, examining how water enters a facility, how efficiently it is used, how losses are managed, and how responsibly wastewater is treated and discharged.

Partnerships with specialised environmental service providers can help organisations implement advanced filtration systems, optimise treatment processes, improve wastewater management, and deploy innovative water-efficiency solutions. When the private sector takes responsibility for its water use, the benefits go far beyond individual company profits and reputations.

By taking stress off municipal systems, businesses actively help secure water for the surrounding community. Water stewardship is no longer an act of corporate philanthropy.  It is a fundamental requirement for organisations seeking to remain competitive, resilient, and sustainable in an increasingly resource-constrained world.

Opinion Piece: Medical Aid Cover is Changing – Are South Africans Prepared for the Gaps?

Photo by Alex Green on Unsplash

By James White, Director: Sales and Marketing at Turnberry Management Risk Solutions

Medical aid remains essential for accessing private healthcare in South Africa, but it is no longer safe to assume it will cover the full cost of treatment. In 2026, industry regulators recommended that scheme contribution increases be capped at around 6-7% (CPI plus 3%), roughly in line with inflation, yet several major schemes have raised contributions well beyond that, with healthcare cost inflation broadly running at 9 – 11% against consumer inflation of about 3%. Medical aid options have also introduced growing numbers of co-payments, sub-limits, penalties and benefit restrictions. As a result, the role of gap cover has changed. What was once seen as an optional extra has become a critical safeguard against medical expense shortfalls, and it is now imperative that advisers and clients understand where medical aid cover may fall short and how those risks can be managed.

Healthcare cover is not what it used to be

The biggest change over the past decade is that medical aid has become far more complex. In the past, it was fairly simple to understand, and many routine healthcare costs were covered. Today, most day-to-day expenses are paid from medical savings or out of a client’s own pocket, and members must weigh up co-payments, sub-limits, designated service providers, network restrictions and benefit limits, all of which affect what a scheme will ultimately pay. At the same time, healthcare costs have continued to climb, and specialists often charge well above scheme rates. This means that having medical aid and being fully financially protected are no longer the same thing.

Every registered medical scheme is still required to cover Prescribed Minimum Benefits (PMBs) in full, a defined list of around 270 conditions, the Chronic Disease List, and emergency care, regardless of a member’s savings or threshold status. But PMBs are a floor, not a ceiling: outside of them, members are far more exposed than many realise.

Despite this, many people still believe they are adequately protected, without fully understanding the limitations of their medical aid. The reality often only becomes apparent when they need treatment. A claim subject to a co-payment, a specialist charging above the scheme rate, or a treatment subject to benefit limits can result in significant and unanticipated out-of-pocket costs.

Advice needs to evolve with the healthcare system

As the healthcare landscape has changed, the role of the adviser has changed with it. Recommending a medical aid option is no longer enough. Advisers also need to help clients understand how that option works, what it covers, where medical expense shortfalls may still arise, and how concepts such as co-payments, penalties, and designated service providers could affect them.

Advice also needs to be more personalised than in the past. Medical scheme options differ significantly, and the right level of cover depends on a client’s healthcare needs, affordability and family circumstances. A younger family with children, for example, may require very different cover from someone approaching retirement, even if both belong to the same medical scheme.

It’s also worth noting that gap cover itself isn’t unlimited. Under the Demarcation Regulations, gap cover claims are capped at an aggregate annual limit per beneficiary, a figure adjusted each year for inflation. Most claims fall comfortably within it, but very large shortfalls can still exceed the cap, which is one more reason the underlying medical aid plan needs to be right in the first place, not just the gap cover sitting on top of it.

This advice is no longer a once-off conversation either. Medical scheme benefits change, family circumstances shift over time, and healthcare needs evolve. Regular reviews help ensure that both medical aid and gap cover continue to provide the level of protection clients need.

A critical part of healthcare planning

The healthcare system has changed significantly over the past decade, and the way advisers approach healthcare cover needs to change with it. Medical aid remains essential, but it no longer provides the level of protection many people still expect. As a result, gap cover has evolved from an optional extra to a core part of protecting against medical expense shortfalls. Helping clients understand how their medical aid works, where shortfalls may arise, and how gap cover can address them has become an important part of modern healthcare advice.

As medical aid benefits, healthcare costs, and client needs continue to change, regular reviews are essential. By ensuring cover continues to reflect a client’s circumstances, and by explaining potential shortfalls before they arise, advisers can help clients make informed decisions and avoid unexpected medical expenses. Clients should speak to their broker or financial adviser regularly, to make sure their medical aid and gap cover continue to meet their healthcare needs.

Turnberry Management Risk Solutions (Pty) Ltd is an authorised Financial Services Provider (FSP no. 36571). Underwritten by Lombard Insurance Company, an Authorised Financial Services Provider (FSP 1596) and Insurer conducting non-life insurance business.

Reforming Prescribed Minimum Benefits Is the First Step to Affordable Medical Cover

Dr Katlego Mothudi is the Managing Director of the Board of Healthcare Funders, an industry representative body for medical aid schemes, administrators and managed care providers.

By Katlego Mothudi

With plans in motion to roll out universal health coverage in South Africa, Dr Katlego Mothudi, of the Board of Healthcare Funders, argues that revising the compulsory prescribed minimum benefits that medical schemes must provide can be a tool to deliver meaningful improvements today while laying the foundations for a more sustainable healthcare system.

South Africa’s journey towards universal health coverage will not be defined by a single policy or piece of legislation, but by the practical reforms that make quality healthcare more accessible and affordable for more people. Achieving this goal requires, among other things, tackling structural barriers that continue to drive up the cost of medical scheme cover and place private healthcare beyond the reach of millions of people in South Africa. One of the most important, yet often overlooked, barriers is the outdated framework governing prescribed minimum benefits (PMBs).

PMBs are the set of conditions and services that every medical scheme is legally required to cover, regardless of the plan a member chooses. Their existence is critical, created with the intention of ensuring scheme members do not lose access to catastrophic care in the event of serious illness. PMBs ensure that members are not reliant on an over-burdened public sector during medical emergencies. And although this principle remains important, the framework has not kept pace with South Africa’s changing disease burden, evolving models of care, or the cost of delivering healthcare.

20 years of PMB limbo

Regulations made under the Medical Schemes Act require PMBs to be reviewed every two years. This must be carried out by the Department of Health together with the Council of Medical Schemes, provincial health departments and other stakeholders. In practice, this has happened only once, more than 20 years ago.

The current review process has been underway for close to a decade without conclusion. As a result, the outdated PMB framework has become one of the most significant contributors to medical scheme costs and thus an inefficient health policy. Actuaries advise that roughly 60% of a scheme’s budget goes towards funding PMBs before any other benefit is considered. This used to be approximately 40% when the PMB was amended in 2003.

The consequences of this laborious review process directly impact household budgets. The most basic scheme cover now costs a single beneficiary in the region of R1 600 a month, with a family of three facing around R4 000. For most working people in South Africa, that is simply unaffordable, and it is a significant reason why medical scheme membership has stagnated even as the population has grown. Furthermore, South Africa’s healthcare “missing middle” has grown to an estimated 8 million people who access private healthcare, paying out-of-pocket, without belonging to a medical scheme.

An out-of-date framework

If the PMB list were redesigned today, using current clinical evidence, the country’s evolving disease burden, and the realities of healthcare affordability, many of its benefits would likely look very different. The current framework no longer reflects what the system can sustainably provide. And because it consumes such a large portion of every scheme’s budget, it crowds out the very things that would make cover more affordable and more useful – primary care, early intervention and prevention.

At a recent Board of Healthcare Funders conference, Dr Fatima Hoosain, a specialist breast and endocrine surgeon, set out the numbers plainly: a mammogram and ultrasound cost in the region of R2 500. Left undetected until the disease has progressed, that same patient may require R100 000 in radiation therapy, R200 000 in chemotherapy, and, for HER2-positive cancers which typically can quickly spread from the breasts to other areas of the body, roughly R7 000 every three weeks for a year in targeted biological therapy. Early detection does not only save lives, but it is also, by a wide margin, the cheaper pathway. From a cardiology perspective, Dr Martin Mpe, president of the South African Heart Association, made the same point at the conference. He argued that the cheapest way to treat a heart attack is to prevent it, and that the system needs to start rewarding prevention rather than paying only for treatment after the fact.

Rather than expanding access, an outdated PMB framework has unintentionally limited it.

A PMB framework anchored in 1999-era diagnosis-and-treatment logic has little room for rewarding the prevention and early detection that would keep patients out of the expensive end of the system altogether. Importantly, reform does not mean stripping away protection. It means modernising the list so that mandatory cover reflects today’s clinical realities. It also means rethinking how the package is defined. The current approach is built around a long, condition-by-condition diagnostic list, a modern framework could instead focus on the essential health services people need most, including preventative care, primary healthcare services, medicines on an essential medicines list, and diagnostics on an essential diagnostics list. It could also emphasise the areas where the disease burden is greatest.

A core service package

This aligns closely with the Board of Healthcare Funders’ (BHF) recent commitment to explore a Core Service Package as a practical step towards universal health coverage. By focusing on the services that deliver the greatest health benefit within available resources, such an approach would place prevention and patients at the centre of the health system while creating greater flexibility to expand affordable access.

The BHF has previously worked to operationalise South Africa’s national Essential Medicines List (EML) within the private funding environment, partnering with MediKredit in 2021 to launch a NAPPI-coded mapping tool that helps funders align benefit design and claims systems with the EML, improve medicine access, and reduce out-of-pocket costs. This existing groundwork offers an affordable, prevention-oriented foundation on which a modernised PMB package could be built.

The evidence of where the current framework falls short is already available. Annually, the Council for Medical Schemes reports on out-of-pocket expenditure, which exceeded R40 billion last year. When people spend that much of their own money on healthcare, over and above their contributions, they are pointing directly to where their cover is failing.

A broader set of changes

PMB reform does not stand alone, and it will not by itself fix affordability. It is the entry point to a broader set of changes that reinforce one another. The most important of these is regulated tariff reform. South Africa currently lacks a transparent, predictable mechanism for setting provider prices, and this absence has driven costs upward for years. Allowing schemes and willing providers to negotiate fair tariffs, within a properly regulated framework, published for transparency, would bring discipline and predictability to pricing and give members clarity on what they are paying for.

Alongside this, permitting schemes to offer low-cost benefit options, a subset of the proposed revised PMBs and based on services rendered in the public sector clinics, would extend affordable, primary-care-based cover to millions of people in South Africa who currently fall outside the system and pay out-of-pocket for private care.

None of these reforms require new legislation or a wholesale restructuring of the health system. They can be pursued within the existing regulatory framework, and PMB modernisation is the logical place to begin, because it addresses the highest single cost in every member’s contribution and unlocks the room to fund better, more preventive care.

For members, this shift would be felt less as a change to their PMB entitlements and more as a change in what their contribution actually buys before a crisis ever occurs. Money currently locked into funding late-stage, high-cost treatment for conditions that could often have been caught earlier could instead support routine age- and risk-appropriate cancer screenings, cardiovascular risk assessments and blood pressure checks, diabetes screening and management support, and the kind of primary care consultations that catch problems while they are still cheap and simple to treat. None of this is about giving members less. It is about intervening earlier, so that fewer members ever need the R100 000 radiation course, the R200 000 chemotherapy regimen, or the cardiac admission that better screening or blood pressure control could have prevented.

There is an understandable reluctance to reopen the PMB framework, given how long the review has already taken and how contested the terrain can be. The longer reform is delayed, the greater the affordability pressures on households and the greater the strain on the broader health system.

Reforming prescribed minimum benefits is ultimately about far more than updating a list of conditions. It is about creating the flexibility to expand access, strengthen prevention and make medical scheme cover affordable for more people in South Africa.

*Mothudi is the Managing Director of the Board of Healthcare Funders, which represents around 45 medical aid schemes in South Africa, including GEMS and Bonitas.

*This piece was published by Spotlight – health journalism in the public interest. Spotlight aims to deepen public understanding of important health issues by publishing a variety of views on its opinion pages. The views expressed in this article are not necessarily shared by the Spotlight editors.

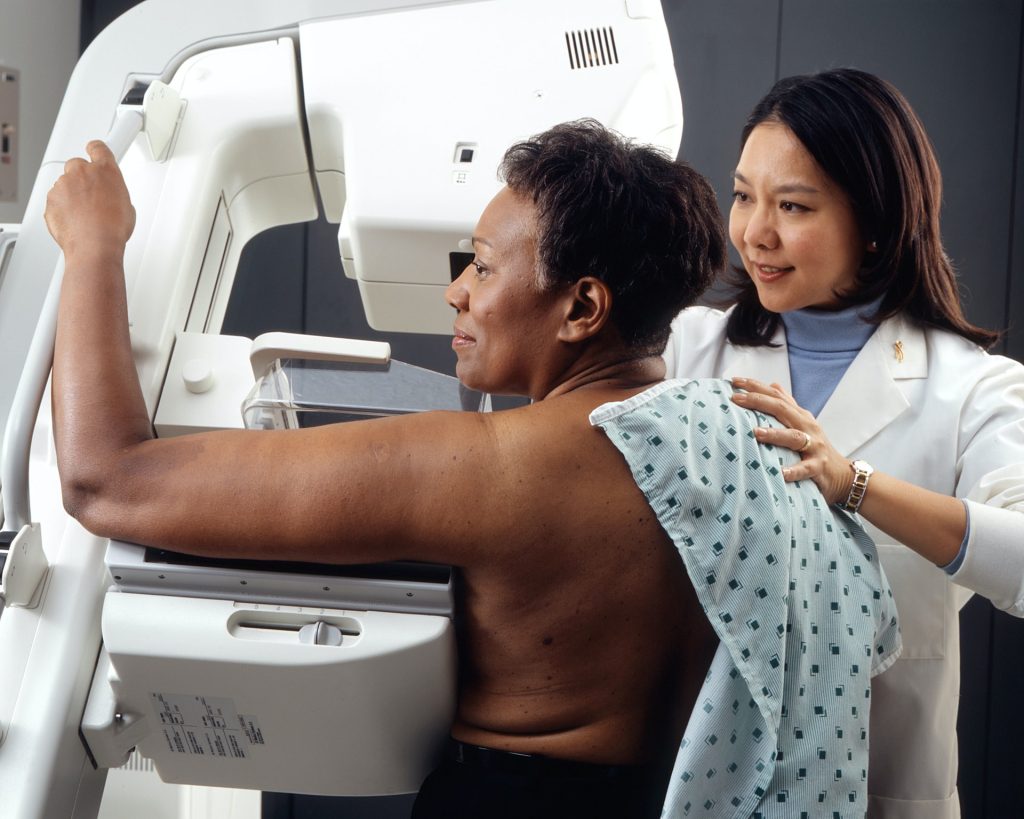
Breast Cancer Screening in South Africa: Balancing Early Detection with Appropriate Care

By Dr Fatima Hoosain, specialist surgeon and Principal of Apffelstaedt, Hoosain & Associates, with a clinical focus on breast and endocrine surgery.

Photo by National Cancer Institute on Unsplash

When people think about breast cancer screening, the conversation often begins and ends with one message: screen more women.

As clinicians, we know it is not quite that simple.

There is no question that screening saves lives. Regular mammography reduces breast cancer mortality and gives us the opportunity to diagnose disease when it is smaller, more treatable and associated with significantly better outcomes. Few interventions in medicine demonstrate such a clear benefit.

The challenge is that good breast care is not defined simply by how many mammograms we perform. It is defined by the quality of the decisions that surround them.

This was the focus of my presentation at the recent Board of Healthcare Funders (BHF) Conference, where we explored how clinicians can balance the burden of breast cancer with evidence-based screening decisions while remaining mindful of both underdiagnosis and overdiagnosis.

Those competing risks are encountered by every clinician involved in breast care.

We all worry about the patient whose cancer is diagnosed later than it should have been. Earlier diagnosis frequently means less extensive surgery, more treatment options and, ultimately, better outcomes. The survival difference between early-stage and advanced disease is substantial, making timely diagnosis one of the most important contributors to long-term prognosis.

At the same time, screening is not without consequences.

Not every abnormality detected on imaging will become life-threatening, yet every suspicious finding understandably creates anxiety. Additional imaging, biopsies and sometimes treatment may follow. Our responsibility is therefore not simply to detect abnormalities, but to interpret them appropriately within the context of each patient’s overall clinical picture.

This is why breast screening should never be approached as a uniform process. Risk matters.

A woman with an inherited genetic mutation or a strong family history should not necessarily follow the same screening pathway as someone at average risk. Likewise, imaging should answer a clinical question. Mammography remains the cornerstone of breast screening, but dense breast tissue, patient age and individual risk factors may require supplementary investigations such as ultrasound or MRI. More imaging is not automatically better medicine. Appropriate imaging is.

These decisions have become even more complex within the South African healthcare environment. International guidelines provide an excellent evidence base, but they do not remove the practical realities we face every day. Access to imaging differs between regions. Advanced investigations may not always be readily available. Medical scheme funding, co-payments and affordability inevitably influence what is possible for many patients. These factors cannot be ignored when discussing best practice because they form part of the reality in which clinical decisions are made.

Fortunately, the treatment landscape continues to evolve.

Advances in oncoplastic surgery, targeted therapies, immunotherapy and modern radiation techniques have transformed outcomes for many patients diagnosed with breast cancer. These developments are encouraging, but they should not distract us from one fundamental principle: the earlier we diagnose clinically significant disease, the greater the opportunity to offer patients treatments that are both effective and less invasive.

Diagnosis, however, is only the beginning of the journey.

Long-term follow-up remains an essential part of breast cancer care. Ongoing surveillance, adherence to endocrine therapy where appropriate, management of treatment side effects and supporting patients through the psychological and financial impact of a cancer diagnosis all influence outcomes. Good breast care extends well beyond the operating theatre or oncology unit.

As our healthcare system continues to face increasing clinical and financial pressures, I believe we need to move beyond simplistic conversations about screening uptake alone.

The more important discussion is whether we are making consistently good clinical decisions. Are we identifying the patients who stand to benefit most? Are we investigating appropriately? Are we avoiding unnecessary intervention when the evidence suggests it is unlikely to improve outcomes?

Those are not easy questions, but they are the ones that matter.

Ultimately, breast cancer screening is not about doing more. It is about doing what is right for the patient sitting in front of us. That remains the most important clinical judgement we make.

Opinion Piece: How Medical Aid Regulation Changes Are Shaping the Future Demand for Gap Cover

By Brian Harris, CEO at Turnberry Management Risk Solutions

28 July 2026 – Medical aid remains essential for accessing private healthcare in South Africa, but it does not always cover the full cost of treatment. While regulations such as Prescribed Minimum Benefits (PMBs) ensure that members have access to a defined level of care for certain conditions, medical schemes still apply tariff limits, treatment protocols, co-payments and other funding rules that can leave members exposed to out-of-pocket costs. At the same time, healthcare costs continue to rise, placing additional pressure on how schemes fund treatment. As a result, medical expense shortfalls are becoming increasingly common, making gap cover an essential part of helping clients manage their healthcare costs and protecting them against unexpected expenses.

Protection within limits

PMBs are a clear example of how scheme rules and funding limits influence what medical schemes ultimately pay for. They are designed to ensure that all medical scheme members have access to treatment for a defined list of emergencies, chronic, and life-threatening conditions. However, they do not provide unlimited funding for every treatment option, and there is often a misunderstanding about this.

When it comes to PMBs, cover is still subject to scheme rules, treatment protocols, formularies, and designated service provider requirements. In many cases, cover is also aligned to the level of care that would ordinarily be available in the public healthcare system. This becomes particularly important in areas such as oncology, where newer or more specialised treatments may fall outside what a scheme is required to fund in full.

As a result, members may still face co-payments, sub-limits, or shortfalls that need to be paid for out of pocket, even when the condition itself qualifies as a PMB.

How scheme rules create shortfalls

PMBs are only part of the picture when it comes to medical expense shortfalls. Even where treatment is covered, medical schemes reimburse according to their own tariffs and funding rules, while healthcare providers may charge significantly more. The difference between what the scheme pays and what the provider charges is the member’s medical expense shortfall.

At the same time, medical schemes use co-payments, benefit limits, Designated Service Providers (DSPs) and authorisation requirements to manage rising healthcare costs and keep contributions affordable. If these rules are not followed, or if treatment falls outside the approved funding structure, members may still need to pay part of the cost themselves.

This means that having medical aid does not always guarantee that treatment will be covered in full. Even where treatment is approved, members can still face significant out-of-pocket expenses.

Advice is essential

As funding rules become increasingly complex, advisers need to take on a more proactive role in helping clients understand and navigate the healthcare landscape. Many clients do not fully understand how PMBs, DSPs, funding rules and scheme tariffs affect what their medical aid will ultimately pay. The reality often only becomes clear at the claims stage, when members discover that they are responsible for part of the cost themselves.

Explaining these rules clearly, together with where medical expense shortfalls may arise, is therefore becoming an increasingly important part of the healthcare funding discussion. Regular reviews and clear guidance also help ensure that changes to scheme rules, benefits, and healthcare costs do not leave clients exposed to unnecessary or unexpected out-of-pocket expenses.

Future-proofing healthcare advice

Medical aid and gap cover should not be treated as once-off decisions. Scheme rules, pricing structures and healthcare costs continue to change, which means healthcare advice needs to be reviewed regularly to ensure that cover remains appropriate.

Helping clients understand how their medical aid works, where medical expense shortfalls may arise, and how gap cover can be structured forms an important part of responsible advice. Regular reviews also help ensure that changes to benefits, family circumstances or healthcare needs do not leave clients exposed to unnecessary costs.

As regulation continues to shape how healthcare is funded in South Africa, gap cover is becoming an increasingly important part of managing healthcare costs. Brokers and financial advisers play an essential role in ensuring their clients have medical aid and gap cover that together provide the right level of protection.

Turnberry Management Risk Solutions (Pty) Ltd is an authorised Financial Services Provider (FSP no. 36571). Underwritten by Lombard Insurance Company, an Authorised Financial Services Provider (FSP 1596) and Insurer conducting non-life insurance business.