Tag: mpox

Donated mpox Vaccine Stock will be Deployed as Needed, Says Health Dept as Cases Climb to 26
Vaccination for mpox is recommended for people who are at high risk of acquiring the virus and at risk of getting severe disease. (Photo: Unsplash)

By Elri Voigt for Spotlight

Twenty of this year’s 26 confirmed mpox cases came after August, concentrated mostly within the Western Cape. Elri Voigt looks at how the virus has changed and how much of the donated vaccine is left.

The viral illness mpox has caused several clusters of outbreaks across the world. In South Africa, sporadic cases have been detected, but an uptick since August has now brought the illness back into the spotlight.

As of 27 October, 26 mpox cases have been confirmed in South Africa this year, Dr Jacqueline Weyer, Head of the Centre for Emerging Zoonotic and Parasitic Diseases at the National Institute for Communicable Diseases (NICD), told Spotlight.

Of those 26 cases, 18 are in the Western Cape, three are in Gauteng, two are in the Eastern Cape, another two are in the Free State, and one is in KwaZulu-Natal. The majority of cases, 20, have been detected since August this year. All but one of these cases were in men between the ages of 23 and 50 years. One case was in a woman aged 35 to 44.

Seven people have been hospitalised, but no deaths have been reported so far this year.

SA has had a low number of cases overall

Mpox was first identified in humans in 1970, and was mostly observed in central, east and west Africa. The Democratic Republic of the Congo (DRC) was particularly affected, with thousands of cases reported since 2005.

Then in 2022, the virus spread rapidly to multiple countries for the first time. Around 140 countries have reported mpox cases since 2022, according to the World Health Organization’s mpox dashboard, with over 190 000 laboratory-confirmed cases reported and over 536 deaths to date.

The overall number of mpox cases in South Africa has been low. Our back-of-the-envelope calculation puts the total confirmed number of mpox cases since 2022 at 71. The NICD mpox dashboard lists a total of 66 cases and three deaths between 2024 and 2026. In 2023, according to Weyer, there were no reported cases of mpox in the country. There were five cases of mpox identified in 2022, according to information on the NICD’s page on mpox.

Small outbreaks

While the number of mpox cases have been relatively low to date, the current situation can be referred to as an outbreak.

Weyer told Spotlight an “outbreak” doesn’t necessarily mean a “large number” of people are affected. “Outbreaks may be large, small and confined, and for some conditions, a single case may be denoted as an outbreak.” In public health, she added, an outbreak “refers to the occurrence of cases of a disease in a particular place and period that warrants investigation and a public health response”.

When asked if there is a risk for a larger mpox outbreak in the country, Weyer is cautious.

“We cannot rule out the possibility of further cases, particularly while investigations are ongoing and local transmission has occurred previously,” she said.

“The risk of further spread depends on several factors, including how quickly cases are detected, the number and nature of contacts, the extent of transmission within affected networks, and the effectiveness of public health measures.”

Weyer added: “We have the opportunity to intervene early, identify additional cases and reduce the likelihood of further spread.” She said the NICD’s approach is to remain alert without creating unnecessary alarm. “We are continuing to strengthen surveillance, laboratory investigation, contact tracing, vaccination of eligible priority groups and public awareness,” she said.

The deal with vaccine doses

There is a limited number of donated mpox vaccines available in South Africa. Since there are currently no registered vaccines against mpox or other treatment options in the country, any vaccine or treatment used will need to be supplied via a Section 21 request, which allows for medicines that are not registered in South Africa to be brought in.

Vaccines against smallpox – which is caused by a virus closely related to the mpox virus – can offer some protection against the illness. There are three vaccines that can be used against mpox – LC16m8, MVA-BN and ACAM2000. The latter is only registered for limited use in the United States.

Last year, the Africa Centres for Disease control and Prevention (Africa CDC) donated just over 10 000 doses of the vaccine MVA-BN (known by the brand names imvanex and JYNNEOS) to the National Department of Health. These doses were used in vaccination efforts ever since, with a total of 2 365 doses administered between September 2025 and September 2026, health department spokesperson Foster Mohale told Spotlight.

There are currently 3 865 doses still available for use, according to Mohale, which will expire on 31 August 2027. We asked the health department about the remaining 4 000 or so doses but are still awaiting reply.

When asked whether any additional mpox vaccines will be procured or donated, Mohale said: “Yes, the department is currently reviewing procurement options of additional mpox vaccine doses, dependant on the recommendation from [the] Incident Management Team and the National Advisory Group on Immunisation.”

Mohale said vaccine doses are distributed to provinces as required, depending on “disease outbreak and response”.

Vaccination for mpox is recommended for people who are at high risk of acquiring the virus and at risk of getting severe disease. It can also be considered as a form of post-exposure prophylaxis for people who have been in contact with someone who has mpox.

An antiviral medicine called tecovirimat is occasionally used to treat mpox symptoms in severe cases. There is some limited stock of the drug available for use in South Africa, which Mohale said was sourced through the World Health Organization (WHO) and Africa CDC’s Access and Allocation Mechanism.

There are still more than 40 containers of tecovirimat capsules available, Mohale said. But there are not currently any plans to procure more, although he added that this will be dependent on the recommendation from the Incident Management Team and the National Essential Medicines List Committee. He did not say how many treatment courses are in a container.

In a 2025 National Department of Health mpox guideline document, the National Essential Medicines List Committee suggests that tecovirimat should only be used to treat those with severe disease who have been hospitalised.

This is because the drug has not been shown to make any significant difference in most cases of mpox. Earlier this year, results from a phase 3 study published in the New England Journal of Medicine showed that there was “no evidence that tecovirimat therapy shortened the time to clinical resolution, reduced pain, or increased viral clearance among adults with clade II mpox.”

How the outbreaks have changed since 2022

At first, mpox cases in the country were traced back to international travel. Then in 2024 and 2025 we started seeing local transmission.

Most people diagnosed with mpox in 2024 reported no recent international travel history, Weyer said, noting that “the epidemiological assessment indicated that local person-to-person transmission was occurring”.

For the current situation, Weyer said local transmission is “implied”, noting that investigations are still ongoing.

“This has been established by identifying contact links between cases, and identifying the same clade and sub-lineage of the mpox virus associated with the cases to date.”

There were some individuals who were diagnosed with mpox this year who had recently been out of the country. One of the people had recently travelled to Spain, while another had travelled to Belgium. In two other cases international travellers came to South Africa already carrying the virus.

The clades at play

The mpox virus has two clades, clade I and clade II, with several sub-clades. Professor Tulio de Oliveira, Director of the Centre for Epidemic Response and Innovation at Stellenbosch University, explained to Spotlight previously that clades are a classification system based on the genetic similarities between different strains of a virus.

“So, what it means is that when we see a genetic change [in a virus] that’s really visible and that may have impacted it, normally we call it a different clade or genotype or variant,” he said at the time.

For now, the two mpox sub-clades that are driving most cases in people are sub-clade Ib and sub-clade IIb. This year, cases of mpox in South Africa are a mix of the two sub-clades. The mpox dashboard shows that of the 26 cases, 19 were sub-clade Ib, four were sub-clade IIb, and three cases didn’t have sub-clade information available.

In 2022, sub-clade IIb was driving the mpox outbreak, said Weyer. This changed by 2024 when a new strain of the mpox virus spread beyond the DRC. Sub-clade Ib was first identified in the DRC in 2023 and was behind a large outbreak of the illness in the country that year. This sub-clade spread from the DRC through international travel and cases of sub-clade Ib were reported across the globe by 2024.

The first case of mpox where sequencing indicated sub-clade Ib in South Africa was detected in 2025, according to the NICD dashboard. There was a total of 15 mpox cases reported that year, and sequencing information was available in all but one of the cases.

Weyer said that at the moment there is not any evidence to indicate that there are additional mpox clades or sub-clades circulating in the country.

How mpox is diagnosed and managed

Knowing which clade or sub-clade someone with mpox has doesn’t change how their illness is managed. Instead, it helps scientists track outbreaks.

“Understanding the genetic character of the viruses assists us in tracking outbreaks, evolution of the viruses and identifying markers which may affect diagnostic test performance and potentially vaccine efficacy,” Weyer said.

“The central priorities remain early diagnosis, appropriate clinical care, identifying and monitoring contacts, vaccination of eligible target groups, and communicating accurate information without stigmatising affected individuals or communities. The approach is the same regardless of the current genetic character of these viruses,” she added.

Mpox is mainly spread through close contact with someone who has the virus or contact with material like bedding or clothing that has been in contact with someone with mpox.

The illness can cause flu-like symptoms – like a headache, sore throat, fever and muscle aches – as well as a distinct and often painful rash. The rash can occur on someone’s palms or soles of their feet, face, mouth and throat and sometimes the genital areas. It starts as a flat sore, then becomes a blister which can be itchy or painful. As the rash heals, the lesions dry up, crust over and fall off.

The virus has an incubation period of anything from five to 21 days – but usually it is around seven to 14 days.

“Mpox can affect anyone who has close contact with an infected person. We should avoid assumptions about who can acquire the infection and ensure that people feel able to seek healthcare without fear of judgement or discrimination,” said Weyer.

Mpox is normally diagnosed by swabbing the lesions from the rash and sending that for testing with a PCR (polymerase chain reaction) test that looks for the virus’s DNA.

While the overall case fatality for mpox is low, typically below 1%, people who are immunocompromised (such as people living with uncontrolled HIV), pregnant women, and children, have a much higher risk of severe illness, complications and even death.

In most cases, according to the mpox guideline document, symptoms can be managed at home, with rash-related pain being a particular challenge. Severe mpox cases require hospitalisation.

Someone who has mpox is considered contagious until the rash has completely gone away, and the scabs have healed. Thus, people diagnosed with mpox are advised to self-isolate until their rash has gone away completely.

“People who develop an unexplained rash, particularly when accompanied by fever, swollen lymph nodes or a history of possible exposure, should seek medical assessment,” Weyer advised. “They should avoid close physical contact with others while awaiting clinical guidance and testing. The public should understand that mpox is preventable and that early diagnosis and appropriate care are important in reducing transmission and complications.”

*This article was first published by Spotlight – health journalism in the public interest. Sign up to the Spotlight newsletter.

Key International Mpox Trial Finds No Clinical Benefit from Tecovirimat 

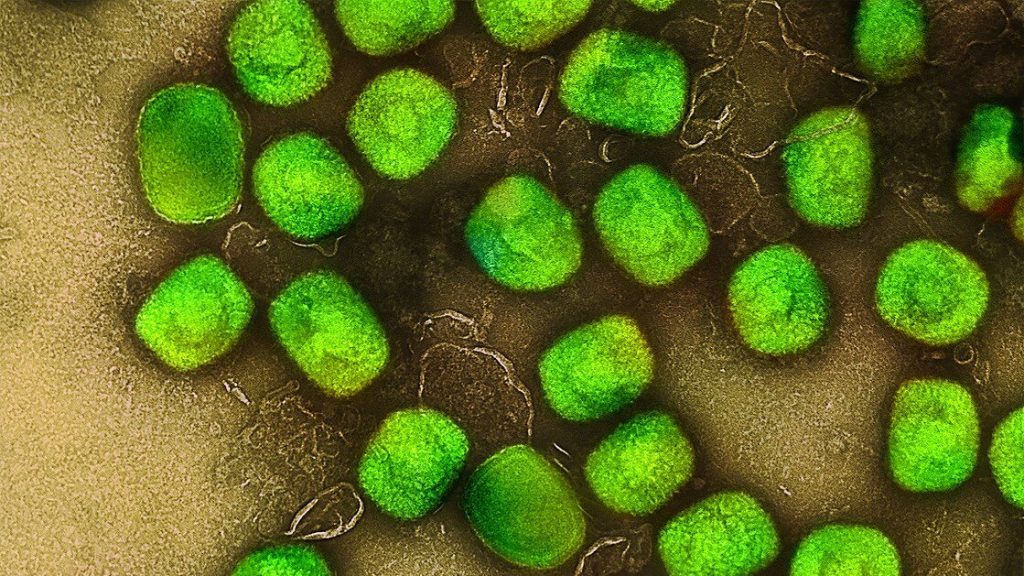
Mpox (monkeypox) virus. Source: NIH

An international, randomised, double‑blind, placebo‑controlled phase 3 study, the largest of its kind for mpox, found that tecovirimat did not improve clinical outcomes for adults with clade II mpox compared with placebo, while demonstrating a similar safety profile. Results of the STOMP/A5418 trial, published in the New England Journal of Medicine underscore both the urgent need for alternative therapeutics and the critical importance of randomised trials during public health emergencies.  

This Phase 3 study randomised 412 participants (344 with laboratory‑confirmed mpox), to receive either tecovirimat or a matching placebo for 14 days. Randomisation was stratified by early versus later symptom onset and by the presence of severe pain. Participants had active skin or mucosal lesions and self‑reported daily symptoms, pain scores, and lesion status through Day 29, with confirmatory clinical assessments at scheduled visits. Biospecimens, including lesion swabs, oral and rectal swabs, and blood samples, were collected at multiple time points to assess viral DNA clearance. The primary endpoint was time to clinical resolution of all lesions, and key secondary endpoints included pain reduction, complete lesion healing, and virologic response.  

Conducted across seven countries at 49 sites, the phase 3 study showed that tecovirimat did not shorten the time to lesion resolution, reduce pain, or speed viral clearance compared with placebo. These results align with interim findings released in December 2024, which led the trial’s independent Data and Safety Monitoring Board to halt further enrolment due to statistical futility.  

“In the midst of a global public health emergency, the ACTG team rapidly conducted this randomized controlled trial to deliver a clear answer for patients and clinicians,” said William A. Fischer II, MD, associate professor of pulmonary and critical care medicine at the UNC School of Medicine, and director of emerging pathogens research at the UNC Institute for Global Health and Infectious Diseases. “These findings advance our understanding of mpox and help the field refocus efforts on identifying safe, effective and accessible treatment strategies, particularly for people at highest risk of severe disease.” 

Although the trial did not demonstrate efficacy, tecovirimat demonstrated a favourable safety profile, with no major safety concerns identified – an important confirmation as thousands of patients worldwide have already received the drug under expanded access protocols.  

“The STOMP trial provides essential evidence at a critical time and demonstrates why randomized controlled trials are an indispensable part of outbreak response,” said Joe Eron, MD, chief of infectious diseases and chair of the ACTG network. “But now we must keep going to find safe and effective treatment for people as this virus continues to circulate globally.”  

The study’s conclusions are expected to influence clinical practice and public health guidance worldwide. With mpox still causing outbreaks in multiple regions, researchers emphasise that developing and evaluating new antiviral candidates remains a top priority.

Source:

SAHPRA Approves Mpox Test Using African Medicines Regulatory Harmonisation (AMRH) Continental EUL Procedure

Mpox (monkeypox) virus. Source: NIH

Pretoria, 27 August 2025 – The South African Health Products Regulatory Authority (SAHPRA) has approved a molecular test kit for Mpox , Cobas MPXV, for use on the Cobas 6800/8800 Systems, within nine working days through a collaborative and harmonised review process under the African Medicines Regulatory Harmonisation (AMRH). Rapid and accurate testing is essential for early detection and to enable timely treatment, and effective containment of the virus.

SAHPRA’s Medical Device Unit, utilising both the World Health Organization (WHO) Emergency Use Listing (EUL) report and the African Medicines Regulatory Harmonisation (AMRH) Continental EUL Procedure, has successfully leveraged reliance mechanisms to facilitate the review and approval of Mpox diagnostic tools. This approach has proven instrumental in accelerating access to critical health technologies, particularly in public health emergencies.

The emergency use approval of the Cobas MPXV for use on the Cobas 6800/8800 Systems, developed by Roche Molecular Systems, Inc. and licensed to Roche Diagnostics South Africa (Pty) Ltd, represents a critical advancement in expanding diagnostic capacity amid Mpox outbreaks. Rapid and accurate testing is essential for early detection, timely treatment, and effective containment of the virus.

 “As part of our efforts to promote regulatory efficiency and responsiveness, SAHPRA has successfully leveraged reliance mechanisms to facilitate the review and approval of Mpox diagnostic tools. This marks a significant milestone in supporting regional and continental harmonisation of the regulatory processes for medical devices, including In-Vitro Diagnostics (IVDs),” says Dr Boitumelo Semete-Makokotlela, SAHPRA’s Chief Executive Officer.

For more information on the AMRH continental EUL listing publication, see here: https://www.nepad.org/news/public-notice-amrh-steering-committee-approves-emergency-use-listing-of-two-mpox

Source: SAHPRA

Mpox Could Become a Serious Global Threat, Scientists Warn

Mpox (monkeypox) virus. Source: NIH

Mpox has the potential to become a significant global health threat if taken too lightly, according to scientists at the University of Surrey. In a letter published in Nature Medicine, researchers highlight how mpox — traditionally spread from animals to humans — is now showing clear signs of sustained human-to-human transmission.

Mpox is a viral infection caused by a virus that belongs to the same family as smallpox.

The virus can cause a painful rash, fever, and swollen glands and, in some cases, lead to more serious illness.

Mpox usually spreads through close contact with an infected person or animal.

Carlos Maluquer de Motes, Reader in Molecular Virology at the University of Surrey, said:

“The most recent outbreaks show that intimate contact is now a significant way the virus spreads. That shift in how it’s transmitted is leading to longer transmission chains and lasting outbreaks.”

The article notes that this change coincided with the rapid spread of clade IIb (a clade is a group of viruses that share a common ancestor) mpox viruses, but different clade I variants are now on the rise too.

Researchers are also concerned because clade I viruses are thought to be more aggressive.

These viruses appear to be accumulating specific genetic mutations — driven by enzymes in the human body — that may be changing viral properties, so the longer these viruses circulate amongst us, the higher the chances these mutations help mpox adapt to humans.

Although mpox was once mainly seen in Central Africa, the virus caused an outbreak worldwide in 2022 and is now causing outbreaks in multiple sub-Saharan countries.

While it currently affects adults the most, the researchers stress that it has the potential to spread among other groups, including children, a group at greater risk of serious illness — although sustained transmission in children has not yet been reported.

Dr Maluquer de Motes added:

“Mpox control has to climb up the global health agenda. We have limited diagnostic tools and even fewer antiviral treatments. We urgently need better surveillance and local or regional capacity to produce what we need — otherwise, we are at risk of future epidemics.”

Unlike smallpox, mpox has an animal reservoir, meaning it can’t be fully eradicated. The authors warn that unless international action is taken now — including investment in point-of-care testing and new treatments — mpox will continue to re-emerge and threaten global health.

Source: University of Surrey

SA’s HIV Burden a Concern as New Mpox Strain Spreads in DRC – but Much Still Unknown

Mpox (monkeypox) virus. Source: NIH

The African Centre for Disease Control and World Health Organization have raised the alarm following a drastic uptick in mpox cases. This surge is being driven by a new strain of the virus. Elri Voigt reports about what we know so far and potential implications for South Africa.

Mpox, a viral illness first identified in Africa in 1970, made headlines in 2022 when it spread across the globe for the first time. Since then, the outbreak has evolved, with multiple strains of the virus circulating in different countries. A new strain, known as clade Ib, first discovered in the Democratic of the Republic of Congo (DRC), is responsible for much of the most recent surge in mpox cases.

These recent developments are complex, and the situation is likely to change. This was the common theme of a special session on the mpox outbreak during the World Health Organization (WHO) Regional Committee for Africa meeting at the end of August. This session took place two weeks after the WHO declared the outbreak to be a Public Health Emergency of International Concern.

“We don’t have one outbreak. We have multiple outbreaks in one,” Dr Jean Kaseya, the Director General of the African Centre for Disease Control (CDC) remarked.

These outbreaks are caused by different clades of the mpox virus. Clades are a classification system based on the genetic similarities between different strains of a virus, explained Professor Tulio de Oliveira, Director of the Centre for Epidemic Response and Innovation (CERI) at Stellenbosch University (SU). “So, what it means is that when we see a genetic change [in a virus] that’s really visible and that may have impacted it, normally we call it a different clade or genotype or variant,” he said.

This is similar to classifying different strains of SARS-CoV-2 as variants, Dr Duduzile Ndwandwe, a molecular biologist working for Cochrane South Africa, an intramural research unit within the South African Medical Research Council, told Spotlight.

She explained that the different mpox clades and sub-clades have mutated so they have genetic differences but still fall under the umbrella of mpox.

“In a nutshell…it’s just talking about the differences in the genome sequence of the virus, how many mutations [it has] or how big the mutations are in that virus’s strain of mpox,” she said.

‘Jump in evolution’

Dr Aida Sivro, senior scientist at the Centre for the AIDS programme of Research in South Africa (CAPRISA), in 2022 told Spotlight that there are two clades of the mpox virus, which were then referred to as the Central African Clade (clade I) and the West African Clade (clade II).

Since then, clade I went through a big jump in evolution and a sub-clade emerged in the DRC, now called clade Ib, De Oliveira told Spotlight. The previous outbreak in 2022 was mostly driven by another sub-clade called clade IIb.

To further complicate matters, there’s a third strain of the virus also circulating – clade Ia.

At the moment, the DRC accounts for about 90% of mpox cases in the African Region, according to Dr Fiona Braka, the Emergency Response Manager for WHO’s AFRO region. She explained that right now the situation is not fully understood because a lack of diagnostics and testing capabilities is limiting understanding of the true burden of disease.

What we do know, she said, is that there are two distinct outbreaks in the DRC. Based on the information currently available, clade Ia is circulating in regions in the country where mpox is considered endemic and affecting mostly children. While clade Ib is spreading mostly among adults in the eastern provinces of South Kivu and North Kivu.

The clade Ib strain has since spread from the DRC to neighbouring countries Burundi, Rwanda, Uganda and Kenya, according to Braka. Sweden and Thailand have also identified one case each.

As of 1 September, the WHO reported that there have been 3 751 confirmed cases of mpox and 32 deaths across 14 countries in African in 2024 alone. But there are many more suspected cases of mpox that have not been tested.

Implications for South Africa

De Oliveira said at this point, South Africa shouldn’t be overly concerned about mpox, but it should be alert. The best way to do this is to make sure the public know what the symptoms are so they can present for diagnosis and treatment if they suspect they have the virus.

In a similar vein, Ndwandwe said the public shouldn’t panic, but we as a country need to remain vigilant. She added that because clade Ib is spreading on the African continent, there is a risk of it spreading to South Africa through cross-border travel, making it a public health concern.

This year, 24 cases of mpox have been reported in South Africa. Three people have died, while 19 have recovered. Two people are still considered to have active disease, with the most recent case identified in early August.

But this doesn’t necessarily mean there aren’t more cases of mpox in the country. “What we do suspect is that we may have milder cases that are actually not reported,” Nevashan Govender, the operation manager of the Emergency Operations Center at the National Institute for Communicable Diseases (NICD) told Spotlight.

He said so far, all the cases in the country have been caused by clade IIb and no cases of clade Ib have been identified.

A polymerase-chain-reaction (PCR) test is the gold standard test used to determine whether someone has mpox. But genome sequencing would need to be done to identify what clade they have.

Lots of unknowns around new strain

At the moment, there are a lot of unknowns around clade Ib.

What is of concern, according to Braka is the severity of disease seen especially in people who are immunocompromised and in pregnant women and children. Ndwandwe added to this and said there is a concern that clade Ib has higher fatality rates than clade IIb.

De Oliveira cautioned against jumping to conclusions about the severity of this new clade without sufficient data. He said we don’t know for sure yet if clade Ib is causing more severe disease than IIb. What we do know from mpox in general, he said, is that when someone is immunocompromised in some way, they tend to develop more severe symptoms.

Govender echoed De Oliveira’s caution that we don’t yet know enough about clade Ib to say definitively if it is for example more transmissible than other clades

“It’s not to say that it isn’t [more transmissible], but there is just not a lot of evidence stating that it is absolutely true…There’s a lot of knowledge and information gaps,” he said.

The NICD in a recent update also stressed that there are a lot of unknowns about this new strain. It added: “South Africa continues to prioritise enhanced surveillance and raising awareness for mpox.”

The state of vaccines and treatment for mpox

Spotlight reported previously that the smallpox vaccine, which hasn’t been routinely administered in South Africa since the 1980s when smallpox was eradicated, is thought to offer some degree of protection against mpox. However, it’s difficult to predict just how much protection the smallpox vaccine would provide, Sirvo told Spotlight for that previous article.

There are currently three vaccines against mpox that have been approved in some countries, a spokesperson from the vaccine alliance Gavi told Spotlight. These are LC16m8, JYNNEOS and ACAM2000.

LC16m8 is a third-generation small pox vaccine manufactured by KM Biologics. According to WHO, from 2022 it had mainly been used in Japan.

The JYNNEOS vaccine is a third-generation smallpox vaccine, manufactured by Bavarian Nordic, Ndwandwe said, and it was used during the outbreak in 2022. She added that this vaccine is considered the preferred option due to its safety profile and targeted protection against mpox.

ACAM2000 is a second-generation vaccine for smallpox and manufactured by Emergent BioSolutions. But it was only approved by the FDA for use in those at high risk for mpox at the end of August this year. It was not widely used during the 2022 outbreak but was available in some places under a compassionate use protocol (a means of providing medicines or vaccines that have not yet been registered).

In 2022, the Centre for Disease Control (CDC) recommended that JYNNEOS be used as the primary vaccine against mpox because it was associated with fewer side effects than ACAM2000.

While these vaccines exist, it doesn’t mean everyone can access them easily. Countries on the African continent have so far relied on vaccine donations facilitated by the WHO, with an initial 10 000 doses expected to arrive in Africa sometime this month.

Vaccine manufacturers KM Biologics and Bavarian Nordic have submitted proposals to the WHO for emergency use listing (EUL), according to WHO Director-General Dr Tedros Adhanom Ghebreyesus. He added this will allow UNICEF and the vaccine alliance GAVI to buy the vaccines to supply to countries that haven’t issued their own national regulatory approval yet.

The treatment options for mpox are also limited. According to this WHO factsheet on mpox, some antivirals have received emergency use authorisation in some countries and are being evaluated in clinical trials. However, so far there is no proven effective antiviral treatment for mpox.

Tecovirimat, which was approved to treat smallpox, is one of these antivirals being evaluated. According to the CDC, studies in animals have shown the antiviral might help treat mpox but it is still considered an investigational drug for mpox. The drug has been used in some cases of severe mpox.

When asked about this, Ndwandwe agreed more research needs to be conducted to fully understand the evidence around using Tecovirimat. “But what we know now is that the fact that it was authorised for compassionate use, there is some benefit to using that treatment, given that there isn’t any other [treatment,” she said.

Mpox vaccine and treatment availability in South Africa

According to De Oliveira, a small batch of vaccines against mpox and an antiviral drug were made available to South Africa through donations during the outbreak earlier this year.

But the country would need more vaccines if cases increase to protect those at risk for severe disease.

At the moment, South Africa does not have access to any mpox vaccines and has asked for a donation of 40 000 vaccine doses, Foster Mohale, spokesperson for the health department told Spotlight. The country has requested the JYNNEOS vaccine, based on the recommendation by the National Advisory Group on Immunisation.

He added that South Africa’s request to its international partners and the WHO is ongoing support with access to tecovirimat should the need increase. He also requested the WHO’s assistance in procuring the 40 000 vaccine doses to vaccinate high-risk groups if mpox cases increase.

When asked if the department will be entirely reliant on donations of mpox vaccines or would seek to procure its own if cases increase, Mohale said it depends. “South Africa has been in communication with the vaccine manufacturer, Bavarian Nordic, and will consider procurement if needed,” he added.

Because there is a shortage of mpox vaccines and treatment and uncertainty about the sustainability of donated supplies, Ndwandwe said: “Our best defence at this point in time is to prevent [the spread of mpox cases] as much as possible and detect the cases as they start, early on.”

Symptoms of mpox

Govender said the NICD is urging people not to panic but to stay informed on the signs and symptoms of mpox using some of the accurate information available from either the National Department of Health or the NICD.

“The first line of defence for any public health emergency and outbreak comes from when people take initiative to protect themselves,” he said.

Mpox, which is spread by close contact, either household or sexual contact, with someone who has the virus, could initially manifest in flu-like symptoms or the characteristic mpox rash. These include a fever, sore throat, muscle aches, headaches and swollen lymph nodes, according to the WHO factsheet on mpox. The rash starts flat and then becomes a blister filled with fluid, which eventually dries and falls off. The rash can occur on someone’s palms or soles of their feet, face, mouth and throat and sometimes the genital areas.

Children, pregnant women and those who are immunocompromised are most at risk for developing severe disease or dying, the factsheet stated. This includes people living with HIV whose viral load is not well controlled.

Mpox is a virus and as with all viral infections it’s the immune system that fights it off, Ndwandwe explained. However, if someone is immunocompromised, so has a weakened immune system, there is a greater chance that the mpox virus will overtake their immune system and cause severe disease.

This is one of the reasons why we would be concerned about the disease in South Africa, Professor Helen Rees, the Co-Chair of the Incident Management Team (IMT) on mpox, previously told eNCA.

“We have many people living with HIV in the country, many of whom are on antiretroviral therapy, their immune system is good. But we have many others, who don’t know what their status is and might be vulnerable to severe mpox,” she said.

Republished from Spotlight under a Creative Commons licence.

Read the original article

WHO Declares International Public Health Emergency over Mpox Outbreak

Mpox (monkeypox) virus. Source: NIH

WHO Director-General Dr Tedros Adhanom Ghebreyesus has determined that the upsurge of mpox in the Democratic Republic of the Congo (DRC) and a growing number of countries in Africa constitutes a public health emergency of international concern (PHEIC) under the International Health Regulations (2005) (IHR).

Dr Tedros’s declaration came on the advice of an IHR Emergency Committee of independent experts who met earlier in the day to review data presented by experts from WHO and affected countries. The Committee informed the Director-General that it considers the upsurge of mpox to be a PHEIC, with potential to spread further across countries in Africa and possibly outside the continent.

The Director-General will share the report of the Committee’s meeting and, based on the advice of the Committee, issue temporary recommendations to countries.

In declaring the PHEIC, Dr Tedros said, “The emergence of a new clade of mpox, its rapid spread in eastern DRC, and the reporting of cases in several neighbouring countries are very worrying. On top of outbreaks of other mpox clades in DRC and other countries in Africa, it’s clear that a coordinated international response is needed to stop these outbreaks and save lives.”

WHO Regional Director for Africa Dr Matshidiso Moeti said, “Significant efforts are already underway in close collaboration with communities and governments, with our country teams working on the frontlines to help reinforce measures to curb mpox. With the growing spread of the virus, we’re scaling up further through coordinated international action to support countries bring the outbreaks to an end.”

Committee Chair Professor Dimie Ogoina said, “The current upsurge of mpox in parts of Africa, along with the spread of a new sexually transmissible strain of the monkeypox virus, is an emergency, not only for Africa, but for the entire globe. Mpox, originating in Africa, was neglected there, and later caused a global outbreak in 2022. It is time to act decisively to prevent history from repeating itself.”

This PHEIC determination is the second in two years relating to mpox. Caused by an Orthopoxvirus, mpox was first detected in humans in 1970, in the DRC. The disease is considered endemic to countries in central and west Africa.

In July 2022, the multi-country outbreak of mpox was declared a PHEIC as it spread rapidly via sexual contact across a range of countries where the virus had not been seen before. That PHEIC was declared over in May 2023 after there had been a sustained decline in global cases.

Mpox has been reported in the DRC for more than a decade, and the number of cases reported each year has increased steadily over that period. Last year, reported cases increased significantly, and already the number of cases reported so far this year has exceeded last year’s total, with more than 15 600 cases and 537 deaths.

The emergence last year and rapid spread of a new virus strain in DRC, clade 1b, which appears to be spreading mainly through sexual networks, and its detection in countries neighbouring the DRC is especially concerning, and one of the main reasons for the declaration of the PHEIC.

In the past month, over 100 laboratory-confirmed cases of clade 1b have been reported in four countries neighbouring the DRC that have not reported mpox before: Burundi, Kenya, Rwanda and Uganda. Experts believe the true number of cases to be higher as a large proportion of clinically compatible cases have not been tested.

Several outbreaks of different clades of mpox have occurred in different countries, with different modes of transmission and different levels of risk.

The two vaccines currently in use for mpox are recommended by WHO’s Strategic Advisory Group of Experts on Immunization, and are also approved by WHO-listed national regulatory authorities, as well as by individual countries including Nigeria and the DRC.

Last week, the Director-General triggered the process for Emergency Use Listing for mpox vaccines, which will accelerate vaccine access for lower-income countries which have not yet issued their own national regulatory approval. Emergency Use Listing also enables partners including Gavi and UNICEF to procure vaccines for distribution.

WHO is working with countries and vaccine manufacturers on potential vaccine donations, and coordinating with partners through the interim Medical Countermeasures Network to facilitate equitable access to vaccines, therapeutics, diagnostics and other tools.

WHO anticipates an immediate funding requirement of an initial US$ 15 million to support surveillance, preparedness and response activities. A needs assessment is being undertaken across the three levels of the Organization.

To allow for an immediate scale up, WHO has released US$ 1.45 million from the WHO Contingency Fund for Emergencies and may need to release more in the coming days. The Organization appeals to donors to fund the full extent of needs of the mpox response.

Source: WHO

Debunking Myths About Mpox

Mpox (monkeypox) virus. Source: NIH

Myths are widely held beliefs about various issues, including illness and disease. They come about through frequent storytelling and retelling. Dr Themba Hadebe, Clinical Executive at Bonitas Medical Fund, helps debunks myths about monkeypox (mpox).

Myth 1: Mpox (formerly monkeypox) is a new disease created in a lab

Fact: The mpox virus was discovered in Denmark (1958) in a colony of monkeys at a laboratory kept for research.  The first reported human case was in 1970 in the DRC. Mpox is a zoonotic disease, meaning it can be spread between animals and people. It is found regularly in parts of Central and West Africa and can spread from person to person or occasionally from animals to people.  

Myth 2: Mpox comes from monkeys

Fact: Despite its name, monkeypox does not come from monkeys. The disease earned the name when the ‘pox like’ outbreaks happened in the research monkeys. While monkeys can get mpox, they are not the reservoir (where a disease typically grows and multiplies). The reservoir appears to be rodents.

Myth 3:  Only a handful of people have contracted mpox

Fact: Globally, more than 97 000 cases and 186 deaths were reported across 117 countries in the first four months of 2024. South Africa is among the countries currently experiencing an outbreak.  On the 5 July, it was reported that the number of mpox cases in the country has risen to 20. This after four more cases have been confirmed in Gauteng and KwaZulu-Natal in the last few days.

15 patients have, however been given a clean bill of health.

Myth 4:  It is easy to diagnose mpox

Fact: It is easy to mistake mpox for something else. While the rash can be mistaken for chickenpox, shingles or herpes, there are differences between these rashes. Symptoms of mpox include fever, sore throat, headache, muscle aches, back pain, low energy and swollen lymph nodes. Fever, muscle aches and a sore throat appear first. The rash begins on the face and spreads over the body, extending to the palms of the hands and soles of the feet and develops over 2-4 weeks in stages. The ‘pox’ dip in the centre before crusting over.

Laboratory confirmation is required. A sample of one of the sores is diagnosed by a PCR test for the virus (MPXV).

Myth 5: Mpox is easily treated

Fact: ‘Currently,’ says the National Institute for Communicable Diseases (NICD), ‘there is no registered treatment for mpox in South Africa. However, the World Health Organization (WHO) recommends the use of TPOXX for treatment of severe cases, in immunocompromised people’. However, the Department of Health (DoH) has only obtained this treatment, with approval on a compassionate use basis, for the five known patients with severe disease.

There is no mpox vaccine currently available in South Africa.

Myth 6: You can get mpox from being in a crowd or from a public toilet seat

Fact: Mpox is not like Covid-19 which is highly contagious. It spreads through direct contact via blood, bodily fluid, skin or mucous lesions or respiratory droplets.

It can also spread though bites and scratches. Studies have shown that the virus can stay on surfaces but it is not spreading in that way or in a public setting. The risk of airborne transmission appears low.

Myth 7: Mpox is deadly

Fact: While mpox lesions can look similar to smallpox lesions, mpox infections are much milder and are rarely fatal. That said, symptoms can be severe in some patients, needing hospitalisation and, in rare cases, result in death. It is, however, painful and very unpleasant. So, it is important to avoid infection.

Myth 8: Mpox is sexually transmitted

Fact: You can become infected though close, direct contact with the lesions, rash, scabs or certain bodily fluids of someone who has mpox. Even though this could imply transmission though sexual activity, it is not limited to that.  You can also be exposed if you are in close physical proximity to infected people, such as spouses or young children who sleep in the same bed.

Myth 9: I can’t protect myself from getting Mpox

Fact:  You can take precautions: Avoid handling clothes, sheets, blankets or other materials that have been in contact with an infected animal or person. Wash your hands well with soap and water after any contact with an infected person or animal and clean and disinfect surfaces. Practice safe sex and use personal protective equipment (PPE) when caring for someone infected with the virus.

Myth 10:  You can’t stop other people being infected by you

Fact: You may not protect them by 100% but you can isolate. Also, alert people who have had recent contact with you.  Wash your hands regularly with soap and water or use hand sanitiser, especially before or after touching sore and disinfected shared spaces.  Cover lesions when around other people, keep skin dry and uncovered (unless in a room with someone else).

Mpox is a notifiable medical condition but is treatable, if you are concerned, call the DoH toll free number of 0800 029 999 but remember, your GP is your first port of call for all your healthcare needs.

More Monkeypox Antibodies with Childhood Smallpox Vaccination

Mpox (monkeypox) virus. Source: NIH

In a study published in Cell Host & Microbe, scientists studied the sensitivity of MPXV, the virus that causes mpox (formerly monkeypox) to neutralising antibodies (NAbs) generated after infection with the virus and/or vaccination with IMVANEX. They found that those who had been born before 1980 had more antibodies in response to either IMVANEX vaccination or mpox infection, highlighting the lasting protection of smallpox vaccination.

The IMVANEX vaccine has been used as pre- and post-exposure prophylaxis in high-risk populations, but its effectiveness is not yet well characterised. To analyse the sensitivity of the virus, a team of scientists led by Pasteur Institut developed two cellular tests to quantify neutralising antibodies, using either the attenuated virus as a vaccine (MVA) or an MPXV strain isolated in a recently infected individual.

In 2022-2023, an unprecedented epidemic of 87 000 cases of mpox occurred in non-endemic areas, affecting people with no direct link to travel in Central or West Africa, where the virus has historically been present. MPXV is mainly transmitted to humans by rodents, with human-to-human transmission occurring via respiratory droplets or close contact. Symptoms are less severe than those of smallpox, and the case-fatality rate is lower. MPXV is still circulating at very low levels in non-endemic areas, which is why it is important to improve characterisation and analyse the immune response of people infected with the virus or vaccinated with IMVANEX, the third-generation vaccine currently available, initially developed for smallpox.

The large number of sera analysed provided good statistical power, meaning that the analysis could be narrowed to subgroups of patients based on various criteria such as age.

The study demonstrated the role of complement, already known for other poxviruses, and the neutralising activity of the antibodies generated by infection or vaccination. Robust levels of anti-MVA antibodies were detected after infection, vaccination with the historic smallpox vaccine, or administration of IMVANEX or another MVA-based vaccine candidate. MPXV was minimally sensitive to neutralisation in the absence of complement. The addition of complement from sera enhanced detection of individuals with antibodies and increased their level of anti-MPXV antibodies. Four weeks after infection, anti-MVA and -MPXV NAbs were observed in 94% and 82% of individuals, respectively. Two doses of IMVANEX generated anti-MVA and -MPXV NAbs that were detectable in 92% and 56% of vaccinees, respectively.

The highest level of antibodies was found in individuals born before 1980 (who had therefore been vaccinated for smallpox), whether after infection or after administration of IMVANEX, highlighting the impact of historic smallpox vaccination on immune responses to infection or administration of IMVANEX. This suggests that a sort of hybrid immunity was generated in infected individuals who were vaccinated in childhood.

The number of MPXV infections has been constantly on the rise since mass vaccination for smallpox was discontinued in the 1980s. “The neutralisation assays developed in connection with this research may help define correlates of protection against infection or disease severity. The assays can also be used to conduct epidemiological surveys, assess the duration of protection conferred by previous infection or by authorised and candidate vaccines, and analyse the use of immunotherapeutic intervention. The assays represent useful tools to understand the mechanisms of multiplication of MPXV and its effects on public health, and to optimsze patient treatment,” commented Olivier Schwartz, Head of the Institut Pasteur’s Virus and Immunity Unit and last author of the study.

Source: Institut Pasteur