

Tag: Spotlight

El Niño is Here. Are KZN Clinics Ready?

By Christina Pitt for Spotlight

With El Niño conditions expected to bring a hotter, drier summer, Spotlight asks whether the KwaZulu-Natal government is ready to keep health services running and protect vulnerable communities during the extreme weather that may be on the way.

For Phumelele Shabalala, extreme weather has made an already difficult life harder.

The 46-year-old has lived in Vimbukhalo, a rural village near Bergville in KwaZulu-Natal’s Drakensberg foothills, for 24 years.

Shabalala grows vegetables to sell and help feed her four children. But during a dry spell in 2024, she says streams began drying up and her maize crops started dying.

Another resident in the area told Spotlight that they had lost cattle to dehydration and untreated wounds caused by sun exposure, threatening livelihoods dependent on farming.

In nearby Stulwane village, 28-year-old Nondumiso Nokwanda Sigubudu has experienced a different kind of devastation.

Heavy rainfall damaged her home in October 2025 and again in October this year, she says. Part of a wall remains open, exposing her family to the cold and leaving their home unsecured. Sigubudu believes the conditions have affected her two children’s health, saying they frequently suffer from colds and fevers.

Extreme weather can also make it difficult for residents to get medical care.

A mobile clinic visits Vimbukhalo once a month for check-ups and chronic medication refills. But Shabalala says it sometimes cannot reach the village when heavy rain makes roads impassable, leaving residents waiting for another visit or seeking alternative care.

Such disruptions are particularly concerning as El Niño, a natural climate pattern that can affect rainfall in southern Africa and increase the risk of drought, is forecast to strengthen towards the end of 2026.

KwaZulu-Natal has a long history of droughts and floods. According to a Council for Scientific and Industrial Research report, the province recorded 85 declared weather- and climate-related disasters between 2007 and 2021 — more than any other province.

For vulnerable communities in rural KwaZulu-Natal, this raises an urgent question: how prepared is the province to protect them and keep essential health services running when extreme weather strikes?

El Niño, KZN and what’s at stake

El Niño occurs when sea surface temperatures in the central and eastern tropical Pacific Ocean become unusually warm, disrupting atmospheric circulation and influencing weather patterns around the world.

South Africa’s seasonal outlook indicates an increased likelihood of below-normal rainfall across much of the country between December 2026 and February 2027, Dr Nosipho Zwane of the South African Weather Service said during a health department webinar in October.

But drought is not inevitable.

“El Niño is often associated with hotter and drier summer conditions. However, this does not happen exactly the same way every time,” Zwane said.

Speaking to Spotlight, University of Pretoria meteorology professor Willem Landman cautions that seasonal forecasts cannot predict individual storms or flash floods months ahead. Even a drier-than-average season can bring intense downpours and localised flooding.

Although El Niño is a natural phenomenon, its effects can be compounded by climate change. The World Meteorological Organization says there is no evidence that climate change is increasing the frequency or intensity of El Niño events, but a warmer atmosphere and ocean can amplify associated extremes, including heatwaves and heavy rainfall.

Hotter conditions increase the risks of heat exhaustion, heatstroke and worsening chronic illnesses, particularly among pregnant and postpartum women, young children, older people and outdoor workers, says public health specialist Celeste Madondo of the Foundation for Professional Development.

Research in rural KwaZulu-Natal has also linked heat exposure to adverse pregnancy outcomes. One study found a “clear relationship between maternal heat exposure during the month preceding conception and miscarriage”.

But the health risks of extreme heat are not always immediately apparent.

“The difficulty with heat is that you can’t see it. You can feel it, but you can’t necessarily see its effects,” Madondo says. “With droughts and floods, the damage is visible. You can see the flooding. You can see that your house is gone.”

Dam levels versus rural realities

While extreme heat poses health risks of its own, reduced rainfall can also threaten the water supplies and livelihoods that rural communities depend on.

South Africa’s major dams were 97.7% full on average in October, compared with 88.3% in KwaZulu-Natal. But Landman says these figures do not necessarily reflect water availability in rural communities dependent on streams, boreholes and rainfall.

For farming households, less water can mean fewer crops, livestock losses and reduced income. As Landman puts it: “If you don’t plant, you don’t have food.”

Drought can also make it harder for people to stay on HIV treatment. In KwaZulu-Natal, almost 1.6 million people were receiving antiretroviral treatment in 2025, according to Thembisa, the leading mathematical model of HIV in South Africa.

Research by the Africa Health Research Institute (AHRI) examined the impact of drought on HIV treatment in rural KwaZulu-Natal, analysing records from more than 40 000 people at 17 clinics between 2010 and 2018. The study found that drought was associated with fewer patients taking their medication as prescribed or staying in HIV care, with some recovery after the drought.

A related study, based on interviews with 27 people living with HIV in rural Hlabisa, in the uMkhanyakude district, explored how the 2015–2016 El Niño-related drought affected access to treatment.

Collins Iwuji, a professor of climate, environment and health at AHRI and co-author of both studies, says food insecurity was among the challenges patients faced.

“During the drought, the price of food was also going up and they didn’t want to take their pills on an empty stomach, because of the potential side effects,” Iwuji explains. “So what some of them did was they skipped the pill.”

Others missed clinic appointments while collecting water or lost contact with their usual clinics after moving with their livestock in search of water.

Iwuji cautions that their work could not prove that drought caused these treatment interruptions, although participants’ accounts suggested that drought-related hardship played a role.

Asked whether the province’s HIV services are now better prepared for climate-related disruptions, Iwuji says improvements have been “partial rather than systematic”.

Measures such as allowing people living with HIV to collect three to six months of medicines at a time and community medicine collection points can reduce the need for frequent clinic visits. But Iwuji says these services expanded significantly during the COVID-19 pandemic, rather than in response to climate-related emergencies.

Is KZN ready?

The question of preparedness extends beyond HIV services. The devastating floods of April and May 2022 exposed serious problems within the province’s preparedness for extreme weather.

The Presidential Climate Commission described the government’s response as largely reactive, identifying poor coordination between departments, inadequate preparation, and gaps in getting early warnings to vulnerable communities.

Problems were also evident within the health system. A 2026 study⁠ involving staff at a KwaZulu-Natal provincial tertiary hospital found that the facility lacked specific plans for weather-related emergencies when researchers collected data in 2023. Staff also reported shortages of personnel and resources, difficulties obtaining emergency supplies and poor communication.

In November 2023, the National Department of Health, working with the World Health Organization (WHO), began establishing a network of Public Health Emergency Operations Centres (PHEOCs) to strengthen preparedness and coordination.

Despite these efforts, a draft health-sector readiness assessment presented by the national health department’s Director of Epidemiology and Surveillance, Mbhekiseni Khumalo, at a webinar in October suggests significant gaps remain.

The country scored 61% across 11 areas of preparedness. Rapid response teams and communication with communities lagged at 45%, while coordination received just 28%. Health service delivery performed better at 82%. The assessment reflects preparedness nationally rather than in KwaZulu-Natal specifically. The findings are preliminary, with supporting evidence attached for only 10% of the indicators assessed.

In KwaZulu-Natal, the provincial health department says it has put measures in place to prepare for extreme weather emergencies.

“The department receives weather warnings through the Provincial Disaster Management Centre, the South African Weather Service application and the National PHEOC WhatsApp channel,” says provincial department spokesperson Ntokozo Maphisa.

This information is then shared with all district health emergency teams, which then put response measures into action.

Maphisa says the department has also developed backup plans for floods, heatwaves, fires and other emergencies, with instructions for healthcare workers. The department also works with other sectors to maintain essential health services, according to Maphisa.

From weather warnings to action

One challenge is ensuring that weather warnings reach healthcare facilities and communities in time for them to act.

A R46.5-million WEATHER project, involving the University of KwaZulu-Natal and international partners, aims to improve how flood notifications reach clinics and hospitals.

“Published research has already shown that official warnings did not reach some eThekwini community health centre managers in 2022. Closing that gap between warning and facility action is at the centre of the system we are designing,” says one of the project’s principal investigators, Professor Saloshni Naidoo.

The research also found that the centres’ emergency plans lacked clear instructions for responding to weather-related disruptions.

Naidoo explains that the proposed system would combine official weather warnings with practical advice for health workers, such as checking medicine supplies and contacting patients on chronic treatment. These aspects of the system still need to be developed with the provincial health department.

The system is being designed to reach rural communities with poor internet connectivity.

Maphisa confirms that senior provincial health managers are involved in the project, which is expected to be tested in early 2027 and evaluated later that year. It will therefore not be operational during the coming summer.

Can hospitals and clinics withstand the next disaster?

The condition of clinic and hospital buildings is another important part of preparing for extreme weather.

The provincial health department has been repairing facilities damaged by severe storms, including the 2022 floods.

Its Strategic Plan 2025/26–2029/30 lists 47 repair projects involving roofs, gutters and drainage systems. At the time of the plan, four were complete, 19 under construction, 18 at the tender stage and six still being planned.

But repairing damage does not necessarily make facilities more resilient to future extreme weather.

The Presidential Climate Commission has warned that rebuilding damaged infrastructure without making it better able to withstand extreme weather could leave it vulnerable to future disasters.

Iwuji says making healthcare facilities more resilient starts with assessing the risks each building faces.

He says the WHO has developed a framework for assessing facilities’ vulnerability to floods, storms, extreme heat and drought, as well as their capacity to cope with these threats. Such assessments can help determine what improvements each facility needs.

Extreme heat presents another challenge, particularly in ageing healthcare buildings.

“The buildings are old. The aircons don’t work. It’s not maintained,” Iwuji says. “Now if you have an overcrowded facility that’s hot, the healthcare workers are also experiencing the effects of the heat. But we expect them to ensure that they serve clients to the best of their ability under these conditions.”

The KwaZulu-Natal health department did not answer Spotlight’s questions about whether the repairs include measures to make healthcare facilities more resilient to future extreme weather.

Iwuji acknowledges that the province has made progress in improving coordination between departments since the 2022 floods, but questions how far these changes have translated into action. “There is movement towards creating some resilience. But in terms of practical implementation and what that means, that is what I haven’t seen yet,” he says.

*This article was first published by Spotlight – health journalism in the public interest. Sign up to the Spotlight newsletter.

Menopause in SA: Women Want Answers, not ‘Old Granny’ Labels

By Joan van Dyk for Spotlight

Menopause, defined as a year with no periods, marks the end of a woman’s reproductive years. Photo by Ayo Ogunseinde on Unsplash

Across the country’s townships and rural clinics, women are breaking inherited silences to redefine reproductive ageing on their own terms.

In South Africa, women are challenging the silence around menopause, and the expectation to endure it without support.

This is significant because research suggests that some women in South Africa never discuss menopause with a healthcare worker. In a 2017 study of 450 black women in communities near Pretoria, more than three-quarters had never sought medical help for their symptoms, possibly, researchers argue, because of a cultural view of menopause as a positive natural process.

Menopause, defined by the World Health Organisation (WHO) as a year with no periods, marks the end of a woman’s reproductive years. It’s a natural transition brought on as the ovaries stop releasing eggs and oestrogen levels fall, usually between the ages of 45 and 55. Joint and muscle pain, exhaustion, poor memory and hot flushes are among the most common symptoms, but a new review suggests there are up to 72 possible symptoms.

Hormone replacement therapy is the most effective treatment to ease hot flushes, according to South African Menopause Society (SAMS) guidance, but whether it’s the right choice will depend on each person’s medical history and preferences.

After researching women’s perceptions of menopause in Gauteng and North West, researcher Sostina Matina now believes that the limited use of menopause treatments in South Africa’s public healthcare sector should not be mistaken for a rejection of clinical care. Many women, she says, had simply never had their options explained to them.

Xoli Madlala, who experienced menopause early, has made it her personal mission to bring menopause out into the open. She travels across the country, speaking in settings ranging from corporate boardrooms to rural Bible study groups.

Wherever she goes, she says, women of different ages are open to talking about a subject that previous generations were often expected to endure without discussion.

How clinic staff can fuel midlife myths

Midlife women seeking menopause symptom relief are often turned away by health workers, Matina says, especially if they’re experiencing symptoms earlier than usual or as a result of surgery.

“They’ll say ‘it’s just menopause, there’s nothing we can do’,” she says.

Yet, on paper, treatment should be available.

The country’s treatment guidelines for clinics and hospitals include menopausal hormone therapy pills that can ease hot flushes and other symptoms. Women who have had a hysterectomy can usually be prescribed pills with only oestrogen. Those with a womb also need to take progestogen because oestrogen on its own can cause the uterine lining to become too thick, which can increase the risk of cancer.

Hormone patches, which deliver hormones through the skin, are not on South Africa’s essential drug list, but they are listed as alternatives if the pills don’t work well for a particular patient or as an alternative when pill stocks are low, which a report by the National Essential Medicines List Committee suggests happens often.

Professor Lineo Matsela, an obstetrician, gynaecologist and president of SAMS, says it’s become common for public sector doctors to write prescriptions for menopausal hormone treatments so that patients can buy them at a private pharmacy.

Over the past three years, however, there have also been sporadic private sector shortages of menopausal hormone therapy treatments.

But access to medicines is only part of the problem, Matina says. Dismissing menopause can also mean the health system could be missing other health risks that can impact women in midlife, a phase that can span about 40% of their lives.

The transition is also associated with bone loss, and the stakes might be slightly higher for women living with HIV. Over five years, a Soweto study found a greater loss of bone-density among women living with HIV compared to those without HIV, though there wasn’t a difference in fractures between the two groups. Researchers didn’t have information on which HIV treatments participants were taking so they couldn’t untangle the effects of HIV itself from the possible impact of tenofovir, which is part of first-line HIV treatment and can contribute to bone loss.

US research suggests there could also be links between HIV, menopause and heart disease and an African study found higher rates of the “bad” kind of cholesterol after menopause regardless of HIV status.

Loss and liberation

People’s experiences of menopause vary widely across countries, cultures and generations.

Women in four rural villages in Limpopo, for instance, described menopause to researchers as a series of losses, of beauty, respect and quality of life even though older people were generally regarded as important veterans who deserve respect regardless of gender.

In some instances, researchers found that elders enforce a culture of silence about menopause. One premenopausal woman explained: “At the girls’ initiation when we were still young, old women told us blood will cease and since then no one ever talked to me about it. That is why I say it is my secret.”

In interviews at two Mamelodi clinics, researchers heard accounts linking pain and weight gain to blood that was no longer flowing out. “I do not know where this blood goes,” one participant said.

In a 2013 discussion of menopause and marriage, theologian Elijah Baloyi described a belief among Tsonga-speaking people that sex after menopause could cause semen to accumulate and a woman’s abdomen to swell.

In Johannesburg’s Soweto township, Matina found many postmenopausal women held beliefs about dirty blood, some saying they withdrew from sexual intimacy entirely or accepted the end of their intimate relationships.

For others, menopause brought liberation from the monthly financial burden of sanitary pads, or elevation to the level of an elder who could commune with ancestors.

Research conducted in South Africa and Zimbabwe suggests that inter-generational support can make all the difference to help women approach the milestone with acceptance.

One woman, who initially worried the changes she was experiencing were signs she could be dying, was calmed by her mother’s reassurance and positive outlook. Another told researchers: “[Menopause] is something I am looking forward to, why, because I am getting old. Yes, if time permits and if God allows it, with life, it’s okay.”

The language of change

It’s language that’s getting in the way, according to the authors of Working with Indigenous Knowledge: A Guide for Health Professionals.

Language mirrors a society’s worldview, and where Western medicine isolated a clinical hormonal deficit, African linguistic traditions instead describe social shifts.

When clinical concepts are translated literally into local languages, they often produce phrases steeped in shame, stigma, or perceived uselessness such as kuguma ura (no longer bearing) in Shona or phelelo maikutlo (the end of one’s feelings) in Setswana.

In response, women may express their bodily changes through idioms and euphemisms, describing hot flushes as fufulelwa or framing the transition socially as ugugile (she has aged), sekhulile (growing older), or into zabogogo (grannies’ stuff).

Because nursing and medical school curricula spend little time on multicultural health communication or the endocrinology of ageing, Matina argues clinic staff frequently misinterpret these cultural expressions or fail to engage with them altogether.

“You know, I don’t know menopause properly… because sometimes people speak in such big English, so you don’t understand it, unless someone explains it to you”, an older woman in Soweto told researchers.

From stigma to selfhood

When researchers set out to learn about midlife health across South Africa and Zimbabwe, they discovered that women want something different from what their public health systems currently offer.

The women described leaving clinics without accessible information and with lingering physical distress or anxiety over health risks.

When asked what would help, participants explicitly requested clear, contextually relevant information so they could understand their bodies and take charge of their own health regardless of their access to more expensive hormone therapies.

The result is a series of question-and-answer booklets co-created with communities, doctors, translators and designers, which reflect the women’s firm rejection of the “old granny” stereotypes.

The participants banned old-fashioned dresses, which they felt aged menopausal women, and insisted on vibrant, modern images of smiling, active women. Also banished were medical jargon and deficit-based translations of “menopause”.

Instead, they opted for culturally relevant terms of dignity and strength such as Ubufazi in isiZulu and Sesadi in Setswana, both of which simply mean “womanhood”.

*This article was first published by Spotlight – health journalism in the public interest. Sign up to the Spotlight newsletter.

Donated mpox Vaccine Stock will be Deployed as Needed, Says Health Dept as Cases Climb to 26

Vaccination for mpox is recommended for people who are at high risk of acquiring the virus and at risk of getting severe disease. (Photo: Unsplash)

By Elri Voigt for Spotlight

Twenty of this year’s 26 confirmed mpox cases came after August, concentrated mostly within the Western Cape. Elri Voigt looks at how the virus has changed and how much of the donated vaccine is left.

The viral illness mpox has caused several clusters of outbreaks across the world. In South Africa, sporadic cases have been detected, but an uptick since August has now brought the illness back into the spotlight.

As of 27 October, 26 mpox cases have been confirmed in South Africa this year, Dr Jacqueline Weyer, Head of the Centre for Emerging Zoonotic and Parasitic Diseases at the National Institute for Communicable Diseases (NICD), told Spotlight.

Of those 26 cases, 18 are in the Western Cape, three are in Gauteng, two are in the Eastern Cape, another two are in the Free State, and one is in KwaZulu-Natal. The majority of cases, 20, have been detected since August this year. All but one of these cases were in men between the ages of 23 and 50 years. One case was in a woman aged 35 to 44.

Seven people have been hospitalised, but no deaths have been reported so far this year.

SA has had a low number of cases overall

Mpox was first identified in humans in 1970, and was mostly observed in central, east and west Africa. The Democratic Republic of the Congo (DRC) was particularly affected, with thousands of cases reported since 2005.

Then in 2022, the virus spread rapidly to multiple countries for the first time. Around 140 countries have reported mpox cases since 2022, according to the World Health Organization’s mpox dashboard, with over 190 000 laboratory-confirmed cases reported and over 536 deaths to date.

The overall number of mpox cases in South Africa has been low. Our back-of-the-envelope calculation puts the total confirmed number of mpox cases since 2022 at 71. The NICD mpox dashboard lists a total of 66 cases and three deaths between 2024 and 2026. In 2023, according to Weyer, there were no reported cases of mpox in the country. There were five cases of mpox identified in 2022, according to information on the NICD’s page on mpox.

Small outbreaks

While the number of mpox cases have been relatively low to date, the current situation can be referred to as an outbreak.

Weyer told Spotlight an “outbreak” doesn’t necessarily mean a “large number” of people are affected. “Outbreaks may be large, small and confined, and for some conditions, a single case may be denoted as an outbreak.” In public health, she added, an outbreak “refers to the occurrence of cases of a disease in a particular place and period that warrants investigation and a public health response”.

When asked if there is a risk for a larger mpox outbreak in the country, Weyer is cautious.

“We cannot rule out the possibility of further cases, particularly while investigations are ongoing and local transmission has occurred previously,” she said.

“The risk of further spread depends on several factors, including how quickly cases are detected, the number and nature of contacts, the extent of transmission within affected networks, and the effectiveness of public health measures.”

Weyer added: “We have the opportunity to intervene early, identify additional cases and reduce the likelihood of further spread.” She said the NICD’s approach is to remain alert without creating unnecessary alarm. “We are continuing to strengthen surveillance, laboratory investigation, contact tracing, vaccination of eligible priority groups and public awareness,” she said.

The deal with vaccine doses

There is a limited number of donated mpox vaccines available in South Africa. Since there are currently no registered vaccines against mpox or other treatment options in the country, any vaccine or treatment used will need to be supplied via a Section 21 request, which allows for medicines that are not registered in South Africa to be brought in.

Vaccines against smallpox – which is caused by a virus closely related to the mpox virus – can offer some protection against the illness. There are three vaccines that can be used against mpox – LC16m8, MVA-BN and ACAM2000. The latter is only registered for limited use in the United States.

Last year, the Africa Centres for Disease control and Prevention (Africa CDC) donated just over 10 000 doses of the vaccine MVA-BN (known by the brand names imvanex and JYNNEOS) to the National Department of Health. These doses were used in vaccination efforts ever since, with a total of 2 365 doses administered between September 2025 and September 2026, health department spokesperson Foster Mohale told Spotlight.

There are currently 3 865 doses still available for use, according to Mohale, which will expire on 31 August 2027. We asked the health department about the remaining 4 000 or so doses but are still awaiting reply.

When asked whether any additional mpox vaccines will be procured or donated, Mohale said: “Yes, the department is currently reviewing procurement options of additional mpox vaccine doses, dependant on the recommendation from [the] Incident Management Team and the National Advisory Group on Immunisation.”

Mohale said vaccine doses are distributed to provinces as required, depending on “disease outbreak and response”.

Vaccination for mpox is recommended for people who are at high risk of acquiring the virus and at risk of getting severe disease. It can also be considered as a form of post-exposure prophylaxis for people who have been in contact with someone who has mpox.

An antiviral medicine called tecovirimat is occasionally used to treat mpox symptoms in severe cases. There is some limited stock of the drug available for use in South Africa, which Mohale said was sourced through the World Health Organization (WHO) and Africa CDC’s Access and Allocation Mechanism.

There are still more than 40 containers of tecovirimat capsules available, Mohale said. But there are not currently any plans to procure more, although he added that this will be dependent on the recommendation from the Incident Management Team and the National Essential Medicines List Committee. He did not say how many treatment courses are in a container.

In a 2025 National Department of Health mpox guideline document, the National Essential Medicines List Committee suggests that tecovirimat should only be used to treat those with severe disease who have been hospitalised.

This is because the drug has not been shown to make any significant difference in most cases of mpox. Earlier this year, results from a phase 3 study published in the New England Journal of Medicine showed that there was “no evidence that tecovirimat therapy shortened the time to clinical resolution, reduced pain, or increased viral clearance among adults with clade II mpox.”

How the outbreaks have changed since 2022

At first, mpox cases in the country were traced back to international travel. Then in 2024 and 2025 we started seeing local transmission.

Most people diagnosed with mpox in 2024 reported no recent international travel history, Weyer said, noting that “the epidemiological assessment indicated that local person-to-person transmission was occurring”.

For the current situation, Weyer said local transmission is “implied”, noting that investigations are still ongoing.

“This has been established by identifying contact links between cases, and identifying the same clade and sub-lineage of the mpox virus associated with the cases to date.”

There were some individuals who were diagnosed with mpox this year who had recently been out of the country. One of the people had recently travelled to Spain, while another had travelled to Belgium. In two other cases international travellers came to South Africa already carrying the virus.

The clades at play

The mpox virus has two clades, clade I and clade II, with several sub-clades. Professor Tulio de Oliveira, Director of the Centre for Epidemic Response and Innovation at Stellenbosch University, explained to Spotlight previously that clades are a classification system based on the genetic similarities between different strains of a virus.

“So, what it means is that when we see a genetic change [in a virus] that’s really visible and that may have impacted it, normally we call it a different clade or genotype or variant,” he said at the time.

For now, the two mpox sub-clades that are driving most cases in people are sub-clade Ib and sub-clade IIb. This year, cases of mpox in South Africa are a mix of the two sub-clades. The mpox dashboard shows that of the 26 cases, 19 were sub-clade Ib, four were sub-clade IIb, and three cases didn’t have sub-clade information available.

In 2022, sub-clade IIb was driving the mpox outbreak, said Weyer. This changed by 2024 when a new strain of the mpox virus spread beyond the DRC. Sub-clade Ib was first identified in the DRC in 2023 and was behind a large outbreak of the illness in the country that year. This sub-clade spread from the DRC through international travel and cases of sub-clade Ib were reported across the globe by 2024.

The first case of mpox where sequencing indicated sub-clade Ib in South Africa was detected in 2025, according to the NICD dashboard. There was a total of 15 mpox cases reported that year, and sequencing information was available in all but one of the cases.

Weyer said that at the moment there is not any evidence to indicate that there are additional mpox clades or sub-clades circulating in the country.

How mpox is diagnosed and managed

Knowing which clade or sub-clade someone with mpox has doesn’t change how their illness is managed. Instead, it helps scientists track outbreaks.

“Understanding the genetic character of the viruses assists us in tracking outbreaks, evolution of the viruses and identifying markers which may affect diagnostic test performance and potentially vaccine efficacy,” Weyer said.

“The central priorities remain early diagnosis, appropriate clinical care, identifying and monitoring contacts, vaccination of eligible target groups, and communicating accurate information without stigmatising affected individuals or communities. The approach is the same regardless of the current genetic character of these viruses,” she added.

Mpox is mainly spread through close contact with someone who has the virus or contact with material like bedding or clothing that has been in contact with someone with mpox.

The illness can cause flu-like symptoms – like a headache, sore throat, fever and muscle aches – as well as a distinct and often painful rash. The rash can occur on someone’s palms or soles of their feet, face, mouth and throat and sometimes the genital areas. It starts as a flat sore, then becomes a blister which can be itchy or painful. As the rash heals, the lesions dry up, crust over and fall off.

The virus has an incubation period of anything from five to 21 days – but usually it is around seven to 14 days.

“Mpox can affect anyone who has close contact with an infected person. We should avoid assumptions about who can acquire the infection and ensure that people feel able to seek healthcare without fear of judgement or discrimination,” said Weyer.

Mpox is normally diagnosed by swabbing the lesions from the rash and sending that for testing with a PCR (polymerase chain reaction) test that looks for the virus’s DNA.

While the overall case fatality for mpox is low, typically below 1%, people who are immunocompromised (such as people living with uncontrolled HIV), pregnant women, and children, have a much higher risk of severe illness, complications and even death.

In most cases, according to the mpox guideline document, symptoms can be managed at home, with rash-related pain being a particular challenge. Severe mpox cases require hospitalisation.

Someone who has mpox is considered contagious until the rash has completely gone away, and the scabs have healed. Thus, people diagnosed with mpox are advised to self-isolate until their rash has gone away completely.

“People who develop an unexplained rash, particularly when accompanied by fever, swollen lymph nodes or a history of possible exposure, should seek medical assessment,” Weyer advised. “They should avoid close physical contact with others while awaiting clinical guidance and testing. The public should understand that mpox is preventable and that early diagnosis and appropriate care are important in reducing transmission and complications.”

*This article was first published by Spotlight – health journalism in the public interest. Sign up to the Spotlight newsletter.
How to Thaw a Health System Frozen in Fear

Photo by Mulyadi on Unsplash

By Joan van Dyk for Spotlight

South Africa’s public healthcare system finds itself caught between two incomplete revolutions – the democratic dream of a decentralised District Health System, and the march toward National Health Insurance. Health systems experts argue that structural changes won’t save a system that is scared stiff. The most urgent task facing the system, they say, is to help frontline doctors and nurses reimagine what is possible.

Part of what makes an octopus such a nimble, wily creature is that there’s more brain outside its head than in it.

In fact, about two-thirds of an octopus brain is spread across its eight tentacles, each one controlled by a tangle of neurons, its own mini-brain.

These semi-autonomous processing centres allow the octopus to control hundreds of individual suckers, which means tentacles can investigate crevices the eyes can’t see, and even learn from each other without much of the big brain’s help.

The suckers can sample the seafloor and decide whether what it finds is safe to eat, at which point a tentacle turns into a temporary elbow to bring the morsel to its beak.

This is the kind of intelligent and adaptable network that was envisioned for South Africa’s District Health System (DHS).

Where apartheid-era planning demanded top-down compliance, among others to enforce racial oppression and dispossession, the DHS, with its 52 districts and 240 sub-districts, promised to empower staff to respond to patients’ everyday realities, whether they live in a city or a rural village.

In reality, much of the system’s financial and administrative power has pooled at provincial head offices, trapping staff on the ground in the old command-and-control way of doing things.

As a result, frontline healthcare workers clock in every day with the task of executing more than 175 new clinical guidelines (that’s just since 2012) while also racing to meet sometimes out-of-touch performance targets. That is according to 2020 research conducted among district managers in the Eastern Cape, Western Cape, KwaZulu-Natal and Limpopo.

What’s more, layers of red tape added to catch corruption have not deterred politically connected syndicates. Research suggests it has only overwhelmed clinical managers and facility heads who are held accountable for patient experiences but can’t replace even the most basic equipment needed for care, such as a scale, without kicking off a months-long procurement effort.

Under these conditions, health workers have said repeatedly that the work of caring for people gives way to constant administrative self-preservation.

One Eastern Cape manager told researchers: “We will comply now and complain later. If you don’t comply, it means you are failing your district, or your sub-district, or your clinic or your people.”

Much like an octopus might become a danger to itself if it only believes its eyes, the health system’s top-down leadership style is damaging to those it employs and ultimately, to those it serves.

Fear and loathing in the platinum belt

It is possible to bring the original DHS dream to life by shaking the systemic fear out of daily operations.

Leading the charge is SALAD, the South African Learning Alliance for the District Health System.

Established in 2023, SALAD connects academic researchers across several South African universities (including UWC, UCT, NWU, and Stellenbosch) with national, provincial, and district health managers, clinicians, and non-profits to help tackle governance problems.

The team recently completed a pilot project in the North West province’s Rustenburg sub-district with more than 50 managers.

“We started at the sub-district level because if you can strengthen it there, you can learn a lot. There’s much less politics than at the top,” explains Beth Engelbrecht, the former Western Cape health department head and an adjunct professor at NWU and UCT.

Their initial analysis revealed staff were dealing with a mix of helpful and harmful experiences. Mistrust was among the more pervasive issues. “Even in regular meetings, it’s a toxic space,” Engelbrecht says. “If you don’t achieve your target, it’s like a ton of bricks coming down on you.”

To address all this, SALAD teamed up with the North West Systems Leadership Development Programme and the provincial health department to co-design a four-pronged plan.

The executive team got support to transform review meetings into learning spaces, managers attended an accredited short course, and everyone received mentoring, and real-time evaluation.

The most important part of the plan was that all the learning and assessment was happening in sub-district’s wards and daily meetings, using the real problems it faces. Workshops ran in short one or to day blocks spaced over four months, which also minimised disruption to clinic operations.

“When people see the effect of adopting different leadership processes in their relationships with colleagues, that builds its own desire to keep working differently,” explains Lucy Gilson, professor of Health Policy and Systems at UCT.

Unfreezing the frontline

The SALAD team also spent a lot of time coaxing staff out of their panic-stricken state and instead focussing on the power they do have using an adapted version of Stephen Covey’s spheres of control, influence, and concern.

They gave staff explicit permission to stop expending energy on systemic issues (such as national budget cuts) they cannot alter, says Professor Helen Schneider, a professor of public health at UWC.

“Acknowledge the system-wide issues, but don’t kill yourself worrying about them,” she explains, “focus on what you can do, and then suddenly people discover a certain kind of agency, and they recognise they do have power.”

For instance, managers and clinicians can directly control in their immediate daily operations, how facility meetings are structured, staff schedules, internal communication tone, queue management, and creating psychological safety within their immediate team.

Outside their own facility, they can build strategic alliances, Schneider says, by navigating local trade union relations or engaging clinic committees, negotiating with sub-district support units, or coordinating across public-private boundaries.

The pilot is complete, and the SALAD team is still in touch with health authorities in the North West to figure out how to scale the programme.

This will take time, Gilson says, because leadership development is not written into provincial annual performance plans. Although it’s a frontline change that’s needed, backing from the top is still crucial.

Engelbrecht and Gilson met with a number of national oversight bodies (including the Department of Planning, Monitoring and Evaluation, the Department of Public Service and Administration, and the National Department of Health) to figure out how leadership was being managed on a national level.

“All three of those national bodies said leadership is critical, but all of them confirmed that leadership development is nowhere in any plan an explicit, funded priority.”

Unlike most other national or provincial departments, the Western Cape has embedded leadership development into its structures, budgets and working practices.

Through the Partnership for Health Leadership and Management Capacity Development (PAHLM), for instance, the Western Cape health department and three universities developed a leadership competency framework and a leadership behaviours charter. The framework was tested and developed through two rounds of workshops involving more than 800 public health-system managers and was commissioned and approved by the provincial health department.

The case of the disappearing paramedic examiners

Years of fear and resentment can crystallise in unexpected ways.

In KwaZulu-Natal, a meticulously planned paramedic examination was nearly derailed when a number of paramedic educators and examiners booked off sick at the same time, Caleb Wang tells those gathered for a SALAD online seminar.

Wang, who coordinates in-service training for clinical employees in KZN, is a paramedic by training. Paramedics are an important link connecting household emergencies, clinics, and district hospitals, though training colleges are often regional or provincial facilities.

These assessments are labour intensive, Wang says, and they require large panels of examiners for clinical skills, oral boards, and simulation exercises. It’s a high-stakes situation for students too, since failing means they can’t progress, get promoted or qualify for salary increases.

The exams continued with fewer examiners for the sake of the students, but the sudden changes created a high-pressure environment for everyone involved.

At first, Wang and his colleagues suspected a stomach bug might be behind the chaos, but upon closer inspection, a stranger reality emerged; the examiners were afraid to attend the assessment, and afraid of saying why.

As it turned out, course coordinators leading the different academic tracks were locked in interpersonal feuds. Educators felt helping to assess a rival coordinator’s exam could be seen as a betrayal. Unsure of how to raise such worries without also facing reprisals, people instead took sick leave in self-defence.

Such a fraught emotional landscape can’t be fixed with rules and reprimands. Though managers started to track sick leave application trends for signs of a coming crisis, the underlying issues could only be remedied using a more collaborative, relational style of leadership.

Wang focussed directly on the relationships between co-ordinators. After they had completed a series of communication exercises, management also instituted regular meetings where structured, open dialogue was encouraged.

Topics previously taboo in administrative settings (feelings, assumptions, perceptions, and hidden dynamics) were reframed as important operational intel.

The formerly warring co-ordinators aren’t personal friends today, Wang says, but the approach succeeded in breaking down the seemingly intractable silos and has restored cooperation across the different academic components.

These days, paramedic examinations go off without a hitch.

Psychologically safe doctors = physically safe patients

People who have the confidence to speak up, admit mistakes, or take calculated clinical risks are much better at saving lives and preventing hospital infections than those who keep their head down out of fear.

Nomlindo Makubalo, a paediatrician in an Eastern Cape district clinical specialist team, has seen this first-hand.

Speaking during a webinar on psychological safety in the DHS, she shares an anonymised story of a junior medical officer and ward nurses at a cash-strapped district hospital who were confronted with a critically ill, ventilated 11-month-old infant.

The baby urgently needed intensive care but there were no available ICU beds in the regional or central referral complexes. The rural ward nurses had no formal ICU ventilation training.

In a traditional, fear-based culture, the local team might have panicked and passed responsibility upward or allowed the infant to deteriorate while waiting for official transport sign-off.

But Makubalo and the district clinical specialist team had intentionally built a relationship of psychological safety, so the junior doctor felt safe to call her directly.

She reassured the team and provided real-time, telephonic clinical supervision for two consecutive nights.

The hospital management authorised additional nursing support to relieve ward strain. Supported by this protective leadership umbrella, the frontline team safely ventilated the infant locally for 48 hours until an ICU bed opened.

The baby was transferred and made a complete recovery.

Makubalo says: “Psychological safety and trust translate directly into quality care. When people know you have their back, they will do everything to save a life.”

The physics of success versus failure

In the Western Cape, the provincial government explicitly measures the energy all civil servants expend that never reaches the public.

In a healthcare setting, patients might lose out because health workers’ energy is spent navigating internal friction, administrative hierarchies and coping with interpersonal conflict.

The technical term used across the province is “organisational entropy”. Very loosely related to the scientific concept of entropy, it measures the percentage of total energy within an institution consumed by unproductive work.

In the proprietary tool used by the Western Cape government, called The Barrett Model®, wasted energy is measured using a survey. It offers a list of personal and organisational values and asks staff to choose 10 personal values, 10 values that describe the current culture of the organisation, and 10 organisational values they’d like to see in the future.

The cultural entropy score comes from the percentage of current organisational values staff pick that the Barrett Model classifies as “limiting,” such as conflict, friction, and frustration.

At the Retreat Community Health Centre, a facility that provides 24-hour emergency and maternity care in Cape Town, researchers found staff operated in a pervasive climate of fear. Their baseline survey suggested that staff viewed management as administrative police designed to catch staff making mistakes, and as a result, communication broke down into departmental silos.

To break this cycle, the facility embarked on an 18-month participatory action research initiative.

The three key facility leaders, the facility manager, family physician, and nursing manager underwent leadership assessments and six months of individual coaching. They engaged in weekly reflective learning sets, mapping out communication flows, and examining how their own management behaviours generated fear.

The results were transformative.

When researchers followed up 18 months later, limiting values had dropped out of the top 10 current organisational values, although they still represented 13% of all values selected (down from 33%). In their place emerged positive, unifying values: caring, open communication, teamwork, respect, fairness, and accountability.

This phenomenon is not confined to isolated research sites. The Western Cape Department of Health and Wellness formally tracked cultural entropy across its entire workforce as an official performance metric, achieving a department-wide entropy reduction from 23% to 20.9% between 2013 and 2016.

This systematic drop in friction directly correlated with improved employee retention, stronger teamwork, and smoother service delivery across health districts.

The latest annual report puts cultural entropy cross the provincial public health system at 16%.

The province also tracks leadership skills on an individual, team, and system level.

Tendani Mabuda, who leads the provincial health department’s People’s Development team, argues the proof of the value of strong leadership can be found in the department’s eight year run of consecutive unqualified audits.

“Leadership development cannot alone resolve structural failures or challenges, but it enables managers to be agile and cope with the environment they are facing,” he says.

‘Trust is not a luxury’

For three decades, the unwritten rule within South Africa’s public sector clinics and hospitals has been to hide errors, follow flawed directives to the letter, and brace for new instructions from headquarters.

Stamping out this culture of fear in favour of psychological safety will be crucial to the success of South Africa’s next big healthcare revolution, the National Health Insurance (NHI)  scheme.

The scheme, which currently faces about a dozen legal challenges, will change the way resources and healthcare services are pooled and purchased.

At the moment, most provincial health funding comes from nationally raised revenue transferred by National Treasury to provincial governments. The amount each province gets is determined by the provincial equitable share equation. The formula determines each province’s share using factors such as population, poverty and demand for health and education services. Provincial governments then decide how much of their budgets to allocate to their health departments. Separately, the national health department administers conditional grants for specified health services and programmes.

Under the proposed new system, funding would shift from this passive approach, where facilities receive budgets shaped by previous allocations to cover costs such as salaries and supplies, to strategic purchasing.

This means actively deciding which services a population needs, which providers should deliver them and how to pay those providers, with funding decisions guided by health needs and provider performance rather than simply historical spending.

For primary healthcare, contracting units would organise networks of public clinics, district hospitals and participating private providers to serve people within a sub-district, with the NHI Fund purchasing services through these arrangements.

These are hardware updates but, as multiple governance studies have shown, a hardware solution won’t fix a software problem.

And strategic purchasing will require sophisticated cultural software and strong leadership from district and sub-district managers with the ability to build trust, negotiate, manage networks that combine public primary care clinics, district hospitals, private doctors, nonprofits, and municipal health services.

At the heart of all of this, is trust between people, explained health economics professor Susan Cleary during a June webinar.

“You don’t get good quality results if you don’t have good quality relationships, they’re part of performance, and trust is not a luxury.”

Incidentally, an octopus can overcome incredible barriers once it decides to seek safety.

In 2016, staff at the Napier Aquarium in New Zealand arrived at work to find that Inky, one of its star inhabitants, had escaped. Finding the glass lid of his tank left slightly ajar after routine maintenance, he slipped out overnight, navigated a 50-metre drainpipe, and disappeared into the sea.

*This article was first published by Spotlight – health journalism in the public interest. Sign up to the Spotlight newsletter.
How Nurses are Learning to Administer the New HIV Prevention Injection

By Christina Pitt for Spotlight

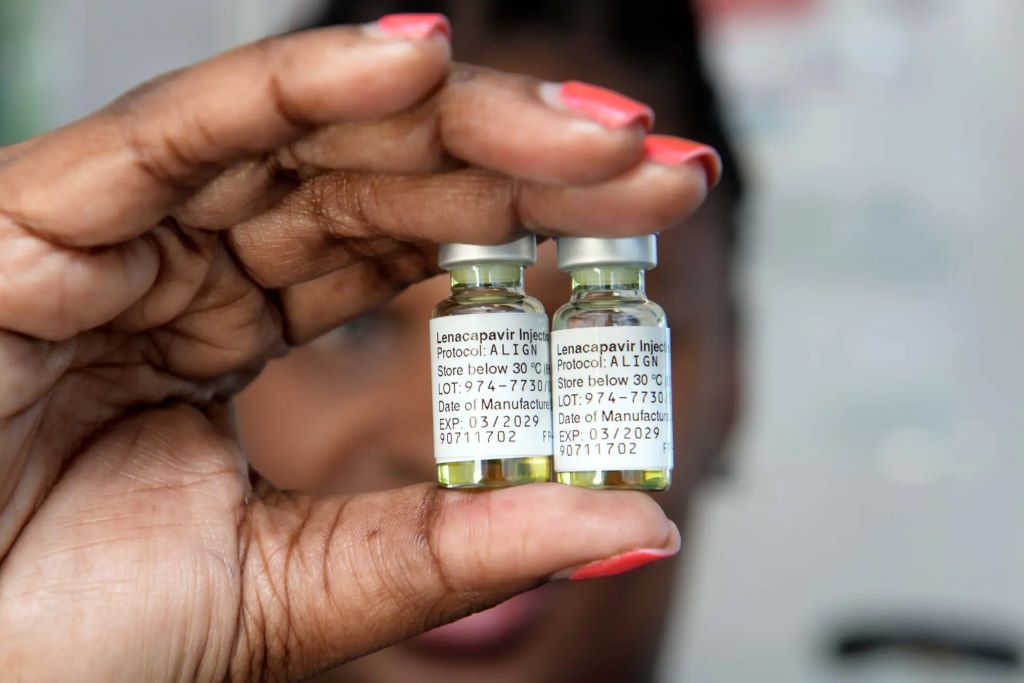
Lenacapavir is administered via two injections of 1.5ml each in the buttocks, thigh, abdomen or upper arm. (Photo: Nasief Manie/Spotlight)

South Africa’s rollout of lenacapavir, a six-monthly HIV prevention injection, requires nurses to learn, adapt and find ways to make it work for patients.

After 26 years in nursing, Sister Keitumetse “Tumi” Senokwane still had something new to learn about giving injections.

The six-monthly HIV-prevention jab, lenacapavir, often referred to as just LEN, presented a unique challenge.

“You know, lenacapavir is different. As much as I’ve got experience with injections, the needle size is different from the subcutaneous (beneath the skin) injections we are used to, and the solution is quite thick,” says Senokwane. “Because we were not used to it, the practical training helped us to get used to it.” She practised withdrawing the yellow liquid, using cooking oil as a stand-in.

That kind of preparation matters because lenacapavir for HIV prevention is being introduced at a time when South Africa still has a substantial need for effective HIV prevention options. The country had an estimated 140 000 new HIV infections in 2025. Modelling suggests that scaling up lenacapavir to 1.4 million to 2.1 million initiations a year by 2030 could avert an average of 32 200 to 51 700 infections annually.

But realising lenacapavir’s potential will depend on more than getting the injection into clinics. It also requires nurses to administer it correctly, answer patients’ questions, and adapt services to their needs.

Getting to grips with lenacapavir

Senokwane is a professional nurse and site manager at Maria Rantho Community Health Centre and Phedisong 1 Clinic in Tshwane, which are participating in the Wits RHI Len4PrEP study.

“LEN4PrEP is an implementation research study, so looking at how we can deliver the product in a real-world setting,” says study investigator Dr Catherine Martin.

The researchers recruited 1 544 participants between November 2025 and June 2026, with follow-up continuing until June 2027. The study began several months before South Africa’s national rollout of lenacapavir on 5 June 2026, when the injection was launched at 360 public health facilities across six provinces.

By 8 October, 76 922 people had initiated LEN nationally, including 36 733 in 133 facilities in Gauteng, according to health department spokesperson Foster Mohale.

For Senokwane and her colleagues, administering lenacapavir meant learning a new HIV prevention method.

Nurses first had to complete a compulsory Nurse-Initiated Management of Antiretroviral Therapy (NIMART) course, which provides a theoretical foundation for managing HIV and antiretroviral treatment. This was followed by practical training in preparing and administering LEN.

Training also covered eligibility, side effects, HIV testing and counselling, with videos and clinical mentorship providing additional support.

Mohale says feedback from early-rollout clinics, nurses and patients would help the department refine its training and guidelines.

At the study clinics, nurses also had to adapt the service to patients’ needs and fit the new injection method into existing care.

The one-stop shop

The Department of Health’s lenacapavir implementation guidelines emphasise counselling clients on their HIV prevention options and helping them choose a method that suits their needs.

At the study clinics, nurses incorporated LEN into existing sexual and reproductive health services, allowing clients to access HIV prevention alongside services such as family planning and STI screening and treatment during a single visit.

“You will get all services in one room like a one-stop shop,” says Senokwane.

“Maybe you are here for lenacapavir, but we also check whether you are on a family planning method. If not, we will give you information and provide a family planning method for you, where we screen you for STIs, and then if you’ve got some infections, we also treat you,” she says.

The LEN4PrEP study also used a mobile clinic to bring HIV prevention and sexual and reproductive health services to young people in their communities.

“So many of our clients already know us. They know how we treat them and the quality of service we provide,” she says.

Initial LEN consultations took longer as nurses explained the available prevention methods and how soon each would offer protection against HIV.

“We give you the information and explain how each method works, how long until it is effective. Participants would like to know when they are going to be protected from HIV if they take this specific method,” says Senokwane.

At the Southern African HIV Clinicians Society’s Long-Acting Antiretroviral Treatment Conference in Johannesburg in September, Wits RHI’s Professor Saiqa Mullick, Director of Implementation Science, shared early findings from the LEN4PrEP study.

She reported that convenience was a major reason participants opted for the lenacapavir jab. They valued not having to take a daily pill or make frequent clinic visits, while the injection offered greater privacy for some. It also attracted people new to PrEP, alongside existing users seeking a method that better suited their lives.

Pre-exposure prophylaxis, or PrEP, refers to antiretroviral medicines taken to prevent HIV infection. When used as prescribed, oral PrEP has been shown to reduce the risk of HIV infection from sex. For several years now, HIV prevention tablets have been widely available in South Africa’s public healthcare system, although uptake has been somewhat muted with only around 350 000 people taking the tablets in mid-2025, according to estimates from Thembisa, the leading mathematical model of HIV in South Africa.

Of the 1 538 participants whose method choices were reported, 85.8% selected the lenacapavir shot, compared with 13.7% who selected the prevention pills and 0.5% who chose not to use PrEP.

“People want options that fit into their lives,” Mullick told delegates.

Sticking the landing

Patients could also choose where in the body to receive the injections: the upper arm, buttocks, abdomen or thigh.

Among the 1 319 participants who started LEN, Mullick says approximately 50% of women preferred the buttocks, while about 51% of men preferred the upper arm. The ongoing study will explore both men and women’s reasons for injection-site preferences.

For nurses, the challenge was to administer the injections correctly while making the process as efficient as possible.

Lenacapavir requires getting two injections during the same visit. Patients also need to take two lenacapavir tablets on the day of their first injections, followed by another two tablets 24 hours later. These tablets form part of the initiation dose before they continue with injections every six months.

Senokwane says a Wits RHI pharmacist taught her a way to withdraw the solution while keeping the vial upright, rather than turning it upside down.

“That was the best method for me because it worked faster,” says Senokwane.

“So with that method, you pull up 1.5 ml of air into the syringe and inject the needle into the vial. [The syringe] draws at least one ml by itself, without assistance, which allows the nurse to multitask. And then you also save time because you are able to prepare two injections at the same time,” she says.

But efficiency was only part of the learning curve. Because lenacapavir is a thick solution, it needs to be injected slowly.

“I wish I knew that you can’t inject it fast,” Senokwane said. The thick solution required a slower injection technique to reduce leakage.

Slow administration was included in nurses’ initial training, but its importance in minimising leakage was reinforced as they gained practical experience and shared lessons with colleagues.

Dr Martin says that in the early stages of implementation, nurses consulted experts, including those involved in clinical trials, on how to manage leakage at the injection site.

“As local experience grew, they learnt to reassure participants that minor leakage could occur and to assess more substantial leakage to determine whether further follow-up was needed.”

Answering patient concerns

Patients were also concerned about the side effects of lenacapavir.

Lumps or small nodules at the injection site are a common side effect of lenacapavir. In one clinical trial, which included 2 140 participants who received lenacapavir, roughly 64% developed subcutaneous nodules at the injection site.

“Most of the clients were curious about the nodules. They were worried about whether they would be able to continue with their normal activities, especially those who wanted to exercise,” says Senokwane.

“They wanted to know how long the nodule would last and whether they would get another one when they came back for their second injection. Usually, by the time they came for their next injection, the nodule would have disappeared.”

Others were worried about the pain.

“We advise them that if the nodule comes with pain, just use a warm or cold compress, or you can even use a painkiller,” explains Senokwane.

Mullick says addressing these concerns and discussing them with clients in advance is part of making the injection work for patients in practice.

“This might seem something relatively small, but from an implementation perspective, it contributes considerably to the person receiving the product.”

Making it work in real time

As nurses became more familiar with administering lenacapavir, the clinics also refined how they moved patients through the service, from the initial consultation to receiving the injection.

Patients first met a navigator who explained the available services. After registration, an HIV test and a check of their vital signs, they saw the research nurse.

The clinics later began using the waiting time more effectively, with navigators introducing patients to PrEP and other services before their consultations.

Initially, appointments could take about an hour and a half. As the clinics refined their workflow and nurses became more familiar with the process, Senokwane says visits took about an hour or less.

“Training manuals and guidelines provide all the theoretical knowledge and framework for delivering lenacapavir,” Martin explains.

“But, that real-world experience gives you a little bit more insight into things that you can only learn by working with clients.”

Each one teach one

Senokwane’s experience eventually helped her become a mentor to other nurses.

“The mentorship was really very important. We’ve got support from our pharmacist, and then we’ve got support from our sub-investigator at site. So everyone needs to be mentored until you are really 100% sure that you can do it on your own,” she says.

When non-research nurses started providing lenacapavir in June at the study sites, she went there to demonstrate the technique. Some nurses she had trained also helped their colleagues.

“They were always grateful that we really helped them. So they really appreciated it. The more you practice, the better you become,” says Senokwane.

Lessons from the clinics also informed training. Videos demonstrating how to prepare and administer lenacapavir were produced by Wits RHI, alongside webinars. Martin says the videos would be incorporated into future training.

“It’s always helpful to see something in practice. With a new product, although it can be explained theoretically, it is helpful to actually see a provider and a client interaction,” she says.

*This article was first published by Spotlight – health journalism in the public interest. Sign up to the Spotlight newsletter.
“We are Willing to Work but the Posts are Not There”, Say Young Doctors

Doctors and supporters of unemployed medical professionals protest outside the Natalia Building in Pietermaritzburg, calling for action on doctor unemployment. (Photo: Supplied)

By Sue Segar for Spotlight

They are qualified, ready, and willing to serve their communities. But scores of these doctors in KwaZulu-Natal, are becoming increasingly desperate because of a lack of posts in government hospitals and clinics.

Dr Tholumusa Sibiya remembers, as if it were yesterday, the day, in 2015, when a group of young doctors visited his school in Ingwavuma, KwaZulu-Natal to urge talented pupils to apply to university to study medicine and other health disciplines.

The doctors were from Mosvold Hospital where manager, Dr Andrew Ross, had started a fund to encourage local pupils to train in medicine and return to serve in their communities.

“The message from these young professionals was, ‘yeah, it’s doable. You can also study medicine. And you’re needed.’ That really inspired me,” says Sibiya, who was the top pupil in matric at Nansindlela Combined School.

He knew about Mosvold Hospital because his father worked in the mortuary, and his mother in the laundry services there. But, till then, it hadn’t occurred to him he could be a doctor there some day.

“One of the doctors said something that knocked sense into me. He said as rural kids, we need to work twice as hard to have half of what guys in other schools have,” he recalls.

Sibiya and other pupils from the area then formed a study group, to “share information and support each other”. “It helped a lot working together … especially with mathematics and physics,” he says.

Against the odds

Sibiya’s hard work paid off, and armed with an Umthombo bursary, he was accepted at the University of KwaZulu-Natal to study dental therapy. A year later, he transferred to the university’s medical school, and qualified as a doctor in 2022.

“My parents were ecstatic,” he says.

Straight after qualifying, he did two years of internship at Empangeni’s Ngwelezana Hospital, followed by community service at Manguzi Hospital in northern KwaZulu-Natal. “I rotated from one department to the next – paediatrics, maternity, the emergency unit – and learnt so much. It was the best,” he says.

He was geared up and ready to return home to serve his rural community as a doctor. His long-term dream was to work as an emergency physician in a hospital in rural KZN; maybe to specialise as an anaesthesiologist. But to specialise, you need to work in a public facility.

That was 2025. Since then, Sibiya has not been able to find a job as a doctor in the public healthcare sector. “I started applying in October last year,” he says. “But, so far, nothing.”

Many unemployed doctors

Sibiya is not alone. Spotlight has spoken to several other young doctors who are in the same boat. He reckons there are well over a hundred recently qualified doctors looking for work just in KwaZulu-Natal, others put the number at closer to 200. Even this may be an undercount since it doesn’t fully account for doctors who are still unemployed from previous years, or who have stopped looking for work. Some recent reporting suggests that the National Department of Health does not have a reliable count of how many unemployed doctors there are who are looking for work in the country.

Those who have received government bursaries, cannot fathom “why the government invests in us, then dumps us”. “Even now, they’re sending a new batch to study overseas, but where will they work?” says one doctor, who suggests that Cuban-trained doctors are prioritised for jobs because the government allegedly has a contractual obligation to give them jobs.

Currently, Sibiya and others have few alternatives but to try and do locums in private practises or in private hospitals.

“We’ve worked hard, done all that’s necessary to qualify and completed our internships and community service in preparation for careers in service to others, but we cannot find jobs,” says Sibiya.

Scrambling to make ends meet

We are meeting Sibiya on a Sunday at a coffee shop in Pietermaritzburg. He is currently living in Margate on the KwaZulu-Natal south coast and has come to Pietermaritzburg to do a locum shift for a private GP.

“I do shifts wherever I can find them. Primarily, I’m working in the emergency unit at the Shelly Beach (private) Hospital on the south coast. They call me whenever they need me, but I have no contract. That’s how I’ve been paying bills,” he says.

He keeps up with scores of other unemployed doctors on three different WhatsApp groups where, among others, they share job and locum opportunities, advise and support each other, and coordinate some of their interactions with the provincial health department.

“There are many people on the group(s) who aren’t able to get locum posts,” he says, “and they are really struggling. Some have depression. Sometimes it boils down to cars being repossessed, people going back home. Some people say, ‘I can’t put bread on the table, I’m selling my stuff because I can’t make ends meet’.”

“The mother of a friend of mine, also an unemployed doctor, called me recently and told me he’s drinking every day because the stress has been too much,” says Sibiya. “Some of the stories will make you cry.”

The situation is particularly tough on young doctors from poor backgrounds who do not have the funds to sustain themselves without work for extended periods.

‘I can feel I’m going into a depression’

Dr Raeesa Kathrada says she has sent her CV “to every doctor I know and to every private hospital and applied for every locum position.

“I can feel I’m going into a depression … as are my colleagues. Many people reach out to me, saying they don’t know how to survive,” she says.

Kathrada says some doctors have been waiting up to three years to find jobs.

Dr Lawrence Khoza from Osizweni, near Newcastle, is also struggling to find a position in the public sector. He started a private general practice, but he says he wants to work for the government and to see patients for free. “My passion is to help poor patients … but now I can only help those in the middle class who can afford medical aid,” he says.

Dr Nazo Nxumalo, originally from Mtubatuba, qualified in medicine at UKZN in 2022, did a two-year internship at Empangeni’s Ngwelezane Hospital and her community service at the Nseleni Community Health Centre in 2025. “After that, it was unemployment,” says Nxumalo. “It was like being dropped in the middle of the ocean.”

“I really thought that, after my community service, employment in the public health system would follow,” she says. “Basically, the department has left us stranded. We went into medicine, a very important job in society, believing we were entering a profession where our skills would always be needed.”

Understaffing in public health facilities

The unemployed doctors say that, while they are struggling to find work, the province at the same time desperately needs more doctors if it is to improve the quality and availability of healthcare services. “There is a big shortage; doctors are suffering in silence. The demand is there but the government is turning a blind eye,” says Khoza.

Several doctors who are currently employed at public sector hospitals in the province agree that they need help. One doctor, from a rural hospital speaks about “long lines of patients, late into the day” and doctors often working overtime and never taking a lunch break because “we can’t afford the 15 or 30 minutes of having no doctor on duty”. We are not naming the employed doctors quoted in this story since they could potentially suffer repercussions for speaking out.

“Whenever people leave our hospital, the posts are not filled because of budget cuts,” says another employed doctor. “Several departments here are severely short staffed.”

A recent report from South Africa’s Health Ombud paints a similarly grim picture. Following an investigation into the deaths of six healthcare workers at six public health establishments in KwaZulu-Natal, the Ombud found that while their deaths were not a result of workplace bullying, victimisation, or adverse working conditions in the hospitals under investigation, there were “significant” systemic challenges affecting healthcare professionals in the health establishments. These included “persistent staffing shortages, frozen vacant posts, rising workloads, shortages of medical equipment and supplies, inadequate employee wellness support services, infrastructure challenges, and security concerns affecting healthcare workers”.

A rough benchmark is that 1 doctor is needed for every 1 000 people, although experts stress that target ratios may differ based on factors like disease profile and population density. According to a 2025 parliamentary answer, the ratio in KwaZulu-Natal stood at around 0.38 doctors per 1 000 people – according to the District Health Barometer it was at just under 0.4 in 2024.

Though the KwaZulu-Natal Department of Health does not describe the situation as a crisis anywhere we could find, they do acknowledge shortages. Their 2025-2026 annual report largely blames a budget crunch. “The ongoing budget cuts due to implementation of austerity measures have had a significant impact on the ability of the department to fill vacant critical posts especially among clinical specialists (nurses and doctors), allied health professionals including in finance and human resource administrative posts,” the report reads.

Protests in Pietermaritzburg

On 17 June this year, a large group of unemployed doctors protested outside Natalia, which houses the KZN Department of Health and the Office of the Premier, to call on the provincial government to act urgently to create jobs for the numerous unemployed medical professionals.

With many wearing scrubs and holding placards, the doctors voiced their willingness to serve their communities. They highlighted the shortage of qualified doctors, the systemic strain in provincial hospitals and clinics, and a poor doctor-to-patient ratio in the province.

The protesters also pointed out that some doctors have been waiting for years for jobs; and that their ambitions to specialise in various medical areas were being severely hindered because of the lack of government posts.

They submitted a memorandum addressed to KZN Premier, Thami Ntuli, Health MEC Nomagugu Simelane, and head of the health department, Penny Msimango. Among others, the protestors demanded that the provincial health department advertise all the vacant medical officer positions at various public healthcare institutions within 14 days and that it develops a sustainable long-term plan to provide posts annually and address doctor unemployment beyond 2026.

Not enough money

In a written response to the protestors, the department said: “A filling of vacant posts is dependent on the availability of funds to compensate employees. The department is underfunded for 2026/7 financial year, therefore not all vacant posts can be filled.” They said that, due to the budgetary constraints, they could not commit to timelines for filling posts.

Spotlight sent the KwaZulu-Natal Department of Health a detailed set of questions (which you can read here) on the afternoon of Thursday15 October. We gave them a deadline of end of business on Tuesday 20 October. While the department acknowledged that they received our questions, they did not provide responses by the deadline.

On July 6, Simelane met with representatives of the unemployed doctors and representatives from the South African Medical Association Trade Union (SAMATU) (the unemployed doctors say that SAMATU had to be present since the department does not recognise the group of unemployed doctors).

According to Sibiya, the meeting did not go well. “Their clear message was that the department has enforced austerity measures and they do not have money to fund posts. They committed to try and look for 20 posts but that was all they could promise,” he says. In his view, 20 is not nearly enough. The department later upped the number of newly released posts to 50. The unemployed doctors say that while these jobs have been advertised, there have been no further movement.

But what stung Sibiya more was the sense he got that the department had accepted the situation and given up. “What was really astonishing was that they said they are comfortable with the numbers of doctors in the province on paper,” he says. Spotlight asked the department whether this characterisation is accurate, but did not receive an answer.

“Our response is that …. if something’s declared a crisis, finances are moved to meet that crisis, be it at provincial or national level,” Sibiya says. “I’m sure the public feels the same way: the doctors on the ground by no means meet the demand. They could hire all the unemployed doctors in the province, and still the demand wouldn’t be met.”

“We are not trying to fight”

As the 2026 convenor of the KZN Unemployed Doctors group, Sibiya has been in the middle of much of these developments. The group was formed a few years back with the goal of communicating with the provincial health department to raise doctors’ concerns about unemployment. It was only after several other efforts at engaging the department had not gone anywhere that they decided to protest.

In the meeting, he says they stressed “that we’re not here to fight”. “We understand the department has financial constraints. But we’re talking about the health of the entire province resting on a few shoulders who are really tired; and people ready to work cannot be integrated into the system because of austerity measures”, he says.

“I think we must all agree it’s a crisis. Once we do this, I’m certain funds can be mobilised from somewhere,” he says. “Alternatively, we could expand the system of employing sessional medical officers, where doctors work for a certain number of hours in clinics and hospitals, and earn less.”

But, says Sibiya, “it’s almost as though they’ve given up”.

That sense that those in power are not hearing them was recently reinforced when premier Ntuli reportedly called on doctors who have left the province to return home and help strengthen the health system. More than one unemployed doctor told Spotlight that they were enraged by the comments in the context of their struggle to get jobs. “It’s ridiculous,” says Sibiya. “After all our efforts to speak to the government, and being ignored, now this.”

“Just go private!”

Meanwhile, Sibiya and scores of other young, unemployed doctors are still having to scramble to make ends meet.

Sibiya says people often say to unemployed doctors that they should go private. “Yes, that’s an option, but from the point of view of specialising, it destroys the pipeline. And if all of us go private, then in upcoming years, we will be talking about a shortage. And, in a time of NHI, why are doctors having to work in private”, he asks.

“It’s worse for us coming from Ingwavuma, funded by Umthombo, where when we signed the contract, we were told, ‘You’re going to come back and serve your community’. I was happy to do that,” he says. Umthombo is a scheme that supports young people from rural KwaZulu-Natal to study medicine and then to return to serve their communities once qualified.

Despite all the setbacks, the dream of serving his community remains alive for Sibiya. His eyes light up when he talks of his dream to work rurally, preferably at the hospital he loves, Manguzi.

But, right now, that dream seems far away. He says his main focus at the moment is just to survive.

*This article was first published by Spotlight – health journalism in the public interest. Sign up to the Spotlight newsletter.

Getting TB Care in the Private Sector is a Complicated Journey

Depiction of tuberculosis bacteria. Credit: CDC

By Elri Voigt for Spotlight

Tuberculosis is mainly diagnosed and treated in the public healthcare system, but the private sector should also be able to deal with it.

Tuberculosis (TB) remains one of the leading causes of death in the country, claiming around 50 000 lives a year. Caused by a tenacious bug called Mycobacterium tuberculosis, it has plagued mankind for centuries.

In response, South Africa’s public healthcare system has devoted a lot of resources to TB and many public sector doctors, nurses, pharmacists, and community healthcare workers have years of experience with the illness. The country was ahead of the rest of the world in rolling out new molecular TB tests in the early 2010s. In the last decade South Africa introduced new treatments for drug-resistant forms of TB, before most other countries did so. Much important TB research has also been conducted at clinical sites in the country, like the recent BEAT-TB study published in the New England Journal of Medicine.

But what about the private healthcare sector? Indications are that it has not become similarly expert at combatting the age-old bug, even though people who use mainly private sector healthcare services also get TB. Spotlight recently reported on a PhD student who became ill with TB and was diagnosed in the private sector but received treatment in the public sector. That was not an isolated case. Up to 29% of TB patients across 13 high TB burden countries, which included South Africa, engaged with the private healthcare system when their symptoms first started, according to a 2017 study. In South Africa’s first TB prevalence survey, of the 1 726 participants surveyed who had TB symptoms and sought out care, 139 (8.1%) first sought care in the private sector.

However, finding information on TB care in the private sector has proven to be a challenge, and what Spotlight was able to find is at times contradictory and confusing.

Most cases of TB could be treated in the private sector

Let’s start with the basics. Does the private sector diagnose and treat TB at all?

Here a distinction between types of TB is important. Well over 90% of people who develop TB in South Africa have “normal” drug-susceptible TB, that is to say TB that can be successfully treated with the standard set of antibiotics. A much smaller group, fewer than one in 10, have drug-resistant forms of TB. Drug-susceptible TB can be treated in the private sector, while drug-resistant TB appears to be exclusively treated in the public sector.

“[T]here is a common misconception that tuberculosis (TB) can only be treated in the public healthcare sector,” Dr Noluthando Nematswerani, Chief Clinical Officer at Discovery Health, tells Spotlight. She says that there are many healthcare providers that can diagnose and treat TB in the private sector, since TB is part of the standard training medical doctors receive in South Africa. “Discovery Health does not maintain a dedicated network of healthcare professionals who exclusively treat TB, as TB care falls within the scope of practice of suitably trained medical practitioners across multiple disciplines,” she says.

Treating TB is covered under the prescribed minimum benefits – a list of benefits medical aid schemes is required by law to provide to their members, regardless of what plan they are on. According to the Council for Medical Aid Schemes, TB treatment can be made available to members of medical aid schemes through public sector clinics, but they should be given the option of getting their treatment through the private sector.

Medical aid schemes are prohibited by the Medical Schemes Act from saying that “they do not cover the costs of diagnosing, treating and/or the care of TB and that you can only get this cover in the public sector”. A member of a medical aid scheme may only be referred to a public sector facility if that scheme has a designated service providers arrangement with that facility. And a medical aid scheme cannot refuse to cover TB treatment.

“In line with these regulations, members across all Discovery Health Medical Scheme plans have access to comprehensive evidence-based TB care which includes consultations with the relevant healthcare professionals, the necessary diagnostic and follow-up laboratory and radiology investigations, and clinically appropriate medications for the effective management and care of TB,” says Nematswerani.

However, while the option is there for doctors in the private healthcare sector to diagnose and treat drug-susceptible TB, the majority of TB cases in the country are tested for and treated in the public healthcare sector, says Dr Francesca Conradie, a leading TB researcher. At the moment, drug susceptible TB in adults is treated with a six-month treatment course – consisting of four drugs for two months and then two drugs for the remaining four months.

Drug-resistant TB is likely only treated in the public sector

The picture for drug-resistant TB looks quite different. Conradie points out that some of the medications used to treat drug-resistant TB are only available in the public sector. This means patients with drug-resistant TB need to be referred to a public sector facility to get treatment.

While there does not appear to be any outright legal or regulatory prohibition on private sector pharmacies supplying these drugs (in fact, they have listed single exit prices), by all appearances these medicines are not available in the private sector.

The Council for Medical Aid Schemes does not plainly say that drug-resistant TB (sometimes subdivided into MDR-TB, pre-XDR-TB, or XDR-TB) cannot be treated in the private sector at all. It does however state: “Complex cases such as MDR-TB are often referred to specialised public TB hospitals or clinics, as the required drugs and monitoring may be unavailable or too expensive in private settings”.

“Discovery Health Medical Scheme members have cover for MDR-TB, including consultations, diagnostics and hospitalisations. However, there are limits in access to certain MDR-TB medicines in the private sector as they are only available in the public health sector. These medications would be funded as per the Scheme’s policy if they were made available in the private sector,” says Nematswerani.

How this works for Discovery members, Nematswerani explains, is those who have been diagnosed with drug-resistant TB will be referred by their private sector doctor to a designated public healthcare facility that offers the treatment under the National Department of Health’s MDR-TB programme.

“When designated facilities submit claims for MDR-TB services, Discovery Health assesses and Discovery Health Medical Scheme funds eligible claims in line with applicable Prescribed Minimum Benefit (PMB) requirements,” she says. “For example, members have received MDR-TB treatment at Nkqubela TB Hospital, a specialised facility near East London. All eligible claims submitted by the facility since 2025 have been funded in full by Discovery Health Medical Scheme under PMB requirements.”

Drug-resistant forms of TB are treated with anything from three to seven drugs and treatment can last anything from six to 24 months. Two of the drugs bedaquiline and pretomanid, which form the backbone of the drug-resistant treatment regimen, are monitored closely and can only be accessed through the National Department of Health in public sector facilities. This is according to Professor Keertan Dheda, Head of Pulmonology at Groote Schuur Hospital and the University of Cape Town. The reason for this, Dheda says is to “ensure antibiotic stewardship and so that we do not get acceleration of antimicrobial resistance to specific drugs through inappropriate prescription of such drugs used for DR-TB”.

“It’s because they [the drugs in the current DR-TB regimen] are pearls of great price,” explains Conradie, adding the restriction is to try and safeguard some of the drugs in the current drug-resistant TB regimen, particularly bedaquiline, against the development of resistance for as long as possible. Another reason is that drug-resistant TB patients need to be monitored quite closely for potential side effects, something Conradie says the public sector is well-equipped for.

Finding confirmation on the degree to which the private sector can or cannot access bedaquiline and pretomanid directly has proven challenging. When Spotlight asked about this, spokesperson for the National Department of Health Foster Mohale indicated that the department does not have information on these issues and that our questions could be better handled or addressed by the pharmaceutical industry and the private sector.

Spotlight contacted all the pharmaceutical companies that were listed on the South African Health Regulatory Authority’s website as having registered the DR-TB drugs bedaquiline, pretomanid, and delamanid.

“Viatris in South Africa is the Marketing Authorisation Holder (MAH) for pretomanid and delamanid, both registered for drug-resistant TB, available to the public sector through the national tender and to the private sector upon request,” says a spokesperson for the pharmaceutical company Viatris. “Drug-resistant TB treatment is predominantly coordinated through the public health system, where patient follow-up, pharmacovigilance and reporting mechanisms are established.”

Bedaquiline, from the pharmaceutical company Johnson & Johnson, is available in South Africa, including through the country’s private healthcare sector, a spokesperson for the company told Spotlight.

Two other companies responded that they are not directly involved in supplying the drugs and were only involved in the registration process.

Private sector prices for bedaquiline and pretomanid are listed in South Africa’s single Exit Price database, something that usually indicates at least some intent from the manufacturers to supply it to the private sector. UKZN pharmaceutical sciences expert, Dr Andy Gray, tells Spotlight that there is no legal reason for not making these medicines available in the private sector, but access is often constrained. “That the manufacturers have taken the trouble to submit a launch Single Exit Price to the National Department of Health Pharmaceutical Economic Evaluations unit is important, and indicates a willingness to supply a private market, even if availability is limited because demand is almost non-existent,” he adds.

Gaps in knowledge of TB in the private sector

Putting aside the complexities of drug-resistant TB, the option for testing and treatment of drug-susceptible TB in the private sector clearly exists on paper. Yet it is not clear how widely such care is actually available, and when it is, whether it is always up to scratch. Our impression is that it is a bit of a lottery as to whether or not your private sector GP has knowledge of TB.

“There are many gaps in knowledge amongst general practitioners, not only for TB,” says Dheda. “Unlike other countries where there are regular licensing exams that are undertaken, we have decided to use a different approach in South Africa and updating one’s knowledge in a particular field is achieved through their own reading and conference attendance, and through the CPD system where they need to accrue a certain number of points showing that they have attended continuing medical education meetings.”

From the limited information available, it appears that the private sector’s approach to testing for and treating TB is underdeveloped. A likely reason for this is because most TB cases are treated in the public sector, so there is little opportunity or need to develop these skills. A few recent studies on TB care in the private sector have shown that there are significant gaps in and among general practitioners in the private sector. “South Africa’s leading role in prioritising TB in policy and practice possibly contributes to its strong public sector performance,” notes a commentary in the South African Medical Journal. “However, it is unclear to what degree recent advancements in TB screening and care recommendations have permeated the private sector.”

One 2022 study looked at the quality of TB and HIV care in the private sector. The researchers used specially trained staff who would go to a general practitioner with one of three sets of symptoms and histories – all indicating possible or confirmed TB. Case one had typical TB symptoms and was HIV-positive; case two had a TB-specified laboratory report and was HIV-negative; and the third case had a history of incomplete TB treatment and was HIV-positive.

Among the 511 interactions the trained staff had with 212 general practitioners in KwaZulu-Natal and the Western Cape, TB was more likely to be ideally managed as per the study framework – meaning the patient was referred to the public sector or given the relevant tests – if the patient had a diagnosis of TB already or a history of TB. The researchers also found that the private sector GPs in their study did not perform as well as public sector doctors in South Africa.

Some of the public health experts we interviewed were sceptical about the private sector’s ability to provide TB care.

Some patients think they’ll get better TB care in the private sector but in reality, it’s been shown that quality of care is actually far poorer when compared to the public sector, Professor Renier Coetzee tells Spotlight. Coetzee is an associate professor at the School of Public Health at the University of the Western Cape.

Conradie has a similar view. Because of personal experience with family members not getting timely TB diagnosis or appropriate treatment, and anecdotes from other doctors and researchers stating similar scenarios, she tells Spotlight that she is not convinced that TB should be treated in the private sector at all.

Dheda disagrees with the idea that drug-susceptible TB shouldn’t be treated in the private sector. “Both the public and the private sectors prioritises patient care and wellbeing and improving outcomes in patients no matter what the disease. The same should apply for TB,” he says.

Strengthening TB care in the private sector

Strengthening these gaps in TB testing and treatment in the private sector is possible in theory, but according to Conradie will require significant investment by medical aid schemes to better equip general practitioners and private sector clinics. She advocates for strengthening referral pathways for the private sector to get TB patients linked to care in the public system. As well as strengthening education on TB for the private sector by improving awareness of how TB presents and how it should be diagnosed.

One way to potentially strengthen the TB response in the private sector is through stronger partnerships with the public sector, particularly around testing for TB. This 2025 pilot study conducted in KwaZulu-Natal linked 158 General Practitioners to free public sector TB testing using an existing medical referral application (Vula). 61 of the doctors (38.6%) submitted at least one sputum sample collected at their practise to be tested for TB. As a result, 107 people who had TB were identified and almost all were linked to care in the public sector. This showed, according to the researchers, a workable public-private mix model for TB management in a high TB burden setting, but more research is needed in this area.

There are some references to including the private sector in the National TB response, the current National Strategy Plan for HIV, TB and STI’s does list the need to engage with all stakeholders, including the private sector, on the policies and guidelines on TB prevention and management. It also vaguely references a multisectoral collaboration that will be guided by the 2017 Moscow Declaration on multisectoral accountability framework for TB.

But how this is playing out in reality, is not clear.

The role of pharmacists

A reoccurring theme in our research for this article is the notion that TB treatment in general could be improved by leveraging pharmacies – both private and public – to make it easier for people to get their medicines.

“More pharmacies in each locality should be designated to carry TB treatment,” says Dheda. “From my experience, often TB treatment is only available at certain designated private pharmacies, and it is not easy to find.”

This experience is echoed by private sector pharmacists interviewed for a recently completed master’s thesis. The thesis has not yet been published, but the author, Brenda Knipe, a pharmacist and master’s student at the University of the Western Cape’s School of Pharmacy shared some general findings with Spotlight.

Her observations are based on interviews with 14 pharmacists from seven provinces (KwaZulu-Natal and the Northern Cape were not included), working in private hospitals or community pharmacies. She says how often pharmacists reported TB patients varied. Some saw many TB patients who come to them to get their treatment, while others never or rarely did.

For those pharmacists interviewed by Knipe who needed to refer patients to the public sector for treatment, some relied on informal networks based on contacts they’ve made in the public sector. This was due to a reported lack of clear guidelines on how or where to refer patients. Knipe says these networks were essentially based on “who you know”. The pharmacists who didn’t have these contacts or informal networks expressed uncertainty about what to do to assist their patients.

The pharmacists, according to Knipe, were eager for more consistent training and continuing professional development on TB so they can assist patients better.

The pharmacists in the study who had to provide TB patients with treatment, according to Knipe, reported sometimes having difficulties in finding stock of drug-susceptible TB treatment. Most community pharmacies don’t normally keep a supply of TB drugs. If a patient does come to the pharmacy with a doctor’s script for TB medicines, the drugs have to be ordered from suppliers. If the drugs are in stock, the pharmacists would then order the full course for that patient, dispense one month’s supply and keep the rest at the pharmacy specifically for that patient.

However, not all the suppliers keep a lot of stock of the drugs on hand, likely due to low demand for TB medicines in the private sector, resulting in some pharmacists in the study reporting that at times they had to phone several suppliers before finding stock. The pharmacists interviewed who were working in private hospitals also had some difficulties sourcing stock of TB medicines, according to Knipe.

Nematswerani points out that Discovery has had similar challenges.

“Discovery Health continues to see a decline in the availability of TB medicines within the private healthcare sector. This is largely attributable to the relatively small number of TB cases managed privately,” she says. “South Africa has a well-established public-sector TB treatment and monitoring programme, and many private healthcare practitioners refer patients to public healthcare facilities for ongoing treatment and follow-up. As a result, demand for TB medicines in the private sector has progressively decreased, contributing to their limited availability through private healthcare channels.”

*This article was first published by Spotlight – health journalism in the public interest. Sign up to the Spotlight newsletter.

Inside The Box with Dr Andy Gray | How Should Medicines Shortages be Managed in South Africa?

#InsideTheBox is a column by Dr Andy Gray, a pharmaceutical sciences expert at the University of KwaZulu-Natal and Co-Director of the WHO Collaborating Centre on Pharmaceutical Policy and Evidence Based Practice. (Photo: Supplied)

By Dr Andy Gray for Spotlight

Imagine you have been taking a medicine for years. Then one day you are told at the pharmacy that supplies have run out. In his latest Spotlight column, Dr Andy Gray zooms in on how governments can monitor and plan for such shortages.

The draft text of the United Nations High-Level Declaration on Pandemic Prevention, Preparedness and Response, which failed to get consensus support at the General Assembly on 25 September 2026, contained this paragraph:

“Deeply concerned by the inequities at national and international levels that hindered timely and equitable access to health products, including vaccines, diagnostics and therapeutics to address coronavirus disease (COVID-19), and recognizing the need to address serious shortcomings at the national, regional and global levels in prevention, preparedness, response and health system recovery for public health emergencies of international concern, including pandemic emergencies;”

However, it is not only during pandemics or public health emergencies that shortages of medicines and vaccines are experienced and have to be actively managed. In fact, in recent decades the issue has become so serious that several high-income countries have taken legal and regulatory steps to address it.

Global access to medicine shortage data

South African health and medicines law does not clearly define what is meant by a “medicines shortage”. By contrast, the US Federal Food, Drug, and Cosmetic Act simply defines it as a period of time when the demand or projected demand for a medicine exceeds its supply.

Since 2012, marketing authorisation holders in the US have been under a legal obligation to report shortages to that country’s medicines regulator. These obligations were strengthened during the COVID-19 pandemic and now require manufacturers to report any interruption in their manufacturing process that is likely to lead to a meaningful disruption in supply, as well as to disclose the reasons for the interruption. Manufacturers are also required to give advanced warning of permanent discontinuation of production, and the reasons for that decision. The US Food and Drug Administration (FDA) maintains a publicly accessible database of current resolved shortages and discontinuations. In addition, the American Society of Health-System Pharmacists maintains a separate database.

Medicines shortages have also been recognised as a critical public health issue by the European Medicines Agency (EMA) and its national agencies. Since 2022, manufacturers have been required to report shortages to the European Shortages Monitoring Platform. The EMA maintains an accessible database of current and resolved shortages, as do each of the national agencies.

A similar resource is provided by the Australian Therapeutic Goods Administration (TGA).

The gap in South Africa

The South African Health Products Regulatory Authority (SAHPRA) has no equivalent reporting requirement, nor does it make any such data publicly accessible.

SAHPRA’s online register includes not only those products with current registration, but also includes those where the status is noted as “Cancelled”. Unfortunately, while the date of registration is recorded, there is no date of cancellation stated, nor any reason provided for discontinuation of the product. Health professionals and patients only find out about product discontinuations after the fact and the regulator has no advanced warning of the decision, nor is it provided with the reasons for discontinuation. There is also no accounting for how many medicines have been withdrawn from the South African market.

Section 19(2) of the Medicines and Related Substances Act allows SAHPRA to request any information from manufacturers, sellers or prescribers of medicines, but the intent is to enable response to a specific request, within a stipulated time period. This provision does not create an ongoing obligation or a permanent reporting process, so cannot be used to impose the type of reporting demanded in the US, Europe or Australia.

A valuable resource – the health department’s “hotlist”

The National Health Department’s website includes a recent innovation, in the form of a “hotlist”, defined as “a list of all essential medicines on contract with stock availability of below 90% and with total orders exceeding supplier stock on hand and total provincial stock on hand less than two months of forecasted demand”. Importantly, the list also documents “the root cause for the supply challenge and proposed remedial actions for each listed item”. The list is updated on a monthly basis and the August 2026 version lists 29 “new” items, 98 described as “longer term” and 120 resolved items. Of particular note, a separate tab lists products which were not being supplied to particular provinces because of non-payment of accounts. The reasons for shortages vary considerably, from delays in quality assurance procedures to delays in accessing critical components, whether active ingredients, excipients or packaging materials. Global supply constraints were also identified, as were local regulatory actions (or delays in obtaining regulatory approval for changes in production).

The health department’s website also provides a link to the current Master Health Product List, which includes all medicines for which a tender has been awarded. One of the columns on the spreadsheet documents the “VEN” status of the medicine. This refers to a judgment on whether a medicine is considered “vital”, “essential” or “non-essential”, in terms of the immediate health consequences of a shortage. Lack of access to a vital medicine, for which alternatives might not exist, would be expected to have immediate and serious health consequences for patients. One way to mitigate that risk would be to contract multiple suppliers of a vital medicine. Such split tenders are used for some essential medicines, notably the first-line antiretrovirals used to treat HIV, but not for all medicines listed as vital.

The private sector – adrift

Not only is there no equivalent of the “hotlist” for the private sector in South Africa, but one of the key responses used by the public sector to manage shortages is also not available. The National Department of Health Contract Management Unit’s website lists the products for which SAHPRA has granted the public sector permission, in terms of section 21 of the Medicines and Related Substances Act, to import unregistered medicines in bulk. In the private sector, similar bulk approvals are not issued, and individual applications are required for every patient seeking access to an alternative product, should there not be a registered alternative on the local market.

Health professionals in the private sector are therefore at a distinct disadvantage, lacking access to timely information about medicine shortages and also denied access to a key mechanism for responding to shortages.

In Australia, the equivalent legal provision (section 19A) enables access to unregistered, imported medicines to manage a medicine shortage considered to be of public health importance. Access is enabled for the entire health system, not only for facilities operated by the state.

The concept of “critical medicines”

European authorities have extended the concept of VEN status to create a list of “critical medicines”. In May 2026, political agreement was reached on the Critical Medicines Act, which will enable a number of important interventions to promote resilience in the pharmaceutical market. One of these interventions will require manufacturers to hold contingency stocks of critical medicines and mandate sharing of data on such stocks when reallocation is required, triggering a call for solidarity between Member States. Procurement of medicines will also be required to promote regional manufacturing in the EU.

Many reasons, key gaps

There can be many reasons for medicines shortages, some related to the national market, others impacted upon by global shifts. Regulatory action by SAHPRA in response to non-compliance with good manufacturing standards has resulted in a number of disruptions in supply, notably in the small volume injectable market.

Although the second single exit price adjustment in 2026 will be welcomed by the pharmaceutical industry, other actions noted in the joint government-industry-regulator statement in August 2026 still require attention. Some immediate actions include a joint review of the pricing regulations, to improve transparency and predictability and also explore alternative reimbursement models for specific medicines. In the longer term, the industry is seeking appropriate incentives, including public sector procurement that supports local production and attracts new investment.

According to the FDA definition, a medicine such as lenacapavir is already showing signs of a shortage, with demand exceeding supply. Improved transparency, applied across both public and private sectors, is crucial if medicine shortages are to be prevented, identified and acted upon with the urgency they deserve.

 – Gray is a Senior Lecturer at the University of KwaZulu-Natal and Co-Director of the WHO Collaborating Centre on Pharmaceutical Policy and Evidence Based Practice.

Disclosure: Gray serves on three technical advisory committees at the South African Health Products Regulatory Authority.

*This column was published by Spotlight – health journalism in the public interest. Sign up to the Spotlight newsletter.

Testing More People with TB Symptoms is Critical to Reducing New Infections, Study Finds

Tuberculosis bacteria. Credit: CDC

By Marcus Low for Spotlight

Many people who report with TB symptoms at South Africa’s public sector clinics do not receive TB tests. Testing more of these people is one of the most effective things we can do to reduce rates of TB disease and death, according to a major new modelling study.

While South Africa has made substantial progress against tuberculosis (TB), we are not on track to meet key targets set for 2030. This is according to a new modelling paper published in the journal Global Health Action.

TB incidence in South Africa was projected to decline by 46% by 2030, relative to a 2015 baseline. The World Health Organization (WHO) End TB target adopted by South Africa aimed at an 80% reduction in incidence. TB mortality was projected to decline by 54%, against the End TB target of 90%.

The researchers also published uncertainty intervals around these estimates. Even though these intervals are relatively wide, their upper limits are below the End TB targets, suggesting that it is unlikely that South Africa will reach the targets by 2030. The modelling however also identified interventions that could help South Africa get closer to the targets.

The new research is an extension of Thembisa, an existing mathematical model of HIV and TB in South Africa. University of Cape Town epidemiologist Dr Leigh Johnson, who is the lead author of the new study, is also the key driving force behind Thembisa.

Identifying what works

The researchers estimated which of a long list of interventions would have the greatest impact against TB. In technical terms, they looked at how varying 27 different parameters linked to TB interventions impacted projected TB incidence and mortality from 2025 to 2040 by calculating correlation coefficients (see the paper for a more nuanced explanation).

They found that the greatest reductions in TB would be achieved if a high percentage (89%) of people reporting with TB symptoms were tested using new point-of-care TB tests. This would result in a 49% reduction in average TB incidence and a 67% reduction in average TB mortality, relative to a scenario in which there are no changes to current programmes. TB symptoms include persistent cough, chest pain, night sweats, fever, and unexplained weight loss. There is good evidence that many people who report with these symptoms at clinics are not offered molecular TB tests.

The World Health Organization earlier this year recommended the use of such new point-of-care TB tests. These tests aren’t yet in general use in South Africa, although they are being evaluated in pilot projects. The new tests can be run on both sputum and tongue swabs. For now, most molecular TB tests in South Africa still involve someone producing a sputum sample – which some people struggle with – and the sample being transported to a lab for testing.

The researchers also found that high rates of door-to-door testing with the new point-of-care tests could reduce TB incidence and mortality by 38% and 49% respectively, while combining high rates of door-to-door testing and digital chest X-ray screening in asymptomatic individuals could reduce TB incidence and mortality by 17% and 21%.

Even without the new tests, there are substantial gains to be had if testing was stepped up in people with symptoms. TB incidence could be reduced by as much as 29% if the level of sputum testing in individuals seeking care for TB symptoms were increased to the upper bound considered by the researchers.

Once people have been diagnosed with TB and start taking TB treatment, they typically become non-infectious within around two weeks. Diagnosing people more quickly thus results in people remaining infectious for shorter periods, thus slowing TB transmission.

Other influential parameters identified by the researchers include the extent to which COVID-19-related behaviour changes are sustained, the rate at which people living with HIV start taking antiretroviral treatment (untreated HIV is a major driver of TB), and the combined uptake and efficacy of 3HP, a relatively new form of TB preventive therapy.

Testing is the key

“We found that the rate of testing in people seeking treatment for TB symptoms is the most important driver of future TB incidence and mortality,” wrote the authors.“This finding is not surprising given the historically low rates of TB testing. In studies of patients seeking treatment for TB symptoms in South African health facilities, the proportion who received a TB test has been highly variable, ranging from 3% to 84%, with a median of only 30%. Similarly low rates have been reported in other countries with high TB burdens.”

The study authors write that these low rates of testing reflect the non-specificity of TB symptoms and healthcare workers’ concerns about the cost and time required to collect sputum specimens and to send them to a central laboratory for molecular testing. In one South African study, they point out that 36% of all people attending clinics had symptoms suggestive of TB.

“Conducting TB testing in such a large fraction of primary care attendees may be infeasible,” they write.

“Achieving high levels of testing in people with TB symptoms could require levels of laboratory testing beyond current testing capacity. However, new point-of-care tests performed on tongue swabs or sputum present an important opportunity to increase levels of TB testing in symptomatic individuals at reduced cost, without placing additional strain on laboratories.”

In addition to reduced cost, the new point-of-care tests also offer quicker results and have lower operational requirements. The main potential benefit of these tests over existing lab tests is thus that they are likely to be used much more frequently.

Regardless of the testing platform, the study authors argue there is a need to strengthen adherence to existing guidelines for systematic testing of all patients with symptoms suggestive of TB and that we need a larger healthcare workforce dedicated to TB diagnosis, better supply chains, and better monitoring systems to identify where and why symptomatic patients are not being tested.

Disclosure: The study reported on here was supported by the Gates Foundation. Spotlight receives funding from the Gates Foundation, but is editorially independent – an independence that the editors guard jealously. Spotlight is a member of the South African Press Council.

*This article was first published by Spotlight – health journalism in the public interest. Sign up to the Spotlight newsletter.

Is Aspen Betting on the Right HIV Prevention Product?

The potent antiretroviral medicine alimatravir is being evaluated in two ongoing clinical trials as a potential once-monthly HIV prevention pill. (Photo: Unsplash)

By Catherine Tomlinson for Spotlight

Aspen Pharmacare has announced that it will not be manufacturing the lenacapavir HIV prevention injection, and that it will instead focus on producing alimatravir, an experimental HIV prevention pill.

At the start of 2020, the only medicine approved to prevent HIV infection in people who are not living with HIV in South Africa was tablets containing the antiretroviral drug tenofovir. Apart from the tablets, ideally taken daily, HIV transmission could also be prevented by the correct use of condoms and reduced through medical male circumcision. Treating people living with HIV also helps a lot, since most people who are stable on antiretroviral treatment become non-infectious.

Since 2020, three more HIV prevention medicines have been registered in South Africa. Most prominent of these is the lenacapavir injection, which provides almost complete protection for six months at a time. The cabotegravir injection (CAB-LA) provides two months of protection and the dapivirine vaginal ring a month of partial protection. Several more products are in advanced clinical trials – including a new formulation of lenacapavir that may provide 12 months of protection and a tablet that could protect for a month.

Yet, despite the promise of new HIV prevention medicines, the rollout and uptake of these products in South Africa and globally has been slower than expected. Currently, only around 350 000 people are using HIV prevention tablets in South Africa, while in the region of 60 000 people have started taking the twice-yearly lenacapavir injections. At these levels, the number of people taking HIV prevention medicines in South Africa remains far too low to make a significant dent in the rate of new infections.

Cost has been a barrier 

HIV prevention tablets cost the health department around $40 (roughly R700) per person per year. This price is considered to be affordable and the tablets are currently available at almost all public sector clinics in the country.

But modelling shows that long-acting injections can prevent more HIV infections than daily tablets, because their efficacy is less reliant on people taking the tablets every day. There is also evidence that many people prefer long-acting injections over daily tablets.

The cost of these newer, long-acting products has been a challenge. The health department has not procured CAB-LA injections, which was registered in the country in 2022. This was largely due to the price of around $160 per person per year. It also didn’t help that the current formulation of CAB-LA provides only two months of protection, compared to lenacapavir’s six.

In June, the health department started rolling out lenacapavir injections to around 10% of public sector facilities – for now the potential demand by far outstrips supply. The limited scale of the rollout is due to both supply and affordability challenges. The health department is paying $60 per person per year for lenacapavir through a Global Fund procurement arrangement that is allowing donors to pay an additional confidential top-up amount to Gilead Sciences above what the health department pays. For now, Gilead is the only supplier of the jab.

Supply should however improve over the next 12 months and prices are likely to come down. Gilead has licensed six companies to manufacture generic lenacapavir and is considering granting additional licenses, possibly to South African companies through a process coordinated by the South African National AIDS Council. Deals are in place with Indian pharmaceutical companies Hetero and Dr Reddy’s that should ensure a generic price of $40 per person per year. Hetero has already filed its product for registration with the South African Health Products Regulatory Authority – although it is expected to only get the green light early in 2027.

Is a new highly affordable option on the way?

In light of these pricing and supply concerns, news from the 2026 International AIDS Society Conference about a monthly HIV prevention tablet under development has made waves. Health economists presented research showing that the monthly tablet, alimatravir, could be profitably produced for a price tag as low as $3 per person per year (a $15 price was indicated in a conference abstract and previously quoted by Spotlight, but the price presented in the conference session was $3).

Not only is this a fraction of the cost of long-acting injections, but it is also substantially cheaper than the cost of daily tablets.

“Alimatravir for $3 per year could be the cheapest HIV prevention drug the world has ever seen, affordable worldwide,” Dr Samuel Cross of Christchurch Hospital told delegates.

He told conference delegates that the methodology used to calculate the $3 per person per year price is the same methodology that has previously been used to predict the manufacturing cost of several medicines. He said that “[o]ver the past decade, this methodology has correctly predicted production costs for [several] drugs,” including drugs for HIV, TB, Hepatitis B and C, and other conditions.

Some caution would however be prudent, given that alimatravir’s safety and efficacy hasn’t been definitively proven. The final verdict will come from two ongoing Phase 3 clinical trials, called EXPrESSIVE-10 and EXPrESSIVE-11 – both expected to report in 2027. Regulators typically approve medicines only after positive findings from such phase 3 trials.

Alimatravir is already influencing the market

Despite the absence of phase III data, alimatravir is already making waves and affecting the market for HIV prevention products.

The most stark example of this is the recent announcement by Aspen Pharmacare that it will no longer pursue a license to locally manufacture lenacapavir and focus instead on developing its capacity to manufacture alimatravir.

Aspen, along with six other companies, are already licensed to produce generic versions of alimatravir. The unusually early licensing of these companies by MSD (known as Merck in the US and Canada) is a key factor as to why this product is expected to be affordable right out of the gate, if it is shown to be effective in preventing HIV.

No generic companies have yet indicated what price they will charge for alimatravir – but the $3 reference price will no doubt exert some downward pressure.

Why Aspen is no longer pursuing lenacapavir manufacturing

Stavros Nicolaou, senior executive for strategic trade at Aspen Pharmacare, this week told Spotlight that Aspen halted its pursuit of a license to manufacture generic lenacapavir because the South African government’s current pharmaceutical procurement policies and practices provide insufficient assurance that the company will be able to recoup its investments.

The absence of guaranteed procurement by the health department, the lack of a local preference procurement policy, and the existence of competitive products – such as alimatravir – coming down the pipeline all factored in Aspen’s decision, said Nicolaou.

He said that developing manufacturing capacity for tablets, such as alimatravir, is less costly than developing manufacturing capacity for injectables, such as lenacapavir.

“We need greater certainty before we make these investments,” Nicolaou told Spotlight.

He added that the early licensing of alimatravir to enable accelerated generic registration of the product following Phase III trials also made the product an attractive candidate for the company to pursue. He said it was premature to comment on the price they might charge for alimatravir.

Aspen’s decision comes against a broader debate regarding the obligations of the health department to support local pharmaceutical manufacturers, while also delivering on its obligations to maximise the benefits derived from the country’s constrained health budget.

What’s next?

A cheap monthly HIV prevention pill could be a game changer in the fight against HIV in the coming years. However, while data on alimatravir are awaited, its potential arrival has complicated the investment decisions facing pharmaceutical companies, governments, and donors regarding new HIV prevention medicines. It has also raised questions over how the state is, or is not, incentivising local production and procurement of locally produced pharmaceuticals.

The prospect of a monthly pill costing around $3 per year is undeniably exciting. Yet scientists have repeatedly shown that offering a range of prevention medicines—allowing people to choose the option that best suits their needs and lives—improves overall uptake. Even if alimatravir works as well as hoped, there will still be a role for six-monthly lenacapavir, let alone the potential 12-monthly version of the jab that is currently being evaluated in a phase 3 clinical trial.

Either way, while the health department must keep a close eye on the products in the pipeline as it plans for the future, it cannot afford to slow the rollout of the products already available.

*This article was first published by Spotlight – health journalism in the public interest. Sign up to the Spotlight newsletter.