Category: HIV

How Nurses are Learning to Administer the New HIV Prevention Injection

By Christina Pitt for Spotlight
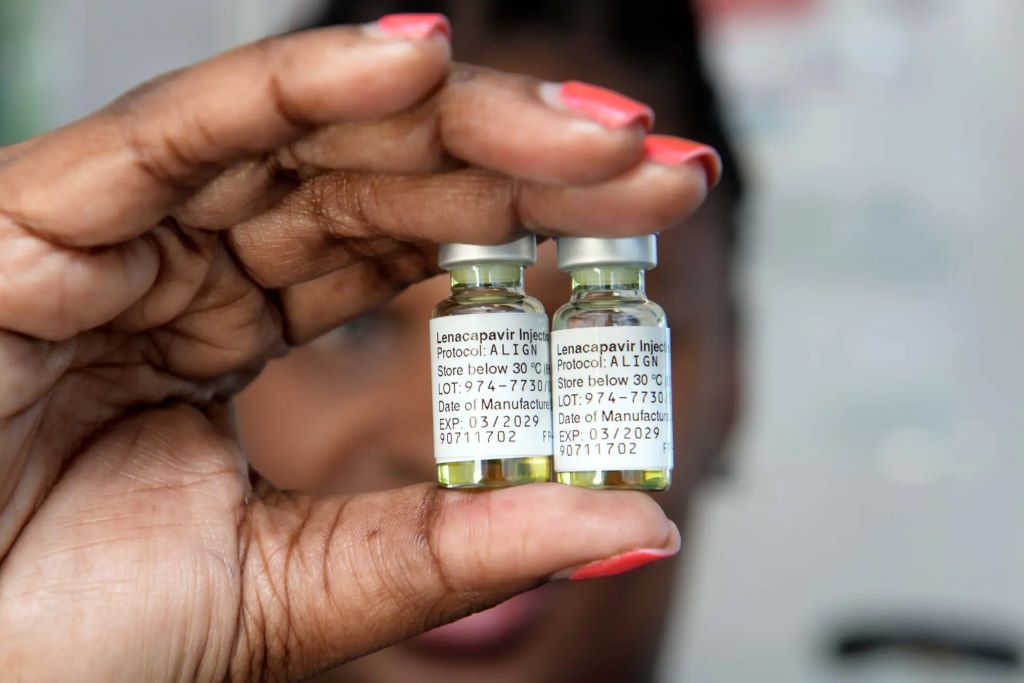
Lenacapavir is administered via two injections of 1.5ml each in the buttocks, thigh, abdomen or upper arm. (Photo: Nasief Manie/Spotlight)

South Africa’s rollout of lenacapavir, a six-monthly HIV prevention injection, requires nurses to learn, adapt and find ways to make it work for patients.

After 26 years in nursing, Sister Keitumetse “Tumi” Senokwane still had something new to learn about giving injections.

The six-monthly HIV-prevention jab, lenacapavir, often referred to as just LEN, presented a unique challenge.

“You know, lenacapavir is different. As much as I’ve got experience with injections, the needle size is different from the subcutaneous (beneath the skin) injections we are used to, and the solution is quite thick,” says Senokwane. “Because we were not used to it, the practical training helped us to get used to it.” She practised withdrawing the yellow liquid, using cooking oil as a stand-in.

That kind of preparation matters because lenacapavir for HIV prevention is being introduced at a time when South Africa still has a substantial need for effective HIV prevention options. The country had an estimated 140 000 new HIV infections in 2025. Modelling suggests that scaling up lenacapavir to 1.4 million to 2.1 million initiations a year by 2030 could avert an average of 32 200 to 51 700 infections annually.

But realising lenacapavir’s potential will depend on more than getting the injection into clinics. It also requires nurses to administer it correctly, answer patients’ questions, and adapt services to their needs.

Getting to grips with lenacapavir

Senokwane is a professional nurse and site manager at Maria Rantho Community Health Centre and Phedisong 1 Clinic in Tshwane, which are participating in the Wits RHI Len4PrEP study.

“LEN4PrEP is an implementation research study, so looking at how we can deliver the product in a real-world setting,” says study investigator Dr Catherine Martin.

The researchers recruited 1 544 participants between November 2025 and June 2026, with follow-up continuing until June 2027. The study began several months before South Africa’s national rollout of lenacapavir on 5 June 2026, when the injection was launched at 360 public health facilities across six provinces.

By 8 October, 76 922 people had initiated LEN nationally, including 36 733 in 133 facilities in Gauteng, according to health department spokesperson Foster Mohale.

For Senokwane and her colleagues, administering lenacapavir meant learning a new HIV prevention method.

Nurses first had to complete a compulsory Nurse-Initiated Management of Antiretroviral Therapy (NIMART) course, which provides a theoretical foundation for managing HIV and antiretroviral treatment. This was followed by practical training in preparing and administering LEN.

Training also covered eligibility, side effects, HIV testing and counselling, with videos and clinical mentorship providing additional support.

Mohale says feedback from early-rollout clinics, nurses and patients would help the department refine its training and guidelines.

At the study clinics, nurses also had to adapt the service to patients’ needs and fit the new injection method into existing care.

The one-stop shop

The Department of Health’s lenacapavir implementation guidelines emphasise counselling clients on their HIV prevention options and helping them choose a method that suits their needs.

At the study clinics, nurses incorporated LEN into existing sexual and reproductive health services, allowing clients to access HIV prevention alongside services such as family planning and STI screening and treatment during a single visit.

“You will get all services in one room like a one-stop shop,” says Senokwane.

“Maybe you are here for lenacapavir, but we also check whether you are on a family planning method. If not, we will give you information and provide a family planning method for you, where we screen you for STIs, and then if you’ve got some infections, we also treat you,” she says.

The LEN4PrEP study also used a mobile clinic to bring HIV prevention and sexual and reproductive health services to young people in their communities.

“So many of our clients already know us. They know how we treat them and the quality of service we provide,” she says.

Initial LEN consultations took longer as nurses explained the available prevention methods and how soon each would offer protection against HIV.

“We give you the information and explain how each method works, how long until it is effective. Participants would like to know when they are going to be protected from HIV if they take this specific method,” says Senokwane.

At the Southern African HIV Clinicians Society’s Long-Acting Antiretroviral Treatment Conference in Johannesburg in September, Wits RHI’s Professor Saiqa Mullick, Director of Implementation Science, shared early findings from the LEN4PrEP study.

She reported that convenience was a major reason participants opted for the lenacapavir jab. They valued not having to take a daily pill or make frequent clinic visits, while the injection offered greater privacy for some. It also attracted people new to PrEP, alongside existing users seeking a method that better suited their lives.

Pre-exposure prophylaxis, or PrEP, refers to antiretroviral medicines taken to prevent HIV infection. When used as prescribed, oral PrEP has been shown to reduce the risk of HIV infection from sex. For several years now, HIV prevention tablets have been widely available in South Africa’s public healthcare system, although uptake has been somewhat muted with only around 350 000 people taking the tablets in mid-2025, according to estimates from Thembisa, the leading mathematical model of HIV in South Africa.

Of the 1 538 participants whose method choices were reported, 85.8% selected the lenacapavir shot, compared with 13.7% who selected the prevention pills and 0.5% who chose not to use PrEP.

“People want options that fit into their lives,” Mullick told delegates.

Sticking the landing

Patients could also choose where in the body to receive the injections: the upper arm, buttocks, abdomen or thigh.

Among the 1 319 participants who started LEN, Mullick says approximately 50% of women preferred the buttocks, while about 51% of men preferred the upper arm. The ongoing study will explore both men and women’s reasons for injection-site preferences.

For nurses, the challenge was to administer the injections correctly while making the process as efficient as possible.

Lenacapavir requires getting two injections during the same visit. Patients also need to take two lenacapavir tablets on the day of their first injections, followed by another two tablets 24 hours later. These tablets form part of the initiation dose before they continue with injections every six months.

Senokwane says a Wits RHI pharmacist taught her a way to withdraw the solution while keeping the vial upright, rather than turning it upside down.

“That was the best method for me because it worked faster,” says Senokwane.

“So with that method, you pull up 1.5 ml of air into the syringe and inject the needle into the vial. [The syringe] draws at least one ml by itself, without assistance, which allows the nurse to multitask. And then you also save time because you are able to prepare two injections at the same time,” she says.

But efficiency was only part of the learning curve. Because lenacapavir is a thick solution, it needs to be injected slowly.

“I wish I knew that you can’t inject it fast,” Senokwane said. The thick solution required a slower injection technique to reduce leakage.

Slow administration was included in nurses’ initial training, but its importance in minimising leakage was reinforced as they gained practical experience and shared lessons with colleagues.

Dr Martin says that in the early stages of implementation, nurses consulted experts, including those involved in clinical trials, on how to manage leakage at the injection site.

“As local experience grew, they learnt to reassure participants that minor leakage could occur and to assess more substantial leakage to determine whether further follow-up was needed.”

Answering patient concerns

Patients were also concerned about the side effects of lenacapavir.

Lumps or small nodules at the injection site are a common side effect of lenacapavir. In one clinical trial, which included 2 140 participants who received lenacapavir, roughly 64% developed subcutaneous nodules at the injection site.

“Most of the clients were curious about the nodules. They were worried about whether they would be able to continue with their normal activities, especially those who wanted to exercise,” says Senokwane.

“They wanted to know how long the nodule would last and whether they would get another one when they came back for their second injection. Usually, by the time they came for their next injection, the nodule would have disappeared.”

Others were worried about the pain.

“We advise them that if the nodule comes with pain, just use a warm or cold compress, or you can even use a painkiller,” explains Senokwane.

Mullick says addressing these concerns and discussing them with clients in advance is part of making the injection work for patients in practice.

“This might seem something relatively small, but from an implementation perspective, it contributes considerably to the person receiving the product.”

Making it work in real time

As nurses became more familiar with administering lenacapavir, the clinics also refined how they moved patients through the service, from the initial consultation to receiving the injection.

Patients first met a navigator who explained the available services. After registration, an HIV test and a check of their vital signs, they saw the research nurse.

The clinics later began using the waiting time more effectively, with navigators introducing patients to PrEP and other services before their consultations.

Initially, appointments could take about an hour and a half. As the clinics refined their workflow and nurses became more familiar with the process, Senokwane says visits took about an hour or less.

“Training manuals and guidelines provide all the theoretical knowledge and framework for delivering lenacapavir,” Martin explains.

“But, that real-world experience gives you a little bit more insight into things that you can only learn by working with clients.”

Each one teach one

Senokwane’s experience eventually helped her become a mentor to other nurses.

“The mentorship was really very important. We’ve got support from our pharmacist, and then we’ve got support from our sub-investigator at site. So everyone needs to be mentored until you are really 100% sure that you can do it on your own,” she says.

When non-research nurses started providing lenacapavir in June at the study sites, she went there to demonstrate the technique. Some nurses she had trained also helped their colleagues.

“They were always grateful that we really helped them. So they really appreciated it. The more you practice, the better you become,” says Senokwane.

Lessons from the clinics also informed training. Videos demonstrating how to prepare and administer lenacapavir were produced by Wits RHI, alongside webinars. Martin says the videos would be incorporated into future training.

“It’s always helpful to see something in practice. With a new product, although it can be explained theoretically, it is helpful to actually see a provider and a client interaction,” she says.

*This article was first published by Spotlight – health journalism in the public interest. Sign up to the Spotlight newsletter.

Researchers Explore Gut & Brain Health Link for People with HIV

Irritable bowel syndrome. Credit: Scientific Animations CC4.0

Oregon Health & Science University researchers have secured a $5.8 million, five-year federal award to investigate whether damage to the gastrointestinal tract contributes to neuroinflammation in people living with HIV – raising the potential for new treatments to preserve brain function in people with HIV and older adults.

“Even though antiretroviral drugs are very successful at suppressing the virus, we’ve seen people living with HIV have neurocognitive disorders similar to what happens when people age,” said co-lead investigator Afam Okoye PhD (professor, OHSU Vaccine & Gene Therapy Institute). “If we can show a dynamic relationship between inflammation in the gut and the brain, this line of research could then lead to new treatments to reduce neuroinflammation.”

The award from the National Institute of Mental Health of the National Institutes of Health will enable researchers to align nonhuman primate models with human autopsy tissues to better understand the interplay between inflammation in the gut and brain health among people living with HIV.

Scientists have long associated inflammation in the gastrointestinal tract with impaired cognition in the brain. People with inflammatory bowel disease are at increased risk for Parkinson’s and Alzheimer’s disease, for example.

This problem disproportionately affects people living with HIV.

Researchers surmise this may be related to the fact that the initial infection of the virus – even when it’s subsequently held in check by antiretroviral therapies – causes lasting damage to immune cells in the GI tract. The research team will include pathologists at OHSU and infectious disease specialists at the NIH to better characterise how exactly inflammation in the gut is linked to brain function.

The research also will involve nonhuman primates at OHSU’s Oregon National Primate Research Center.

“Neuroinflammation in people with HIV is very hard to study,” said Okoye (also Division of Pathobiology and Immunology, ONPRC). “These are very challenging studies to do, but we have expertise and experience in the nonhuman primate model. It’s high risk but also high reward.”

Ultimately, it may be possible to develop targeted therapies that tamp down harmful or runaway inflammation while retaining the beneficial effects of a strong immune system.

“Inflammation in and of itself is not bad,” said co-lead investigator Jacob Estes PhD (professor and director of the VGTI). “It’s part of the immune system’s response to mediate infection. Ultimately, this research could lead to precision targets that would limit pathology that harms brain function but doesn’t completely shut off the immune system’s ability to do the things it needs to do to promote health.”

Source: Oregon Health & Science University

Is Aspen Betting on the Right HIV Prevention Product?

The potent antiretroviral medicine alimatravir is being evaluated in two ongoing clinical trials as a potential once-monthly HIV prevention pill. (Photo: Unsplash)

By Catherine Tomlinson for Spotlight

Aspen Pharmacare has announced that it will not be manufacturing the lenacapavir HIV prevention injection, and that it will instead focus on producing alimatravir, an experimental HIV prevention pill.

At the start of 2020, the only medicine approved to prevent HIV infection in people who are not living with HIV in South Africa was tablets containing the antiretroviral drug tenofovir. Apart from the tablets, ideally taken daily, HIV transmission could also be prevented by the correct use of condoms and reduced through medical male circumcision. Treating people living with HIV also helps a lot, since most people who are stable on antiretroviral treatment become non-infectious.

Since 2020, three more HIV prevention medicines have been registered in South Africa. Most prominent of these is the lenacapavir injection, which provides almost complete protection for six months at a time. The cabotegravir injection (CAB-LA) provides two months of protection and the dapivirine vaginal ring a month of partial protection. Several more products are in advanced clinical trials – including a new formulation of lenacapavir that may provide 12 months of protection and a tablet that could protect for a month.

Yet, despite the promise of new HIV prevention medicines, the rollout and uptake of these products in South Africa and globally has been slower than expected. Currently, only around 350 000 people are using HIV prevention tablets in South Africa, while in the region of 60 000 people have started taking the twice-yearly lenacapavir injections. At these levels, the number of people taking HIV prevention medicines in South Africa remains far too low to make a significant dent in the rate of new infections.

Cost has been a barrier 

HIV prevention tablets cost the health department around $40 (roughly R700) per person per year. This price is considered to be affordable and the tablets are currently available at almost all public sector clinics in the country.

But modelling shows that long-acting injections can prevent more HIV infections than daily tablets, because their efficacy is less reliant on people taking the tablets every day. There is also evidence that many people prefer long-acting injections over daily tablets.

The cost of these newer, long-acting products has been a challenge. The health department has not procured CAB-LA injections, which was registered in the country in 2022. This was largely due to the price of around $160 per person per year. It also didn’t help that the current formulation of CAB-LA provides only two months of protection, compared to lenacapavir’s six.

In June, the health department started rolling out lenacapavir injections to around 10% of public sector facilities – for now the potential demand by far outstrips supply. The limited scale of the rollout is due to both supply and affordability challenges. The health department is paying $60 per person per year for lenacapavir through a Global Fund procurement arrangement that is allowing donors to pay an additional confidential top-up amount to Gilead Sciences above what the health department pays. For now, Gilead is the only supplier of the jab.

Supply should however improve over the next 12 months and prices are likely to come down. Gilead has licensed six companies to manufacture generic lenacapavir and is considering granting additional licenses, possibly to South African companies through a process coordinated by the South African National AIDS Council. Deals are in place with Indian pharmaceutical companies Hetero and Dr Reddy’s that should ensure a generic price of $40 per person per year. Hetero has already filed its product for registration with the South African Health Products Regulatory Authority – although it is expected to only get the green light early in 2027.

Is a new highly affordable option on the way?

In light of these pricing and supply concerns, news from the 2026 International AIDS Society Conference about a monthly HIV prevention tablet under development has made waves. Health economists presented research showing that the monthly tablet, alimatravir, could be profitably produced for a price tag as low as $3 per person per year (a $15 price was indicated in a conference abstract and previously quoted by Spotlight, but the price presented in the conference session was $3).

Not only is this a fraction of the cost of long-acting injections, but it is also substantially cheaper than the cost of daily tablets.

“Alimatravir for $3 per year could be the cheapest HIV prevention drug the world has ever seen, affordable worldwide,” Dr Samuel Cross of Christchurch Hospital told delegates.

He told conference delegates that the methodology used to calculate the $3 per person per year price is the same methodology that has previously been used to predict the manufacturing cost of several medicines. He said that “[o]ver the past decade, this methodology has correctly predicted production costs for [several] drugs,” including drugs for HIV, TB, Hepatitis B and C, and other conditions.

Some caution would however be prudent, given that alimatravir’s safety and efficacy hasn’t been definitively proven. The final verdict will come from two ongoing Phase 3 clinical trials, called EXPrESSIVE-10 and EXPrESSIVE-11 – both expected to report in 2027. Regulators typically approve medicines only after positive findings from such phase 3 trials.

Alimatravir is already influencing the market

Despite the absence of phase III data, alimatravir is already making waves and affecting the market for HIV prevention products.

The most stark example of this is the recent announcement by Aspen Pharmacare that it will no longer pursue a license to locally manufacture lenacapavir and focus instead on developing its capacity to manufacture alimatravir.

Aspen, along with six other companies, are already licensed to produce generic versions of alimatravir. The unusually early licensing of these companies by MSD (known as Merck in the US and Canada) is a key factor as to why this product is expected to be affordable right out of the gate, if it is shown to be effective in preventing HIV.

No generic companies have yet indicated what price they will charge for alimatravir – but the $3 reference price will no doubt exert some downward pressure.

Why Aspen is no longer pursuing lenacapavir manufacturing

Stavros Nicolaou, senior executive for strategic trade at Aspen Pharmacare, this week told Spotlight that Aspen halted its pursuit of a license to manufacture generic lenacapavir because the South African government’s current pharmaceutical procurement policies and practices provide insufficient assurance that the company will be able to recoup its investments.

The absence of guaranteed procurement by the health department, the lack of a local preference procurement policy, and the existence of competitive products – such as alimatravir – coming down the pipeline all factored in Aspen’s decision, said Nicolaou.

He said that developing manufacturing capacity for tablets, such as alimatravir, is less costly than developing manufacturing capacity for injectables, such as lenacapavir.

“We need greater certainty before we make these investments,” Nicolaou told Spotlight.

He added that the early licensing of alimatravir to enable accelerated generic registration of the product following Phase III trials also made the product an attractive candidate for the company to pursue. He said it was premature to comment on the price they might charge for alimatravir.

Aspen’s decision comes against a broader debate regarding the obligations of the health department to support local pharmaceutical manufacturers, while also delivering on its obligations to maximise the benefits derived from the country’s constrained health budget.

What’s next?

A cheap monthly HIV prevention pill could be a game changer in the fight against HIV in the coming years. However, while data on alimatravir are awaited, its potential arrival has complicated the investment decisions facing pharmaceutical companies, governments, and donors regarding new HIV prevention medicines. It has also raised questions over how the state is, or is not, incentivising local production and procurement of locally produced pharmaceuticals.

The prospect of a monthly pill costing around $3 per year is undeniably exciting. Yet scientists have repeatedly shown that offering a range of prevention medicines—allowing people to choose the option that best suits their needs and lives—improves overall uptake. Even if alimatravir works as well as hoped, there will still be a role for six-monthly lenacapavir, let alone the potential 12-monthly version of the jab that is currently being evaluated in a phase 3 clinical trial.

Either way, while the health department must keep a close eye on the products in the pipeline as it plans for the future, it cannot afford to slow the rollout of the products already available.

*This article was first published by Spotlight – health journalism in the public interest. Sign up to the Spotlight newsletter.

Angst as South Africa’s HIV & TB Healthcare Worker Hotline Goes Offline

South Africa’s HIV & TB Healthcare Worker Hotline service is run by the University of Cape Town’s Medicines Information Centre. (Photo: Unsplash)

By Adiel Ismail for Spotlight

A crucial hotline run for nearly 20 years from the slopes of Devil’s Peak in Cape Town for healthcare workers anywhere in South Africa, from the country’s busiest urban hospitals to far flung resource strained rural clinics, has been suspended due to a lack of funding.

Around two decades ago when Dr Laurel Giddy first started working with people living with HIV, they were already very ill. She remembers five of her patients that she put on antiretroviral treatment dying. She says it was heartbreaking.

“I was just at sea. I felt like I was in the deep ocean, and it was very difficult to get help. There just wasn’t a lot of knowledge going around at the time,” she tells Spotlight. “Getting trapped in an environment where you’re not sure what you’re doing and where people die and you feel unsupported is just demoralising.”

This is the kind of high-stakes situation that the team at the South African National HIV & TB Healthcare Worker Hotline responded to when South Africa’s antiretroviral rollout started gathering steam after the end of state-sponsored AIDS denialism.

And with their help, the milestones at Giddy’s HIV treatment clinic that she help set up at the Knysna Provincial Hospital followed: first 100 people on HIV medicine and a couple of years later, 5 000.

“I’m getting quite emotional, but they helped our programme just fly,” says Giddy.

18 years of national support

The free hotline has to date answered more than 86 000 queries from doctors, nurses and pharmacists in public and private healthcare facilities in all corners of the country. The service is run by the University of Cape Town’s Medicines Information Centre.

“Over 18 years, the hotline has provided trusted, evidence-based clinical support to healthcare workers across South Africa, contributing significantly to patient care and strengthening health system capacity,” Annoesjka Swart, manager of the Medicines Information Centre, tells Spotlight.

But now the phone lines have fallen silent.

“Regrettably, we no longer have the financial resources required to sustain the service, having received no funding support for the hotline since April 2025,” she says. “Although we submitted a bid for a tender that was released on 1 April 2026, to our knowledge the bid has not yet been awarded.”

SA’s troubled twins

The suspension of a free hotline service dedicated to providing clinical advice for the management of HIV and TB is particularly worrying in South Africa where the two diseases remain deeply intertwined public health crises.

South Africa has one of the highest TB incidence rates in the world and the largest HIV epidemic in any single country. TB and HIV is among South Africa’s leading causes of death. Each is estimated to claim over 50 000 lives per year, although there is substantial overlap between the two since TB is the top killer of people with HIV.

The connection between HIV and TB is relatively straightforward. People with untreated HIV infection typically suffer severe damage to their immune systems, which dramatically increases the risk of falling ill with TB and dying of it.

One study showed how usage of the hotline by nurses increased dramatically in its first few years. Such support for nurses is particularly important in the context of the health department’s decision to authorise specially trained nurses to diagnose HIV and prescribe antiretroviral medicines in terms of its NIMART (nurse-initiated Management of Antiretroviral Therapy) programme. NIMART has been lauded as one of the reasons why South Africa’s HIV treatment programme could grow as fast as it did in the 2010s. Prior to NIMART, only medical doctors could prescribe antiretrovirals.

The team behind the hotline has also been involved with research – such as this study on healthcare workers’ knowledge of interactions between a widely used antiretroviral and other medicines.

How the hotline works

Swart explains that queries received by phone, e-mail, WhatsApp and ‘please call me’ go directly to one of the specially trained information pharmacists, who record all the details in a password-protected database. “Details recorded include caller demographics – profession, sector, facility, province – and relevant patient details – antiretroviral therapy history, medical history, laboratory results and other conditions/treatment and the question.”

The pharmacist then researches the query using up-to-date, evidence-based references and, where necessary, consults an expert clinician. “All references used and clinician input is recorded on the database. Most queries are answered on the same day,” says Swart.

As the patient of a healthcare worker who calls the hotline, she says that patient can be assured that the best possible treatment has been discussed with a multi-disciplinary team, where needed, without having to leave their local clinic.

Swart adds that hotline pharmacists have access to many clinical experts, based at the University of Cape Town’s medical school, Groote Schuur Hospital, Red Cross Children’s Hospital and more.

“Up to the end of August 2026, the hotline had answered 86 672 queries,” she says. Over the last five years from 2020 to 2025, Swart says the hotline managed about 380 to 430 HIV/TB queries per month, around 18 to 20 healthcare worker consultations every working day, or an estimated 90 to 100 consultations every week.

Most queries are received from the Western Cape, Eastern Cape, Gauteng, and KwaZulu-Natal. “Over the past 5 years, we’ve seen a steady increase in calls from Mpumalanga – 347 in 2021 to 571 in 2025 – and Limpopo – from 90 in 2021 to 201 in 2025,” she says.

Practical resources

While the primary focus of the hotline is to provide clinical support to healthcare workers across South Africa, Swart says her team also develops and designs easy-to-use posters, booklets and tools based on national guidelines.

There is also an associated SA HIV/TB Hotline app available on Google Play and the Apple App Store. It includes a drug-drug interaction checker allowing healthcare workers to check multiple medicines against all HIV medicines, a step-by-step tool on how to manage skin, renal and liver adverse drug reactions to antiretrovirals and TB medicines, and a dosing tool for prescribing HIV medicines for children. “The app had over 6 000 active South African users between April and June 2026,” says Swart.

She adds that a Facebook page was created in 2016, which posts daily news and a weekly query of the week on Fridays to a following of over 12 500 people.

In one query posted on Facebook, a nurse from the Eastern Cape wanted to know if she should recall a patient earlier than the month she instructed. She initiated the 23-year-old male, who had been diagnosed with HIV three days earlier, onto the single-pill, once-a-day antiretroviral regimen of Tenofovir disoproxil fumarate, Lamivudine, and Dolutegravir. While he was clinically well, results for his CD4 count – the number of blood cells in a cubic millimetre of blood which gives an indication of the health of a person’s immune system – was 179 and he tested positive on a cryptococcal antigen test (CrAg).

The hotline’s experts advised the nurse to recall the client urgently, within 1 to 3 days and was pointed to the country’s guidelines which state that any client with a first or new CrAg-positive result should be called back for an urgent lumbar puncture and clinical assessment for meningitis, regardless of whether symptoms of meningitis are present. (Read Spotlight’s special briefing on cryptococcal meningitis, which is a serious fungal infection causing inflammation of the lining of the brain and one of the top killers of people living with HIV in South Africa.)

Swart says based on knowledge gaps that the pharmacists on the hotline pick up through the queries received, the hotline service has provided weekly WhatsApp-based microlearning sessions to three groups of healthcare workers. Since May 2025, 723 nurses, 915 pharmacists and doctors, and 375 community health workers joined these sessions on a wide spectrum of HIV and TB topics.

“The closure of the hotline will result in the unavailability of free clinical support for healthcare workers across the country managing people living with HIV and TB,” Swart says. “In addition, no posts will be added to the Facebook page, no new posters or tools will be designed, the weekly training has stopped, and the app will be maintained but not expanded.”

The funding conundrum

Swart explains that the hotline service has been funded throughout its existence, and most recently through a service level agreement with the National Department of Health from a Global Fund grant. “Our last Global Fund tranche finished in March 2025, and all documents to renew the contract were previously submitted in May 2024 for a new contract to start on 1 April 2025,” she says.

The Global Fund, established in 2002 to provide funding for HIV, TB and malaria programmes, announced in May last year that it was reducing funding to over 100 countries amidst shortfalls. It has indicated that it’s final grant to South Africa of around US$403 million will be for the period running from April 2031 to March 2034.

Swart says her team was informed in November 2024 that the team in charge of the Global Fund grant at the National Department of Health were planning to implement a tender process and was reassured that the hotline activities will still be supported.

“Several delays then ensued in combination with the global funding cuts across the board in February 2025. In April 2026, the service was put out on tender, and we successfully progressed through Phases 1 and 2 of the evaluation process. Following an invitation to present on 15 May 2026, we have unfortunately not received any further feedback, despite follow-up efforts made in a manner that respects the integrity and confidentiality of the procurement process. There has also been no information that another bidder was successful.”

Swart says the hotline’s activities came under strain in October 2025 when significant cuts in staff time were implemented and emergency funding was used to sustain the service.

“While we have always needed to seek and apply for funding, we have kept the service going and never had to face suspension before. Unfortunately, the massive budgetary constraints can no longer be overcome with emergency and cross funding endeavors,” she says. “It will remain suspended until alternative funding can be secured or the tender is awarded, so that we can reopen the hotline and continue all advisory activities.”

Spotlight sent questions to the National Department of Health, but had not received a response by time of publication.

What it means for healthcare workers

The news of the suspension of the National HIV and TB Healthcare Worker Hotline has prompted widespread concern.

Southern African HIV Clinicians Society CEO Dr Fiona Storie says it has promoted the use of the hotline to their extensive network of healthcare workers throughout the years.

“We believe the hotline provides an integral support service to clinicians in the country. The suspension of the hotline represents a significant loss of a valuable resource that enhances evidence-based HIV and TB management in South Africa.”

Noluthando Swartbooi, an occupational health nurse practitioner at Kwazakhele Clinic in Nelson Mandela Bay, tells Spotlight she has been using the hotline for about four years now. “HIV and TB management continues to require ongoing support, up to date knowledge and at times specialist guidance. Having access to experience through the hotline has been extremely helpful,” she says.

With chronic shortages of healthcare workers in the public sector among other challenges, she says she is worried about the suspension of the service. “The cases we deal with are not straight textbook examples so guidance from experts is beneficial. Suspending the hotline could place a strain on healthcare workers as they may have fewer options of teams that may assist in management of patient cases. This may affect the quality of care provided to patients,” she says.

A clinical pharmacist in Mpumalanga, who has been using the hotline for around five years, says she is daunted because most practitioners she works with don’t keep updated with current national treatment guidelines. She says it falls on her with the help of the hotline to ensure that all patients are taking appropriate treatment and the right doses.

“I do not know who I’ll be seeking help from moving forward, especially for patients that need dose adjustments according to the liver and kidney function tests as well as paediatrics since there’s some TB medication that’s out of stock. Their absence will make my workload even heavier than it already is right now,” she says.

For her part, Swart seems committed to limiting the disruption and finding a way to getting the hotline up and running again.

“While the suspension of services represents a significant and regrettable setback, we remain fully committed to preserving the hotline and are actively exploring funding opportunities that may allow us to resume operations in the future,” she says. “Should funding become available, we will work diligently to restore the service as soon as possible.”

Giddy says she is devastated that the hotline service is on its knees. “They supported us in our sorrows, and they rejoiced in our triumphs with us for years,” she says.

*This article was first published by Spotlight – health journalism in the public interest. Sign up to the Spotlight newsletter.

With over 3 600 Western Cape Users, Lenacapavir is “Cool”

Lenacapavir is administered via two injections of 1.5ml each in the buttocks, thigh, abdomen or upper arm. (Photo: Nasief Manie/Spotlight)

By Biénne Huisman for Spotlight

From counselling about small nodules to overcoming people’s fears of needles, Spotlight takes the pulse of a new HIV prevention injection’s rollout in the Western Cape.

At Cape Town’s Philippi Village, beside a rainbow-emblazoned mobile clinic, Olwam Plaatjie says she switched from the two-monthly cabotegravir HIV prevention injection to the six-monthly injectable lenacapavir. Despite small nodules forming at the two jab sites on her abdomen, the 20-year-old is delighted with the new HIV prevention medicine.

Plaatjie, who is from Crossroads and who started taking cabotegravir injections three years ago, says: “I see many people who are HIV positive. Many of them are girls. Guys often don’t even want to be tested; my boyfriend didn’t want to go for HIV tests. So that’s why I started to have a fear. I was like, you know, maybe there is something he is hiding.”

Plaatjie is one of a stream of young women now taking their health in their own hands as they personally implement HIV prevention strategies, thanks to national government and research campaigns aimed at this vulnerable group.

According to Foster Mohale, spokesperson for the National Department of Health, as of 23 August, there have been 3 641 initiations of lenacapavir, or LEN for short, across the 22 government clinics in the province that are offering the injection. Nationally, the number stood at 47 934.

Due to severely constrained supply, lenacapavir is for now only being rolled out to 360 health facilities across six provinces (Free State, Limpopo, and Northern Cape are not currently included). Gauteng accounts for over a third of facilities and KwaZulu-Natal for around a quarter. The Western Cape’s 22 facilities makes up only around 6% of the total. The selection of facilities was in part informed by how well facilities had been doing in the provision of HIV prevention pills, currently available in almost all the country’s public sector health facilities.

Mohale said the three clinics with the highest administrations in the Western Cape as of August 26, were the Khayelitsha Community Health Centre, Michael Mapongwana Community Health Centre, in Khayelitsha, and Nolungile Community Health Centre, also in Khayelitsha.

Uptake in adolescent girls and young women

Asked about the high uptake in this area, Director of Service Priorities Coordination for the Western Cape Government Department of Health and Wellness, Hilary Goeiman, pointed out the community’s large population of adolescent girls and young women, who are being targeted in the medicine’s roll-out strategy.

“Nolungile Community Day Centre has demonstrated strong clinical leadership and effective implementation of the programme, successfully integrating lenacapavir into routine HIV prevention services,” she said.

On the demographics of the administrations, Goeiman said: “Most recipients are women, in line with the initial rollout focus on adolescent girls and young women, women of reproductive age, and pregnant and breastfeeding women who are at substantial risk of HIV acquisition.”

Mohale said 258 pregnant women had been initiated on lenacapavir at the 22 clinics across the Western Cape, since June.

Science in tandem with government

Meanwhile, Plaatjie was part of an initial cohort of 15- to 35-year-olds who received lenacapavir jabs in February, as part of a study spearheaded in the area by the Desmond Tutu Health Foundation. The study, called ALIGN, will evaluate implementation strategies for lenacapavir and how to encourage continued use.

The research is unfolding in collaboration with the Western Cape Department of Health and Wellness and the National Department of Health, but with a separate stock of the drug, independently sourced by the scientists. Social behavioural expert at the foundation, Elzette Rousseau, says their goal is to enrol at least 1 500 people on lenacapavir and to follow them for 18 months. She adds that at this stage, their data is still too limited to have any clear findings.

Cool, but a fear of needles

At Philippi Village, next to Plaatjie, Lutho Windvoel reflects on lenacapavir. He says that to his knowledge, men can be afraid of injections, and thus of HIV prevention through jabs. But, to him the benefit of protection over six months outweighs a fear of needles. “It’s just cool,” says Windvoel, who is wearing a black T-shirt with a pink teddy bear graphic.

At Philippi Village in Cape Town, a rainbow-emblazoned mobile clinic operated by the Desmond Tutu Health Foundation provides Lenacapavir injections. From left to right: Olwam Plaatjie, Sinovuyo Plaatjie, Lutho Windvoel, and Okuhle Trinity Potelwa. (Photo: Nasief Manie/Spotlight)

“LEN makes life easier. People are excited. Before, I took PrEP tablets daily but I worried that I would forget.”

Also in the conversation is Sive Mphambaniso, youth reference engagement facilitator at the Desmond Tutu Health Foundation. On a fear of injections, particularly among men, Mphambaniso agrees: “Most of them [men], when we talk about injections, they’re like, ‘nah.’ Many men are afraid of needles. Especially when we talked about cabotegravir when it arrived. So many of them preferred to take the oral PrEP, actually. Until the six month injection came in. Now people are saying, ‘it’s better for me to just have the guts to take the injection, rather than taking pills every day’. It’s the promise of six months that makes you just say, ‘Now let me have the guts to do this thing’.”

On some men being resistant to HIV testing or prevention, he says: “To be honest, it’s a struggle. And talking to men about HIV prevention, it’s quite a challenge, but it is happening. And I would say it is better for them to come to the mobile clinic rather than to go to a traditional clinic. Sometimes men don’t like people to think that they are sick. So they come here, it’s quite quick and it’s efficient.”

From the researchers’ side, Rousseau pointed out that one in four of their clients for lenacapavir had been men, “similar numbers to those accessing oral PrEP,” she says.

Small nodules that disappear

Speaking to Spotlight, Plaatjie and Windvoel, along with Sinovuyo Plaatjie, 22, and Okuhle Potelwa, 19, who were also in the initial cohort in the study led by the Desmond Tutu Health Foundation, agree that small nodules formed under the skin where the lenacapavir was injected. “It was like small bumps,” said Plaatjie. “It’s not even visible, but you can just feel it when you touch yourself. And it’s not sore.”

Lenacapavir is administered via two injections of 1.5ml each in the buttocks, thigh, abdomen or upper arm. Speaking to Spotlight, the four recipients say the nodules had not been painful, and that the bumps started growing smaller after about a month and eventually disappeared. They did not experience any other side effects.

Inside the “Tutu teen truck” mobile clinic parked at Philippi Village, nurse Zimasa Zwide elaborates on the nodules. “Most of the time they form immediately, especially on the slimmer people,” she says. “So what I normally do when I’m injecting people, I ask them to feel the nodules so that they won’t be surprised at home later. They get smaller with time and they disappear depending on the body of each participant. And most of them are not reporting any pains.”

However, at a workshop hosted by the Bhekisisa Centre for Health Journalism at the end of August, Spotlight heard from two lenacapavir users, who did report initial pain along with “bumps” at the injection sites – for a few weeks following administration. At some facilities, icepacks are used to numb the injection site, either before or after the injection is administered, or both.

Glass vials of pale yellow liquid

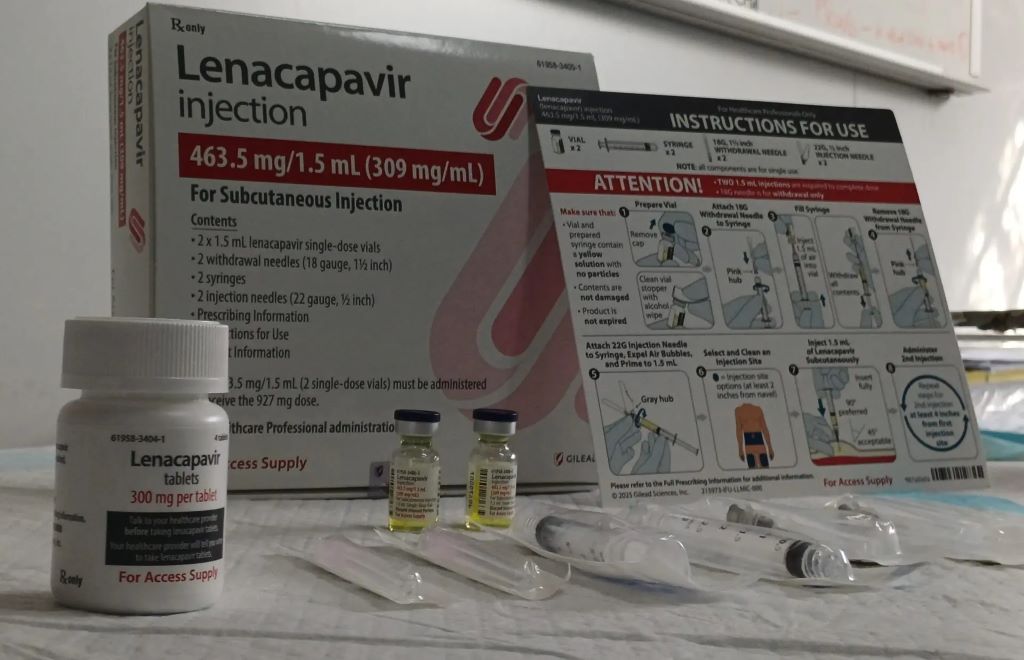
During our conversation, Zwide opens a lenacapavir dosing kit. Inside there are two syringes, two glass vials of pale yellow liquid, and a plastic container with tablets.

She says: “It’s two injections. One on each side of the abdomen, well depending on the injection site that they are choosing. And two tablets which are taken on the day of the injection, plus two tablets that I give them to take home, and which needs to be taken exactly 24 hours later. The tablets, it’s a form of speeding up the absorption process of the lenacapavir.”

If these steps are followed, she says, a recipient is fully protected against HIV three days later. The recipient needs to visit the clinic a month later for an HIV test and follow-up treatment. Zwide says the most patients she have injected with lenacapavir in her mobile clinic in a day were around six or seven people. This is her maximum capacity, she says, as the required administration takes around two hours per person.

Demand for the jab

On demand for the jab, Zwide says: “On a daily basis, there are a lot of people who are interested in lenacapavir. When we started rolling out LEN, there were a couple of participants who were coming in, even ones who were older than 35. Unfortunately, in our service, we take from 15 to 35 years, so we couldn’t give them. But luckily as it was now rolled out at the local clinics, we can refer them to Phumlani Clinic [three kilometres away].” Phumlani Clinic is one of the 22 facilities in the Western Cape offering the injection.

Contents of a Lenacapavir injection kit, including the drug vials, syringes, needles and instruction pamphlet, alongside a plastic pill container holding lenacapavir tablets. (Photo: Elri Voigt/Spotlight)

Responding to Spotlight’s questions around education on lenacapavir and demand creation in South Africa, Rousseau spoke highly of government’s rollout efforts.

“The national launch of lenacapavir in early June has created great demand and awareness of lenacapavir,” she says.

In addition, Mphambaniso points out the value of creating awareness about HIV prevention strategies and lenacapavir on channels that reach young people, specifically social media like TikTok.

Goeiman explained distribution of the medicine around the country. “Lenacapavir is procured centrally by the National Department of Health and distributed to provinces through phased deliveries. The Department continues to actively manage available stock to ensure equitable access throughout the phased rollout.” Technically, the department is procuring the medicines from the pharmaceutical company Gilead Sciences using money from the Global Fund (a large multinational donor).

For now, lenacapavir supply in South Africa remains highly constrained. That is expected to change once generic versions of the drug are registered and marketed in South Africa. Gilead have granted several companies licenses to produce generics. One of those, the Indian pharmaceutical company Hetero, has already filed a lenacapavir generic with the South African Health Products Regulatory Authority.

It seems plausible that the first lenacapavir generics will be approved in the first half of 2027 and indications are that the Department of Health will be quick to move to procuring lenacapavir generics on tender. Once that happens, the programme should expand rapidly with the aim of eventually covering all public healthcare facilities in the country.

This article was first published by Spotlight – health journalism in the public interest. Sign up to the Spotlight newsletter.

Some Pharmacists Can Now Apply for Permits to Provide HIV Prevention Pills Without a Doctor’s Script

Specially trained pharmacists will be allowed to dispense HIV treatment and prevention medicines without a doctor’s script. (Photo: Unsplash)

By Catherine Tomlinson for Spotlight

Ten months after an enabling court judgment, some pharmacists in South Africa can finally start applying for permits that allows them to dispense HIV prevention pills without a script from a doctor.

Specially trained pharmacists can now begin applying for permits to dispense antiretroviral medicines for HIV prevention without a doctor’s prescription. The long-awaited permitting process was announced to pharmacists in a South African Pharmacy Council (SAPC) e-Note on 13 August.

The announcement came 10 months after the Supreme Court of Appeal cleared the way for the implementation of pharmacist-initiated management of antiretroviral treatment (PIMART) in South Africa.

What is PIMART?

PIMART is a form of task-shifting that allows pharmacists to provide some limited HIV services that are currently only provided by doctors and nurses.

It is intended that, under the PIMART programme, pharmacists that have completed a dedicated training programme and have received a special permit from the Director-General of Health will be authorised to provide first-line antiretroviral treatment to people with uncomplicated HIV without a doctor’s script.

They will also be allowed to dispense HIV prevention medicines without a doctor’s script – this includes both pre-exposure prophylaxis (PrEP) and post-exposure prophylaxis (PEP). PrEP is taken prior to sex to prevent potential infection while PEP is taken shortly after a possible HIV exposure to prevent infection.

PIMART’s long road to implementation

The SAPC first proposed PIMART to the health department in 2018. The proposal was in response to a request from the department for pharmacists to take on a larger role in the country’s HIV response.

In 2021, Spotlight reported the imminent launch of PIMART services in South Africa’s pharmacies, but then a court challenge against PIMART by a group of general practitioners blocked the programme’s implementation.

Four years later, in October 2025, a ruling by the Supreme Court of Appeal finally cleared the way for SAPC to launch PIMART. Following the court ruling, Vincent Tlala, CEO and Registrar of the SAPC, told media that the SAPC would issue a memo in November 2025 inviting pharmacists to apply for PIMART permits. But this would in fact only materialise in August 2026.

The SAPC’s 13 August memo to pharmacists, said that certain pharmacists can now begin to apply for temporary PIMART permits to provide PEP, PrEP, and HIV testing services – but not yet HIV treatment services. The temporary permits will be valid for 24 months.

Also, only pharmacists that completed the South African HIV Clinicians Society’s (SAHCS) previous PIMART training course can apply for the limited-scope, temporary PIMART permits.

Pharmacists that have not completed this course will have to wait for a new training course to be accredited and launched before they can apply for permits to provide PIMART services.

How long will it take to get a permit?

Tlala told Spotlight that the granting of the limited-scope, temporary PIMART permits by the Director-General and their recording by the SAPC may take a few months.

“The Department of Health processes applications for permits within 90 days (maximum),” said Tlala, adding that “[t]he PIMART permit recording process with the South African Pharmacy Council then takes between 72 working hours and 14 days, depending on the completeness of the application.”

The permits will only be granted to pharmacists who have already completed the Southern African HIV Clinicians Society’s (SAHCS) continuous professional development (CPD) PIMART course. Pharmacists that did not complete this course will need to wait for an updated PIMART course to become available before they can undertake the required training to be permitted.

Fiona Story, CEO of SAHCS, told Spotlight that nearly 800 pharmacists have completed the course.

Taken together, all of this suggests that toward the end of the year, a few hundred pharmacists in South Africa might be dispensing HIV prevention medicines without doctors’ scripts.

When will the updated training course be available?

Currently, there is no PIMART training course available for pharmacists, as the previous PIMART training course provided by SAHCS is on pause, while the updated course awaits accreditation. Based on dates provided by SAHCS, the updated course might only be available early next year.

However, once the updated course is available, it is anticipated that pharmacists that complete it will be able to apply for full-scope PIMART permits that allow them to dispense first-line antiretrovirals to people with uncomplicated HIV without a doctor’s script, in addition to PEP and PrEP.

“The CPD-accredited PIMART course is no longer available as it was reviewed and updated in line with the requirements for accreditation as a supplementary training course,” Story told Spotlight.

She said that the SAHCS is seeking accreditation of its updated PIMART training course from the SAPC. “SAHCS anticipates the PIMART supplementary training course accreditation process will conclude before the end of 2026,” said Story. She added: “SAHCS has prepared to launch the PIMART supplementary training course as soon as accreditation has been received.”

When will pharmacists be able to dispense HIV treatment without a doctor’s script?

The timeline for when pharmacists will be able to provide the full scope of services intended under PIMART, including HIV treatment for uncomplicated cases, remains unclear. Before this can happen, the SAPC must accredit the SAHCS’ updated supplementary training course and the SAHCS must launch this course.

After this, the permits granted to pharmacists by the Director-General will need to be expanded to include the provision of first-line antiretroviral therapy for treatment of uncomplicated HIV.

In the meantime, the around 800 pharmacists who completed the SAHCS’s previous PIMART training course can now start applying for permits to provide PrEP, PEP, and HIV testing services.

This article was first published by Spotlight – health journalism in the public interest. Sign up to the Spotlight newsletter.
What are Broadly Neutralising Antibodies and What do They Mean for the Fight Against HIV?

After several years of living with HIV, some people are able to produce a special type of antibody known as broadly neutralising antibodies. (Photo: Pixabay)

By Catherine Tomlinson for Spotlight

HIV is known for its ability to outsmart our immune system’s normal defences. A small number of people living with the virus are however able to generate unusually effective immune responses. In this special briefing, Spotlight zooms in on broadly neutralising antibodies, the secret sauce in these immune responses, and their potential role in the future of HIV treatment and prevention.

Our immune systems are highly effective at identifying and fighting off foreign invaders, such as viruses. One way our immune systems does this is by producing antibodies. In short, antibodies recognise viruses and then latch on to them. This blocks the viruses from entering our cells and flags them for destruction by other parts of the immune system.

One of the most remarkable things about our immune system is that it is able to create an enormous variety of such antibodies tailored to each different virus and other disease-causing pathogen that we encounter over our lifetime.

The human immunodeficiency virus (HIV), however, outsmarts our bodies’ normal immune responses by constantly changing the parts of its surface that antibodies recognise. This makes HIV difficult for antibodies to attach to and neutralise.

After several years of living with HIV, some people are able to produce a special type of antibody, known as broadly neutralising antibodies, or bNAbs. These antibodies are more effective at neutralising HIV than regular antibodies because they recognise parts of the virus that change very little, known as ‘conserved regions’. By targeting parts of the virus that are less prone to change, bNAbs are more effective than regular antibodies in identifying and neutralising the constantly changing virus.

“About 20 percent of people living with HIV naturally develop bNAbs, after many years,” explains AVAC, a US-based NGO seeking to advance the development of HIV prevention tools. “By the time bNAbs have developed in these individuals, the constantly mutating HIV has outpaced these defenders, changing too fast and too significantly for bNAbs to be effective in that individual. But that same bNAb, or a combination of them, may work in someone else,” they say.

A vibrant area of research

Researchers first identified bNAbs in a person living with HIV in the 1990s. Since then, they have discovered many more bNAbs and papers and presentations on the topic have become a staple at HIV conferences. At the 2026 International AIDS Conference held in Rio de Janeiro, Brazil, in July, there were 21 abstracts related to the topic.

Since the 1990s, researchers have learned how to replicate and produce bNAbs in the lab. They have conducted early-stage trials showing that bNAbs can be safely administered to people and they have learned how to engineer bNAbs to increase their potency and make them last longer in our bodies.

Currently, researchers are studying whether bNAbs, given by infusion or injection, can prevent HIV infection in people who are HIV negative and control the virus in people who are already living with it. There is also an interesting cross-over with vaccine research, whereby researchers are trying to develop HIV vaccines that prompt the body into making bNAbs.

Before we dig into the details, it is worth stressing that all of this research is still at an early stage. Whereas bNAbs show promise, they have neither set the world alight, nor completely failed. For now, antiretroviral medicines remain the only effective form of HIV treatment, as well as being an extremely effective form of HIV prevention. It is not clear whether bNAbs will ever reach the high bar set by antiretrovirals.

bNAbs for HIV prevention

One of the big HIV stories of the last decade or so has been the use of antiretrovirals to prevent HIV infection. Antiretroviral tablets to prevent HIV infection are already widely available in the public sector, and since June this year, government has been rolling out the six-monthly lenacapavir HIV prevention injection to around 10% of clinics. Such pre-exposure prophylaxis, taking something to prevent infection, is commonly referred to as PrEP.

One of the big hopes for bNAbs is that an infusion of the cells could similarly work as a form of HIV PrEP. The thinking is that these ‘smarter’ immune responses will be more effective than our regular immune responses in recognising and neutralising the shape-shifting virus, and thus clearing it before it can get a foothold in the body.

Substantial research has already been done in this area with two landmark studies, the AMP trials, having garnered the most attention. In the two trials, researchers evaluated an infusion of a bNAb called VRC01 to prevent HIV acquisition in men and transgender people who have sex with men, as well as in cis-gender women. The trials were conducted by the HIV Vaccine Trials Network (HVTN) and the HIV Prevention Trials Network (HPTN).

The AMP trials found that VRC01 did not prevent HIV infection. While this was disappointing, the studies did make a breakthrough by showing that bNAbs could neutralise strains of the HIV virus under certain conditions. While HIV could shape-shift enough to get around VRC01 and cause HIV infection, VRC01 was able to neutralise the HIV strains that were vulnerable to this specific bNAb.

This pattern of bNAbs blocking some, but not all strains of HIV, has been seen in several other studies. It provides both reason for hope, since there is clearly some efficacy, but also frustration, since the efficacy is not nearly as good as what is achieved with antiretrovirals.

Learning from the AMP trials, scientists are now studying whether combining different bNAbs that target a broader range of HIV strains, as well as different regions of the virus’ surface, into a single infusion or injection can be used to prevent HIV.

HVTN and HPTN’s planned Combo-AMP trial will evaluate whether providing people with a combination of different bNAbs can prevent HIV, explained Fred Hutchinson Cancer Center’s Holly Janes at the recent AIDS Conference.

Beyond the AMP trials, the Durban-based research group CAPRISA has also led important studies on the use of bNAbs for HIV prevention. They recently announced the results of a trial called CAPRISA 012C that evaluated the use of a combination of two bNAbs to prevent HIV acquisition in young women in Southern Africa.

Disappointingly, the combination bNAb provided in this trial did not prevent HIV infection. However, CAPRISA reported that “a positive finding was that there was a trend towards protection when the viruses were sensitive to both or one of the two bNAbs compared to when the viruses were resistant to both bNAbs.” In other words, HIV infections occurred more frequently with strains of the virus that were resistant to the bNAbs studied than with strains that were sensitive to them.

“The CAPRISA 012C trial is a culmination of 22 years of research – while it has not led to a new HIV prevention product, it provides valuable information to guide further bNAb research,” said CAPRISA, adding that sensitivity to bNAbs in contemporary circulating viruses will need to be factored into planning future trials of bNAbs.

bNAbs for HIV treatment

bNAbs are also being evaluated as potential treatment for HIV. Researchers are trying to understand whether, under what circumstances, and for how long bNAbs can control the virus in people living with HIV, with the goal of developing products that can achieve long-lasting HIV control without antiretroviral treatment.

This is important because the emotional and psychological burden of having to adhere to a life-long daily pill regimen to treat HIV is a known cause of poor treatment adherence. For infants and young children there are also practical challenges to swallowing and keeping down daily treatment.

One of the main ways that researchers are evaluating the potential of bNAbs to treat HIV is through analytical treatment interruption (ATI) studies. In ATI studies, people living with HIV are given bNAb infusions or injections –  sometimes in combination with long-acting injectable antiretroviral drugs – and then temporarily taken off their regular antiretroviral treatment under close medical observation.

Researchers then monitor how long HIV remains suppressed in order to learn whether and how well bNAbs can control HIV infection.

The results from ATI studies, including the RIO and FRESH trials, have been tantalizing. bNAb infusions have allowed some study participants to remain off antiretroviral treatment for more than a year without the virus rebounding in their bodies.

Yet, the studies have also raised questions about how and why bNAbs have such mixed efficacy. Researchers are still trying to understand why some people are able to maintain periods of viral control after receiving bNAbs, while others experience rapid viral rebound. The reasons for this appear to extend beyond a person’s sensitivity to the specific bNAbs being used to also include other factors related to the characteristics of one’s HIV infection and immune response.

At the 2026 AIDS Conference, Michel Nussenzweig, senior physician at the Rockefeller University, told delegates that research so far indicates that bNAb therapy is more likely to deliver periods of post-treatment control in individuals with a less diverse HIV reservoir, pre-existing autologous antibodies, and pre-existing stem cell like CD8+ T cells.

Scientists are now considering whether the factors associated with bNAb treatment success can be boosted through other interventions, said Nussenzweig.

Another important area of research is whether bNAbs can be used as a form of treatment for infants and young children living with HIV. An infusion or injectable treatment could be a gamechanger for this group, given the challenges faced by caregivers in getting infants and young children to swallow and keep down daily antiretroviral treatment.

The Tatelo and Tatelo Plus studies conducted in Botswana were set up to evaluate whether young children given bNAbs can maintain viral suppression after stopping antiretrovirals. Results from the Tatelo study reported in 2022 showed that some children (44%) who received a combination of two bNAbs were able to maintain a period of viral control (24 weeks) after stopping HIV treatment. The Tatelo Plus study, now underway, is evaluating whether and for how long a combination of three bNAbs can maintain HIV suppression in young children after antiretrovirals are stopped.

bNAbs for HIV vaccination

While bNAbs have not yet been shown to be a practical and effective form of HIV prevention or treatment, research has demonstrated that, under the right conditions, they can protect against and suppress HIV strains that are susceptible to them.

These findings have generated excitement about using bNAbs as a target for HIV vaccines. Unlike research into bNAbs for PrEP or HIV treatment, in which laboratory made bNAbs are infused or injected directly into our bodies, some HIV vaccine researchers are trying to figure out how to trigger our bodies to produce their own bNAbs.

In other words, vaccine researchers are trying to make our bodies, rather than laboratories, the factories that make bNAbs against HIV.

At this stage, scientists do not expect that a single vaccination will be able to trigger our bodies to produce mature bNAbs capable of combating HIV. Instead, they anticipate that a vaccine protocol that involves a series of vaccines will be needed to coax our immune systems to produce mature bNAbs.

While this branch of research remains at its early stages, many HIV researchers are hopeful that it may one day produce an effective vaccine protocol against HIV.

One study to watch is a Phase 1 safety and dosing trial launched by the International AIDS Vaccine Initiative (IAVI) and partners in South Africa at the end of 2025. “The hypothesis being tested is that highly specialized vaccine immunogens, delivered in a specific sequence, can target certain B cells within the immune system and coach them toward the production of broadly neutralizing antibodies against HIV,” says IAVI, adding “scientists widely believe that a vaccine inducing broadly neutralizing antibodies (bNAbs) could provide broad protection against many strains of HIV.”

Where to from here?

Since the first bNAbs against HIV were discovered in the 1990s, scientists have made important, but incremental, progress towards translating these immune responses into tools that can prevent and treat HIV.

As we’ve seen in this Spotlight special briefing, research into bNAbs for HIV treatment is arguably the furthest along, with bNAbs already demonstrating the ability to control HIV during extended periods of antiretroviral treatment interruption in some people. But why some people respond to this treatment and not others remains uncertain. This is an important area for future research.

In the HIV prevention space, bNAbs have delivered protection against HIV strains susceptible to the specific bNAbs studied, but this protection has not been broad enough to protect against HIV infection by the highly diverse, mutating virus. Hope however remains that combining different bNAbs that target different conserved regions of the HIV virus, as well as currently circulating viruses, could broaden protection enough to prevent HIV infection. Here too, as with attempts to develop vaccines that spark the production of bNAbs, it is imperative that the research continues.

Of course, even if scientists can crack the code and find a way to produce highly effective bNAbs, the road ahead might not be a smooth one. For these products to have an impact in the developing world, where they are most needed, they will have to be cost-effective compared to cheap antiretroviral therapy. They will also have to be easy to administer in often stretched and under-resourced healthcare systems.

While much remains to be done, the scientific leads are certainly there, waiting to be explored.

This special briefing is part of a series by Spotlight – health journalism in the public interest. Sign up to the Spotlight newsletter.

Triple-dose Regimen May Permanently Clear HIV in Infected Newborns

OHSU-led discovery in animal model could advance quickly to clinical trials in people

Research from the lab of Jonah Sacha, PhD, at OHSU, has identified a one-time regimen of therapies for newborns with HIV that, if given within three days of birth, could permanently clear the virus. The research team hopes to use the animal model results to move into a human clinical trials. (OHSU/Christine Torres Hicks)

Every year, more than 120 000 newborns worldwide contract HIV, a global health burden that requires lifelong treatment for millions of people – assuming they have access and can afford it. New research led by Oregon Health & Science University suggests another possibility: a one-time regimen of therapies given to newborns within three days of birth to permanently clear the virus. The research was published in the journal Nature Microbiology.

“The really exciting part is that it could go to clinical trials immediately to eliminate HIV infection in newborns,” said co-lead author Jonah Sacha, PhD, professor and chief of pathobiology and immunology at OHSU’s Oregon National Primate Research Center and Vaccine and Gene Therapy Institute. “The next step after that is to test if this can work in newly exposed adults.”

The research involved many collaborators and nonhuman primates at both the Oregon and California national primate research centres.

Researchers tested three distinct treatments that were delivered for a few weeks: neutralising antibodies, standard antiretroviral therapy, and an experimental monoclonal antibody known as leronlimab.

Each of the individual treatments has been tried previously and failed to permanently clear the virus – and Sacha wasn’t convinced combining them would work any better. Sacha has worked for years to develop leronlimab, which is designed to block HIV from entering immune cells through a surface protein called CCR5. His longtime OHSU colleague and coauthor Nancy Haigwood, PhD, thought combining existing therapies with leronlimab might be effective.

The study that published today shows she was correct.

Haigwood, a former professor and ONPRC director, is a virologist and immunologist who has specialised in HIV antibody research for decades. “We were astounded and overjoyed, actually,” Haigwood said. “It’s a remarkable result.”

Antiretroviral therapy has already been approved in people, whereas broadly neutralising antibodies and leronlimab are both being tested separately in clinical trials. This new discovery of a one-time, three-part regimen to clear the virus in newborn babies would first need to be tested in clinical trials in people – most likely in newly exposed adults initially – before it would be widely available to constrain an HIV epidemic that continues to kill 600 000 people worldwide each year.

Researchers say they are optimistic, given the anatomical similarity between nonhuman primates and people.

“There was no reason to think this would completely clear the virus,” Sacha said. “It’s one of those things where you test it and, holy cow, it works and you’ve discovered something new.”

Exactly how this approach worked remains unclear, but Sacha and Haigwood said it appears that the combination of therapies is far more potent and effective than each therapy alone. The key appears to be leronlimab’s ability to block HIV from entering immune cells through the surface protein CCR5.

“For reasons we don’t understand, HIV really wants to use CCR5 receptors to infect cells,” Sacha said. “By blocking access, it’s like you’ve kept fuel away from the fire.”

Haigwood uses a slightly different analogy:

  • Turning off the faucet: Antiretroviral therapy doesn’t eliminate HIV altogether, but it minimises its ability to replicate.
  • Mopping up: Neutralising antibodies effectively corral HIV so there is less virus circulating in the body’s blood supply.
  • Sealing off: Leronlimab blocks what’s left of the virus from infecting immune cells – the equivalent of sealing off the room with a water-tight valve.

Haigwood believes the combination appears to be especially potent early in the infection.

“There’s a lot more going on during the first week of infection than we previously thought,” she said. “From this experiment, it looks like there’s a dynamic interaction between the virus and antibodies that takes place as the virus begins to spread.”

Researchers are eager to see whether the combined regimen can be effective beyond 72 hours of the initial infection.

“We only tested out to three days,” Sacha said. “Could it work a week after infection? Two weeks? How far can you go after infection, and still purge the virus?”

By Erik Robinson

Source: Oregon Health & Science University

Another HIV Treatment Option – but with Less Weight Gain

SA study finds doravirine works as well as dolutegravir to supress HIV viral load, enabling choice for those living with HIV.

Photo by Miguel Á. Padriñán

If you’re a black, 34-year-old South African woman living with HIV, antiretroviral (ARV) treatment options have likely been limited to tenofovir disoproxil fumarate (TDF), lamivudine (3TC) and the ‘gold standard’ dolutegravir (DTG).

Now, another once-a-day, three-drug regimen has been found to be as effective as DTG in supressing HIV viral load.

Not only is the once daily regimen of tenofovir disoproxil fumarate (TDF), lamivudine (3TC) and doravirine non-inferior to DTG, it is associated with significantly less weight gain and has a better lipid profile than the combination favoured and recommended as first-line in many countries, and increasingly in low-and-middle income countries.

These were the end point findings of the South African Opti-DOR study presented at the 2026 International AIDS Society Conference on HIV Science on 31 July and published in the Journal of the American Medical Association (JAMA).

Dr Joana Woods, Senior Research Clinician at Ezintsha at the University of the Witwatersrand (Wits) and lead author, says:“The findings are important because although second-generation ARVs such as dolutegravir and bictegravir are highly effective HIV medicines, they have been consistently associated with substantial weight gain and new onset obesity, particularly among women and black populations and especially when combined with TAF. This has raised concern about long-term cardiometabolic risk, including diabetes and cardiovascular disease.”

In primary healthcare, prevention is better than having to deal with long term consequences. This is why in a country like South Africa with widespread HIV and NCDs, managing weight gain in people living with HIV is critical to their health.

“So if you can start an ARV that’s not going to cause as much weight gain, or not cause weight gain at all, or have an alternative, that would be first prize. And that’s the premise of this study,” says Woods.

About the OPTI-DOR Study

The Africa Health Research Institute (AHRI) ran the rural arm of the Opti-DOR study at the AHRI-Somkhele site in rural northern KwaZulu-Natal province.

“By including participants from both rural KwaZulu-Natal and urban Gauteng, we can be confident that these findings are relevant to people living with HIV in different communities across South Africa,” says Professor Limakatso Lebina, Principal Investigator at the rural AHRI-Somkhele study and Director of Science at AHRI.

The AHRI site enrolled 178 participants between December 2023 and March 2025, with the Johannesburg site enrolling the rest, for a total of 600.

Participants were randomised in a 1:1 ratio to receive either oral daily doravirine (TDF/3TC/DOR) or dolutegravir (TAF/FTC/DTG).

Weight gain differed significantly between the two study groups. Median weight gain at week 48 was 3.0 kg with doravirine (TDF/3TC/DOR) compared with 5.0 kg with dolutegravir (TAF/FTC/DTG).

Increases in total body fat percentage were also significantly lower with doravirine (TDF/3TC/DOR) at 1.5%, versus 2.2%.

“These results add some clarity to a challenge that has frustrated both doctors and patients for years: how to treat HIV effectively without causing significant weight gain,” says Lebina. “For many patients, especially black women who are disproportionately affected by treatment-associated weight gain, this could be a game changer. It offers an important new treatment option that supports long-term health while maintaining excellent HIV control.”

Non-inferior yet drug resistance potential

Woods emphasises that the efficacy of doravirine is dependent on patients’ absolute adherence to taking it. If doravirine is taken properly, HIV viral load will be suppressed. However, failure to adhere can cause drug resistance.

“Doravirine is non-inferior to dolutegravir in the sense that if you take the drug properly, you will suppress it [HIV viral load]. If you don’t take it properly, you will likely become resistant. That unfortunately is one of the downsides of using doravirine.”

In the Opti-DOR clinical trial, seven patients developed resistance to the drug. These participants were then switched over to dolutegravir and successfully suppressed again.

Woods emphasises that doravirine is unlikely to be a replacement for DTG: “It is not a replacement. It has to be targeted to patients who are at risk of gaining more weight – and complications thereof.”

Despite drug resistance, the data prove that doravirine is not inferior to dolutegravir and that it causes less weight gain.

Research into action

Doravarine is already an available and registered drug.

The researchers have alerted the South African National Department of Health and the South African Health Products Regulatory Authority.

“Imagine you’re a diabetic and you only have access to one drug? It’s the same thing with HIV. Yes, the drug they have at the moment is really top of the tops, but it doesn’t suit everybody. You have to have options. Until we can cure HIV, you’ve got to make it as easy as possible for people to take their treatment. That’s what it comes down to.”

Key findings of the Opti-DOR study at week 48

  • Doravirine [TDF/3TC/DOR] was non-inferior to dolutegravir [TAF/FTC/DTG] for viral suppression.
  • Viral suppression was achieved by 89.0% of participants on doravirine [TDF/3TC/DOR] and 90.7% on dolutegravir [TAF/ FTC/DTG].
  • Median weight gain was significantly lower with doravirine [TDF/3TC/DOR]: 3.0 kg versus 5.0 kg.
  • Total body fat percentage increased less with doravirine [TDF/3TC/DOR]: 1.5% versus 2.2%.
  • Lipid changes favoured doravirine [TDF/3TC/DOR].
  • Glycaemic measures and blood pressure were similar between arms.
  • No emergent integrase inhibitor resistance was observed.
  • Bone mineral density declined more with doravirine [TDF/3TC/DOR].
  • Serious adverse events and major laboratory abnormalities were infrequent across and similar between both groups, and not considered treatment related.

Read the full story from Wits University.

Cipla Announces Voluntary Licensing Agreement Relating to Investigational HIV Prevention Candidate

Photo by Sora Shimazaki

Through Cipla’s voluntary licensing agreement with Merck (MSD), Cipla may support potential future access to generic alimatravir, an investigational medicine being studied for HIV-1 pre-exposure prophylaxis (PrEP).

The announcement underscores Cipla’s role in supporting responsible partnerships at a critical moment for the global HIV response, as global leaders, researchers and healthcare professionals convene in Brazil this week for the world’s largest HIV and AIDS conference.

Through the agreement, Cipla may produce generic alimatravir following completion of development, applicable regulatory approvals, technology-transfer requirements and any other country-specific requirements. The voluntary licensing agreement builds on Cipla’s vertically integrated capabilities across the pharmaceutical value chain, enabling the company to support the development and manufacturing activities, under the terms of the agreement. 

As one of Africa’s leading pharmaceutical companies, Cipla has contributed to improving access to critical HIV medicines and prevention-related public-health programmes across the continent. In the early 2000s, Cipla made quality, affordable antiretrovirals available at less than $1 per day, contributing to wider access to HIV treatment during a critical period in the global HIV response.

Building on this legacy, Cipla continues to strengthen its contribution to public health through the development, manufacture and distribution of high-quality, affordable medicines that support national and regional HIV priorities, where such medicines are appropriately authorised and supplied in accordance with local requirements.

Paul Miller, CEO of Cipla Africa, said: “Cipla’s vision has always been to make quality healthcare more accessible for patients who need it most. This licensing agreement reflects our long-standing commitment to supporting responsible innovation in HIV prevention for the patients and communities we serve. We believe that expanding future access, where permitted by applicable regulatory requirements, requires extensive manufacturing expertise, reliable supply chains and strategic partnerships that can translate scientific innovations into real-world impact.”

Investment in Local Manufacturing, Sustainable Access

Cipla’s manufacturing network and established presence across African markets position the company to support widespread, sustainable access to HIV medicines. Through decades of experience in producing and supplying medicines at scale, Cipla has helped strengthen healthcare systems and HIV treatment programmes.

The company also remains committed to supporting local healthcare priorities by investing in local manufacturing capabilities and working collaboratively with governments and healthcare professionals to improve access to life-saving medicines. Cipla has been supplying the South African government with equitable access to HIV medication for a number of years.  These efforts align with broader ambitions to strengthen pharmaceutical manufacturing capacity on the continent, reinforcing Cipla’s commitment to secure and ensure reliable ARV supply.

Most recently for example, Cipla made significant investments in its local manufacturing facility, upgrading the capacity of the ARV production line with the installation of a new Countec bottle line and increased its tablet filing capacity by 190%. The company is able to locally produce 475 million ARV tablets annually and has upscaled its manufacturing capabilities to ensure sufficient capacity to meet current demand and support near‑term growth, ensuring continuity of supply. Cipla’s overall manufacturing capacity is 1,625 billion tablets annually.

“With a long history of leadership in HIV treatment and prevention, Cipla remains dedicated to helping shape a future where innovative healthcare solutions are accessible, affordable and available to communities across Africa. We want people to live a long and healthy life as part of our ethos of caring for life,” said Paul Miller, CEO of Cipla Africa.

*According to Statistics South Africa, the number of people living with HIV in the country is estimated to be approximately 8 million (12,7% of the population)[1].

Important regulatory notice: Alimatravir is an investigational medicine. It is not registered by the South African Health Products Regulatory Authority (SAHPRA), has not been approved for sale or supply in South Africa, and is not currently available in South Africa. Its safety, quality and efficacy have not been evaluated or approved by SAHPRA. This communication is a corporate announcement about a voluntary licensing agreement and is not intended to promote, recommend or encourage the use of any medicine.

Alimatravir remains investigational and no claims are made regarding its safety, efficacy or suitability. No availability in South Africa is implied by this announcement. Any future availability remains subject to successful completion of development, regulatory approval and applicable local authorization requirements.

[1] Source: https://www.gov.za/faq/health/where-can-i-find-latest-hiv-and-aids-statistics-south-africa