Dr Thembisile Xulu is the newly-appointed Director General of the National Department of Health. (Photo: Denvor de Wee/Spotlight)
By Marcus Low
Dr Thembisile Xulu is South Africa’s sixth permanent Director-General of health since the dawn of democracy. How will she measure up against her predecessors?
In recent months, we’ve been keeping an especially close eye on the media statements following the twice-monthly meetings of South Africa’s cabinet. Then last week, we finally spotted the line we had been waiting for – the announcement of South Africa’s new Director-General (DG) for Health.
The name of the country’s sixth permanent DG since 1994 was a familiar one. Back in 2020, Spotlight interviewed Dr Thembisile Xulu when she was appointed CEO of the South African National AIDS Council (SANAC) – the national body established by Cabinet to coordinate South Africa’s response to HIV, Tuberculosis, and Sexually Transmitted Infections.
In moving from the job of SANAC CEO to health DG, Xulu follows in the footsteps of Dr Sandile Buthelezi, who was CEO of SANAC from 2017 to 2020 and DG for Health from 2020 to early 2026, when he was suspended along with two other senior officials in the department.
Prior to her time at SANAC, Xulu worked at the non-profit Right to Care for around a decade and a half. She is a medical doctor and has a master’s degree in public health. As far as we can tell, she is well liked in healthcare circles.
A huge task
The job facing Xulu is a daunting one.
First, she will have to sort out problems within the department itself. As we pointed out in an editorial published in April, the department hasn’t gotten a clean audit in any of the last five years. The Digital Vibes scandal and the suspension of several senior officials earlier this year relating to another matter paints a bleak picture. While we know there are several committed and capable people working in the department, organisationally it seems to be exhibiting all the classic signs of chronic dysfunction and a lack of effective leadership.
Maybe the most urgent task facing Xulu then is simply to turn the health department into a more professional organisation. This will require strong leadership and management skills, but it will also require her to more effectively protect the department from whatever the political whims of the day may be. Ultimately, a DG that always says, “yes Minister”, isn’t actually doing the Minister, or the public, any favours.
But it won’t be easy. When the DG job was advertised back in March, the advert did not open by referencing the Constitution or the National Health Act, as one might expect, but by stating that the DG will be responsible for implementing the Presidential Social Compact for transformation of the health sector. The last health compact, signed in 2024, was a controversial document that did not get buy-in from several key business and healthcare worker organisations. That the job advert starts by referencing the compact rather than the relevant laws, seems an ominous sign for the DG’s chances of building a more capable, less politicised, department.
Second, getting the department’s house in better order will help with what is of course Xulu’s main job – helping to address the country’s many health challenges. Top of the list is the chronic shortages of healthcare workers in the public sector. We have seen an important policy document and some extra funds for healthcare workers, but the incisive leadership and sustained commitment and planning needed to really get on top of the problem has been absent.
There is a worrying pattern whereby government looks into a problem, maybe a committee of some sort is set up, the intentions are all good, but then everything stalls once some implementation challenge or political complication arises. We need a DG who does not allow important health issues to drift in this way, but who has the focus and determination to find workable solutions and to see them through.
And then there is NHI
The NHI Act might currently be tangled up in a thicket of litigation, but whatever happens in the courts, NHI will be a big part of the DG’s work in the coming years (DGs are appointed for five years at a time). This may take the form of implementing some elements of the current NHI Act, or working with a revised Act, we just don’t know at this stage.
But there will be many other bread and butter issues besides NHI demanding Xulu’s attention. In our analysis, the department has badly dropped the ball on urgent issues such as healthcare worker shortages, the regulation of private healthcare, and improving the quality of public healthcare services in areas such as mental health, diabetes, and hypertension. Hopefully under the new DG, the department will find ways of better addressing these issues in parallel with its work on NHI.
A chance at renewal
There is some reason for optimism. With the appointment of Xulu as DG, and that of Dr Nonhlanhla Ndlovu before that as the department’s HIV czar, new people are now in two of the most important positions in the department. Such leadership changes offer a unique opportunity for organisational renewal.
Spotlight has requested an interview with Xulu and we hope to get some time with her once she’s been in the job for a few weeks. We will ask her the tough questions, but we will also be fair and give her time. After all, we all want to see a health department and a health system that works.
Specially trained pharmacists will be allowed to dispense HIV treatment and prevention medicines without a doctor’s script. (Photo: Unsplash)
By Catherine Tomlinson for Spotlight
Ten months after an enabling court judgment, some pharmacists in South Africa can finally start applying for permits that allows them to dispense HIV prevention pills without a script from a doctor.
Specially trained pharmacists can now begin applying for permits to dispense antiretroviral medicines for HIV prevention without a doctor’s prescription. The long-awaited permitting process was announced to pharmacists in a South African Pharmacy Council (SAPC) e-Note on 13 August.
PIMART is a form of task-shifting that allows pharmacists to provide some limited HIV services that are currently only provided by doctors and nurses.
It is intended that, under the PIMART programme, pharmacists that have completed a dedicated training programme and have received a special permit from the Director-General of Health will be authorised to provide first-line antiretroviral treatment to people with uncomplicated HIV without a doctor’s script.
They will also be allowed to dispense HIV prevention medicines without a doctor’s script – this includes both pre-exposure prophylaxis (PrEP) and post-exposure prophylaxis (PEP). PrEP is taken prior to sex to prevent potential infection while PEP is taken shortly after a possible HIV exposure to prevent infection.
PIMART’s long road to implementation
The SAPC first proposed PIMART to the health department in 2018. The proposal was in response to a request from the department for pharmacists to take on a larger role in the country’s HIV response.
In 2021, Spotlight reported the imminent launch of PIMART services in South Africa’s pharmacies, but then a court challenge against PIMART by a group of general practitioners blocked the programme’s implementation.
Four years later, in October 2025, a ruling by the Supreme Court of Appeal finally cleared the way for SAPC to launch PIMART. Following the court ruling, Vincent Tlala, CEO and Registrar of the SAPC, told media that the SAPC would issue a memo in November 2025 inviting pharmacists to apply for PIMART permits. But this would in fact only materialise in August 2026.
The SAPC’s 13 August memo to pharmacists, said that certain pharmacists can now begin to apply for temporary PIMART permits to provide PEP, PrEP, and HIV testing services – but not yet HIV treatment services. The temporary permits will be valid for 24 months.
Also, only pharmacists that completed the South African HIV Clinicians Society’s (SAHCS) previous PIMART training course can apply for the limited-scope, temporary PIMART permits.
Pharmacists that have not completed this course will have to wait for a new training course to be accredited and launched before they can apply for permits to provide PIMART services.
How long will it take to get a permit?
Tlala told Spotlight that the granting of the limited-scope, temporary PIMART permits by the Director-General and their recording by the SAPC may take a few months.
“The Department of Health processes applications for permits within 90 days (maximum),” said Tlala, adding that “[t]he PIMART permit recording process with the South African Pharmacy Council then takes between 72 working hours and 14 days, depending on the completeness of the application.”
The permits will only be granted to pharmacists who have already completed the Southern African HIV Clinicians Society’s (SAHCS) continuous professional development (CPD) PIMART course. Pharmacists that did not complete this course will need to wait for an updated PIMART course to become available before they can undertake the required training to be permitted.
Fiona Story, CEO of SAHCS, told Spotlight that nearly 800 pharmacists have completed the course.
Taken together, all of this suggests that toward the end of the year, a few hundred pharmacists in South Africa might be dispensing HIV prevention medicines without doctors’ scripts.
When will the updated training course be available?
Currently, there is no PIMART training course available for pharmacists, as the previous PIMART training course provided by SAHCS is on pause, while the updated course awaits accreditation. Based on dates provided by SAHCS, the updated course might only be available early next year.
However, once the updated course is available, it is anticipated that pharmacists that complete it will be able to apply for full-scope PIMART permits that allow them to dispense first-line antiretrovirals to people with uncomplicated HIV without a doctor’s script, in addition to PEP and PrEP.
“The CPD-accredited PIMART course is no longer available as it was reviewed and updated in line with the requirements for accreditation as a supplementary training course,” Story told Spotlight.
She said that the SAHCS is seeking accreditation of its updated PIMART training course from the SAPC. “SAHCS anticipates the PIMART supplementary training course accreditation process will conclude before the end of 2026,” said Story. She added: “SAHCS has prepared to launch the PIMART supplementary training course as soon as accreditation has been received.”
When will pharmacists be able to dispense HIV treatment without a doctor’s script?
The timeline for when pharmacists will be able to provide the full scope of services intended under PIMART, including HIV treatment for uncomplicated cases, remains unclear. Before this can happen, the SAPC must accredit the SAHCS’ updated supplementary training course and the SAHCS must launch this course.
After this, the permits granted to pharmacists by the Director-General will need to be expanded to include the provision of first-line antiretroviral therapy for treatment of uncomplicated HIV.
In the meantime, the around 800 pharmacists who completed the SAHCS’s previous PIMART training course can now start applying for permits to provide PrEP, PEP, and HIV testing services.
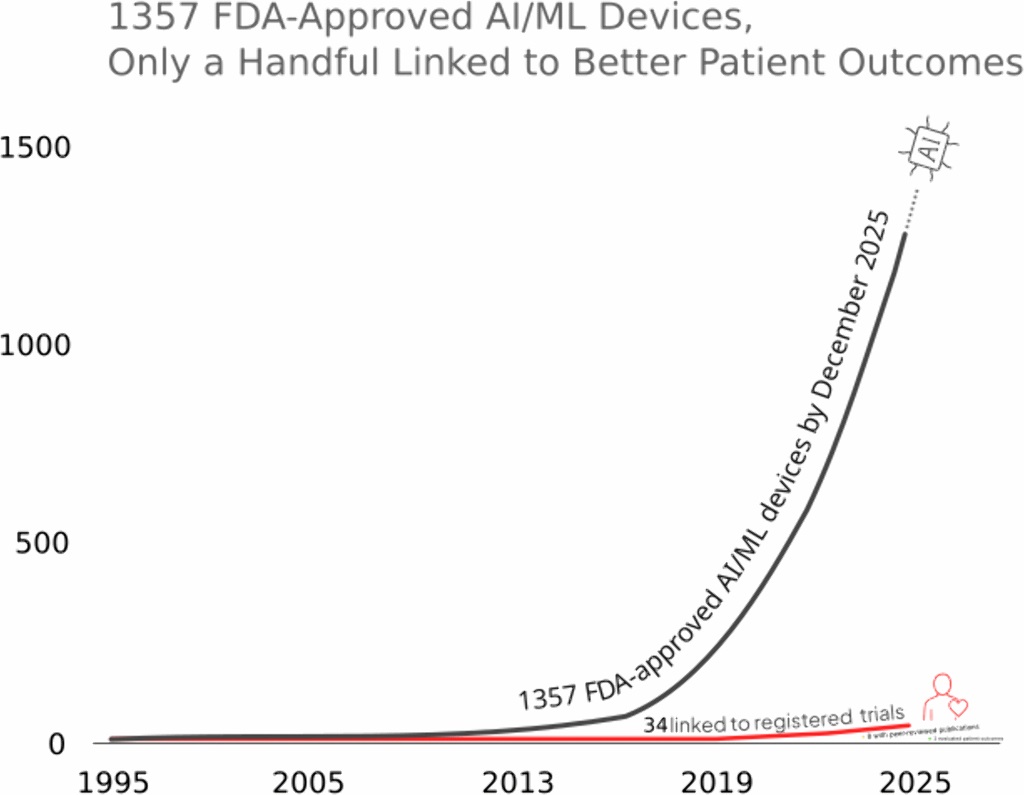
Of 1357 devices authorised by the US FDA, only 3 were evaluated on clinical effectiveness
Growth of FDA-cleared AI/ML-enabled medical devices from 1995 to December 2025. Of 1,357 cleared devices, only 34 were linked to registered clinical trials and only 3 were evaluated for patient-centred outcomes. (Fig 1 of the article.), Credit: Abulibdeh R, Cajas Ordóñez SA, Celi LA, Gorijavolu R, Izath N, Markussen Lunde T, 2026, PLOS Digital Health, CC-BY 4.0 (https://creativecommons.org/licenses/by/4.0/)
A new analysis shows that, of 1357 artificial intelligence (AI)-based medical devices authorised by the US Food and Drug Administration (FDA) for use in patient care, only three had been tested on whether they actually improve patients’ health. Rawan Abulibdeh of the University of Toronto, Canada, and colleagues present these findings in the open access journal PLOS Digital Health on August 19, 2026.
New AI devices increasingly inform clinical care, such as systems that aid surgical planning, calculate cardiovascular risks, and guide interpretation of mammograms and other imaging. In order to be authorised for use in the US, AI devices typically only need to show “substantial equivalence” to an existing authorised device, and developers are not required to demonstrate whether new AI devices help people live healthier lives – with benefits shared equitably across diverse subgroups.
To deepen understanding of this topic, Abulibdeh and colleagues investigated how all 1357 AI devices authorised by the FDA as of December 5, 2025, had been evaluated in patients prior to authorization.
They found that only 34 of the devices had been included in registered clinical trials, with results posted for 12 and peer-reviewed manuscripts published for 12. Only 3 devices had been tested on patient-centred outcomes, such as death rates, strokes, hospitalizations, and quality of life. Most studies were conducted in highly resourced healthcare systems, and most excluded key patient subgroups, such as pregnant women, adults over 75, and non-English speakers.
The researchers suggest that structural barriers such as financial incentives and logistical challenges discourage developers from testing AI devices on patient outcomes, resulting in greater emphasis on speedy development than on rigor. They discuss how this framework could allow new tools to amplify existing disparities in healthcare and how it could lead to patients in low- and middle-income countries becoming inadvertent test populations for under-studied AI devices, as many countries rely on higher-income countries’ authorisation decisions.
On the basis of their findings, the researchers conclude that existing policies for AI medical device authorization should be redesigned. They propose a novel, three-phase framework that includes demonstration of effectiveness across diverse patient subgroups and healthcare settings.
The authors add: “We expected the evidence base to be thin, but not this thin. Out of 1357 AI devices the FDA has cleared for use in patient care, only three have been tested on whether patients actually live longer or better. Clearance tells you a device resembles something already on the market. It does not tell you it helps anyone.”
#InsideTheBox is a column by Dr Andy Gray, a pharmaceutical sciences expert at the University of KwaZulu-Natal and Co-Director of the WHO Collaborating Centre on Pharmaceutical Policy and Evidence Based Practice. (Photo: Supplied)
By Dr Andy Gray for Spotlight
The regulation of complementary and alternative medicines in South Africa has been hotly contested in recent decades, including in court rooms. In his latest column for Spotlight, Dr Andy Gray unpacks the legal background and the current state of this still unfolding regulatory saga.
Multivitamin and mineral supplements are commonly found in many South African retail outlets, from pharmacies to health shops and supermarkets. Some outlets will stock a wider range of medicines, perhaps on shelves marked as “complementary”, or among other non-prescription medicines available for self-service.
Are these medicines regulated in the same way as other medicines, including those available on prescription?
The concept of a “call-up notice”
When South Africa’s medicines legislation was first passed in 1965, there were already many medicines on the local market which had not been assessed for safety, efficacy or quality. As all such medicines could not be immediately “called up” for registration, a stepwise approach had to be followed.
Between 1967 and the mid-1980s, medicines were identified for registration by pharmacological classification. The remnant of that approach is still evident in section 14(1) and (2): of the Medicines and Related Substances Act, 1965:
(1) Save as provided in this section or sections 21 and 22A, no person shall sell any medicine, … which is subject to registration by virtue of a declaration published in terms of subsection (2) unless it is registered.
(2) (a) The Authority may from time to time determine that a medicine, …, or class or category of medicine, … or part of any class or category of medicine, … mentioned in the declaration, shall be subject to registration in terms of this Act.
(b) Any such declaration may also relate only to medicines, … which were available for sale in the Republic immediately prior to the date on which it comes into operation in terms of paragraph (c) or only to medicines, … which were not then so available.
The declaration that a category or class of medicine is subject to registration is referred to colloquially as a “call-up notice”. A notice could be applied to those medicines already marketed, or only to those not yet marketed. Medicines which were already marketed but exempted from a full registration process were then regulated as “old medicines”. They are still subject to control according to their scheduling status and their production still needs to be in accordance with Good Manufacturing Practice. In time, new brands of some of the “old medicines” have been registered.
By the mid-1980s, the process of working through the pharmacological classifications was concluded. Thereafter, every new medicine would need to be registered before being marketed. In other words, a manufacturer or importer would need to provide sufficient evidence of the medicine’s safety, efficacy and quality to justify registration.
However, an important exception was created in 1986, which exempted homeopathic medicines from the full registration process. Two important restrictions were included. Firstly, no medical claims could be made for the medicine. Secondly, the following wording was to be included on the label of such medicine: “Homeopathic Medicine” and “WARNING: Use only as directed by a medical practitioner, pharmacist or homeopath”. The provision applied to homeopathic mother substances and so-called “minute-dose forms” made in accordance with homeopathic principles.
Broadening the scope of complementary medicines
Homeopaths are one of several complementary and traditional health professions regulated by the Allied Health Professions Council of South Africa. Medicines legislation has been amended to accommodate this wider range of complementary and traditional medicines.
A separate South African Health Products Regulatory Authority (SAHPRA) web site is dedicated to what are termed Category D medicines, also known as complementary medicines.
The General Regulations issued in terms of the Medicines Act includes a definition of complementary medicines which has two components: health supplements and medicines used in accordance with a “discipline as determined by the Authority”. The pharmacological classifications listed in Annexures 1 (human) and 2 (veterinary) medicines list the “disciplines” as Aromatherapy, Homeopathy, Phytotherapy, Traditional Chinese Medicine, Unani Medicine, Western Herbal Medicine, Combination Products and Other Herbal. The Annexures also list the types of health supplements, including amino acids, mineral, probiotics and vitamins. Two elements are important here – the nature of the substance included in the complementary medicine and the claims made in relation to that medicine.
Since 2013, the intention has been to progressively bring all complementary medicines under effective regulation, using a risk-based approach to identify those requiring registration and full assessment of safety, efficacy and quality data. The first pharmacological classifications identified were those claiming antiviral properties, and those intended to treat diabetes, cardiac conditions and cancer. However, no complementary medicines have yet been registered and the initial “call-up notices” have been repealed.
Like much of South Africa’s medicines regulatory space, this process has been affected by litigation. A challenge of the complementary medicines regulatory scheme by the Alliance of Natural Health Products (South Africa) was finally decided by the Supreme Court of Appeal in 2022. The court confirmed the finding that SAHPRA should have no regulatory power over substances and preparations that did not meet the definition of a medicine. A preparation that seeks to supplement a diet or provide a nutritional benefit is not a medicine, but a foodstuff. Draft amendments to the 2017 General Regulations, informed by the court judgment, were published for comment in March 2023, but have yet to be issued in final form.
Not a total lack of regulation
The hiatus in finalising regulations does not mean, however, that there is no regulatory control over complementary or Category D medicines. The initial “roadmap” outlined in the 2013 regulations has been replaced by a series of guidelines. The progressive, developmental approach to the regulation of complementary medicines remains in place, albeit delayed and as yet incomplete.
The overall roadmap was updated in 2021. All manufacturers, wholesalers or distributors of complementary medicines are required to be licensed by SAHPRA, but this process relies on an applicant’s “attestation of compliance with minimum requirements at the time of application and the payment of the required licence application, and desktop evaluation fees”, rather than the full Good Manufacturing Practice inspection applied to manufacturers of other medicines. However, SAHPRA reserves the right to conduct inspections where warranted. A similar approach is applied to the regulation of medical devices and diagnostic tests.
In the meantime, while no complementary or alternative medicines have been registered by SAHPRA, there is relatively strict regulation of what companies can say about the unregistered complementary medicines that they market in South Africa.
As with the 1986 exclusion for homeopathic products, all category D products which have not been registered have to include the following statement on the label: “This unregistered medicine has not been evaluated by the SAHPRA for its quality, safety or intended use”. The guideline also distinguishes between low risk and high-risk claims, in either labelling or advertising. Low risk claims are those for general health enhancement without any reference to specific diseases; health maintenance; or the relief of minor symptoms (not related to a disease or disorder).
The guideline is specific about a widely used wording: “Unregistered complementary medicines making use of the terms “Clinically proven” or any similar expression … shall also be considered to be HIGH RISK and may be subject to individual call-up in terms of section 14(2) of the Medicines Act.” Examples of acceptable low risk claims are provided, such as “Helps enhance/promote joint health”. Further guidance on the evidence to be relied upon for low risk and high-risk claims has been provided for the discipline-specific complementary medicines.
Manufacturers and importers of health supplements are only allowed to make low risk claims, and the relevant guideline provides Annexures (from Annexure A to O), showing the allowable levels and claims for each type of supplement. For example, a single component vitamin B3 (nicotinamide) product sold for adults may not contain more than 500mg per dose, and can only make a claim of “Helps to metabolise carbohydrates, fats and proteins”, “Contributes to normal growth and development” or “A factor in the maintenance of good health”.
A key document is the current guideline on the regulation of discipline-specific complementary medicines. An additional guideline was updated in 2022, which provides guidance on caffeine, menthol, camphor and cannabidiol. Low-dose cannabidiol can be sold as either a discipline-specific complementary medicine or a health supplement. At a dose not exceeding 20mg per day or 600mg per pack, it can be sold as a Schedule 0 product.
As no complementary medicines have yet been registered, none have as yet been specifically included in any of the Schedules, and they are therefore assumed to be controlled as Schedule 0 products, which can be sold in any retail outlet. One exception would be any injectable product, as those are automatically included in Schedule 3 and are prescription-only.
Important sources of information
The SAHPRA complementary medicines website provides a crucial resource which can be accessed by the public. The list of licensed complementary medicines manufacturers, importers and exporters is accessible here. There are currently 117 entries on the list. Each entry also provides a list of the products provided by that licensed entity, with details of ingredients, recommended doses and intended uses, whether discipline-specific or health supplement. The entire database is also searchable.
The site also enables anyone to lodge a complaint about a complementary medicine, including anonymous complaints.
Gaps in the system
While some progress has been made, the regulatory scheme for complementary medicines remains incomplete. Apart from finalising the regulations after the court challenge, a risk-based “call-up” process still needs to commence. Moving from an attestation process to confirmation that every manufacturer has met current Good Manufacturing Practice standards is still necessary.
Currently, the proprietary (brand) names used for complementary medicines are not pre-approved by SAHPRA, and many are in contravention of the naming guidelines applied to other medicines.
Effective oversight of advertising and marketing practices remains elusive, not only in respect of complementary medicines.
The dictum traditionally applied to consumer goods of “let the buyer beware” (in Latin, “caveat emptor”) is no longer considered appropriate. The Consumer Protection Act, 2008 seeks to protect the public against unsafe products and unfair marketing. Medicines are treated as a special category of goods, deserving closer regulatory control. The remaining gaps in the medicines regulatory system need to be plugged. One very particular gap, which has never been adequately addressed, is the regulation of African traditional medicines, which are not currently captured in the definition of Category D medicines.
– Gray is a Senior Lecturer at the University of KwaZulu-Natal and Co-Director of the WHO Collaborating Centre on Pharmaceutical Policy and Evidence Based Practice.
Disclosure: Gray serves on three technical advisory committees at the South African Health Products Regulatory Authority.
Through Cipla’s voluntary licensing agreement with Merck (MSD), Cipla may support potential future access to generic alimatravir, an investigational medicine being studied for HIV-1 pre-exposure prophylaxis (PrEP).
The announcement underscores Cipla’s role in supporting responsible partnerships at a critical moment for the global HIV response, as global leaders, researchers and healthcare professionals convene in Brazil this week for the world’s largest HIV and AIDS conference.
Through the agreement, Cipla may produce generic alimatravir following completion of development, applicable regulatory approvals, technology-transfer requirements and any other country-specific requirements. The voluntary licensing agreement builds on Cipla’s vertically integrated capabilities across the pharmaceutical value chain, enabling the company to support the development and manufacturing activities, under the terms of the agreement.
As one of Africa’s leading pharmaceutical companies, Cipla has contributed to improving access to critical HIV medicines and prevention-related public-health programmes across the continent. In the early 2000s, Cipla made quality, affordable antiretrovirals available at less than $1 per day, contributing to wider access to HIV treatment during a critical period in the global HIV response.
Building on this legacy, Cipla continues to strengthen its contribution to public health through the development, manufacture and distribution of high-quality, affordable medicines that support national and regional HIV priorities, where such medicines are appropriately authorised and supplied in accordance with local requirements.
Paul Miller, CEO of Cipla Africa, said: “Cipla’s vision has always been to make quality healthcare more accessible for patients who need it most. This licensing agreement reflects our long-standing commitment to supporting responsible innovation in HIV prevention for the patients and communities we serve. We believe that expanding future access, where permitted by applicable regulatory requirements, requires extensive manufacturing expertise, reliable supply chains and strategic partnerships that can translate scientific innovations into real-world impact.”
Investment in Local Manufacturing, Sustainable Access
Cipla’s manufacturing network and established presence across African markets position the company to support widespread, sustainable access to HIV medicines. Through decades of experience in producing and supplying medicines at scale, Cipla has helped strengthen healthcare systems and HIV treatment programmes.
The company also remains committed to supporting local healthcare priorities by investing in local manufacturing capabilities and working collaboratively with governments and healthcare professionals to improve access to life-saving medicines. Cipla has been supplying the South African government with equitable access to HIV medication for a number of years. These efforts align with broader ambitions to strengthen pharmaceutical manufacturing capacity on the continent, reinforcing Cipla’s commitment to secure and ensure reliable ARV supply.
Most recently for example, Cipla made significant investments in its local manufacturing facility, upgrading the capacity of the ARV production line with the installation of a new Countec bottle line and increased its tablet filing capacity by 190%. The company is able to locally produce 475 million ARV tablets annually and has upscaled its manufacturing capabilities to ensure sufficient capacity to meet current demand and support near‑term growth, ensuring continuity of supply. Cipla’s overall manufacturing capacity is 1,625 billion tablets annually.
“With a long history of leadership in HIV treatment and prevention, Cipla remains dedicated to helping shape a future where innovative healthcare solutions are accessible, affordable and available to communities across Africa. We want people to live a long and healthy life as part of our ethos of caring for life,” said Paul Miller, CEO of Cipla Africa.
*According to Statistics South Africa, the number of people living with HIV in the country is estimated to be approximately 8 million (12,7% of the population)[1].
Important regulatory notice: Alimatravir is an investigational medicine. It is not registered by the South African Health Products Regulatory Authority (SAHPRA), has not been approved for sale or supply in South Africa, and is not currently available in South Africa. Its safety, quality and efficacy have not been evaluated or approved by SAHPRA. This communication is a corporate announcement about a voluntary licensing agreement and is not intended to promote, recommend or encourage the use of any medicine.
Alimatravir remains investigational and no claims are made regarding its safety, efficacy or suitability. No availability in South Africa is implied by this announcement. Any future availability remains subject to successful completion of development, regulatory approval and applicable local authorization requirements.
The South African Health Products Regulatory Authority, with the South African Pharmacy Council, recently announced what was described as a crackdown on a compounding pharmacy. They allege “critical regulatory non-compliance” in relation to the compounding of unregistered medicines. In his latest Inside The Box column, Dr Andy Gray provides some background to the issues at stake, while recognising that some key elements remain contested.
Until the 20th century, medicines dispensed by pharmacists were all compounded (mixed) from raw ingredients, most of which were inorganic chemicals and herbal products. The gilded majolica jars displayed in pharmacies and museums depict the names of those common ingredients, often in Latin. Hence, a jar labelled as “Paraf mol alb” would contain “paraffinum molle album”, or white soft paraffin (white petroleum jelly), more commonly known as Vaseline.
The market for finished pharmaceutical products, in the form of modern tablets, capsules and the like, has grown dramatically over the last century. Even so, the need for the preparation of medicines in a pharmacy, from either raw ingredients or existing products, has not entirely disappeared.
#InsideTheBox is a column by Dr Andy Gray, a pharmaceutical sciences expert at the University of KwaZulu-Natal and Co-Director of the WHO Collaborating Centre on Pharmaceutical Policy and Evidence Based Practice. (Photo: Supplied)
There has always been a need for the preparation of particular products for individual patients in cases where a commercial product does not exist or is not suitable. For example, a pharmacist may be asked to produce an eye drop when no commercial products exist, using an injection as the starting material. Similarly, where a patient is unable to swallow tablets or capsules, an oral liquid preparation may be compounded. In many cases, the preparation is done extemporaneously, meaning that it is done specifically for that patient at a point in time. Such medicines are compounded by pharmacists as part of their usual professional practice in community and hospital pharmacies.
Exceptions, limitations and contestation
Modern medicines regulatory practice is based on the concept of registration or marketing authorisation. This is where a manufacturer is required to provide evidence to the national medicines regulatory authority of the quality, safety and efficacy of a medicine, before it can be sold. However, an exception has been created, allowing for compounding of medicines. In the South African medicines legislation, this is provided by section 14(4) of the Medicines and Related Substances Act (Act 101 of 1965).
The usual approach is described in section 14(1) of the Act, which states that “no person shall sell any medicine … which is subject to registration by virtue of a declaration published in terms of subsection (2) unless it is registered”. The declaration in this regard refers to the call-up notices issued for different pharmacological classifications of medicines since 1967, when the Act came into operation. All pharmacological classifications have now been made subject to registration.
The exception is provided by section 14(4), which states that subsection 14(1) will not apply when a medicine is “compounded in the course of carrying on his or her professional activities by a pharmacist”. A similar exception applies to licensed dispensing and compounding practitioners and veterinarians. Two scenarios are envisaged: compounding a preparation in accordance with a prescription for a particular patient, or compounding by a pharmacist for the retail trade.
However, there are three critical additional restrictions: a compounded medicines shall “not contain any component the sale of which is prohibited by this Act or any component in respect of which an application for registration has been rejected”, the compounded medicine “is not or has not been advertised”, and the “the active components of such medicine appear in another medicine which has been registered”. Thus, unless declared undesirable or never before registered, an active ingredient may be compounded and sold without being registered. A compounded medicine may also not be advertised to the public or to health professionals.
Further details were provided by the General Regulations to the Medicines and Related Substances Act, which were published in 2017. The initial version of those regulations added some additional restrictions, for example restricting the quantity to be compounded to the “quantity that is intended to be used by a patient for not more than 30 consecutive days from the date of compounding”. More importantly, sub-regulation 3(3)(a) prohibited compounding that was intended “to circumvent the provisions of section 14 of the Act”, the requirement for registration.
Legal challenge
In December 2021, the North Gauteng High Court in Pretoria ruled in a case brought by The Association of Compounding Pharmacists of South Africa, challenging the regulations. While noting that “[w]hat constitutes pharmacy compounding is not well defined”, Judge Norman Manoim ordered that the regulations be redrafted and that a draft guideline on good compounding practice be published. In particular, the judgment recognised the need to clarify what was needed for “anticipatory compounding”, where medicines were compounded in anticipation of a prescription or for sale by a pharmacist.
In accordance with the court judgment, amended regulations were published for comment and finalised in 2022, deleting sub-regulation 3(3)(a), and recognising that a pharmacist could “based on the amount of medicine compounded previously for a particular period, compound such medicine in anticipation of supply thereof within such particular period”. Lastly, the regulations required that draft guidelines on good compounding practice be published within 6 months, for public comment. These draft guidelines were published for comment in June 2023, but have not been issued in final form. The draft guidelines are no longer accessible on the South African Health Products Regulatory Authority (SAHPRA) website.
Compounding pharmacies
While the extemporaneous compounding of medicines for individual patients is routinely performed in most community and hospital pharmacies, “anticipatory compounding” has emerged as a speciality practice.
Compounding pharmacies are not recognised as a specific category of pharmacies licensed by the Department of Health and recorded as such by the South African Pharmacy Council (SAPC). The current regulations to the Pharmacy Act only recognise community, institutional (hospital), wholesale, manufacturing and consultant pharmacies. The services that each category of pharmacy can deliver are regulated, with both community and institutional pharmacies enabled to perform “compounding, manipulation or preparation of any medicine or scheduled substance”. Specialist compounding pharmacies are thus licensed as community pharmacies.
SAHPRA licenses manufacturers and wholesalers of medicines, not community pharmacies. Section 22C(1)(b) of the Medicines and Related Substances Act states that the Authority “may … issue to a … manufacturer, wholesaler or distributor of a medicine … a licence to manufacture, import, export, act as a wholesaler of or distribute, as the case may be, such medicine … upon such conditions as to the application of such acceptable quality assurance principles and good manufacturing and distribution practices as the Authority may determine”.
Whether a compounding pharmacy, licensed as a community pharmacy, can import active pharmaceutical ingredients (APIs) for the purposes of compounding, is contested. It is the API which is responsible for the desired medicinal effect but can also be the cause of adverse events. Inactive excipients are added to produce the final dosage form administered to patients.
The question of quality
As was outlined in a previous column in this series, patients are assured of the quality of medicines on the South African market by virtue of their registration by SAHPRA and compliance with Good Manufacturing Practice (GMP) standards by licensed manufacturers. Compounded medicines are an exception to the rule – they are unregistered, and their preparation is not subject to GMP.
In the case of medicines compounded for individual patients, the risk is more manageable. Where larger quantities are prepared in anticipation of demand, and in particular where sterile preparations such as injections are made, the risks may be greater.
Equally, there is a need to ensure that APIs used for manufacturing or compounding medicines are of acceptable quality. A draft guideline on post-importation testing, published by SAHPRA for comment in May 2026, applies to all imported APIs.
Following a major incident in the United States, where contaminated compounded corticosteroid injections resulted in a number of serious fungal infections, US law was amended in 2013 to create a new category of outsourcing facilities regulated by the Food and Drug Administration (FDA), not by state pharmacy boards. State pharmacy boards were not considered to have the capacity to effectively regulate large scale compounding, especially for higher risk sterile preparations.
In South Africa, while the Good Pharmacy Practice standards issued by the SAPC cover the usual services delivered by community and hospital pharmacies, they are insufficient to cover larger scale anticipatory compounding or outsourcing services.
Ongoing contestation
Existing South African law may well be deficient in the way in which it regulates compounding pharmacies. How the current legal provisions are applied and interpreted is contested and will be the subject of a number of court challenges.
Patient safety must remain the key animating feature of any future regulatory process that is fit for purpose and effective.
*Dr Gray is a Senior Lecturer at the University of KwaZulu-Natal and Co-Director of the WHO Collaborating Centre on Pharmaceutical Policy and Evidence Based Practice. This is part of a series of columns he is writing for Spotlight.
Disclosure: Gray serves on three technical advisory committees at the South African Health Products Regulatory Authority.
Note: Spotlight aims to deepen public understanding of important health issues by publishing a variety of views on its opinion pages. The views expressed in this article are not necessarily shared by the Spotlight editors.
Specially trained pharmacists will soon be allowed to dispense antiretrovirals without a doctor’s script. Photo by National Cancer Institute on Unsplash
By Catherine Tomlinson
A Supreme Court of Appeal ruling in October 2025 cleared the way for specially trained and permitted pharmacists to dispense antiretroviral medicines without a doctor’s script. Seven months later, no pharmacists are yet providing these services. Spotlight explores the reasons for the delay.
After a three-and a half year court battle between a group of private doctors and the South African Pharmacy Council (SAPC), the Supreme Court of Appeal (SCA) cleared the way for the SAPC to implement pharmacist-initiated management of antiretroviral treatment (PIMART) in October 2025.
The SAPC welcomed the ruling with a bullish press conference promising rapid implementation of PIMART. “The South African Pharmacy Council, together with stakeholders and the Department of Health, will work with speed to ensure that PIMART-trained pharmacists join other primary healthcare practitioners in providing primary care in relation to HIV and Aids,” said Mogologolo Phasha, president of the SAPC, at the time.
Vincent Tlala, CEO and Registrar of the SAPC, also in October 2025, said that the SAPC aimed to issue an e-note inviting pharmacists to apply for the PIMART permits in November. However, seven months later, this has still not happened and no pharmacists in the country are yet permitted to provide PIMART services.
What is PIMART?
PIMART stands for pharmacist-initiated management of antiretroviral treatment. It is a form of task-shifting that allows pharmacists to provide some limited HIV services that are currently only provided by doctors and nurses. The programme seeks to better utilise pharmacists in the country’s HIV response and relieve some of the burden on overcrowded and under resourced public clinics. It will also offer a route into treatment for people who are not willing or able to visit clinics.
It is intended that, under the PIMART programme, pharmacists that have completed a dedicated training programme and have received a special permit from the Director-General of Health will be authorised to provide first-line antiretroviral treatment to people with uncomplicated HIV without a doctor’s script. They will also be allowed to dispense HIV prevention medicines without a doctor’s script – this includes both pre-exposure prophylaxis (PrEP) and post-exposure prophylaxis (PEP). PrEP is taken prior to sex to prevent potential infection while PEP is taken shortly after a possible HIV exposure to prevent infection.
Why is PIMART needed?
PIMART was proposed by the SAPC in response to a request from the health department for the SAPC to design an intervention to enable pharmacists to take on a greater role in the country’s HIV response.
South Africa has adopted the UNAIDS 95-95-95 targets that aim to ensure that 95% of people living with HIV know their status, 95% of people diagnosed with HIV are on treatment, and 95% of people on treatment are virally suppressed (and therefore cannot transmit HIV onwards).
According to new estimates from Thembisa, the leading mathematical model of South Africa’s HIV epidemic, 7.9 million people are living with HIV in South Africa. Ninety six percent of people living with HIV know their status, yet only 82% of people who know they are HIV positive are on antiretroviral treatment.
While South Africa’s health system should be commended for the fact that around 6.2 million people are taking HIV treatment, it is concerning that 1.7 million people living with HIV are not yet on treatment. In recognition of this problem, the health department has launched the “Close the Gap” campaign.
The thinking behind PIMART is that pharmacies can help close the gap by providing an important third option to people who are disinclined or unable to access HIV treatment from public clinics or private sector doctors.
More urgent than ever following US funding cuts
While PIMART was always intended to help identify patients falling through the gaps between South Africa’s public and private health sectors and to link them to care, the need for this third option is now more urgent than ever. US funding cuts over the last 15 months or so have led to the closure of many NGO-run clinics that previously provided HIV treatment and prevention services to populations at high risk of HIV who often face stigma at traditional health facilities. These groups include sex workers, men who have sex with men, and people who inject drugs.
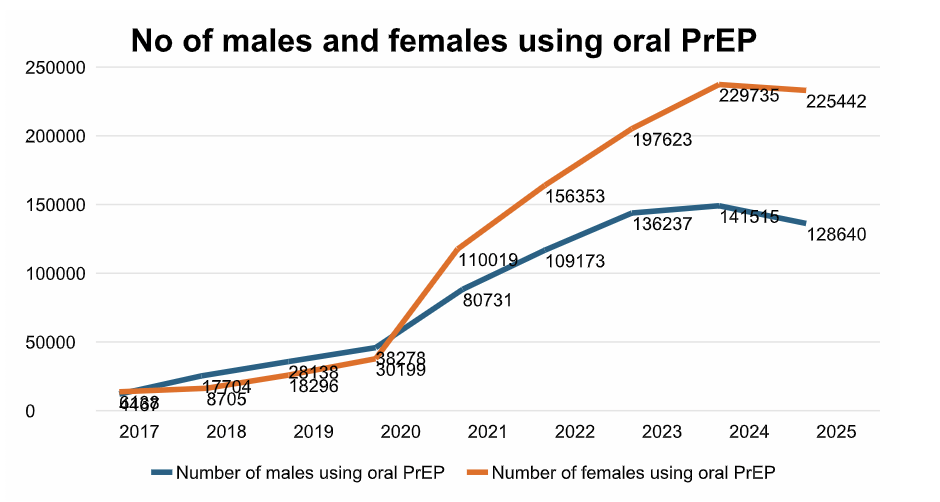
In addition to expanding access to HIV treatment, PIMART aims to increase access to PrEP and PEP to prevent new HIV infections. While the full impact of US funding cuts on these services remains unclear, the cuts likely contributed to the slight decline in PrEP use in South Africa seen in 2025, following seven years of steady growth in PrEP uptake.
Graph by Spotlight. Data courtesy of the Thembisa model.
Finger pointing and lack of accountability
Seven months after the Supreme Court of Appeal ruled that the SAPC could implement PIMART and the SAPC promised to move rapidly in implementing PIMART, pharmacists have still not been invited to apply for permits and no PIMART permits have yet been issued to pharmacists.
When asked why the programme remains unimplemented, the SAPC pointed to the Southern African HIV Clinicians Society’s (SAHCS) PIMART training course as the cause of the delay.
SAHCS is the only entity in the country providing PIMART training to pharmacists. In October 2025, Mokoena said several groups had expressed interest in becoming accredited to provide PIMART training. However, on 14 May 2026, Tlala told Spotlight: “While we have invited existing providers of pharmacy education in South Africa to offer (the course), the South African Pharmacy Council is yet to receive applications for the accreditation of the PIMART supplementary training course.”
He added: “Currently, the Southern African HIV Clinicians Society are the only approved provider for the PIMART short course.”
So, what’s going on with SAHCS’ PIMART training?
PIMART used to be on a very different timeline before it got tangled up in the court processes that led to the October 2025 SCA judgment. Back in July 2021, Spotlight reported that the launch of PIMART was imminent, and indeed, that was roughly the timeline the SAHCS training had been working toward.
In fact, the SAHCS has offered a PIMART training course for pharmacists that want to provide PIMART services since 2019. Professor Natalie Shellack, chairperson of the SAPC Education Committee, said in October 2025 that this course was developed jointly by SAHCS and SAPC.
Over a thousand pharmacists have completed SAHCS’s original PIMART training course as continuous professional development (CPD) training. But after the October 2025 SCA ruling, Lizeth Kruger, Dischem’s Clinical Executive, told Spotlight that due to the time lapse between the initial training and court ruling, Dischem pharmacists “will need to do a refresher course to ensure compliance and up-to-date knowledge”.
While SAHCS’s PIMART course has not yet been accredited by the SAPC as a PIMART course, it is accredited as a CPD course for pharmacists. Tlala told Spotlight in May that it has not been accredited as a PIMART course because of an identified “gap” in the course.
“The gap identified between the short course and the approved qualification standard meant that the approved provider of the short course, the Southern African HIV Clinicians Society, had to conduct a gap analysis and develop a bridging course to enable pharmacists trained in the short course to access the full PIMART scope of services,” said Tlala.
In response to questions about the “gap” in their training course identified by the SAPC, SAHCS’s CEO Dr Fiona Storie told Spotlight on 19 May: “SAHCS has completed a full review and update of the PIMART training course in line with the requirements for accreditation as a supplementary training course (i.e. not just a CPD accredited course).”
“As PIMART training was originally provided from 2019, there is a need for pharmacists to undergo refresher training since the field of HIV medicine is evolving and clinical recommendations change over time,” said Storie. She added: “SAHCS’ recommendation is that pharmacists undertake the newly updated PIMART training course as either a refresher/bridging course or, if not previously trained, as a new course.”
“SAHCS is engaging with SAPC to finalise the accreditation of the updated PIMART course as a refresher course and a new supplementary training course to make it available as soon as possible,” Storie said.
Limiting PIMART’s scope
Tlala told Spotlight that because of the “gap” in SAHCS’s training course, the SAPC has asked the Director-General of Health to grant limited scope PIMART permits.
“The Director-General: Health has been requested to issue a limited scope permit granting PIMART-trained pharmacists’ access to those services fully addressed in the short course previously delivered by the South African HIV Clinicians Society,” he said.
The health department confirmed to Spotlight that this request was received on 23 April 2026.
Neither the SAPC nor the Department of Health responded to Spotlight’s requests for clarification on which PIMART services the SAPC had proposed for inclusion in the limited-scope permits.
Angela Tembo, director of pharmacy health at the research centre Ezintsha, told Spotlight that she understands that the limited scope permits that the SAPC has requested the Director-General of Health to grant “will be limited to HIV prevention (PrEP and PEP) and not treatment”.
“Our understanding is that the delays [in implementing PIMART] relate to ongoing discussions around training requirements, accreditation processes, and the practical implementation pathway following the SCA ruling,” she added.
Tlala said as soon as the Director-General of Health approves the limited-scope permits, the SAPC will publicly communicate the launch of the PIMART programme and the services that may be accessed under such a permit.
“The full PIMART scope of services will only be available once the Southern African HIV Clinicians Society has finalised and submitted a bridging course following gap analysis or, alternatively, once another training provider is accredited to provide the PIMART Supplementary Training course,” he added.
Organisations working to strengthen health systems in Africa, including COHSASA, are likely to find renewed urgency in the latest report from the World Health Organization, which warns that gains in global health are under threat.
The World Health Statistics 2026 report released yesterday highlights uneven progress, slowing gains and, in some areas, reversals – leaving the world off track to achieve the health-related Sustainable Development Goals (SDGs) by 2030. WHO points to the need for stronger health systems and improved data to sustain progress and close persistent gaps.
There have been notable advances over the past decade. New HIV infections fell by 40% between 2010 and 2024, while the number of people needing interventions for neglected tropical diseases dropped by 36%.
In the WHO African Region, progress in reducing HIV (down 70%) and tuberculosis (down 28%) has outpaced global averages.
However, these gains are fragile. Malaria incidence has increased by 8.5% since 2015, and progress towards universal health coverage has slowed sharply. One quarter of the global population faces financial hardship due to healthcare costs, and an estimated 1.6 billion people were pushed into or further into poverty due to out-of-pocket spending in 2022.
The report also underscores critical weaknesses in health information systems. As of the end of 2025, only 18% of countries were reporting mortality data within one year, and just one third met WHO standards for high-quality mortality data. These gaps limit the ability to monitor trends, target interventions and ensure accountability.
WHO Director-General Tedros Adhanom Ghebreyesus said the findings reflect “both progress and persistent inequality,” emphasising the need for stronger, more equitable health systems supported by resilient data systems.
For organisations such as COHSASA, the findings reinforce the importance of systematic approaches to improving the quality and safety of care. While the WHO report does not prescribe specific mechanisms, it points to challenges – such as uneven performance, gaps in measurement and preventable harm – that that are directly addressed through structured quality improvement and accreditation processes.
By applying measurable standards, supporting continuous improvement and strengthening the use of data at facility level, accreditation programmes provide a practical means of translating system-wide priorities into day-to-day clinical practice. The report sends a clear message: global health progress is real, but fragile. Strengthening health systems – supported by better data and sustained, measurable improvement – will be essential to regain momentum towards the 2030 health goals.
The Constitutional Court’s hearing over National Health Insurance (NHI) concluded on 7 May. The Board of Healthcare Funders (BHF) and the Western Cape Provincial Government made a combined application challenging the NHI Act on public participation grounds.
The Court is now deliberating; on such complex constitutional matters, it can be weeks to months before a judgment is made. The implementation of NHI remains suspended, following February’s High Court order – President Cyril Ramaphosa and the Minister of Health have formally undertaken not to proclaim or implement any part of the act until the Constitutional Court’s ruling. Other legal challenges are now paused.
What were the arguments?
The hearings focused on one key question: whether Parliament’s process met the constitutional threshold for public participation (primarily under Sections 59 and 72 of the Constitution). Section 59 mandates proactive, reasonable, and meaningful public engagement for the country’s participatory democracy. Formalities alone do not satisfy it – rather, the test is contextual reasonableness aimed at genuine influence. Constitutional Court challenges for national legislation are the main means by which Section 59 is enforced.
The BHF argued that hundreds of thousands of written submissions were effectively ignored; critical information was not provided; and whether, without such information, the test for rational law-making was met.
The Western Cape (led by Premier Alan Winde) focused primarily on deficiencies in the NCOP and provincial stages of the process, arguing that these violated constitutional public-participation requirements and undermined provincial roles. For example, the NCOP process was compressed into only eight weeks, key inputs were ignored, and provincial roles were undermined.
Parliament contended that the process was far more than a “tick-box” exercise, presenting the NHI to the public as a radical, transformative process and that details would only emerge as the project proceeded. [Nevertheless, even a simple calculation would show an NHI budget of R200bn, requiring crippling taxation.] They also argued that accommodations were made, such as extending written comment deadlines. They also argued that changes were made to the Bill, and that engagement does not mean that the legislature agrees, but rather is informed.
Judges raised questions about the integrity and practicality of the public health system in the context of NHI, but the core legal issue remained procedural compliance as opposed to the policy merits.
Is there precedent?
This would not be the first time the Constitutional Court has set aside Acts. In 2006, in a case brought by Doctors for Life, the Choice on Termination of Pregnancy Amendment Act and Traditional Health Practitioners Act were invalidated as Parliament had failed to comply with its section 72(1)(a) constitutional obligation to facilitate public involvement before passing.
Further cases reinforced that inadequate information, rushed timelines, and a lack of consultation over major changes would result in a breach. Parliament, however, argues that Doctors for Life shows that the requirement for participatory democracy has been met.
All parties now await the Court’s decision, which could either uphold the Act, declare it partially or wholly invalid, or remit aspects back to Parliament for correction.
From 5–7 May, the Constitutional Court will hear two of the multiple challenges to the NHI Act. Sasha Stevenson, Executive Director of SECTION27, considers what will be on the line in these first potentially landmark cases that deal with the process that led to the Act.
The public discussion on National Health Insurance has gone from abstract; to alternatively excited or worried about implementation; to dizzying references to a range of court cases filed over the course of 2024 and 2025. It can be difficult to keep up with what NHI may mean for our health system and when the promised system reform may happen.
We may now be approaching a decisive moment, with the Constitutional Court set to hear two of the NHI challenges.
From 5–7 May 2026, the Constitutional Court will be hearing challenges brought by the Board of Healthcare Funders and the Premier of the Western Cape. These two challenges deal with public participation in the making of what is now the NHI Act.
In February 2026, parties challenging the constitutionality of specific sections of the NHI Act agreed with government to put their cases on hold, pending a decision of the Constitutional Court in the May 2026 public participation challenges. The parties bringing constitutional challenges include the South African Private Practitioners Forum, the Hospital Association of South Africa, the South African Medical Association, and the Health Funders Association, among others. They agreed to hold off because a decision of the Constitutional Court on public participation could make the constitutional challenges unnecessary.
So for now, all eyes are on the Constitutional Court, whose judges will decide whether government must go back to the drawing board and follow a different procedure, or whether it may go ahead (and face a slew of constitutional challenges).
The Western Cape’s case
The Western Cape government is challenging the NHI Act because it argues that consultation with the Western Cape government, over legislation that restructures health services provided by provinces, was lacking. They argue that the National Council of Provinces (NCOP) failed to respond to a request for an extension for the Western Cape to submit the outcome of its provincial consultation on the NHI Bill and its voting mandate, and then went ahead without the Western Cape documents.
The NCOP also did not, the Western Cape government alleges, consider or debate any proposed amendments to the NHI Bill arising from the public participation in other provinces. When the Western Cape government submission and public participation report came in, the NCOP merely confirmed its earlier decision to approve the Bill.
In essence, the Western Cape’s challenge is about the NCOP’s role of ensuring that provinces and their residents have a say in the making of new laws, and whether that role was properly played. It argues that the NCOP’s failure to play its constitutional role should result in the NHI Act being declared unconstitutional and invalid.
The Board of Healthcare Funders case
While the Western Cape challenge does not deal with public participation in the NHI law-making writ large, the Board of Healthcare Funders (BHF) case fills this gap.
The BHF argues that both the National Assembly and the NCOP failed to comply with their constitutional obligations to facilitate meaningful and effective public involvement in the NHI law-making process. The BHF contends that the public was not provided with sufficient information to allow for meaningful engagement (such as details about the costs and the benefits package of the NHI Fund); and that law makers were not open to persuasion in the participation process.
The BHF asks that the NHI Act is declared invalid and set aside.
Why should we care about public participation?
The Constitutional Court has held that “[i]t is apparent from the preamble of the Constitution that one of the basic objectives of our constitutional enterprise is the establishment of a democratic and open government in which the people shall participate to some degree in the law-making process.”
There was a huge amount of public participation in the law-making process for the NHI Act, with roadshows, written submissions and oral presentations. Government respondents in the BHF case point to the fact that 338 891 written submissions were made at various stages, and many oral presentations were heard by Parliament. Few could argue that, if you wanted to, you did not have a chance to have your say on the NHI Bill.
But is being able to say something enough?
In a constitutional democracy where citizens participate in law-making between elections as a way of directly influencing the law, if there is no chance of having that influence, merely being able to speak is insufficient.
There is, of course, no obligation on government to adopt proposed changes as a result of public participation. Parliament cannot be required to agree with all submissions, and the validity of a process does not turn on whether amendments were made to take into account submissions. But when few or no amendments are made, it inevitably raises eyebrows.
In the case of the NHI Bill, while there were limited changes to the Bill when it went through the National Assembly, no changes at all were made following the NCOP public participation process. Given the hundreds of thousands of submissions, many of which were substantive, the small number of amendments is surprising. Particularly given that some submissions that were consistently made are now being conceded by the Department of Health, in public or in private. These include submissions related to the position of asylum-seekers, transitional provisions, and the role of medical aids.
SECTION27 and the Treatment Action Campaign made submissions at Draft Bill stage, before the National Assembly, and before the NCOP. As health activists and health rights lawyers, our submissions were carefully considered and proposed amendments to bring the Bill in line with the Constitution and the needs of healthcare users. Our experience was of MPs engaging to a very limited extent with the substance of the submissions, focusing rather on whether we were ‘for’ or ‘against’ the NHI, or their party’s position on it. It was an experience that brought into question how seriously real public participation was being taken.
The Constitutional Court will now be able to consider whether the public participation processes on the NHI Act were in line with the constitutional call for participatory democracy; or whether they were an unconstitutional tick box exercise. Its decision will determine if the NHI Act will be further scrutinised for substantive constitutionality through litigation, or if it should be returned to the legislature for further consideration and participation.
Either way, what NHI may mean for our health system is a question that may yet take some time to answer. On the other hand, what participatory democracy requires of parliament (arguably an even more consequential question) may soon be answered by the Constitutional Court.
*Stevenson is a human rights lawyer and executive director of SECTION27. SECTION27 is representing the Treatment Action Campaign in an application to be admitted as amicus curiae in a court case relating to the NHI.
Note: Spotlight is published by SECTION27, but is editorially independent – an independence that the editors guard jealously. Spotlight aims to deepen public understanding of important health issues by publishing a variety of views on its opinion pages. The views expressed in this article are not necessarily shared by the Spotlight editors.