Category: Hospitals

Dis-Chem and Cipla Foundation Partner to Bring Affordable Primary Healthcare Closer to Macassar Residents

The partnership supports community-based care while empowering a local nurse entrepreneur to provide quality primary healthcare closer to home

Macassar, Western Cape – Residents of Macassar will now have improved access to affordable, quality primary healthcare close to home following the launch of a new Sha’p Left nurse clinic.

Established through a partnership between Dis-Chem’s Better Tomorrow programme and the Cipla Foundation’s Sha’p Left initiative, the clinic aims to remove everyday barriers to care, including high transport costs, lost working hours and long queues at public health facilities.

Home to approximately 52 400 people across 14 000 households, Macassar is a growing, working-class community. Most residents rely on the local Community Health Centre for primary and maternity care. The new clinic will help ease pressure on this already busy facility while improving access to care for conditions including HIV, tuberculosis, diabetes and hypertension.

Led by experienced Clinical Nurse Practitioner Patricia-Ann Smith, the new fee-for-service practice is fully licensed to dispense medication up to Schedule 4. Patients can therefore be examined, diagnosed and receive the required treatment and prescriptions during a single visit, offering a convenient, cost-effective and dignified alternative for routine primary healthcare.

“Better Tomorrow is about finding practical ways to bring quality care closer to communities,” says Joshila Shiba, Dis-Chem’s Head of Health Equity and Sustainability. “Rather than building every solution from scratch, we partner with experienced organisations that already have proven, community-rooted models. Macassar gives us an invaluable opportunity to measure the real-world impact of this intervention and assess its long-term sustainability.”

From nurse to nursepreneur

At the heart of the clinic, Smith, a veteran healthcare professional with 37 years of nursing experience says the initiative has created an opportunity to turn a lifelong ambition into reality. The Sha’p Left model supports qualified nurses, predominantly women, with the infrastructure, training, compliance support and operational systems needed to establish independent practices.

“I have always wanted to own a healthcare business, but nursing has always been about putting people first and building trust,” says Smith. “Caring for my own community means a great deal to me. Primary healthcare gives us an opportunity to prevent illness, promote healthier choices and improve quality of life. Being able to make quality healthcare more accessible while contributing to my community makes this practice especially meaningful to me.”

A scalable model for primary healthcare

Designed by the Cipla Foundation, the Sha’p Left initiative aims to establish self-sustaining primary healthcare practices that can operate independently of ongoing philanthropic funding. The model is built on the principle that trusted local clinical nurse practitioners are well placed to expand access to primary healthcare in their own communities.

“Affordable, nurse-led clinics have an important role to play in expanding access to quality healthcare in South Africa,” says Paul Miller, CEO of Cipla Africa. “By bringing essential services closer to communities, we can help ease pressure on overburdened public health facilities while empowering qualified nurses to become healthcare providers and entrepreneurs in their own communities.”

For Dis-Chem Better Tomorrow, funding the Sha’p Left Macassar clinic forms part of a broader commitment to strengthening primary and preventative healthcare across South Africa.

“We want to help build and support healthcare models that strengthen the broader primary healthcare system for the long term,” says Shiba. “Macassar is our starting point. Demonstrating real societal health impact by improving access to quality healthcare for more South Africans through our integrated healthcare ecosystem is core to our purpose.”


World Pharmacists Day – 25 September 2026

Pharmacists are the most accessible healthcare professionals for many South Africans. Image created with AI.

Astrid Stealey, Area Managing Director, South Africa & Sub-Saharan Africa, Kenvue

World Pharmacists Day is an opportunity to recognise the contribution pharmacists make to the health of communities across South Africa. But recognition must go hand in hand with ensuring they have the training, resources and support to meet the demands being placed on them.

Pharmacists are often among the most accessible healthcare professionals in their communities. They play an important role in helping people navigate everyday self-care, understand the responsible use of medicines and recognise when symptoms require referral to a doctor or another healthcare service. That guidance can help people make more informed decisions about their health, but it should never be taken for granted.

Kenvue’s previously published research found that 82% of surveyed South African pharmacists regularly provide advice to people who cannot access a GP. At the same time, 76% reported increased demands on their time.

These findings highlight both the value pharmacists provide and the pressure many are working under. Supporting them means investing in continuous professional education, access to credible, evidence-based information and systems that recognise both the potential and the limits of their role.

This year’s World Pharmacists Day 2026 theme, “Empowering pharmacists for healthier futures,” captures that challenge well. A healthier future depends on pharmacists being equipped and supported to use their expertise confidently, responsibly and sustainably.

Hiring More Specialists won’t Fix Wait Times – And May Worsen Them

Harvard, NYU, and NEJM researchers draw on traffic engineering to explain why more physicians per capita is linked to longer waits

Photo by RDNE Stock project

A new analysis published in NEJM Catalyst Innovations in Care Delivery finds that the standard response to growing specialist wait times, hiring more physicians, is unlikely to solve the problem on its own, and may even worsen it. The article, Reducing Specialist Wait Times: What Can We Learn from Highway Traffic Engineers?, draws a direct parallel between specialist scheduling and highway congestion, where adding lanes fails to ease traffic because drivers simply adjust their behavior to take advantage of the new capacity. 

Wait times for new specialist appointments in the United States have been rising for two decades. A national survey of six specialties across 15 metropolitan areas found that average wait times reached 31 days in 2025, up 19% since 2022 and 48% since 2004. Longer waits carry real costs for patients, including psychological strain and, in some cases, worsening symptoms that lead to more hospitalizations and emergency department visits. 

Key Findings 

Examining wait-time and physician-density data across four referral specialties – cardiology, dermatology, obstetrics-gynaecology, and orthopaedic surgery – the authors found positive association between the number of specialists per capita in a metro area and how long patients waited for an appointment.  

The authors describe that this pattern mirrors “induced demand” in transportation economics: when road capacity increases, people drive more, quickly eroding any gains in travel time. In specialty care, the analogous dynamic is that more available specialists can lower the threshold at which primary care physicians refer patients, encourage patients to seek specialty care more readily, and lead specialists themselves to manage issues that primary care could otherwise handle. The result, the authors write, is that new specialists’ schedules fill quickly and wait times fail to fall. 

Rather than relying primarily on hiring, the authors outline three categories of tactics, adapted from how traffic engineers manage congestion, that health systems can use instead or in tandem: 

  • Expanding care options, such as building guidance into electronic health records so primary care physicians can manage more conditions themselves, expanding physician assistants’ and nurse practitioners’ role in specialty care, and offering virtual group visits to cut wait times. 
  • Adjusting financial incentives, including raising copayments for specialist visits relative to primary care, and reduced out-of-pocket costs for chronic disease care delivered by nurse and other provider teams. 
  • Giving patients better information tools, such as online self-scheduling, which reduces no-show rates and helps keep physician schedules full, and implementation of AI to answer patient questions and flag developing problems before they require a specialist visit. 

The authors caution that redesigning specialty care is difficult: seeing long-stable patients is often easier for specialists than taking on new, complex cases, and any redesign has to give specialists the support they need to handle the patients who most need their expertise. 

“Our argument is not against hiring more physicians, but for better leveraging the clinicians we have,” the authors write, adding that advanced practice providers in particular are “perpetually overlooked” in care redesign despite their central role on care teams. 

About the Research 

The analysis was authored by Leemore Dafny of Harvard Kennedy School & Harvard Business School, Sherry Glied of NYU Wagner Graduate School of Public Service, and Thomas H. Lee of NEJM Catalyst. It draws on wait-time and appointment-scheduling data from a national survey of physician offices in six specialties across 15 metropolitan areas, combined with physician density data from the Area Health Resources Files. 

Source: Harvard Kennedy School, EurekAlert

Nearly 70% of the Global Health Workforce Are Women – But Health Worker Shortage Remains

Photo by Hush Naidoo on Unsplash

Women have driven the expansion of the global health workforce over the past three decades, yet substantial workforce shortages remain, according to a new study published in The Lancet Public Health. Researchers estimate that an additional 34.4 million doctors, nurses, midwives, dentists, and pharmacists are needed worldwide to achieve moderate levels of universal health coverage, where people can access essential health services without financial hardship. 

The study found that the global health workforce nearly tripled between 1990 and 2023, growing from 40.9 million to 122.1 million workers. Women accounted for 71.4% of this growth and represented 68.9% of all health workers in 2023. Despite this progress, substantial shortages persist across many regions, particularly South Asia and sub-Saharan Africa, where health systems continue to face some of the world’s lowest workforce densities. 

Based on Global Burden of Disease (GBD) 2023 estimates, this study provides the first global, sex-disaggregated estimates of 20 health worker cadres, or groups of specially trained health personnel such as doctors, nurses, midwives, pharmacists, dentists, and community health workers, across 204 countries and territories from 1990 to 2023, including the first global estimates of community health workers. It also offers the most comprehensive assessment of the global health workforce to date.  

Women have driven global health workforce growth but remain underrepresented in many higher-paid professions. 

Between 1990 and 2023, the global health workforce expanded by more than 81 million workers, including 18.9 million nurses and 8.7 million doctors. Most regions saw substantial growth over this period, although the pace of expansion varied across countries and health professions. 

In 2023, the global health workforce included 122.1 million health workers, including 33.2 million nurses, 15.1 million doctors, 7.6 million community health workers, 6.8 million pharmacists and pharmaceutical assistants, and 6.1 million dentists and dental assistants. Women represented nearly seven in ten health workers worldwide, comprising 80.7% of nurses, 96.0% of midwives, and 89.5% of community health workers, while less than half of doctors were women. Similar patterns were observed across dentistry and pharmacy, where women were more likely to work as assistants than as dentists or pharmacists.  

“Women have transformed the global health workforce over the past three decades, but they continue to be concentrated in professions that generally offer lower pay and fewer opportunities for leadership,” said Megan Knight, lead author of the study and researcher at the Institute for Health Metrics and Evaluation (IHME). “Building stronger health systems will require not only expanding the workforce, but also creating equitable opportunities for career advancement, leadership, and safe, supportive working environments.”

Millions of health workers will be needed to achieve universal health coverage. 

Despite substantial workforce growth, researchers estimate the world would need an additional 34.4 million health workers to achieve a score of 80 out of 100 on the GBD universal health coverage effective coverage index, a benchmark representing moderate levels of universal health coverage. This includes shortages of 23.9 million nurses and midwives, 7.1 million doctors, 1.8 million dentists, and 1.6 million pharmacists. 

Workforce shortages were greatest in South Asia, which would require an additional 2.6 million doctors and 10 million nurses and midwives to reach moderate universal health coverage. Sub-Saharan Africa also faced severe shortages across major health professions, with nursing density of 14.5 per 10 000 population compared with 121.8 per 10 000 in high-income countries. At the country level, nurse density was as low as 3.2 per 10,000 in Chad and 3.3 in Madagascar, compared with 171.7 per 10 000 in Belgium and 161.4 in the United States. 

“Health workers are the foundation of every health system,” said Dr Annie Haakenstad, senior author of the study and Assistant Professor of Health Metrics Sciences at IHME. “Although the global workforce has expanded dramatically, millions more doctors, nurses, midwives, dentists, and pharmacists will be needed to ensure people everywhere can access essential health services. These findings provide countries with minimum thresholds for planning the workforce needed to strengthen health systems and move toward universal health coverage.” 

Meeting global health goals will require sustained investments in the health workforce. 

The study estimates that achieving moderate universal health coverage is associated with minimum workforce densities of 23.8 doctors and 64.5 nurses and midwives per 10 000 people, along with 5.2 dentists and 5.6 pharmacists per 10 000. These minimum benchmarks can help countries identify workforce gaps and plan the investments needed to meet future health needs. 

The estimates also provide a measure of progress toward Sustainable Development Goal (SDG) target 3.c.1, which calls for substantially increasing the recruitment, development, training, and retention of the health workforce, as well as SDG target 3.8 on achieving universal health coverage.  

Closing global workforce gaps will require sustained investments in health worker education, recruitment, retention, and working conditions. Gender-responsive policies, including leadership development, workplace protections, paid parental leave, and flexible work arrangements, can also help support the predominantly female health workforce. Building a well-supported health workforce will be essential to expanding access to care and ensuring health systems are equipped to meet future health challenges.

Source: Institute for Health Metrics and Evaluation

Why Doctors and Nurses Keep Leaving

Healthcare leaders say generational differences are making it more difficult to retain doctors and nurses

Source: Pixabay CC0

By Lesley Henton, Texas A&M University Division of Marketing and Communications

Healthcare leaders say retirements, burnout and changing workforce expectations are making it complicated to keep experienced clinicians in place. A new study published in the Joint Commission Journal on Quality and Patient Safety suggests the reasons go beyond staffing shortages. Leaders from four major health systems in one of the United States’ largest metropolitan areas say generational shifts are reshaping who enters healthcare, who stays and why clinicians leave.

“We’ve talked about clinical workforce shortages as a numbers problem involving training and retention,” said study co-author Dr William Sage, founding director of the Texas A&M University Institute for Healthcare Access in Fort Worth. “What these leaders described was something more complicated, as healthcare organisations are struggling to meet growing patient needs while accommodating five distinct generations of clinicians with different needs and perspectives about work, well-being and career longevity.”

Why keeping clinicians is getting harder

Study participants, 17 leaders from four major healthcare systems in the Dallas-Fort Worth metroplex, repeatedly described the departure of clinicians as one of their biggest concerns, whether the higher turnover now common among young physicians or an older physician’s lack of transitional options short of full retirement. Some said replacing a highly experienced physician could require hiring multiple younger clinicians, given the way that the healthcare system measures and rewards productivity.

“When a veteran clinician leaves, healthcare organisations lose more than just a position,” said Keegan Warren, co-author and the institute’s executive director. “They can lose years of institutional knowledge, mentoring relationships and practical experience that are difficult to replace. For physicians in particular, departure carries a high institutional price tag. Treating clinicians as people whose lives and contributions matter is not just the right thing to do; it’s a critical strategy for protecting both continuity of care and the financial health of the system.”

Participants also pointed to burnout and shifting workplace expectations. Younger physicians and nurses are more likely to discuss mental health, work-life balance and scheduling flexibility, and they expect employers to play a major role in addressing those concerns.

Sage said the findings should not be interpreted as a simple clash between generations but as the shifting and mixing of expectations over time, including as the result of discrete events such as the introduction of work hours regulation for medical trainees, the reduction of physician-owned practices in favour of employment by hospitals and other large organisations and the COVID pandemic.

“This isn’t a story about one generation being right and another being wrong,” Sage said. “It’s about how the profession is changing and how healthcare organisations can adapt while continuing to provide excellent patient care.”

Clinicians are people first, with lives, families, identities and limits. They’re not just ‘providers’ or FTEs.

Keegan Warren, Executive Director, Texas A&M University Institute for Healthcare Access

Building the healthcare workforce of the future

The researchers say addressing these challenges will require more than simply hiring more clinicians.

The study identifies several approaches that could help strengthen the healthcare workforce:

  • Create more intentional mentorship programs to transfer knowledge from experienced clinicians to younger colleagues.
  • Reduce early career turnover through retention-focused benefits, continuous career development and workplace flexibility.
  • Include multiple generations in leadership and decision-making, ensuring workplace policies reflect different career stages and perspectives.
  • Give human resources leaders a larger role in workforce planning, retention strategies and succession planning.
  • Develop flexible late-career roles for experienced clinicians, allowing them to continue mentoring and contributing even as they reduce clinical workloads.
  • Improve communication across generations to address workplace tensions before they affect morale, retention or patient care.

A stable, capable clinical workforce is foundational to patient access to care, say the researchers, and if healthcare organizations can better support each generation of clinicians throughout their careers, patients will benefit.

“We’re seeing healthcare organizations recognize that retention can no longer be an afterthought,” Warren said.

“Clinicians are people first, with lives, families, identities and limits. They’re not just ‘providers’ or FTEs. When leaders design roles and cultures that honour that humanity, they strengthen commitment, stabilise teams and build a more resilient healthcare system.”

Source: Texas A&M University

Long-term Relationships with Family Physicians Linked to Fewer Urgent Hospitalisations

Photo by Cottonbro on Pexels

A new study published in the American Academy of Family Physicians finds that keeping patients connected to the same practice and physician over time may help reduce avoidable hospital use.

This retrospective cohort study using longitudinal data from 100 450 patients across 48 general practices in and around Amsterdam found that patients registered with their practice for longer than 5 years had 9% to 21% lower odds of urgent hospital admission and 17%-28% lower hospital costs compared to those registered for 0 to 5 years.

Consistently seeing the same general practitioner was associated with 6% to 7% lower hospital costs, but not with fewer urgent admissions. Researchers measured continuity associations with urgent hospital admissions and hospital costs in two ways: duration of the general practitioner-patient relationship and how concentrated a patient’s visits were with one physician. 

The researchers concluded, “Our study suggests an association between continuity in general practice and hospital use and costs. Although there is an overwhelming amount of evidence regarding the benefits of continuity of care for both patients and GPs, this study shows that continuity is also associated with fewer urgent admissions and lower hospital costs.”

Source: EurekAlert!

Scheduling Surgeons: Researchers Identify Factors for Hospital Efficiency

Booking operating rooms with surgical precision starts with more accurate predictions of how surgeons spend their time

Photo by Piron Guillaume on Unsplash

Researchers at the University of Massachusetts Amherst have analysed nearly 86 500 surgeries at Baystate Medical Center to identify the top factors that influence inefficiencies in surgeon schedules. Having an efficiently organised surgical schedule has the potential to lower costs and reduce surgeon burnout, which would also improve patient outcomes.

As shortfalls in the availability of surgeons grow, the ability to meet surgical demands will only worsen, with implications for both healthcare delivery and costs.

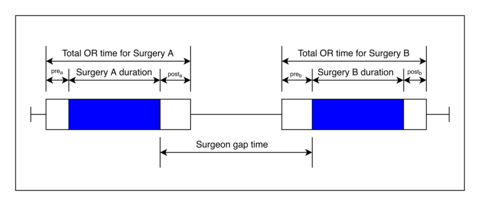
This illustrates the timeline of two surgeries performed by the same surgeon. The blue area represents the duration of the actual surgery itself, while the white blocks represent pre- and post-surgery activity.  Surgeon gap time is the time interval between two operations where the surgeon is not actively working.

“The most expensive part in this process of getting a surgery is the surgeon,” says Muge Capan, assistant professor in the Riccio College of Engineering at UMass Amherst and an author of the new paper published in the Journal of the American Medical Informatics Association. “Surgeons are highly skilled and they perform high-risk tasks. When we think about utilising a resource, we don’t want them to sit idle – but we also don’t want to overutilise them because these are not machines, these are people. Finding that right balance is a challenging problem.”

However, to efficiently schedule, hospitals need to predict how long a procedure will take. This includes the surgery itself as well as many other factors that surround an operation – has the surgeon recovered from their previous operation? Is the room clean? Is the proper equipment in place? “There is a lot of uncertainty there at the system level,” says Capan.

Currently, surgeries are scheduled in blocks, which is not compatible with the unpredictable nature of a hospital. “If you’re scheduling tennis lessons, it works because a tennis lesson is exactly one hour,” says Capan. “You block the court for one hour, you play, you leave, next group. But blocks don’t make sense for surgeries, because they’re so uncertain.” As a result, operating rooms (ORs) can sit empty since any block of time less than two-and-a-half hours is unusable for most surgeries.

In the pursuit of engineering a better schedule, Capan and her team collaborated with surgeons to predict their schedule by focusing on the person, not the operating room.

Surgeons are highly skilled and they perform high-risk tasks… we don’t want them to sit idle – but we also don’t want to overutilise them because these are not machines, these are people. Finding that right balance is a challenging problem.

Muge Capan, assistant professor in the Riccio College of Engineering at UMass Amherst

“There’s so much research on the operating room itself – what happens between the time a patient leaves the OR to the time the next patient enters the OR,” says Jonathan Akhagbosu, first author on the paper and UMass Amherst industrial engineering Ph.D. candidate. “But we wanted to look at it from a surgeon’s point of view: What happens between when a surgeon finishes one case and proceeds to the next case?”

The researchers named this time between operations “gap time.” In their study, they used machine learning to analyse three years of medical records from Baystate Medical Center in Springfield to determine the characteristics of a surgery that can predict these gaps in a surgeon’s schedule. 

A selection of the top factors associated with larger gap times are: if the surgeon’s previous or following case is an emergency, the preceding surgery is related to the chest (thorax), the following procedure is on the heart, or the surgery is highly demanding. 

Also, the last factor on the list – the assessment of how taxing an operation is on the surgeon – the researchers used mathematical models to create a new measurement called surgical case demand. Cases fall into one of three tiers. Type 1 consists of short, scheduled procedures of low-severity illness and elective surgeries, such as the removal of fatty lumps from the skin (lipoma excision) or simple dental rehabilitation. Type 2 events are more demanding, such as a mastectomy or knee replacement. And type 3 surgeries are the most onerous: the condition is more severe and they happen during off-hour times. Examples include emergency brain or abdominal operations and spine procedures.

It’s also worth noting that eye (ophthalmology) and orthopedic surgeries were associated with shorter gap times.

Capan envisions that predicting schedules can help recapture some of this lost time. “If there’s going be a gap, let’s figure out if that gap is long enough that I could squeeze in something else,” says Capan. “This is called ‘collectible time’ in the literature. Collectible time means it’s a useful gap. So what we learned about gap time could potentially help us understand collectible time.”

By Julia Westbrook 

Source: University of Massachusetts

The Charlotte Maxeke Fire Should Have Been a National Turning Point – Is SA Now Ready to Listen?

Charlotte Maxeke Johannesburg Academic Hospital. (Photo: Gauteng Department of Health)

By Haseena Majid and Mogie Subban

The fire that engulfed parts of Charlotte Maxeke Johannesburg Academic Hospital was never just a fire, it was a warning, argue Dr Haseena Majid and Professor Mogie Subban. Five years later, the real question they say is whether South Africa is prepared to listen.

The fire that ripped through parts of Charlotte Maxeke Johannesburg Academic Hospital in April 2021 should have been a national turning point. Instead, five years later, we were confronted with explosive findings from the Public Protector confirming that the Gauteng Department of Infrastructure Development and the Gauteng Department of Health delayed repairs, fought internally over responsibilities, and failed to spend almost half of the approximately R666.7 million budget allocated to restore the hospital.

The Public Protector’s report revealed that by March 2024, only about 49% of the ringfenced funds had been spent despite the hospital’s catastrophic service disruptions. At the same time, Charlotte Maxeke’s Head of Internal Medicine Professor Adam Mahomed, who lodged the complaint with the Public Protector, publicly described overcrowded wards, exhausted clinicians, and a hospital effectively surviving through improvisation rather than recovery.

These are not isolated failures. They point to deeper governance weaknesses within public administration.

The question that inevitably arises is how these failures have persisted for so long, given that South Africa’s governance framework is not lacking in legal safeguards.

South Africa’s governance framework already contains extensive mechanisms for oversight and accountability. Section 195 of the Constitution demands accountability, transparency and efficient resource use. Section 217 governs fair and cost-effective procurement. The Public Finance Management Act regulates expenditure and financial accountability. The Public Administration Management Act strengthened ethics, norms and oversight within public administration. The Auditor-General and Public Protector both play critical roles in identifying maladministration and safeguarding accountability. These frameworks are designed to ensure that information flows upward, warning signs trigger intervention and accountability occurs before systems fail.

Yet, the reality tells a different story. Five years after the Charlotte Maxeke fire, hundreds of millions of rand allocated for restoration remained underutilised. Procurement scandals at Tembisa Hospital allegedly operated for years before attracting national attention. Medicine stockouts continue despite multiple reporting structures. More than 240 000 people are reportedly waiting for cataract surgery in one province, while public hospitals continue to lose skilled personnel as infrastructure deteriorates.

Even more troubling is the time it takes before these failures become visible for some form of action to follow. The asbestos scandal in the Free State, corruption at Transnet and Eskom, and the alleged procurement networks at Tembisa all reveal the same pattern: accountability mechanisms kick in long after the damage has already been done.

These failures point to deeper systemic weaknesses. They reflect institutions that have struggled to respond effectively and correct themselves. And every delayed intervention carries human consequences. Cancelled operations, interrupted treatment, avoidable disability, burnout among healthcare workers, lost productivity and preventable deaths are not abstract administrative failures. They are the lived consequences of governance failure.

What to do

The question confronting South Africa is not whether another report or task team is required. The country has already produced no shortage of investigations, commissions and oversight findings. The real challenge is whether institutions are willing and able to act on what is already known.

A capable health system rests on several pillars: skilled staff, functioning infrastructure, sustainable financing, effective programmes, reliable procurement systems, coherent policy implementation and operational coordination. Yet even when these pillars exist, the entire structure remains vulnerable if the systems responsible for integration, oversight and accountability are weak.

Modern health systems are increasingly complex institutions requiring both clinical excellence and strong governance capability. Expertise in organisational systems, budgeting, monitoring and evaluation, procurement and institutional accountability should therefore be viewed not as alternatives to clinical expertise, but as interdependent capabilities essential for institutional resilience.

Money matters. Infrastructure matters. Human resources matter. Technology matters. But without institutions capable of coordinating, overseeing and acting, crises simply repeat themselves.

What South Africa needs is more than another cycle of crisis management. It needs a renewal of governance itself. That means stronger alignment between roles, competencies and institutional responsibilities, protected oversight pathways and consequence management that operates before catastrophe rather than after it. It means rebuilding a public service culture in which accountability is not treated as an inconvenience, but as the moral backbone of a constitutional democracy.

*Majid is a postdoctoral researcher at the University of KwaZulu-Natal specialising in public administration and systems governance. She is a Global Atlantic Fellow for Health Equity and Social Justice at Tekano. Her research focuses on stakeholder mapping, disaster resilience and strengthening governance systems through collaborative public-sector approaches. Subban is an Academic Mentor and Public Governance Expert, at the College of Law and Management Studies, University of KwaZulu-Natal.

Note: Spotlight aims to deepen public understanding of important health issues by publishing a variety of views on its opinion pages. The views expressed in this article are not necessarily shared by the Spotlight editors.

Republished from Spotlight under a Creative Commons licence.

Read the original article.

Emergency Doctors Are Stressed out – And Patient Irritation Plays a Significant Role

Research finds physicians with peevish patients were more likely to become disengaged in the patients’ care

Photo by Usman Yousaf on Unsplash

HBO’s emergency-department drama “The Pitt” has become a smash hit in large part because it shows the deeply human toll that emergency medicine exacts from those who practice it. While researchers have long known that real-life ER doctors are affected by many of the stresses that “The Pitt” has so effectively captured, a recent study led by the University of Massachusetts Amherst and published in BMJ: Quality & Safety is the first to design an interactive and controlled experimental method to test how irritable patients – those displaying frustration or anger – affect the emotions of those treating them, and thus, potentially, the effectiveness of care they receive.

The emergency department has always been one of the most stressful places to work in any hospital – one never knows what sorts of injuries, or how many of them, each shift will hold. Additionally, these spaces have increasingly been on the frontlines of various economic and social crises, including the lack of health insurance and skyrocketing medical costs, immigration and law enforcement and increasing needs for mental health and addiction services. One of the results of all of this is that patients are increasingly irritable, and too often take their frustrations out on caregivers.

“Emotions are an inherent part of our lives – they’re what makes us human,” says Linda Isbell, Feldman-Vorwerk Family Professor in Social Psychology at UMass Amherst and the paper’s lead author. “But for too long, the medical culture has expected doctors to leave their emotions at the door. This is just unrealistic.”

It seems reasonable to conclude that when physicians experience stress in response to patient irritation, the quality of patient care suffers, and there is good anecdotal evidence to support that. But until Isbell and her co-authors, including emergency medicine doctors from the UMass Chan Medical School and the Harbor-UCLA Medical Center, began their study, there were no reliable controlled experiments that had rigorously studied how patient behaviour affects physicians’ emotions and patient care.

For too long, the medical culture has expected doctors to leave their emotions at the door. This is just unrealistic.

 Linda Isbell, Feldman-Vorwerk Family Professor in Social Psychology at UMass Amherst and the paper’s lead author

The team designed a novel approach that began with professional “standardised patients”, people who are specially trained to play patients with realistic, specific medical conditions. Four standardised patients were each trained to perform in one clinical case that corresponded to one of four different diagnoses. Each “patient” was trained to perform two different roles: someone calmly seeking medical care, and someone behaving irritability with their physician. 

“What’s most important here is that each standardised patient, no matter whether they were playing their calm or irritable role, provided the same exact medical details,” says Isbell. “The only thing they changed was their emotional condition.” 

Isbell and her colleagues video-recorded these patient encounters and then recruited 134 emergency medicine physicians from 46 U.S. states. Each physician was randomly assigned a set of four recorded patient encounters, two of which were from calm patients, two from the far more irritable group. 

The physicians were then asked to order clinical tests, for which they received results, and continuously assess their patients, just as they would do in a real-life setting. 

Finally, Isbell and her team asked the physicians to report on their emotional state and engagement with each patient. With this information, researchers examined whether or not physicians’ emotional responses, clinical assessments or clinical behaviours shifted when they were assessing irritable patients versus calmer ones.

What they found is that irritable patients make physicians feel worse. Those physicians reported increased levels of anger, anxiety and fatigue. Doctors were also less engaged in their irritable patient’s care, and much more likely to find their patients unreliable in terms of reporting their own symptoms. Physicians with irritable patients were more likely to interpret their patient’s pain as exaggerated, find them less cooperative, less engaged in their own care or willing to adhere to a treatment plan, and less likely to return to work.

Furthermore, those physicians who were more susceptible to finding medical uncertainty stressful experienced a greater emotional toll when their patients were difficult.

More research is needed to better understand how all of this affects patient care, but, as Isbell put it, “the interaction between a patient’s behaviour and a doctor’s ability to tolerate stress associated with medical uncertainty is critical.” Doctors who are especially vulnerable to stress are likely to experience their difficult patients as more challenging and emotionally taxing – fuelling a cycle that could lead to worse patient outcomes.

“Medicine is inherently uncertain and emotional,” says Isbell, “especially in the ER. We need a systemic shift that acknowledges the human reality of uncertainty and emotions in medicine and supports both doctors and patients as they work toward a common goal: health and well-being for all.”

Source: University of Massachusetts

Brushing Your Teeth in Hospital Could Reduce the Chance of Catching Pneumonia

Photo by Stephen Andrews on Unsplash

Brett Mitchell, University of Newcastle; Allen Cheng, Monash University; Nicole White, Queensland University of Technology; Peta Ellen Tehan, Monash University, and Philip Russo, Monash University

You go to hospital for treatment and to get better. But sometimes, you get something much less welcome: an infection.

Pneumonia, an infection of the lungs, is one of the most common and deadly infections people develop in hospital. Around 50 000 patients contract pneumonia in Australian hospitals every year. Around 1900 of them die from it.

It’s rarely monitored and rarely reported. And to date, few studies have looked at how it can be prevented.

But our new trial, published today in The Lancet Infectious Diseases, shows a surprisingly simple action can make a major difference: brushing patients’ teeth.

We found this can reduce the chance of getting this type of pneumonia, called non-ventilator hospital-acquired pneumonia, by 60%.

What is this type of pneumonia?

Non-ventilator hospital-acquired pneumonia occurs in patients who aren’t on a ventilator, usually outside of intensive care settings.

Patients are infected when bacteria from the mouth or throat are breathed into the lungs.

Patients who develop this type of pneumonia stay in hospital between ten and 48 days longer, and are around eight times more likely to die during their admission.

A simple intervention made a big difference

We studied 8,870 patients across three Australian hospitals to see whether improving oral care – which included tooth-brushing – could reduce this type of pneumonia.

Usually, when patients go to hospital, they don’t pack a toothbrush – especially in emergencies.

In busy hospital wards, oral care isn’t always given the attention it needs, nor are oral care products always readily available. Patients don’t always get reminders to brush their teeth and many patients need help with their oral care.

The intervention in our study was deliberately simple. We:

  • gave patients in hospital a toothbrush and toothpaste in a bag when they were admitted
  • educated patients and hospital staff about the importance of tooth-brushing. The toothbrush also had a written prompt on it – “Brush away pneumonia”
  • assisted patients who needed help with tooth-brushing
  • audited how oral care was being delivered and gave feedback to hospital wards.

We introduced the intervention into one ward at a time over 12 months at each hospital. This gradual roll-out is known as a stepped-wedge cluster randomised trial. It can test new health interventions when it’s too difficult to randomise individuals without revealing who is receiving the intervention and who isn’t.

We found that this relatively simple intervention increased the proportion of people who cleaned their teeth from 16% to 62%.

This increasing oral care led to a 60% reduction in the risk of acquiring pneumonia, from the equivalent of eight infections per month on a typical ward of 30 patients, to less than four infections per month.

This is the largest trial of its kind and the first completed across multiple hospitals.

Why does brushing teeth help?

The mouth is home to billions of bacteria. Oral hygiene often deteriorates when people are unwell, sedated, immobile, or taking certain medications.

When this happens, bacteria build up on the teeth, gums and tongue. If these bacteria are breathed in – even in tiny amounts – they can cause pneumonia.

Daily tooth-brushing reduces this bacteria. It’s a simple mechanical action with a powerful protective effect.

Yet in busy hospitals, oral care is often overlooked. Patients may not know just how important oral care is. Staff are often busy with competing priorities and oral care can be de-prioritised. There is also a general lack of understanding about the importance of oral care.

Patients can help protect themselves

One of the most important messages from our research is patients aren’t powerless. While health-care staff such as nurses play a crucial role, patients who are able to brush their own teeth can meaningfully reduce their own risk.

If you or a loved one is admitted to hospital, you can:

  • bring your own toothbrush and toothpaste
  • brush your teeth twice a day if you’re able
  • ask staff for help if you can’t
  • remind staff if oral care has been missed.

These small actions can reduce the risk of a serious, life-threatening infection.

What happens next?

Pneumonia is costly – in lives, hospital days and the financial cost of care. But because non-ventilator hospital-acquired pneumonia isn’t routinely reported, it’s often invisible.

Our research challenges the assumption that hospital-acquired pneumonia is an unavoidable complication when you go to hospital.

It also highlights the need for hospitals to monitor non-ventilator hospital-acquired infections, in the same way they monitor falls, pressure injuries and other preventable harms.

Finally, our study strengthens the case for including oral care in national infection-prevention guidelines and nursing practice.

Oral care isn’t glamorous, expensive or technologically advanced – but it works. Sometimes, the simplest interventions are the most powerful.

Brett Mitchell, Professor of Nursing and Health Services Research, University of Newcastle; Allen Cheng, Professor of Infectious Diseases, Monash University; Nicole White, Associate Professor of Statistics, Queensland University of Technology; Peta Ellen Tehan, Senior Lecturer, Monas University, Monash University, and Philip Russo, Professor, Director of Research, Nursing and Midwifery, Monash University

This article is republished from The Conversation under a Creative Commons license. Read the original article.