Category: Mental Health

Autistic Kids Showed Improved Social Skills After Summer Programme

Photo by Peter Burdon on Unsplash

A summer intervention programme for autistic children ages 4-6 with no intellectual disability significantly improved their social performance, according to a study by researchers at the Institute for Autism Research (IAR) at the University at Buffalo. It was published in Advances in Neurodevelopmental Disorders.

“Completion of our 5-week summerMAXyc programme was associated with significant social, behavioral and autism symptom benefits for the children,” says Christopher J. Lopata, PsyD, co-author on the study and co-founder/co-director of the IAR with Marcus L. Thomeer, PhD; both are professors of pediatrics in the Jacobs School of Medicine and Biomedical Sciences at UB. “Developing such foundational skills early in development sets the stage for development of more advanced skills later in childhood, adolescence and adulthood, thus leading to better long-term outcomes.”

Thomeer notes that while programmes for autistic children with no intellectual disability ages 4-6 do exist, few provide intensive social programming. This population also tends to engage in significantly fewer group recreational activities in general than their peers without autism, further limiting social development opportunities.

“This constitutes a significant gap in social intervention development and service provision, which prompted our interest in developing such a programme for this population,” he says. 

Five weeks, five days a week

The intensive summerMAXyc programme was conducted five-days-a-week over five weeks in the summer. The programme follows a similar model to that of the IAR’s successful, evidence-based summerMAX programme for older children, which has helped improve the social skills of hundreds of children since it began 23 years ago.

In the summerMAXyc programme, each 6-hour day included 8 cycles of 30 minutes each, which began with 10 minutes of instruction in particular skills, such as having a conversation or accepting consequences, followed by a 20-minute cooperative activity.

According to the study, the children found that the programme was fun and helped them learn skills and make new friends. Average child satisfaction was 14.9 out of a possible 15 with parent satisfaction at 69.8 out of a possible 70. Parents reported significant improvement in the children’s social skills, behaviors and autism symptoms.

There is broad consensus that earlier intervention is associated with better outcomes for autistic children. And parents are often the first to recognize the need.

“Parents reach out to us because their child has difficulty navigating the social world,” says Thomeer. “They describe their autistic children as wanting to have friends but not knowing what to do in social situations.”

Families noticed the difference

Over the course of their child’s participation in summerMAXyc, Thomeer says, parents reported that other family members began to notice the child playing with others, not just playing alone. They also noticed that the child now makes eye contact, asks about others, plays games without getting upset and can recognise and understand different emotions.

According to Thomeer, a mother of one of the participants reported that her child not only noticed that she was frustrated about something, but also told her to “squeeze the orange,” a technique the children are taught where they squeeze an imaginary orange and take a deep breath in order to calm themselves down.

One of the study’s major strengths involved the use of objective observers to assess the children’s social performance. According to Lopata, parents are a critical source of information, however there is a risk of bias because they know that their children are in the intervention. Most social skills intervention studies for autistic children rely on parent ratings alone and therefore suffer from this limitation, he adds.

 “Our use of masked observers – trained individuals – eliminated that risk because they were unaware that the children received an intervention,” says Lopata.

The authors also note that the intervention was similarly successful in improving the children’s social performance and autism features regardless of the child’s age, IQ level, communication ability or level of diagnostic symptoms.

“There is widespread recognition in the field that no intervention will be effective for all autistic children and there is a significant need to determine which children are most likely to benefit from a specific intervention,” says Lopata. “Answering this question can help ensure that scarce resources are efficiently allocated and that children receiving a given intervention are most likely to benefit.”

The next step is to test the intervention in a large-scale randomised clinical trial with a control group, which would be a first for such a social intervention in this population. 

Original written by Ellen Goldbaum

Source: University at Buffalo

Psychiatrists Agree on a Diagnosis in Only 55% of Cases, New Study Finds

Photo by Vitaly Gariev on Unsplash

When psychiatrists assess the same patient, they agree on the diagnosis in only about half of cases, according to a new study from the University of Copenhagen. The findings raise concerns about potential misdiagnosis, inappropriate treatment, and errors in psychiatric research.

In the 1970s, psychiatric diagnoses were marked by considerable uncertainty and disagreement. Since then, organisations such as the American Psychiatric Association and the World Health Organization (WHO) have worked to develop standardised diagnostic criteria that psychiatrists around the world can use.

These efforts have shaped modern psychiatry by establishing common, criteria-based systems for diagnosing mental disorders across institutions and national borders.

However, a new study, led by researchers at the University of Copenhagen, suggests that major challenges remain. In the study, 1038 psychiatrists and physicians working in psychiatry from 19 countries were presented with nine written patient case descriptions. Each participant was assigned two cases and asked to determine the most appropriate diagnosis.

The results surprised the researchers.

“Our study shows that when two psychiatrists diagnose the same patient, they will agree only 55% of the time. We consider that worryingly low. In fact, it is similar to the levels reported in some of the studies conducted in the 1970s, which prompted the development of standardised diagnostic criteria in the first place,” says Professor and Consultant Psychiatrist Julie Nordgaard.

“This is not about psychiatrists doing a poor job. Rather, it reflects the fact that, despite the existence of diagnostic systems, clinicians continue to differ in how they interpret symptoms and which features they consider most important. We need a greater degree of consensus, otherwise patients risk receiving changing diagnoses and treatments,” she adds.

Same symptoms, different diagnoses

The study found substantial variation in diagnostic agreement across different mental disorders. Diagnoses within the schizophrenia spectrum proved particularly challenging.

“Cases that could be diagnosed either as schizophrenia or schizotypal disorder generated especially high levels of disagreement. In many of these cases, agreement among participants was well below 50%,” says PhD candidate Mateo Boberg, the study’s first author.

According to Boberg, one reason is that symptoms frequently overlap across psychiatric disorders. For example, obsessive thoughts may occur in both obsessive-compulsive disorder (OCD) and schizophrenia.

“These are not random errors. There is a clear pattern to the disagreements. This likely reflects the fact that diagnostic categories are not as clearly defined as we have assumed, when experienced psychiatrists can interpret the same symptom presentations so differently.”

Diagnostic uncertainty undermines research

Disagreement about diagnoses is an obvious concern for patients. But the researchers argue that diagnostic uncertainty also threatens the reliability of some kinds of psychiatric research¸ explains Professor Mads Gram Henriksen:

“In research, it is essential that we know exactly what we are studying. If a considerable part of participants enrolled in a study on treatment of personality disorders actually suffer from schizophrenia, the study’s results become difficult to interpret. Which condition is the treatment having – or not having – an effect on? Personality disorders or schizophrenia?”

The researchers argue that progress in psychiatric research risks remaining limited until there is a clearer and more widely shared understanding of what mental disorders are and how they can be distinguished from one another. Greater diagnostic agreement, they say, is a prerequisite for the breakthroughs needed to improve patient care.

“WHO’s ICD-10 diagnostic system, which participants in the study used to assess the cases, contains more than 200 diagnoses, a complexity that may contribute to uncertainty. At the same time, many psychiatric conditions are inherently multifaceted,” says Julie Nordgaard and concludes:

“In our view, it is necessary to take a step back and develop more precise descriptions of psychiatric disorders so that clinicians can distinguish them more clearly. It may also be necessary to reduce the number of diagnostic categories.”

The study, Reliability of Psychiatric Diagnoses in the 21st Century, has been published in Frontiers in Psychiatry.

Source: University of Copenhagen

“People Are Crying Out for Help,” Says SADAG, with 460 Suicide Attempts a Day in SA

Photo by Alex Green on Pexels

Every day in South Africa, an estimated 23 people die by suicide, while another 460 attempt suicide.

The impact is particularly concerning among younger people. Globally, suicide is the third-leading cause of death among people aged 15 to 29, according to the World Health Organization’s (WHO) latest estimates.[1] The South African Depression and Anxiety Group (SADAG) is also seeing the extent of the need first-hand as its helplines currently receive between 2 500 and 3 000 calls a day, with around one in four serious suicide-related calls.[2]

“People are crying out for help, and the calls we receive every day show us just how many people are struggling,” says SADAG’s Operations Director Cassey Chambers. “For us to make a meaningful difference and prevent suicides, we can’t just intervene at the point of crisis. People need help recognising the warning signs to make it easier to talk openly about suicide and know where they can turn for help. We need families, friends, schools, workplaces and communities to understand that talking about suicide is crucial and that asking someone directly if they are struggling can open the door to getting them the support they need.”

Every conversation counts

This World Suicide Prevention Day (10 September), Cipla is partnering with SADAG to encourage more of these conversations before someone reaches crisis point. The initiative supports SADAG’s 2026 World Suicide Prevention Day campaign, Every Conversation Counts, which provides South Africans with practical resources to help them understand what to say, how to respond and where to find support.[3]

As part of the campaign, Cipla is introducing the Postcard Wall of Hope, an interactive activation where members of the public can write and share messages of encouragement and support for people they may never meet.

“Sometimes, a few words can mean more than we realise. The Postcard Wall* of Hope is about sharing those words while they can still reach someone, reminding them that their life matters and that it is okay to speak about how they are feeling,” says Paul Miller, CEO of Cipla Africa.

Members of the public can read a postcard, take one that speaks to them or write a message for somebody else to find.

“You don’t have to know who will eventually read your postcard or what they may be going through,” says Miller. “It could simply remind someone that they matter or encourage them to keep going and reach out. The Wall is a way of showing that our words don’t only have to come when it is too late. We can use them now to start conversations and remind people that support is available.”

When to start the conversation

SADAG advises people to take changes in a loved one’s behaviour seriously. Warning signs can include talking about death or suicide, withdrawing from loved ones, risky or self-harming behaviour, giving away personal belongings or a sudden change in mood after a period of depression.[4]

“Importantly, asking somebody directly about suicide does not increase their likelihood of attempting it. SADAG encourages people to ask directly if they are thinking about suicide, listen without judgement and encourage them to seek professional help,” adds Cassey Chambers.

Starting a conversation doesn’t mean you need to know exactly what to say or have all the answers. It can begin with noticing that somebody isn’t themselves and asking how they are really doing. “What matters is that we don’t allow our fear of saying the wrong thing to stop us from saying anything at all,” concludes Miller.

Help is available

Anyone experiencing emotional distress, or concerned about someone they know, can contact SADAG for free telephonic counselling and support:

  • Cipla Mental Health Helpline: 0800 456 789 – free, 24-hour counselling
  • Cipla Mental Health WhatsApp: 076 882 2775 – daily, 08:00–17:00
  • For more mental health and suicide-prevention resources, visit the SADAG website: https://www.sadag.org

*The Postcard wall will be launched during Mental Health month in October as malls in Cape Town, Johannesburg and Durban.

References

[1] World Health Organization (2025), *Suicide worldwide in 2021: Global health estimates*. WHO reports suicide as the third-leading cause of death globally among people aged 15–29.

[2]South African Depression and Anxiety Group (SADAG), World Suicide Prevention Day 2026 media information.

[3] South African Depression and Anxiety Group (SADAG), *Every Conversation Counts: World Suicide Prevention Day 2026*.

[4] South African Depression and Anxiety Group (SADAG), *Understanding Suicide*, suicide warning signs and guidance on supporting somebody who may be suicidal.

More Frequent Cannabis Use Linked to Poorer Mental Health

Research coauthored by a University of Miami Business School professor links more frequent cannabis use to fewer days of good mental health, particularly among men.

Photo by Rodnae Productions on Pexels

More frequent cannabis use is associated with fewer days of good mental health among adults, particularly men, according to a study coauthored by a University of Miami Business School professor.

Michael T. French, professor and chair of the Department of Health Management and Policy, and Weiwei Chen, an economist at Kennesaw State University, examined how cannabis use relates to self-reported overall, physical and mental health. Their study was published in Medical Care Research and Review.

“People have some preconceived notions about alcohol and other drug use, including how they affect individuals, society and governments,” said French. “I believe this paper is another example of how our preconceived notions aren’t always correct, especially when it comes to cannabis use and related policies.”

The study examined the relationship between cannabis use and overall physical and mental health, added French, who has spent much of his career studying substance use policies and risky behaviours.

Cannabis use has become more prevalent as additional states pass medical and recreational cannabis laws. In April, FDA-approved cannabis medications and cannabis sold under state medical licences were moved out of the Schedule I classification they shared with heroin and into Schedule III, a category for drugs with accepted medical uses and a moderate risk of dependence, such as ketamine and Tylenol with codeine.

French and Chen applied statistical techniques to data on cannabis use, health status and other individual characteristics from the 2016–2023 Behavioral Risk Factor Surveillance System. The analysis included adults from 38 states and found that more days of cannabis use were associated with fewer days of good mental health among younger adults, particularly men. Results for adults 65 and older were mixed and often not statistically significant.

The main analyses did not find a consistent relationship between cannabis use and physical health in either age group. The authors caution that this does not mean cannabis use carries no physical health risks.

“Although medical use of marijuana has numerous benefits, the cannabis industry, just like the pharmaceutical industry or the medical-device industry, tends to emphasize all the advantages of their products without a full assessment of the potential consequences,” said French. “Objective academic researchers and other scientists without a predetermined agenda can provide unbiased analyses of the true costs and benefits.

“As articulated in the paper, we are presenting our findings without advocating for a particular policy or law. Policymakers can use our results to formulate more informed initiatives that consider the full spectrum of pros and cons associated with cannabis use.”

By Blair S. Walker

Source: University of Miami

GLP-1s do not Cause Major Psychiatric Harm, Review Shows

Photo by Haberdoedas on Unsplash

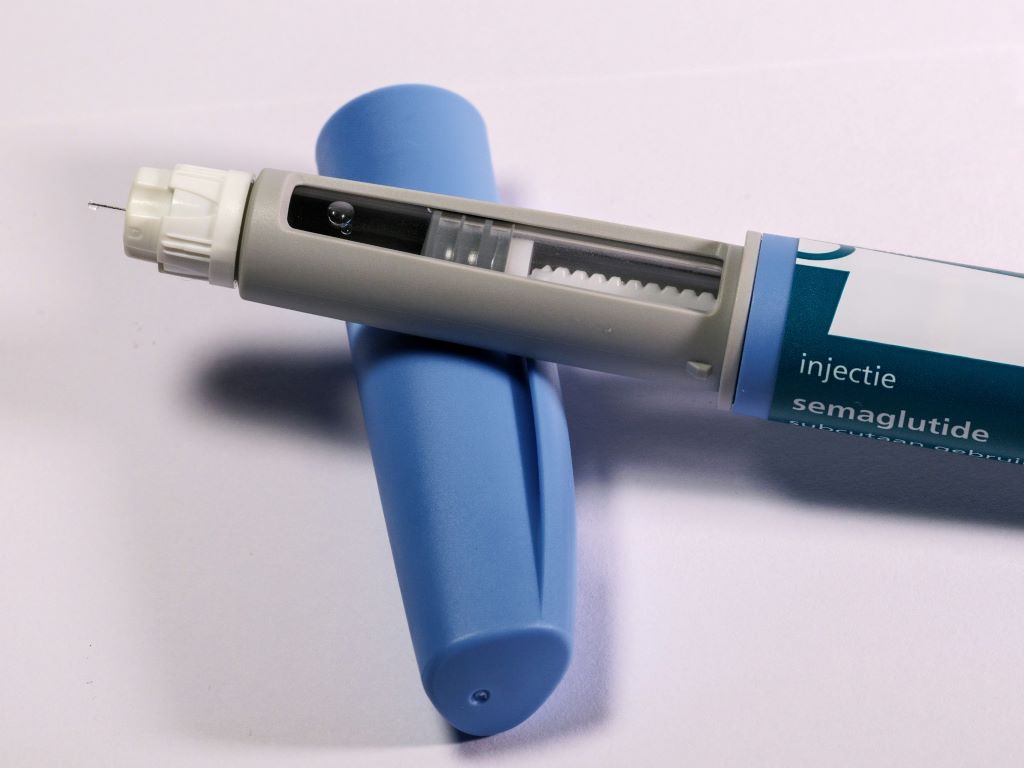
There is no link between the widely used diabetes and obesity medications known as GLP-1 receptor agonists and increased suicidal thoughts, depression or other serious psychiatric harm based on an integrative review of current scientific evidence conducted by researchers at New Mexico State University and the University of Nevada, Las Vegas.

The review, published in the journal Diabetology, traced the earliest concerns raised over GLP-1 RA therapies and found that after subsequent investigations, the medications do not increase psychiatric risk.

“GLP-1 RAs have become a cornerstone treatment for Type 2 diabetes and obesity, now used by tens of millions of patients worldwide,” said Jagdish Khubchandani, a professor of public health at NMSU, who co-authored the study with Kavita Batra, executive director of medical research and scholarly activities at the UNLV Kirk Kirkorian School of Medicine.

Reports that GLP-1s might trigger suicidal ideation, depression or anxiety began appearing  soon after the medications gained mainstream popularity. Those reports then prompted formal safety reviews by the U.S. Food and Drug Administration and the European Medicines Agency, beginning in 2023.

The research team analyzed five years of mechanistic, pharmacovigilance, observational and regulatory evidence to trace how early reports were investigated and how the scientific and regulatory consensus shifted over time. Earlier this year, the FDA removed its suicidality warning from GLP-1 medications.

“When reports of depression and suicidal thoughts first surfaced with GLP-1 RA use, they came from patients and doctors voluntarily reporting what they saw, and such reports can raise a question, but can’t answer it,” Batra said. “Since then, studies following millions of patients, including a pooled analysis of 91 clinical trials, have found no increase in psychiatric risk. But an answer for millions isn’t an answer for everyone. The right response is to screen and check in with each patient, not to take an effective treatment off the table.”

The review found that early warning signals were largely tied to one drug from selected patient groups, while larger controlled studies often pointed in contradictory directions – something the research team attributes to study design rather than the drugs themselves.

Khubchandani said spontaneous adverse-event reports can be skewed by media attention, by the fact that people with obesity and diabetes already have higher baseline rates of depression and suicidality, and by more frequent medical visits among treated patients that create more opportunities for symptoms to be reported. Controlled studies that account for these factors do not show exceptionally high risks, he added.

Still, the review found that some groups using GL-P1s may need closer monitoring. Patients already taking antidepressants or benzodiazepines showed a substantially amplified reporting signal for suicidal ideation, suggesting that any residual risk may be concentrated among those with pre-existing psychiatric vulnerability rather than the general patient population.

“Depression is more common in people with Type 2 diabetes than in the general population, and it works in both directions: Depression makes diabetes harder to manage, and diabetes makes depression more likely,” Batra said. “So, the mood symptoms a patient reports on any diabetes medication may have been there long before the prescription. That’s exactly why asking about mental health should be a routine part of diabetes care, not a special step reserved for when a drug is under suspicion.”

Khubchandani said the pace of research on GL-P1 medications needs to catch up with their pace of usage, particularly among groups like adolescents, those with serious mental illnesses and other groups underrepresented in clinical trials to date.

 “Just like for several other medications, the decision to use GLP-1 RA should include individualized screening of patients for psychiatric history and suicidality before starting treatment, watching more closely for patients with a history of mood disorders or concurrent psychiatric medication use, and educating patients and caregivers to report mood changes promptly,” Khubchandani said.

To read the review, visit https://www.mdpi.com/2673-4540/7/8/144.

Source: New Mexico State University

Digital Wellness Program Eases Anxiety and Depression in Adults with Chronic Health Conditions

A controlled trial across 13 countries found that a self-guided digital program and a version paired with telephone support both outperformed usual care for anxiety and depression

Photo by RDNE Stock project: https://www.pexels.com/photo/an-elderly-man-standing-on-one-leg-on-a-yoga-mat-8173497/

A digital program combining guided movement, breathing and meditation exercises, and coping-skills training reduced anxiety and depression symptoms in adults with chronic medical conditions, according to a new study published August 20th in the open access journal PLOS Medicine by Puneeta Tandon of the University of Alberta, Canada, and colleagues.

More than half of adults living with chronic physical conditions experience anxiety, depression, or fatigue, which can significantly reduce quality of life. Access to effective symptom management support is limited by mobility barriers, geography, cost, and shortages of trained clinicians. Digital programs may offer a scalable way to address this burden, but clinical trial evidence backing these interventions has been limited, and the role of human support in their efficacy is unclear.

Researchers conducted a fully remote, three-arm randomised controlled trial across 13 countries, involving 825 adults with self-reported chronic medical conditions including Primary Biliary Cholangitis, chronic digestive diseases, cirrhosis, and heart failure. Participants were assigned to a waitlist control group, a self-directed digital program (eMPower), or the same program supplemented with weekly telephone check-ins from trained non-clinicians. The program included movement, breathwork/meditation, coping skills, and disease education. Anxiety and depression symptoms were measured using a standard symptom scale ranging from 0 to 42.

At 12 weeks, participants receiving the digital program with telephone support showed significantly greater improvement in anxiety and depression scores than the control group (2.9-point greater improvement; 95% CI, 2.0–3.8). They also reported improved quality of life and less fatigue. In exploratory analyses, the self-directed program alone also significantly improved symptoms compared with control (2.6-point greater improvement; 95% CI, 1.8–3.5), and no significant difference was found between the two program formats, although the trial was not designed or powered to directly compare them.

The study primarily included women with higher education and only measured outcomes for 12 weeks, so longer-term impact and generalisability to other populations remain unclear. However, the authors say the data suggest a path forward for digital mental health interventions.

“Taken together, the eMPower clinical trial provides robust evidence that a fully digital, multicomponent intervention reduced anxiety and depression symptoms and was associated with improvements in fatigue, and quality of life across a range of chronic disease populations,” the authors say. “Rather than developing separate digital programs for each condition, a single cross-condition approach with tailoring for disease-specific education is effective in addressing shared symptoms.”

Corresponding author Dr. Puneeta Tandon states, “As clinicians, we are good at treating organ-specific problems, but the whole-person burden of chronic illness – the anxiety, low mood and exhaustion – that is often where patients have fewer practical options. People often leave the clinic without much they can try, but it doesn’t need to be that way. While these skills don’t replace medication or mental health care when those are needed, they do give people a practical place to start at home.

“What was surprising was that, in an exploratory analysis, we did not find a significant difference between the fully self-directed program and the program with brief weekly check-ins from a trained team member. This does not prove that the two approaches are equal, but it suggests that a program like this may be able to reach far more people without requiring one-to-one support for everyone. Support could then be focused on those who need it most.

“Because the study was entirely online, people could take part from home. The average age was 56, almost one in four participants was over 65, and 84% completed the 12-week follow-up – a strong result for a fully online study. We’re very grateful to the patient partners and organisations representing heart, kidney, liver, transplant and digestive communities who helped shape the program from the beginning. Their involvement was an important part of the study’s success.”

“The 12-Week eMPower program has demonstrated meaningful improvements in quality of life for people living with primary biliary cholangitis (PBC), the largest group enrolled in the eMPower study,” said Gail Wright, a PBC patient and President of the Canadian PBC Society. “Participants living with a significant symptom burden reported clinically meaningful improvements in fatigue and overall quality of life. The success of this program represents an important milestone for the PBC community, providing clinicians with evidence to support more personalised care that combines pharmaceutical treatment with an evidence-based self-management program for people living with PBC.”

First author Emily Johnson, MD/PhD Candidate, notes, “Running the trial entirely online meant we could reach people who are often left out of research – including people managing severe fatigue or mobility limitations, people living far from a specialist centre, and people who can’t add another appointment to their week. What struck me most was that they stayed. Patient partners shaped this program from the first draft, and I think that’s why it held people’s attention for 12 weeks. I look forward to continuing with this work and helping even more people.”

Provided by PLOS

Why a Doctor Saying ‘It’s Normal’ Can Backfire

Research shows that patients often interpret normalising language to mean treatment isn’t necessary, but the misunderstanding can be prevented

Photo by cottonbro studio

Doctors may think they’re saying “Don’t panic.” But many patients hear “Don’t bother” instead.

A new study from the University of California San Diego Rady School of Management suggests that when physicians try to reassure patients by saying their symptoms are ‘normal’, patients may actually infer that treatment isn’t necessary – and become less inclined to seek it.

Published in Nature Human Behaviour, the findings held across 14 experiments involving 9371 participants and a wide range of health conditions, from menopause and migraines to dental pain, seasonal allergies and elevated blood glucose levels.

Why ‘normal’ can send the wrong message

The idea for the research grew from first author Seyi Lawal’s interest in communication around menopause, where patients sometimes report feeling dismissed after being told disruptive symptoms are simply a normal part of aging. Could it be, she wondered, that doctors and patients were interpreting the same conversations differently?

To find out, the researchers conducted 14 studies involving members of the public and healthcare providers. Participants read realistic medical scenarios in which healthcare providers either described symptoms as ‘normal’ or did not. The researchers then measured the participants’ willingness to pursue treatment and compared it with what providers expected patients would do.

“Providers expected that normalising a patient’s symptoms would increase their treatment likelihood, or at worst have no impact, but patients actually reacted in the opposite way,” said Lawal, a doctoral student at the UC San Diego Rady School of Management.

Doctors use ‘normal’, it seems, to mean common and well understood. Patients often interpret it as meaning acceptable – or not worth treating.

Fixing the communication gap, making reassurance work

The findings come amid broader conversations about patients feeling dismissed in healthcare settings, sometimes described as “medical gaslighting.” The study identifies a communication gap that may contribute to those experiences, even when doctors are trying to help.

The good news is that miscommunication isn’t inevitable. The researchers also tested two simple ways to reduce it: pairing normalising language with an explicit recommendation for treatment, and explaining that “normal” was meant in a statistical, not normative or prescriptive, sense.

Both approaches helped close the communication gap.

“Doctors usually have a noble goal. They mean to ease anxiety, but somehow it backfires,” said senior author On Amir, professor of marketing and holder of  the Wolfe Family Presidential Endowed Chair in Life Sciences Innovation and Entrepreneurship at the UC San Diego Rady School of Management. “Doctors shouldn’t stop reassuring patients. But they should make their meaning unmistakable.”

Co-author Brianna Chew, a doctoral student at the Rady School, said the same lesson applies to patients. Hearing that symptoms are “normal,” she said, shouldn’t be taken to mean they are any less serious.

The key takeaway for patients: If you’re unsure what your doctor means when they say a symptom is “normal,” don’t assume it means treatment isn’t recommended and you should just live with it. Ask.

Common symptoms can still deserve attention – and treatment.

Source: University of California San Diego

Can Sports Help Improve Motor Skills in Children with Autism?

Photo by Thao LEE on Unsplash

Research suggests that more than half of children with autism spectrum disorder, a neurodevelopmental condition, experience motor impairments. An analysis in Developmental Medicine & Child Neurology indicates that sports-based interventions may improve motor skills in children with autism spectrum disorder, with martial arts and aquatic training demonstrating the most consistent benefits.

The analysis was based on data from 11 clinical trials of various sports. Martial arts demonstrated consistently large improvements in balance, total motor skills, and object control skills, with especially strong effects in Tai Chi Chuan and kata programs. Aquatic training demonstrated large improvements across balance, locomotor skills, and object control skills. Gymnastics and trampoline interventions demonstrated large improvements in balance and bilateral coordination, with additional effects on total motor scores in trampoline studies. Table tennis produced broad gross motor improvements, and Australian football had a large effect on object control skills and had a medium effect on balance and total motor skills. Across all sports categories, balance was the most consistently improved motor domain.

The authors noted that many of the studies had significant limitations, however, and higher-quality studies are needed.

“Organized sports-based interventions may offer benefits beyond recreation for children with autism by supporting motor skill development,” said corresponding author Sonia Khurana, PT, PhD, of Old Dominion University. “While our review identified promising effects, particularly for martial arts and aquatic training, larger and more rigorous studies are needed to confirm these benefits and guide evidence-based recommendations.”

Source: Wiley

Certain Mental Disorders Are Associated with Faster Brain Ageing

Increased brain ageing was associated with dementia, addiction and psychiatric disorders like schizophrenia

Generated with Gencraft AI

People with dementia, mild cognitive impairment, alcohol addiction, or psychiatric disorders such as schizophrenia show increased brain ageing, each in specific patterns within the brain, according to a study published July 21st in the open access journal PLOS Medicine by Shile Qi from the Nanjing University of Aeronautics and Astronautics, China, and colleagues.

Some conditions can make the brain age faster. Scientists calculate how old the brain is relative to the body using the predictive age difference (PAD), the difference between chronological age and the age predicted by brain imaging, where a positive PAD indicates that ageing is accentuated or increased. To better understand how brain disorders and divergences might affect brain ageing, the authors of this study collected structure magnetic resonance imaging (MRI) data from 45 900 controls across several brain imaging banks, and compared them with those of 2698 patients with different brain conditions and differences, including attention-deficit/hyperactivity disorder (ADHD), autism spectrum disorder (ASD), alcohol or tobacco addiction, Alzheimer’s disease (AD), mild cognitive impairment (MCI), schizophrenia, bipolar disorder or major depressive disorder.

The authors found that neurodegenerative disorders of AD and MCI had the largest association with a high PAD. Addiction and psychiatric disorders were also associated with increased PAD. In contrast, there were no differences in PAD between people with ADHD or ASD and controls.

The researchers also looked at PAD values in specific areas of the brain, and examined which genes showed increased expression in people with different brain conditions. The prefrontal cortex showed higher PAD across brain disorders. Higher PAD in the frontal and temporal lobes was associated with psychiatric disorders, while high PAD in the frontal and occipital cortex was associated with dementia. Addiction was connected with high PAD in the default mode network, and in the salience network and the putamen and thalamus. There were also differences in gene transcription that associated with specific conditions and divergences. While the results are correlational, and not causal, and while some conditions such as psychiatric disorders and addiction have high co-occurrence, the author suggest that understanding more about PAD could help provide biomarkers for commonly occurring brain disorders.

The authors add, “Different neurological disorders appear to leave different signatures on the brain ageing clock, which may help researchers better understand the neural and biological pathways involved in these conditions.”

Provided by PLOS

Emergency Doctors Are Stressed out – And Patient Irritation Plays a Significant Role

Research finds physicians with peevish patients were more likely to become disengaged in the patients’ care

Photo by Usman Yousaf on Unsplash

HBO’s emergency-department drama “The Pitt” has become a smash hit in large part because it shows the deeply human toll that emergency medicine exacts from those who practice it. While researchers have long known that real-life ER doctors are affected by many of the stresses that “The Pitt” has so effectively captured, a recent study led by the University of Massachusetts Amherst and published in BMJ: Quality & Safety is the first to design an interactive and controlled experimental method to test how irritable patients – those displaying frustration or anger – affect the emotions of those treating them, and thus, potentially, the effectiveness of care they receive.

The emergency department has always been one of the most stressful places to work in any hospital – one never knows what sorts of injuries, or how many of them, each shift will hold. Additionally, these spaces have increasingly been on the frontlines of various economic and social crises, including the lack of health insurance and skyrocketing medical costs, immigration and law enforcement and increasing needs for mental health and addiction services. One of the results of all of this is that patients are increasingly irritable, and too often take their frustrations out on caregivers.

“Emotions are an inherent part of our lives – they’re what makes us human,” says Linda Isbell, Feldman-Vorwerk Family Professor in Social Psychology at UMass Amherst and the paper’s lead author. “But for too long, the medical culture has expected doctors to leave their emotions at the door. This is just unrealistic.”

It seems reasonable to conclude that when physicians experience stress in response to patient irritation, the quality of patient care suffers, and there is good anecdotal evidence to support that. But until Isbell and her co-authors, including emergency medicine doctors from the UMass Chan Medical School and the Harbor-UCLA Medical Center, began their study, there were no reliable controlled experiments that had rigorously studied how patient behaviour affects physicians’ emotions and patient care.

For too long, the medical culture has expected doctors to leave their emotions at the door. This is just unrealistic.

 Linda Isbell, Feldman-Vorwerk Family Professor in Social Psychology at UMass Amherst and the paper’s lead author

The team designed a novel approach that began with professional “standardised patients”, people who are specially trained to play patients with realistic, specific medical conditions. Four standardised patients were each trained to perform in one clinical case that corresponded to one of four different diagnoses. Each “patient” was trained to perform two different roles: someone calmly seeking medical care, and someone behaving irritability with their physician. 

“What’s most important here is that each standardised patient, no matter whether they were playing their calm or irritable role, provided the same exact medical details,” says Isbell. “The only thing they changed was their emotional condition.” 

Isbell and her colleagues video-recorded these patient encounters and then recruited 134 emergency medicine physicians from 46 U.S. states. Each physician was randomly assigned a set of four recorded patient encounters, two of which were from calm patients, two from the far more irritable group. 

The physicians were then asked to order clinical tests, for which they received results, and continuously assess their patients, just as they would do in a real-life setting. 

Finally, Isbell and her team asked the physicians to report on their emotional state and engagement with each patient. With this information, researchers examined whether or not physicians’ emotional responses, clinical assessments or clinical behaviours shifted when they were assessing irritable patients versus calmer ones.

What they found is that irritable patients make physicians feel worse. Those physicians reported increased levels of anger, anxiety and fatigue. Doctors were also less engaged in their irritable patient’s care, and much more likely to find their patients unreliable in terms of reporting their own symptoms. Physicians with irritable patients were more likely to interpret their patient’s pain as exaggerated, find them less cooperative, less engaged in their own care or willing to adhere to a treatment plan, and less likely to return to work.

Furthermore, those physicians who were more susceptible to finding medical uncertainty stressful experienced a greater emotional toll when their patients were difficult.

More research is needed to better understand how all of this affects patient care, but, as Isbell put it, “the interaction between a patient’s behaviour and a doctor’s ability to tolerate stress associated with medical uncertainty is critical.” Doctors who are especially vulnerable to stress are likely to experience their difficult patients as more challenging and emotionally taxing – fuelling a cycle that could lead to worse patient outcomes.

“Medicine is inherently uncertain and emotional,” says Isbell, “especially in the ER. We need a systemic shift that acknowledges the human reality of uncertainty and emotions in medicine and supports both doctors and patients as they work toward a common goal: health and well-being for all.”

Source: University of Massachusetts