April 16 2024 – The Chris Hani Baragwanath Hospital School officially opened in its new location today, marking a key milestone in the partnership between Wits University and the academic hospital. The school caters for all learners in need of longer-term and chronic treatment for various paediatric conditions. Learners between Grades R and 12 are taught.
“Sick children have multiple needs, and it’s our duty to ensure that they don’t miss out on any schooling. Everyone deserves the right to be educated and to contribute meaningfully to their communities as adults,” said Professor Shabir Madhi, Dean of the Wits Faculty of Health Sciences.
Professor Madhi noted that the previous school building will be used as a campus for medical students and to grow the university’s teaching and learning footprint at Chris Hani Baragwanath Academic Hospital.
The school district representative for Johannesburg Central, Ronica Ramdath, said that often sick children forfeit their education, which can be mitigated through the correct teaching approach and through supportive facilities. “When I first came to the school some years back, I was amazed at the teachers’ dedication. I remember seeing a teacher load all their educational resources in a bag and walk to the paediatric ward to teach sick children. Today, these children all benefit from such support,” she said.
The Wits Faculty of Health Sciences heads of schools were present, together with hospital and teaching representatives.
Meanwhile, Professor Madhi said that the university’s wifi is available at Chris Hani Baragwanath Hospital, underpinning Wits’ commitment to invest in a world-class academic hospital facility. “We are very proud of our footprint at the hospital and hope to continue to add value through research and clinical work,” he said.
Twenty-five-year-old Amahle is a proud stem cell donor – despite her fear of needles. Photo: supplied.
South Africans in need of life-saving stem cell transplants face an uphill battle due to a high rate of donor attrition. While more than 30 000 South Africans registered as stem cell donors in 2023, a 43% increase year-on-year, more than half of matched donors changed their minds when they received the call.
Palesa Mokomele, Head of Community Engagement and Communications at DKMS Africa, says that donor attrition reduces the chances of survival for many patients. “Unlike other medical donations, such as donating blood, which take place immediately, stem cell donation is a multi-stage process, meaning that those who have registered may be contacted weeks, months, or even years after they have signed up if they are a possible match for a patient. “The uncertainty around whether and when they will be called on to donate therefore impacts donor availability.”
“If notified, they will be asked to undergo confirmatory typing to determine whether they are the best match for the patient and healthy enough to donate. It is usually at this point that they decide whether to proceed with the donation or not,” shares Mokomele.
“Finding a matching stem cell donor is already like searching for a needle in a haystack, so when they choose not to follow through, it further delays the process of locating suitable donors while also increasing wait times for transplants – putting patient survival at risk,” she points out.
To prevent this and help give patients a second chance at life as fast as possible, Mokomele urges those who have registered to regularly update their donor profile to reflect their current health status and availability. “Although it can take some time between registering and receiving the call that you’re a match, it is well worth the wait.”
Twenty-five-year-old Amahle, who recently answered the call, concurs, saying, “I couldn’t believe I was going to give another person a chance to live a healthy life.”
After receiving the news, she underwent confirmatory typing and a preliminary health check. She was also given a detailed briefing call on what to expect.
As with most cases, a Peripheral Stem Cell Donation was required, which is similar to a blood donation in 90% of cases. Blood is drawn and passes through a machine (apheresis machine) that collects the stem cells after which the rest of the blood is returned back into the body. This procedure does not require anaesthetic or admission to hospital and is normally completed within four to six hours. To help Amahle generate sufficient stem cell quantities, she was injected with a hormone-like substance called G-CSF in the lead up to the donation so her body can produce more stem cells for her genetic twin. G-CSF is safe and is a significant part of the process.
Finally, the big day arrived and although she was a ball of nerves (especially given her fear of needles), she pushed through. “I was strong. I knew I needed to continue because soon I was going to save a life.”
“We applaud Amahle’s selfless act. It is moments like these that remind us of the profound impact each individual can have on another’s life. At the same time, however, we are forced to acknowledge the sobering reality that 56% of registered donors drop out. With every registration, there is hope. But hope alone is not enough. Action is what truly makes a difference. We, therefore, urge South Africans between the ages of 17 and 55 who are in good health to not only register as a stem cell donor but to act when the call for donation comes,” concludes Mokomele.
Professor Shabir Madhi of Wits University. Photo: supplied.
The Sabin Vaccine Institute presented the Albert B. Sabin Gold Medal to physician-researchers Keith Klugman and Shabir Madhi.
Nicole Basta, an associate professor at Canada’s McGill University and Canada Research Chair in Infectious Disease Prevention, received Sabin’s 2024 Rising Star Award.
The awards were made on 18 April 2024 at a ceremony in the National Academy of Sciences building in Washington D.C.
Formidable Wits alumni are world leaders in vaccinology
Klugman and Madhi received the Sabin Gold Medal, one of the highest recognitions for vaccinologists globally, for their seminal combined contributions to the development of vaccines against pneumonia and diarrhoeal disease – major causes of death in children in low- and middle-income countries (LMICs).
Klugman is a Wits University alumnus who received an honorary doctorate from his alma mater in 2023.
Madhi, also a Wits alumnus, is currently Professor of Vaccinology and Dean of the Faculty of Health Sciences at Wits University.
The Gold Medal is Sabin’s highest scientific honour. It has been given annually for more than three decades to a distinguished member of the global health community who has made exceptional contributions to vaccinology or a complementary field.
Klugman first met his then-graduate student Madhi at Wits University, where Klugman established, and Madhi expanded, a now globally renowned infectious diseases research institute. Apart from pneumonia, their work focused on maternal and children’s vaccines including influenza, respiratory syncytial virus (RSV), typhoid, and Group B streptococcus (GBS).
The evidence produced by these two awardees has and continues to inform the World Health Organization’s recommendations for vaccines. Klugman and Madhi’s research has helped pave the way for the introduction of lifesaving vaccines in public immunization programs – including the pneumococcal conjugate vaccine where their findings were pivotal in influencing vaccination policy in many low- and middle-income countries (LMICs).
Klugman’s efforts help prevent babies from dying of pneumonia
Fuelled by an early interest in science as a child in South Africa – in part due to a physician father – Klugman holds both a medical as well as a science doctorate degree from Wits University and was the first student in the school’s history to obtain them simultaneously.
He began his research career nearly five decades ago investigating the typhoid vaccine and has since distinguished himself as a formidable infectious diseases’ scientist.
Klugman is widely known for his work on pneumonia, which still kills a child under five every 43 seconds, many in the world’s poorest countries.
As the director of the pneumonia programme at the Seattle-based Bill & Melinda Gates Foundation, Klugman orchestrates strategic initiatives aimed at reducing deaths from pneumonia, RSV, neonatal sepsis, and meningitis.
He has authored hundreds of publications that have been cited over 50 000 times to date and has been elected to the National Academy of Medicine in the United States. He is also a professor emeritus of global health at Atlanta’s Emory University.
His scientific achievements aside, Klugman has long championed the need for the world’s poorest children to have equitable access to vaccines. While in South Africa he joined in Wits University’s struggle to allow access to the institution for all students.
“It is absolutely wonderful to be receiving this award, especially together with Shabir,” he says. “When I look down the list of previous awardees, I recognize the great majority of them, and it is extraordinary to now be numbered among them.”
Past award recipients include leaders of vaccinology and vaccine advocacy such as Drs. Barney Graham, Carol Baker, Bill Foege, Anne Gershon, Stanley Plotkin, and Kathrin Jansen.
Madhi’s research informed WHO recommendations on universal rotavirus vaccination
With a career spanning more than 25 years, Madhi, also from South Africa, is a trained paediatrician whose research continues to be instrumental in prioritising the rollout of vital vaccines and guiding global public health policies. At Wits University, he led clinical trials focused on respiratory and meningeal pathogens, including vaccines targeted at pregnant women and their unborn babies.
Madhi led the first study showing that a rotavirus vaccine could significantly prevent severe diarrhoea during the first year of life in African infants. That research served as a key piece of evidence for the WHO’s recommendation of universal rotavirus vaccination. In addition, he also led the first two COVID-19 vaccine trials in Africa, and a number of COVID-19 epidemiology studies which led to the first evidence suggesting that infection-induced immunity and vaccinations played a role in reducing severity of disease.
In addition to serving as Professor of Vaccinology and Dean of Health Sciences at Wits University, Madhi heads South Africa’s widely respected South African Medical Research Council (SAMRC) Vaccines and Infectious Diseases Analytics Research Unit (Wits VIDA). He is also the co-founder and co-Director of the African Leadership Initiative for Vaccinology Expertise (ALIVE).
He has co-authored hundreds of publications which have been cited over 59 000 times. Madhi is a recipient of numerous lifetime achievement awards in South Africa, as well being bestowed an Honorary Commander of the Order of the British Empire (CBE) from the British Government for his services to science and public health in a global pandemic.
“It is really humbling for me to be acknowledged for my contributions in the field of vaccinology along with those who have received the Gold Medal award,” says Madhi. “It makes me realise that the work my team and I have done is acknowledged by my peers as being of substance. Most significantly, we contributed to protecting lives in those settings where a majority of death and suffering occurs, and that is in LMICs.”
Amy Finan, Sabin’s chief executive officer, says, “I am honoured to award the Sabin Gold Medal to Dr Klugman and D. Madhi for their extraordinary work on vaccines that have saved lives in communities most in need of these interventions. Their pneumonia research has been particularly transformative in shaping our understanding of the disease and strengthening global health strategies to protect children from this vaccine-preventable disease.”
The MOU between SAHPRA and Rwanda FDA will allow the regulators to develop a cooperative partnership towards ensuring access to safe, quality, and effective health products in the respective countries.
Areas of cooperation
SAHPRA and Rwanda FDA will cooperate in joint products reviews and inspections to enable efficient access to health products. The World Health Organization (WHO) has set up an initiative for establishing a mRNA technology transfer hub, together with six spokes, in Africa as a strategy to increase mRNA vaccine production capacity in under-served regions and thus promote regional health security. Rwanda is one of the spokes and South Africa being the hub. Thus, building on this model, SAHPRA and Rwanda FDA will collaborate in the area of mRNA vaccines regulatory oversight.
“The forging of partnerships with fellow African National Regulatory Authorities, namely the Rwanda Food and Drug Authority allows SAHPRA to further our drive in enhancing and building capacity on the continent,” says SAHPRA CEO, Dr Boitumelo Semete-Makokotlela.
“The signing of this MoU underscores the profound potential of collaboration among African NRAs, affirming that the solutions to our shared challenges lie within our continent. Rwanda FDA staunchly believes in the power of collaboration and strategic partnerships. This MoU symbolises the culmination of dedicated efforts and signifies our unwavering commitment to facilitating mutual exchange and enhancing regulatory oversight. Through collaborative efforts with SAHPRA, we aim to strengthen our regulatory capacity and promote public health. As we embark on this journey together, let us harness the collective strength of our agencies to advance the pharmaceutical sector in Rwanda and beyond,” shares Rwanda FDA Director-General, Professor Emile Bienvenu.
In addition to shedding light on what people actually die of, autopsies can also play an important role in helping us to better understand disease. Tiyese Jeranji unpacks tuberculosis-related autopsy research in the Western Cape and delves into some of the fascinating complexities of this branch of TB research.
Figuring out how many people in South Africa die every year of tuberculosis (TB) is not straight-forward. On the one hand, Stats SA’s frequent mortality reports put the number at under 30 000, on the other hand, the World Health Organization (WHO) estimates that it is over 50 000.
While this may at first glance seem like a large discrepancy, there is a simple explanation. The Stats SA figures are based on what is written on death notifications, and these notifications very often do not tell the full story of what a person died of. The WHO estimate, is derived using mathematical modelling that triangulates estimates based on several data sources.
Looking at the numbers from studies that determine the cause of death (or what people actually died of) is one of the ways we know that relying on death notifications result in an undercount of TB deaths. Such autopsy studies have consistently found that many people had undiagnosed TB at the time of death and that the undiagnosed TB was often the actual cause of death.
One review study published in the journal AIDS concluded that “in resource-limited settings, TB accounts for approximately 40% of facility-based HIV/AIDS-related adult deaths” and that “almost half of this disease remains undiagnosed at the time of death”. According to WHO figures, of the estimated 280 000 people who fell ill with TB in South Africa in 2022, over 65 000 were not diagnosed.
Importance of autopsy research
Dr Muhammad Osman, Academic Portfolio Lead and Senior Lecturer: Public Health at the University of Greenwich, tells Spotlight that it is important to do TB autopsy studies because it enables us to identify TB that was not diagnosed during life – and this helps us understand the true burden of the disease.
Osman says identifying TB at autopsies has significant benefits. He says by overlaying health seeking behaviour (how people visit clinics), we can identify missed opportunities for TB screening and design interventions to improve screening for TB. “We could trace family contacts of the deceased and offer TB screening and prevention. This is not taking place at present,” he says.
Osman and his colleagues published a paper in the International Journal of Infectious diseases in 2021 looking at TB in people with sudden unexpected death (SUD) in Cape Town. They found that active TB was identified at post-mortems in 6.2% of the 770 cases they studied. More strikingly, in around 92% of those cases the TB had not been diagnosed while the person was alive.
Osman says that these days there is an increasing awareness of undiagnosed and untreated TB. He points out that new interventions to improve TB testing and diagnosis have been implemented such as targeted universal testing — an approach by which people who do not have any TB symptoms, but who are considered to be at high risk of TB, are routinely offered TB tests.
He says these days healthcare worker risk is considered more carefully and he stresses the importance of protecting forensic and pathology teams. (Forensics focuses on determining the cause and manner of death while pathology is the study and diagnosis of disease through examination of tissue, cells, autopsies, and so on.)
Closing the gaps
Osman says their study also identified a gap between the pathology services and access to routine health service records. “We thought that this is an essential gap to close – the forensic/pathology services need access to routine health service. For a limited number of these deaths we were able to match their records to the public health clinic and hospital records – and many of them had contact with the health services in the six months before death,” he says.
“If forensic pathologists are given full access to the health records, they would know the timing of previous TB and the treatment outcomes of those episodes. The lung changes seen with TB are different in the case of active TB and healed/recovered TB. There are well documented macroscopic (what’s is seen by the examination) and microscopic (seen through histology and microbiology) findings,” says Osman.
A complex disease
The study of TB is complicated by the fact that TB can occur at several stages on a continuum and can impact several different parts of the body.
Professor Threnesan Naidoo, research pathologist at the African Health Research Institute (AHRI), tells Spotlight that when people think of TB, they usually think of the person who’s been coughing for a few months, loss of weight, loss of appetite, having night sweats, and maybe coughing up some blood. “But there’s a journey to that point and then generally beyond that point, and clinically, there’s a continuum of the disease. We refer to it as latent disease, subclinical, active and then healed TB,” he says. It is an area in which things are changing fast – a paper published in the Lancet medical journal last week proposed dividing TB into five stages.
Naidoo says autopsies provide an opportunity to study TB at different stages (latent, subclinical, active, healed) especially when someone with TB dies of another cause. He says they can encounter people at any stage along the TB continuum because at any point someone could be shot, stabbed, or involved in a motor vehicle accident. “You (pathologist) have a unique opportunity to study the effect of TB on cells and tissue physically under a microscope and not through imaging (x-ray),” Naidoo says.
Autopsies also presents the opportunity to look at TB disease not only in the lung, but also the brain, thyroid gland, kidney or urinary system since TB has the capacity to spread everywhere, explains Naidoo.
“Autopsy gives you the opportunity to study TB everywhere,” he says. “Clinically (when someone is alive), you don’t go about investigating the entire body. Neither is it practical nor feasible or safe. But [with an] autopsy you’re examining the entire body anyway. We study TB in totality,” he says.
How it is done
The standard manner of doing an autopsy involves a thorough examination of the body. Naidoo explains that the process starts with an external examination to document injuries, marks, and other physical characteristics that are visible. The internal examination involves dissecting organs, tissues, and body cavities to identify any abnormalities or signs of disease. Samples may be taken for further analysis, such as toxicology tests, histological examination, or TB research.
Any findings from the samples, Naidoo notes, must be interpreted taking into account changes that occur in a dead body. “[In] the living, you know, it’s a living person and they’re able to do things and you’re able to see things on imaging (X-Ray), but in the dead you have to account for the fact that the person has now demised and certain changes occur after death.”
Autopsy study at UCT
An ongoing study at the University of Cape Town is exploring the role of lymph nodes in the spread or containment of TB disease by looking at tissue of the deceased.
Much TB research so far have been done on animals and not on humans, points out Dr Virginie Rozot, research officer at the South African TB Vaccine Initiative (SATVI) and co-principal investigator of the UCT study. “We have great non-human primate and great mice studies that try to underline the mechanism of the disease progression. However, animal models are not a true reflection of what happens in humans.
“For the longest time in these human studies, most studies have been done in the blood and what is happening in the blood has been taken to correlate with what is happening in the lung.”
In short, autopsies allow researchers to look directly at lung, brain and other tissue in a way that simply isn’t feasible in living people.
“So the only way you can actually access tissues is to do post mortem studies. Post mortem studies have been happening since the beginning of last century. And they were like fantastic studies, but the tools were not the same as we have today. I think that should come back to the front of the scene of research because then you can ask all the questions we’ve been trying to answer on what is happening in the tissue by looking into the blood,” she says. “Autopsy allows us to study the exact part we want to study not just the blood.”
Collecting samples
In collaboration with the Western Cape Forensic Pathology Service, UCT has created a postmortem sample collection platform to help with TB research. By leveraging the Inquest Act of 1959, which states that people that die of unnatural causes must undergo a medico-legal investigation to determine the cause of death, Rozot and her team come in to conduct a post-mortem to get their samples. They aim to do the post-mortem in less than 24 hours after death.
Since starting this study about eight months ago, they have done 125 autopsies , with a consent rate of 64%. “I think our consent rate is incredible. We are still putting together our findings to determine how many cases of TB we have found so far by looking at autopsies,” says Rozot.
Representative samples
Dr Laura Taylor, forensic pathologist at the Western Cape Forensic Pathology Services, says the bodies that they look at, in line with the Inquest Act relating to unnatural deaths, are representative of people in South Africa. “However, they are not exactly representative of the entire South African population because there are certain socio economic groups that are more likely to die of unnatural deaths due to increased prevalence of trauma and violence in their communities,” she says.
Because there is no central database, Taylor couldn’t say how many cases of TB they find among the deceased. “[T]here are autopsy records or reports which are written for each case, but there is no central database for TB specifically detected [through] autopsy,” she says.
Forensic autopsy and other diseases
Rozot and Naidoo share the view that, if done well, TB autopsy studies can help shed light on other diseases.
The value of this information is that people dying with or from TB will also have any of the other conditions such as hypertension, HIV, and diabetes, Naidoo says.
“You can work out all those variables… [people] don’t just come with diabetes, the diabetes changes the face of TB, HIV changes the face of TB and TB changes the face of those diseases as well. So, the complexity of it becomes something that we need to pay attention to, and look at all the common variables, like the association of TB and HIV is a big one. So studies might look at HIV infection and how it may affect TB and vice versa. Same with diabetes, hypertension, any of the other non-communicable diseases as well,” he concludes.
The South African healthcare landscape is undergoing a transformative shift, driven by the rapid advancement of technology. At the forefront of this change is the rise of the “digital nurse,” a testament to the increasing integration of technology into the nursing profession. This transformation is not only streamlining processes; it is addressing critical challenges like the nation’s nurse shortage while ultimately improving patient care.
Embracing convenience and accessibility
Virtual platforms have become commonplace in the nursing world, facilitating efficient and accessible professional development for nurses through online meetings, networking opportunities, and educational resources. This fosters a more connected and knowledgeable nursing community, better equipped to serve patients.
Telehealth consultations, another facet of digital nursing currently revolutionising patient care, provide convenient and accessible medical consultations from the comfort of one’s home, eliminating long wait times and unnecessary travel.
Mitigating nurse shortages and ensuring quality care
South Africa grapples with a significant nurse shortage, placing a strain on the healthcare system to which digital nursing offers a practical potential solution. By leveraging technology, nurses can effectively manage larger patient volumes, reducing the burden on the existing workforce and optimising resource allocation. Remote monitoring systems and AI-powered tools further empower nurses by providing real-time patient data and facilitating early intervention, ultimately improving the quality of care delivered.
Additionally, embracing technology ensures that patients, even in underserved areas, receive quality care. The efficiency gained through virtual platforms allows nurses to allocate their time effectively, addressing minor health concerns remotely and reducing the strain on healthcare facilities for non-emergency cases.
However, it must be pointed out that although leveraging technology allows nurses to effectively manage larger patient volumes, which can alleviate the strain on the current system, this doesn’t necessarily mean fewer nurses are needed, but rather that technology empowers existing numbers to reach a wider patient base to deliver more efficient, personalised care.
Evolving alongside technology: the digital nurse of tomorrow
As the healthcare industry embraces digital technologies, the role of the nurse will continue to expand. While traditional nursing skills will remain essential, the “digital nurse” of the future must possess additional competencies. Acquiring proficiency in digital tools and equipment, along with the capability to interpret and analyse digital data, will be crucial for delivering effective patient care. However, the most critical attribute for the digital nurse will be the willingness to adapt and embrace constant technological advancements. This will require a mindset shift that comes with acknowledging that traditional methods might not be sufficient in the face of evolving patient needs.
The challenges and opportunities in change
While the adoption of digital nursing brings numerous benefits, challenges remain. Resistance from individuals accustomed to traditional healthcare practices is one hurdle. However, with the younger generation being more adaptable, the shift towards digital nursing is expected to gain wider acceptance as technology advances. To ensure the success of this digital-first healthcare, it will be necessary to focus our attention on upskilling, which means recognising that continuous training and development programs are vital for nurses to remain proficient in the face of change.
On the flip side, a change in perspective from nursing professionals themselves will be necessary. This means embracing a growth mindset and being open towards new technologies to adapt and thrive in the digital age. Lastly, healthcare professionals as a whole need to bear in mind that transformation is essential to meet the evolving needs of patients, which includes catering to a growing preference for digital healthcare solutions. Continuing to meet the needs of patients is the only guaranteed way for nursing professionals to ensure their relevance in the future. By embracing technology and fostering a culture of continuous learning, South Africa can empower its nurses to become the digital healthcare leaders of tomorrow.
Condom distribution in South Africa has dropped dramatically over the last five years, finds a Spotlight analysis of data recently published in the Health System Trust’s District Health Barometer.
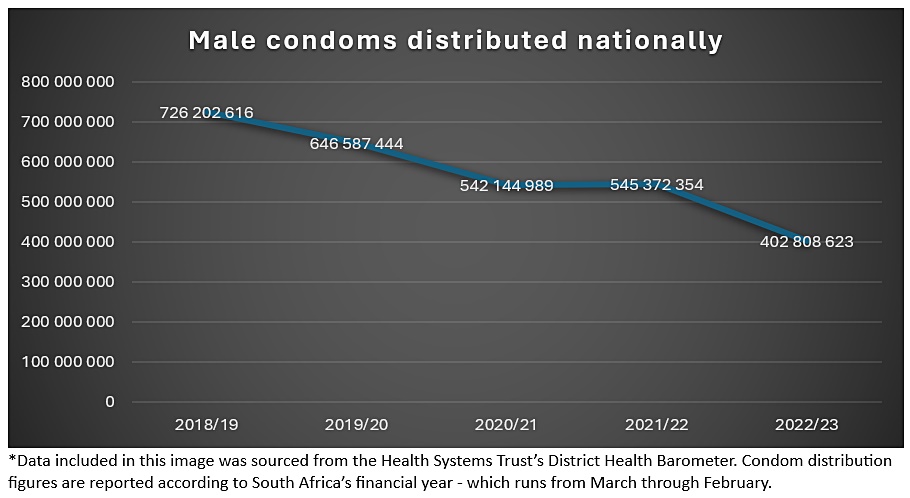
The South African government distributed 45% fewer male condoms in 2022 than it did in 2018. The total number of male condoms distributed dropped by over 300 million from 728 million in the financial year from March 2018 to February 2019 to 403 million in 2022/2023. Female condom supply also declined over this period, but not as sharply.
The full extent of the actual decline in condom supply across the country over the past five years has not previously been reported. The Democratic Alliance, though, did raise the alarm bells about condom supply challenges in Gauteng in April 2023.
Provincial departments of health have pin-pointed the time required for certification of condoms by the South African Bureau of Standards (SABS) following the start of a new condoms tender in 2022 as a key driver of the decline, yet Health System Trust’s District Health Barometer (DHB) data shows that condom distribution figures have in fact steadily declined over the past five years. Similarly, while COVID-19-related supply chain interruptions were a contributing factor to supply shortages at the height of the pandemic, the decline in government supplied condoms started before the pandemic and continued after COVID-19 supply chain disruptions were resolved (as shown in the below graph).
The large decline in condom distribution in South Africa is alarming in the context of the country’s ongoing fight against HIV. While other biomedical interventions are now available to protect against HIV (such as HIV prevention pills), condoms should remain a cornerstone of countries’ HIV prevention strategies according to the World Health Organization.
Research conducted by the University of Witwatersrand’s Health Economics and Epidemiology Research Office (HE2RO) has found that condoms are not only the most cost-effective intervention available to government to combat HIV, but that provision of condoms is in fact cost saving for the country’s health system.
Where did condom distribution fall the most in 2022?
According to the DHB data, all provinces except for the Free State saw a decline in condom distribution in 2022/2023 compared with 2018/19 levels (as shown in the below graph).
The Eastern Cape distributed 65% fewer condoms in 2022/23 than it did in 2018/19, Gauteng and the Northern Cape distributed around 60% fewer, Limpopo 52% fewer, and the Western Cape around 46% fewer. With a reduction of around 19% over the five years, the decrease was much less pronounced in KwaZulu-Natal than in South Africa’s other provinces with large populations.
Male condoms distributed by province
Province
2018/19
2019/20
2020/21
2021/22
2022/23
Eastern Cape
73 672 416
78 817 157
51 122 509
45 839 588
25 490 700
Free State
50 756 150
53 246 000
52 248 000
55 352 800
52 469 700
Gauteng
172 953 486
135 857 486
146 303 254
129 075 303
69 220 678
KwaZulu-Natal
111 028 599
108 503 920
96 529 200
106 967 000
89 664 600
Limpopo
82 563 322
67 818 200
53 325 900
52 862 900
38 910 442
Mpumalanga
67 150 600
51 749 400
38 316 000
31 364 066
35 627 000
Northern Cape
13 934 960
12 959 400
10 825 929
9 518 000
5 194 000
North West
50 820 283
55 579 921
39 841 971
42 361 097
30 810 803
Western Cape
103 322 800
82 055 960
53 632 226
72 031 600
55 420 700
*This table shows a breakdown of male condoms distributed by province, according to data from the Health Systems Trust’s District Health Barometer.
What caused the decline in condom supply?
Condoms are tendered nationally by the National Department of Health for a three-year period. Condoms procured by government must be tested and certified by the SABS before distribution.
Neither the National Department of Health, nor the Gauteng Department of Health responded to questions from Spotlight about the reasons for the decline in condom distribution. However, Gauteng’s Department of Health has previously pinpointed SABS certification processes as the culprit for condom supply shortages in the province. According to an April 2023 media statement by the Gauteng Department of Health, suppliers that received tenders to supply condoms to the public sector were unable to supply condoms to the province while awaiting SABS certification in 2022 – resulting in low condom stock in the province.
Spokesperson for the Eastern Cape Health Department, Sizwe Kupelo, told Spotlight in response to questions for this article that in 2022/23 “for most of the year there were no condoms to distribute”.
Kupelo said that the decline in condom distribution in the Eastern Cape was due to a combination of lags in supply availability while condom suppliers were awaiting SABS certification and challenges in delivering condoms to distribution sites in the province.
“2022/23 was the end of the condom supply contract and the period to award a new contract effective from 1st April 2022. This transition experienced a delay in availing the condoms due the SABS quality assurance process that could be finalised only around September 2022,” said Kupelo, adding that the province started to receive condoms from October of the same year.
“The second reason were related to suppliers who were not finding it easy to deliver to Eastern Cape areas due to the high cost of transportation to the identified 26 delivery distribution sites across the province. Suppliers are all based in Gauteng,” said Kupelo. This matter he said was now resolved.
Kupelo added that condom supply in the province is now improving. He said that the province had reached 96.7% of its target to distribute 17 million condoms in quarter 3 of 2023/24 (quarter 3 of 2023/24 is September to November 2023).
The SABS’ response
Lungelo Ntobongwana, acting CEO of the SABS, told Spotlight that all condoms that are distributed nationally by the Department of Health are tested at the SABS condom laboratory in Groenkloof, Pretoria. “The laboratory is an accredited and dedicated laboratory for the testing of condoms,” he said.
“Downtime or challenges to operations as a result of unplanned disruptions have been experienced on rare occasions and the SABS has incorporated contingency plans to ensure that the testing processes and deliverables would not be negatively impacted.
“The value chain, from the production of condoms to the distribution and usage of condoms, requires the intervention of various role players. When there is a shortage of condoms, it could be due to several reasons and chinks in the value chain. The SABS can categorically state that there are currently no challenges in its laboratory or deliverables regarding the testing of samples,” said Ntobongwana.
Did clinics run out of condoms in 2022/23?
The National Department of Health insisted in April 2023 that while Gauteng was facing low stocks of condoms, there were no serious condom shortages in the country.
Surveys conducted by community-lead clinic monitoring group Ritshidze also show that condoms remained available in most facilities – but not all – throughout the year, but also indicate a pattern of rationing by health care workers and clinics. In some cases, they say condoms are only available in public clinics on request, and key populations often face stigma and discrimination when seeking to access condoms and lubricant.
Surveys conducted by Ritshidze in 2022, found that only 55% of sex workers could get enough condoms at public facilities. Ritshidze recommends that “condoms and lubricants should be available at all facilities and can easily be placed in the toilets or other areas of the clinic where people could take them without the fear of being seen and judged by others, or being told to put some back”.
Anele Yawa, General Secretary of the Treatment Action Campaign (a member of Ritshidze), told Spotlight that the organisation faced challenges in accessing adequate condoms for its community outreach efforts. He said when TAC undertakes community outreach efforts, its members request condoms from public health facilities for distribution in communities but are sometimes told that there are not enough condoms for this.
Yawa added that people seeking condoms from public clinics are often told they can only take a limited number of condoms because of stock availability and that in some clinics “the condom box is empty, there are no condoms”.
Has the decline in condom availability impacted condom usage?
There are some concerning indicators that condom usage in the country is declining, which may in part be related to the drastic decline in condom supply.
The Human Science Research Council (HSRC), which conducts regular surveys of HIV knowledge and sexual behaviour in South Africa, recently released early data from its 2022 survey. The survey showed that teenagers and young adults between 15 and 24 years old reported lower rates of condom use at last sex than in previous survey years. The data presented did not pin-point a cause for the decline – apart from supply constraints, other factors like a decrease in people’s perceived risk of contracting and dying of HIV may also play a role.
The HSRC will release its full survey results in April 2024, which are expected to provide more insight into why condom use at last sex declined among 15- to 24-year-olds in 2022.
Another concerning indicator of declining condom usage is the reported rise in sexually transmitted infections (STIs) in Gauteng. Spotlight reported in February that the worried resurgence in reported cases of STIs in Gauteng in 2023 is a wake-up call that control and management strategies are not keeping pace with the growing disease burden in South Africa’s most populous province.
In response to the increase in STIs, Gauteng’s Health MEC Nomantu Nkomo-Ralehoko recommended expanded, consistent condom use – noting a number of factors including non-use of condoms, inconsistent use of condoms, and the forgoing of condoms by people using Pre-Exposure Prophylaxis (PrEP) as contributors to the rise in STIs. PrEP refers to antiretrovirals taken to prevent HIV infection.
Dismissing the conclusion of a causal relationship between a higher number of people being initiated on PrEP and the higher recorded number of STIs, Professor Linda-Gail Bekker, director of the Desmond Tutu Health Foundation, told Spotlight that there is no evidence to back up the claim that PrEP is leading to lower rates of condom usage. She added that the increase in STI diagnoses may be attributed to increased rates of testing, which has increased in the PrEP era.
“The notion that sexually transmitted infections have suddenly increased in the era of PrEP does not have evidence to support this,” said Bekker, adding “we have no strong evidence to suggest that people are having more condomless sex than before”.
“The value of condoms as a measure against sexually transmitted infections as well as unwanted pregnancy is not disputed and condoms remain the corner stone of the HIV response” said Bekker. “However, we know that for many people, and particularly young women and young men who have sex with men, the choice to use male condoms is not always a given and negotiating condom use may not be easy and can be dangerous,” she said.
Photo by Miguel Á. Padriñán: https://www.pexels.com/photo/syringe-and-pills-on-blue-background-3936368/
Over the last four years South Africa has taken large strides in making HIV prevention pills available at public sector clinics, but uptake has not been as good as some may have hoped. Thabo Molelekwa asks several experts why this might be.
HIV prevention pills, also referred to as oral pre-exposure prophylaxis (PrEP), contain a combination of two antiretroviral medicines. They are highly effective at preventing HIV infection when taken as prescribed by someone not living with HIV.
But while the pills are now available through most public sector clinics in the country, not as many people are using them as one might have expected. According to the most recent estimates from Thembisa, the leading mathematical model of HIV in South Africa, only around 4% of sexually active adolescent girls and young women used PrEP in 2022. This is a substantial improvement on 0.6% in 2020, but given that the rate of new HIV infections in adolescent girls and young women has remained stubbornly high, one may have expected this number to be higher by now.
“So the rates of uptake are definitely increasing in South Africa, but not to the point that we would hope. There’s still definitely a gap between people who would benefit from being on PrEP or alternative HIV prevention methods and those who are actually accessing the biomedical daily oral prevention,” says Cheryl Hendrickson, a Senior Researcher at the Health Economics and Epidemiology Research Office (HE²RO) at the University of the Witwatersrand.
Ongoing stigma
One explanation for uptake not being better is the ongoing impact of HIV-related stigma. A recent study conducted among young people in Gauteng found that stigma and a lack of confidentiality continue to impede PrEP adoption. The researchers identified several barriers for PrEP-naive participants, including limited knowledge, negative staff attitudes, and misconceptions about side effects. Structural factors like healthcare provider bias and a lack of culturally sensitive interventions were also found to hinder PrEP uptake. The research was conducted by HE²RO – Hendrickson was a co-author.
“Participants were worrying about their families or friends thinking they were taking ARVs,” says Constance Mongwenyana-Makhutle, a research associate and co-author of the study.
Professor Linda-Gail Bekker, CEO of the Desmond Tutu HIV Centre, also emphasises the persistent role of stigma. “People don’t want to be associated with HIV, HIV risk or any misconception that they may be living with HIV and on antiretroviral therapy,” she tells Spotlight.
The perception around PrEP, says Dr Fareed Abdullah, Director of AIDS and TB Research at the South African Medical Research Council, is similar to that of contraception. “Basically, a young person would consider it an admission that they are sexually active and consider themselves to be at risk of HIV; thereby inviting judgement and stigma from others, especially healthcare workers,” he says.
Not enough awareness?
Closely related to the issue of stigma is awareness. Here COVID-19 may have played a role. As the provision of PrEP through public sector clinics gained momentum in 2020, many potential PrEP users would have stayed away from clinics due to pandemic-related restrictions and fear of contracting SARS-CoV-2. The pandemic also meant that any plans to build awareness of PrEP would have had a hard time finding purchase, at least in 2020 and 2021.
Reflecting on past HIV awareness campaigns, Bekker stresses the need for increased public demand creation for PrEP
“I think we have not had enough public demand creation- if you think of the campaigns for getting people to take up COVID vaccines….then we really haven’t done enough in this regard. It is a new concept- a pill a day to prevent HIV ……and so people need to have the idea socialised and normalised so that there is also a reduction in stigma,” she says.
What happens at the clinic
Another barrier to PrEP uptake is likely that while PrEP is being made available through public sector clinics, not everyone feels welcome at, or like to visit, their local clinic.
Bekker says youth complain that government clinics are often a barrier for them to access PrEP. “Their hours, their long queues, their discrimination and sometimes the prejudicial attitudes drive young people away,” she says.
Bekker argues that some of these barriers would be removed if HIV prevention measures was taken outside of health facilities and into community spaces.
“PrEP for young people in the public sector is free. If they want to use private pharmacies though, they would need to pay currently. I think more can be done to make PrEP and other sexual and reproductive health services more readily available so that young people, in a way, have no excuses not to make sure they are using them … colleges, universities and even secondary schools could also reach more young people. If we want to reduce STIs and unintended pregnancies in our adolescents, we are going to have to be sure there are very few barriers to these contraceptive and prophylactic services,” says Bekker.
Hendrickson points out that there are several projects around the country that are looking at alternative service delivery methods. “There’s a project that’s looking at prep delivery in pharmacies. Currently, they are providing oral prep, and hopefully soon, they will provide injectable prep within several pharmacies in Gauteng and the Western Cape,” she says. According to her, the pharmacy model appeals especially to men.
Healthcare worker attitudes and training
Related to the issue of visiting public healthcare facilities to access PrEP, healthcare worker attitudes and training has also been flagged as a concern.
Bekker says some health care professionals are not trained to deal with young people in their diversity. “Adolescents are a very distinct population – they can be offended, they value their privacy, and they can make health choices and decisions but need supportive, empathic and tailored information that they can use,” she says.
Abdullah makes a similar point. If some health care workers are properly trained, can identify people at high-risk and understand the efficacy of the intervention, then the vast majority would follow and offer the service in a professional manner, he says.
Ritshidze, a community-based healthcare monitoring group, say they have observed an increase in the number of healthcare facilities where staff say they prioritise offering PrEP to members of key populations such as young women and adolescent girls or men who have sex with men. Of 394 clinic staff surveyed earlier this year, 97% said they prioritise young women and adolescent girls.
But when Ritshidze asked users of healthcare facilities whether they’ve been offered PrEP, the numbers were much lower. “Compared to data collected in 2022, our 2023 data report a lower percentage of people saying they have been offered PrEP for most population groups,” Ritshidze say in a recent report. Complaints about negative staff attitudes have been a running theme in Ritshidze’s reports on public sector healthcare facilities over the last three years.
Actual and perceived risk
Abdullah suggests another barrier to PrEP uptake. There is a perception that HIV is no longer an urgent priority and that the risk of infection is low. This, he says, has led to lower public awareness of the importance of behaviour change and the need for young people at risk to protect themselves.
Recent data from a Human Sciences Research Council survey and the District Health Barometer indicate that condom use is declining in South Africa. While the reasons for the decline are not clear, one theory is that it is driven by the perceived risk of HIV infection having reduced over time.
Will more choice help?
Currently only oral PrEP is routinely available in the public sector, but PrEP in the form of a two-monthly injection and a monthly vaginal ring have been approved by the South African Health Products Regulatory Authority and is being offered to people taking part in pilot projects. It is likely that the prevention injection will become much more widely available once its price drops sufficiently – which is anticipated to happen once generic manufacturers enter the market in around three years’ time. Products that combine PrEP and a contraceptive into a single pill or injection are also under development.
Mitchell Warren, director of Avac, a global HIV advocacy organisation, is optimistic about people being offered a choice between the three types of PrEP. While condoms were widely available in public clinics in the 1990s, Warren says he noted the desire of people to buy condoms from spaza shops, shebeens, or pharmacies. This didn’t replace clinic supplies, he clarifies, but it did bring into sharper focus the importance of providing choice to people.
“But even with three different PrEP options, what we clearly have known for many years now is that PrEP is not only about the products, PrEP is really a programme, helping people identify not just their personal risk, but their desires, what they want and need out of relationships,” he says.
Government perspective
Foster Mohale, spokesperson for the National Department of Health, says the department is aware of reports of youth experiencing problems accessing PrEP at healthcare facilities.
Mohale maintains that healthcare workers are sufficiently trained to provide comprehensive HIV prevention services to all groups of people. He says that clinicians, counsellors, health promotors and peer educators have access to online training platforms. “These training modules are availed offline on flash drives to facilitate access to facilities and health care providers that do not have easy access to wifi or data to access the online version of the training materials,” he says.
A massive and long-awaited study of an experimental tuberculosis vaccine has kicked off in South Africa. Marcus Low reports.
Photo by National Cancer Institute
By Marcus Low for Spotlight
The first jabs in a much-anticipated clinical trial of an experimental tuberculosis (TB) vaccine have been administered at a clinical trial site at the University of the Witwatersrand in Johannesburg. Up to 20 000 people are anticipated to take part in the study, according to study sponsor, the Bill and Melinda Gates Medical Research Institute (Gates MRI).
The study will be conducted at 60 different sites in South Africa, Zambia, Malawi, Mozambique, Kenya, Indonesia, and Vietnam. The researchers estimate that between 50% and 60% of the study participants will be in South Africa.
The experimental vaccine called M72/AS01E (M72 for short) made waves in 2018 and 2019 when it was found to be around 50% effective at preventing people with latent TB infection from falling ill with TB over a three-year period in a phase 2b clinical trial. In June 2023, it was announced that, after some delays, $550 million in funding had been secured for a phase 3 study of the vaccine. Medicines or vaccines are typically only registered and brought to market after being shown to be safe and effective in large, phase 3 clinical trials.
While most cases of TB can be cured using a combination of four antibiotics for four or six months, TB rates are declining relatively slowly and it is widely thought that an effective vaccine would help bring TB rates down much more quickly. The World Health Organization estimates that at the level of protection seen in the phase 2b trial, the vaccine could potentially save 8.5 million lives and prevent 76 million people from falling ill with TB over a 25-year period. The one TB vaccine we already have, called bacille Calmette-Guerin (BCG), is over a century old and only provides limited protection against severe illness for children and no protection for adolescents or adults.
“Reaching Phase 3 with an urgently needed TB vaccine candidate is an important moment for South Africans because it demonstrates that there is a strong local and global commitment to fight a disease that remains distressingly common in our communities,” said Dr Lee Fairlie, national principal investigator for the trial in South Africa, in a media statement released by Gates MRI.
“South Africa also has considerable experience with TB- and vaccine-related clinical trials and a strong track record for protecting patient safety and generating high quality data essential for regulatory approvals.”
Fairlie is also the Director of Maternal and Child Health at the Wits Reproductive Health and HIV Institute at Wits University.
The initial response from TB activists was positive.
“TB Proof (a South African TB advocacy group) is delighted that the M72 phase 3 trial has been launched,” the organisation’s Ruvandhi Nathavitharana and Ingrid Schoeman told Spotlight. “Having an effective TB vaccine is critical for TB elimination efforts.”
While he said it is good to finally see the phase 3 trial of M72 get underway, Mike Frick, TB co-director at Treatment Action Group, a New York-based TB advocacy organisation, went on to say:
“The fact that we had to wait so long between phase II and phase III says everything one needs to know about the headwinds – financial, political, commercial – that TB research is up against.”
How the study will work
Half of the up to 20 000 study participants will receive the M72 jab and the other half a placebo. The vaccine is administered as two intramuscular injections given a month apart. After being jabbed, study participants, all aged 15 to 44, will be followed for four years from the date of the first study participant being enrolled to see if they fall ill with TB.
“The plan is to complete enrolment in 2 years,” Fairlie and Alemnew Dagnew, clinical lead for the trial, told Spotlight in response to written questions. They explained that the actual duration of the trial will depend on how long it takes for 110 people in the study to fall ill with TB. According to the Gates MRI statement, the study is expected to take around five years to complete.
According to Fairlie and Dagnew, the majority of study participants (around 18 000 people) will be people who are HIV negative and who have latent TB infection – that is to say people who have TB bacteria in their lungs, but who are not ill with TB. Latent TB infection is thought to be very common in South Africa and only around 10% of people with latent infection ever fall ill with TB. In the study, latent infection will be tested for using a type of test called an IGRA (Interferon-Gamma Release Assay).
Around 1000 HIV negative people with no TB infection will also be recruited to the study. This is being done to make sure the vaccine is safe and effective in this group of people – while latent infection will be tested for in the study, in the real world such testing may not always be feasible prior to vaccination.
It is anticipated that 1000 of the 20 000 study participants will be people living with HIV. Establishing how well the vaccine works in people living with HIV is important since around 13% of people in South Africa are living with HIV and HIV substantially increases the risk of falling ill with TB. The main phase 2b study of M72 did not include people living with HIV although another phase 2 study looked specifically at the safety and immunogenicity of M72 in people living with HIV – according to Fairlie and Dagnew, “that trial “was completed and supported the inclusion of such participants in a phase 3 trial”.
Smaller than previously thought
When funding for the phase 3 trial was announced last year, it was estimated that 26 000 people would participate in the study. That number has now been revised down to 20 000.
“As a result of ongoing discussions between the institute and our funders, the decision was taken to review the study protocol with the intent of simplifying the study given its size and complexity. This will not affect the safety of the trial. It is common to continue to refine a protocol. We found a way to expedite the study that would potentially allow us to offer the public health impact of this vaccine to those in need sooner. All partners, including the trial funders, are fully aligned to the protocol refinements,” Fairlie and Dagnew explained to Spotlight.
“Some assumptions used to inform the design of the first protocol were deemed overly conservative, so the clinical team used slightly less conservative assumptions on vaccine efficacy and TB incidence rate, thus allowing for a reduction in the number of participants in the trial, while still retaining the primary goal of confirming the safety and efficacy of the M72/AS01-E-4 vaccine for prevention of TB, guided by the final results of the phase 2b study completed several years ago.”
Planning for access
The development of M72 has taken a somewhat unusual path – with the pharmaceutical company GSK leading development up to the end of phase 2b and then largely passing the baton to Gates MRI with the conclusion of a licensing deal in 2020. GSK has come in for some criticism for not moving more quickly after the initial publication of the phase 2b results in 2018. A ProPublica article published last year suggested that the development of M72 slowed because GSK were focussing on more profitable vaccines.
According to the Gates MRI statement, GSK continues to provide technical assistance to the Gates MRI, supplies the adjuvant component of the vaccine for the phase 3 trial, and will provide the adjuvant post licensure should the trial be successful. An adjuvant is an agent included in the vaccine that improves the immune response elicited by the vaccine – in the case of M72/AS01E the AS01E refers to the adjuvant made by GSK.
This ongoing dependence on a single company for the adjuvant has some activists worried. “We are concerned about reports that scaling this vaccine may be difficult due to limited availability of the vaccine adjuvant. Access for everyone who needs it should be part of the early phases of the research process – not an afterthought,” said Nathavitharana and Schoeman.
“The press release announcing the study’s start in several places refers to the ‘complexity’ of ‘developing and ensuring access’ to a new vaccine. Part of the unspoken complexity here is the opaque licensing deal GSK and Gates MRI signed in 2020 in which GSK gave rights to develop and commercialise M72 to Gates MRI while retaining control over the AS01E adjuvant,” Frick told Spotlight. “There are legitimate concerns that the fine print of this arrangement could work against equitable access, but terms of the licence remain unknown to the public.”
When asked about supply concerns, Gates MRI told Spotlight: “Gates MRI collaboration with GSK includes provisions to ensure there is sufficient supply of adjuvant for the clinical development and first adoption in low-income countries with high TB burden, at an affordable price, should the vaccine candidate be successful in phase 3 trials and approved for use. For broader implementation, GSK has committed to working with its partners to ensure there is sufficient supply.”
Disclosure: The Gates MRI is a non-profit subsidiary of the Bill and Melinda Gates Foundation. Spotlight receives funding from the Bill and Melinda Gates Foundation. Spotlight is editorially independent and a member of the South African Press Council.
Dr Siya Mjwara, founder of the AskDrSiya Psychotherapy and Wellness Coaching Practice, has just launched the first online recovery school in South Africa. The Recovery School will support individuals in identifying and confronting their challenges and businesses in developing and implementing wellness solutions in order to reduce absenteeism and improve productivity, as well as overall workplace culture. Dr Mjwara will provide a supportive and transformative environment where healing and growth are possible for all.
She says, “We create a virtual sanctuary where individuals can find healing, empowerment and community support. We strive to cultivate a space where you can reclaim your life and thrive, no matter what you’ve been through.
“After 17 years of working with individuals, couples and families, I can say, without a doubt, that we South Africans are a traumatised nation. Unfortunately, many of us are completely unaware of how our traumas are negatively impacting our lives, as well as the decisions we take on a daily basis. Recently, I’ve been hearing people say, “avoid dating anyone who has never been to therapy”. This is an indication that more of us are recognising how unresolved trauma can negatively impact our relationships.
“Besides our personal experiences, such as childhood trauma, relationship, family and workplace traumas, many of us are still dealing with the effects of intergenerational trauma.
This is part of the background that informs the vision for The Recovery School. My wish is for individuals to not only cope with trauma, but also to be able to thrive and become the best version of themselves. It takes courage to face your fears and begin living authentically, and you don’t need to walk the journey alone.
The school’s programmes are primarily designed to enable individuals to
Rediscover themselves
Break free from limiting beliefs
Cultivate resilience
Forge meaningful connections
Live fully in the present
Achieve their goals
Dr Mjwara BSW Hons (UWC), MA FCS (UWC), Dphil (UNIZULU) can be contacted on Ask@DrSiya.co.za or 079 772 1950.