Men make up just 28% of potential blood stem cell donors on a registry of more than 210 000 in South Africa, despite growingevidencethat younger male donors can play an important role in successful transplant outcomes.
Women outnumber men by more than two to one on the registry, highlighting a significant need for greater male representation. Young men aged 17 to 25 account for just 11% of registered donors. Although men’s share of new registrations has risen from 19% in 2021 to 31% in 2025, they remain significantly underrepresented. Yet men accounted for 40% of the 42 stem cell donations collected from the registry in 2025.
Research suggests that donor age and sex can influence transplant outcomes. A study of more than 10,000 unrelated donor transplants found that male and younger donors were associated with improved event-free survival, with researchers recommending male donors aged 18 to 30 when several suitable donors in that age group were available. A separate analysis of 452 transplant patients also linked male donors to better overall survival and faster platelet recovery. Other research has revealed that men also tend to yield larger numbers of stem cells.
Yet, despite being underrepresented on the registry, men accounted for 40% of the 42 stem cell donations facilitated through the registry in 2025.
“When a transplant team searches the registry, age and other characteristics can influence which suitable donor they select,” says Palesa Mokomele, Head of Community Engagement and Communications at DKMS Africa. “On International Men’s Day, we’re encouraging more men to register and learn about what’s involved in donating stem cells.”
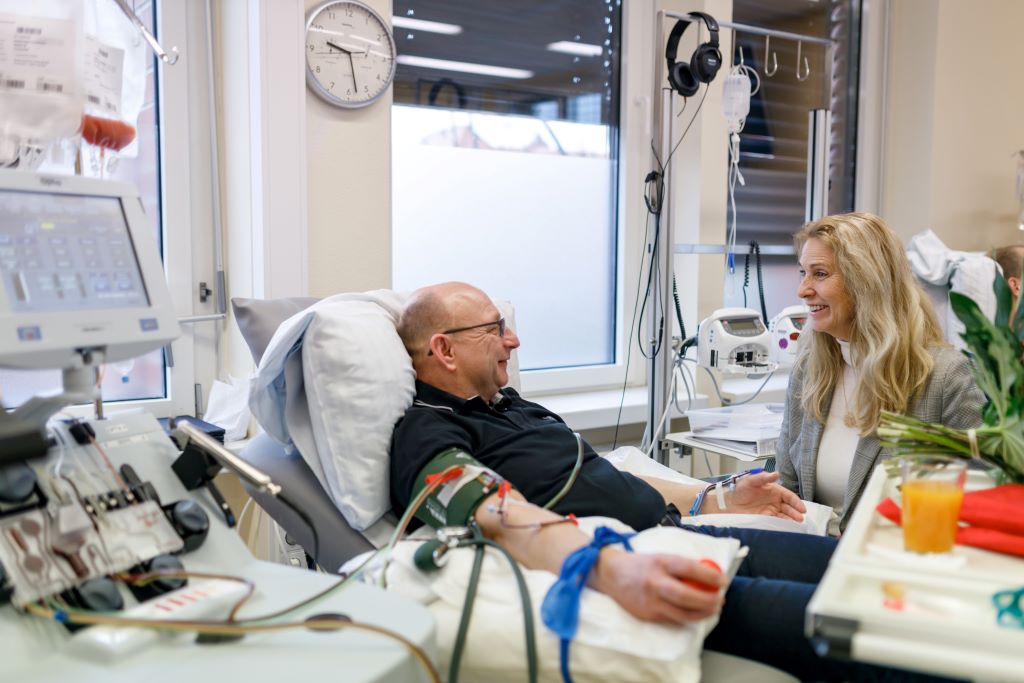
She says misconceptions about the process, along with concerns about taking time off work, can discourage potential donors. “Some men assume that donating stem cells means undergoing surgery, or worry that they can’t afford to take time off work. In most cases, stem cells are collected from the bloodstream through a procedure similar to donating blood, and DKMS Africa covers the costs associated with donation.”
Former Springbok Jaco Pretorius once shared some of these misconceptions. He registered as a donor in 2018 after watching his best friend’s life being saved by a stem cell transplant. Four years later, he was identified as a match for a patient.
“My experience is that people are not aware of the great need in our country and the simplicity of the process,” he explains. “The perception is that it is a painful procedure which carries personal risk. My personal experience was the complete opposite, which I try my best to communicate as far as possible to potential donors.”
After blood tests and medical checks, Pretorius donated through peripheral blood stem cell collection. The procedure took a few hours, and he experienced no side effects. He later learned through DKMS Africa that the transplant had been successful, and that the recipient was healthy.
“That was one of the best feelings, to know that through such a simple action, someone else’s life was saved,” he recalls.
Pretorius now hosts donor registration drives along with DKMS Africa to encourage others to join the registry. However, Mokomele stresses that signing up is only the beginning. “Joining the registry is incredibly important, but it doesn’t end there. If you’re identified as a potential match, we need to be able to reach you. Keeping your contact details up to date and being willing to donate when the time comes could make all the difference to someone waiting for a transplant.”
South Africans aged 17 to 55 who meet the health requirements can register at www.dkms-africa.org/register-now, while existing donors can update their contact details here.
For more information, contact DKMS Africa on 0800 12 10 82.
An illustration of blood glucose monitoring, an important aspect of diabetes management and the prevention of complications. Source: Pixabay CC0
PRETORIA – Diabetes has remained South Africa’s leading underlying natural cause of death for three consecutive years, claiming nearly 29 000 lives in 2024 alone. A University of Pretoria (UP) public health expert is calling for urgent action to strengthen healthcare and prevent avoidable deaths.
According to the latest Statistics South Africa mortality report, 28 767 South Africans died from diabetes-related complications in 2024. This represents 6.1% of all recorded deaths, or about 79 people every day.
Diabetes was also the leading underlying natural cause of death in 2022 and 2023, with 33 126 and 27 967 deaths, respectively.
“These numbers cannot be accepted as South Africa’s new normal,” he says. “Diabetes is mostly preventable and manageable. With timely support, people can lead long, healthy lives free from preventable complications.”
Diabetes is a chronic condition in which the body cannot properly regulate blood sugar levels. Without appropriate treatment, it can cause life-threatening complications affecting the heart, kidneys, eyes, and blood vessels.
Women and working-age adults are most at risk
The national statistics reveal significant inequalities in the burden of diabetes.
In 2024, diabetes claimed 17 429 women’s lives, accounting for 7.9% of all recorded female deaths. Among men, it caused 11 334 deaths, representing 4.5% of male deaths.
Working-age South Africans are also particularly vulnerable. Diabetes was the leading natural cause of death among people aged 45 to 64, accounting for 9 364 deaths, or 7.9% of deaths in this age group.
It also ranked as the leading natural cause of death in five provinces: Gauteng, KwaZulu-Natal, Western Cape, Eastern Cape, and Limpopo.
The findings reflect a broader national health challenge, with noncommunicable diseases, including diabetes and cardiovascular conditions, accounting for 60.7% of all recorded deaths in 2024.
Why better healthcare could save lives
Dr Ngassa Piotie argues that mortality statistics tell us how many lives have been lost to diabetes, but reveal little about the circumstances surrounding those deaths, including whether they could have been prevented through earlier diagnosis, timely treatment, and better-quality care.
“We should not wait until people die to identify where our health system is failing them,” he says. “We must use the evidence available today to improve care, prevent avoidable complications, and save lives.”
Death certificates cannot reveal whether patients received timely diagnoses, had reliable access to medication, or were regularly monitored for complications.
Through UP’s Tshwane Insulin Project, researchers have demonstrated how nurse-led care can help patients with type 2 diabetes start and adjust insulin treatment at primary healthcare facilities, supported by follow-up care at home.
“Survival rarely hinges on high-tech interventions,” Dr Ngassa Piotie says.
Instead, effective diabetes care depends on trained healthcare workers, reliable medicine supplies, regular screening, continuous monitoring, and support that accommodates patients’ everyday circumstances.
From policy to action: Preventing avoidable deaths
South Africa’s National Strategic Plan for Non-Communicable Diseases includes targets known as 90-60-50. These aim to ensure that 90% of adults know their blood pressure and blood glucose status, 60% of those with elevated levels receive treatment, and 50% of those receiving care achieve clinical control.
However, translating these commitments into effective healthcare remains a challenge.
Dr Ngassa Piotie advocates for the establishment of a national diabetes registry and the integration of digital health systems to track patients from diagnosis through treatment, identify those who discontinue care, and monitor complications.
He identifies three immediate priorities: connecting early diagnosis to sustained treatment, measuring healthcare outcomes across districts and provinces, and addressing socio-economic barriers such as food insecurity, transport costs, and limited healthcare access.
For Dr Ngassa Piotie, preventing avoidable diabetes-related deaths requires more than awareness campaigns. It demands a coordinated national response that ensures patients receive the continuous care they need.
“People living with diabetes must help define what quality care looks like,” he says.
Menopause, defined as a year with no periods, marks the end of a woman’s reproductive years. Photo by Ayo Ogunseinde on Unsplash
Across the country’s townships and rural clinics, women are breaking inherited silences to redefine reproductive ageing on their own terms.
In South Africa, women are challenging the silence around menopause, and the expectation to endure it without support.
This is significant because research suggests that some women in South Africa never discuss menopause with a healthcare worker. In a 2017 study of 450 black women in communities near Pretoria, more than three-quarters had never sought medical help for their symptoms, possibly, researchers argue, because of a cultural view of menopause as a positive natural process.
Menopause, defined by the World Health Organisation (WHO) as a year with no periods, marks the end of a woman’s reproductive years. It’s a natural transition brought on as the ovaries stop releasing eggs and oestrogen levels fall, usually between the ages of 45 and 55. Joint and muscle pain, exhaustion, poor memory and hot flushes are among the most common symptoms, but a new review suggests there are up to 72 possible symptoms.
Hormone replacement therapy is the most effective treatment to ease hot flushes, according to South African Menopause Society (SAMS) guidance, but whether it’s the right choice will depend on each person’s medical history and preferences.
After researching women’s perceptions of menopause in Gauteng and North West, researcher Sostina Matina now believes that the limited use of menopause treatments in South Africa’s public healthcare sector should not be mistaken for a rejection of clinical care. Many women, she says, had simply never had their options explained to them.
Xoli Madlala, who experienced menopause early, has made it her personal mission to bring menopause out into the open. She travels across the country, speaking in settings ranging from corporate boardrooms to rural Bible study groups.
Wherever she goes, she says, women of different ages are open to talking about a subject that previous generations were often expected to endure without discussion.
How clinic staff can fuel midlife myths
Midlife women seeking menopause symptom relief are often turned away by health workers, Matina says, especially if they’re experiencing symptoms earlier than usual or as a result of surgery.
“They’ll say ‘it’s just menopause, there’s nothing we can do’,” she says.
The country’s treatment guidelines for clinics and hospitals include menopausal hormone therapy pills that can ease hot flushes and other symptoms. Women who have had a hysterectomy can usually be prescribed pills with only oestrogen. Those with a womb also need to take progestogen because oestrogen on its own can cause the uterine lining to become too thick, which can increase the risk of cancer.
Hormone patches, which deliver hormones through the skin, are not on South Africa’s essential drug list, but they are listed as alternatives if the pills don’t work well for a particular patient or as an alternative when pill stocks are low, which a report by the National Essential Medicines List Committee suggests happens often.
Professor Lineo Matsela, an obstetrician, gynaecologist and president of SAMS, says it’s become common for public sector doctors to write prescriptions for menopausal hormone treatments so that patients can buy them at a private pharmacy.
Over the past three years, however, there have also been sporadic private sector shortages of menopausal hormone therapy treatments.
But access to medicines is only part of the problem, Matina says. Dismissing menopause can also mean the health system could be missing other health risks that can impact women in midlife, a phase that can span about 40% of their lives.
The transition is also associated with bone loss, and the stakes might be slightly higher for women living with HIV. Over five years, a Soweto study found a greater loss of bone-density among women living with HIV compared to those without HIV, though there wasn’t a difference in fractures between the two groups. Researchers didn’t have information on which HIV treatments participants were taking so they couldn’t untangle the effects of HIV itself from the possible impact of tenofovir, which is part of first-line HIV treatment and can contribute to bone loss.
US research suggests there could also be links between HIV, menopause and heart disease and an African study found higher rates of the “bad” kind of cholesterol after menopause regardless of HIV status.
Loss and liberation
People’s experiences of menopause vary widely across countries, cultures and generations.
Women in four rural villages in Limpopo, for instance, described menopause to researchers as a series of losses, of beauty, respect and quality of life even though older people were generally regarded as important veterans who deserve respect regardless of gender.
In some instances, researchers found that elders enforce a culture of silence about menopause. One premenopausal woman explained: “At the girls’ initiation when we were still young, old women told us blood will cease and since then no one ever talked to me about it. That is why I say it is my secret.”
In interviews at two Mamelodi clinics, researchers heard accounts linking pain and weight gain to blood that was no longer flowing out. “I do not know where this blood goes,” one participant said.
In a 2013 discussion of menopause and marriage, theologian Elijah Baloyi described a belief among Tsonga-speaking people that sex after menopause could cause semen to accumulate and a woman’s abdomen to swell.
In Johannesburg’s Soweto township, Matina found many postmenopausal women held beliefs about dirty blood, some saying they withdrew from sexual intimacy entirely or accepted the end of their intimate relationships.
For others, menopause brought liberation from the monthly financial burden of sanitary pads, or elevation to the level of an elder who could commune with ancestors.
Research conducted in South Africa and Zimbabwe suggests that inter-generational support can make all the difference to help women approach the milestone with acceptance.
One woman, who initially worried the changes she was experiencing were signs she could be dying, was calmed by her mother’s reassurance and positive outlook. Another told researchers: “[Menopause] is something I am looking forward to, why, because I am getting old. Yes, if time permits and if God allows it, with life, it’s okay.”
Language mirrors a society’s worldview, and where Western medicine isolated a clinical hormonal deficit, African linguistic traditions instead describe social shifts.
When clinical concepts are translated literally into local languages, they often produce phrases steeped in shame, stigma, or perceived uselessness such as kuguma ura (no longer bearing) in Shona or phelelo maikutlo (the end of one’s feelings) in Setswana.
In response, women may express their bodily changes through idioms and euphemisms, describing hot flushes as fufulelwa or framing the transition socially as ugugile (she has aged), sekhulile (growing older), or into zabogogo (grannies’ stuff).
Because nursing and medical school curricula spend little time on multicultural health communication or the endocrinology of ageing, Matina argues clinic staff frequently misinterpret these cultural expressions or fail to engage with them altogether.
“You know, I don’t know menopause properly… because sometimes people speak in such big English, so you don’t understand it, unless someone explains it to you”, an older woman in Soweto told researchers.
From stigma to selfhood
When researchers set out to learn about midlife health across South Africa and Zimbabwe, they discovered that women want something different from what their public health systems currently offer.
The women described leaving clinics without accessible information and with lingering physical distress or anxiety over health risks.
When asked what would help, participants explicitly requested clear, contextually relevant information so they could understand their bodies and take charge of their own health regardless of their access to more expensive hormone therapies.
The result is a series of question-and-answer booklets co-created with communities, doctors, translators and designers, which reflect the women’s firm rejection of the “old granny” stereotypes.
The participants banned old-fashioned dresses, which they felt aged menopausal women, and insisted on vibrant, modern images of smiling, active women. Also banished were medical jargon and deficit-based translations of “menopause”.
Instead, they opted for culturally relevant terms of dignity and strength such as Ubufazi in isiZulu and Sesadi in Setswana, both of which simply mean “womanhood”.
Doctors and supporters of unemployed medical professionals protest outside the Natalia Building in Pietermaritzburg, calling for action on doctor unemployment. (Photo: Supplied)
By Sue Segar for Spotlight
They are qualified, ready, and willing to serve their communities. But scores of these doctors in KwaZulu-Natal, are becoming increasingly desperate because of a lack of posts in government hospitals and clinics.
Dr Tholumusa Sibiya remembers, as if it were yesterday, the day, in 2015, when a group of young doctors visited his school in Ingwavuma, KwaZulu-Natal to urge talented pupils to apply to university to study medicine and other health disciplines.
The doctors were from Mosvold Hospital where manager, Dr Andrew Ross, had started a fund to encourage local pupils to train in medicine and return to serve in their communities.
“The message from these young professionals was, ‘yeah, it’s doable. You can also study medicine. And you’re needed.’ That really inspired me,” says Sibiya, who was the top pupil in matric at Nansindlela Combined School.
He knew about Mosvold Hospital because his father worked in the mortuary, and his mother in the laundry services there. But, till then, it hadn’t occurred to him he could be a doctor there some day.
“One of the doctors said something that knocked sense into me. He said as rural kids, we need to work twice as hard to have half of what guys in other schools have,” he recalls.
Sibiya and other pupils from the area then formed a study group, to “share information and support each other”. “It helped a lot working together … especially with mathematics and physics,” he says.
Against the odds
Sibiya’s hard work paid off, and armed with an Umthombo bursary, he was accepted at the University of KwaZulu-Natal to study dental therapy. A year later, he transferred to the university’s medical school, and qualified as a doctor in 2022.
“My parents were ecstatic,” he says.
Straight after qualifying, he did two years of internship at Empangeni’s Ngwelezana Hospital, followed by community service at Manguzi Hospital in northern KwaZulu-Natal. “I rotated from one department to the next – paediatrics, maternity, the emergency unit – and learnt so much. It was the best,” he says.
He was geared up and ready to return home to serve his rural community as a doctor. His long-term dream was to work as an emergency physician in a hospital in rural KZN; maybe to specialise as an anaesthesiologist. But to specialise, you need to work in a public facility.
That was 2025. Since then, Sibiya has not been able to find a job as a doctor in the public healthcare sector. “I started applying in October last year,” he says. “But, so far, nothing.”
Many unemployed doctors
Sibiya is not alone. Spotlight has spoken to several other young doctors who are in the same boat. He reckons there are well over a hundred recently qualified doctors looking for work just in KwaZulu-Natal, others put the number at closer to 200. Even this may be an undercount since it doesn’t fully account for doctors who are still unemployed from previous years, or who have stopped looking for work. Some recent reporting suggests that the National Department of Health does not have a reliable count of how many unemployed doctors there are who are looking for work in the country.
Those who have received government bursaries, cannot fathom “why the government invests in us, then dumps us”. “Even now, they’re sending a new batch to study overseas, but where will they work?” says one doctor, who suggests that Cuban-trained doctors are prioritised for jobs because the government allegedly has a contractual obligation to give them jobs.
Currently, Sibiya and others have few alternatives but to try and do locums in private practises or in private hospitals.
“We’ve worked hard, done all that’s necessary to qualify and completed our internships and community service in preparation for careers in service to others, but we cannot find jobs,” says Sibiya.
Scrambling to make ends meet
We are meeting Sibiya on a Sunday at a coffee shop in Pietermaritzburg. He is currently living in Margate on the KwaZulu-Natal south coast and has come to Pietermaritzburg to do a locum shift for a private GP.
“I do shifts wherever I can find them. Primarily, I’m working in the emergency unit at the Shelly Beach (private) Hospital on the south coast. They call me whenever they need me, but I have no contract. That’s how I’ve been paying bills,” he says.
He keeps up with scores of other unemployed doctors on three different WhatsApp groups where, among others, they share job and locum opportunities, advise and support each other, and coordinate some of their interactions with the provincial health department.
“There are many people on the group(s) who aren’t able to get locum posts,” he says, “and they are really struggling. Some have depression. Sometimes it boils down to cars being repossessed, people going back home. Some people say, ‘I can’t put bread on the table, I’m selling my stuff because I can’t make ends meet’.”
“The mother of a friend of mine, also an unemployed doctor, called me recently and told me he’s drinking every day because the stress has been too much,” says Sibiya. “Some of the stories will make you cry.”
The situation is particularly tough on young doctors from poor backgrounds who do not have the funds to sustain themselves without work for extended periods.
‘I can feel I’m going into a depression’
Dr Raeesa Kathrada says she has sent her CV “to every doctor I know and to every private hospital and applied for every locum position.
“I can feel I’m going into a depression … as are my colleagues. Many people reach out to me, saying they don’t know how to survive,” she says.
Kathrada says some doctors have been waiting up to three years to find jobs.
Dr Lawrence Khoza from Osizweni, near Newcastle, is also struggling to find a position in the public sector. He started a private general practice, but he says he wants to work for the government and to see patients for free. “My passion is to help poor patients … but now I can only help those in the middle class who can afford medical aid,” he says.
Dr Nazo Nxumalo, originally from Mtubatuba, qualified in medicine at UKZN in 2022, did a two-year internship at Empangeni’s Ngwelezane Hospital and her community service at the Nseleni Community Health Centre in 2025. “After that, it was unemployment,” says Nxumalo. “It was like being dropped in the middle of the ocean.”
“I really thought that, after my community service, employment in the public health system would follow,” she says. “Basically, the department has left us stranded. We went into medicine, a very important job in society, believing we were entering a profession where our skills would always be needed.”
Understaffing in public health facilities
The unemployed doctors say that, while they are struggling to find work, the province at the same time desperately needs more doctors if it is to improve the quality and availability of healthcare services. “There is a big shortage; doctors are suffering in silence. The demand is there but the government is turning a blind eye,” says Khoza.
Several doctors who are currently employed at public sector hospitals in the province agree that they need help. One doctor, from a rural hospital speaks about “long lines of patients, late into the day” and doctors often working overtime and never taking a lunch break because “we can’t afford the 15 or 30 minutes of having no doctor on duty”. We are not naming the employed doctors quoted in this story since they could potentially suffer repercussions for speaking out.
“Whenever people leave our hospital, the posts are not filled because of budget cuts,” says another employed doctor. “Several departments here are severely short staffed.”
A recent report from South Africa’s Health Ombud paints a similarly grim picture. Following an investigation into the deaths of six healthcare workers at six public health establishments in KwaZulu-Natal, the Ombud found that while their deaths were not a result of workplace bullying, victimisation, or adverse working conditions in the hospitals under investigation, there were “significant” systemic challenges affecting healthcare professionals in the health establishments. These included “persistent staffing shortages, frozen vacant posts, rising workloads, shortages of medical equipment and supplies, inadequate employee wellness support services, infrastructure challenges, and security concerns affecting healthcare workers”.
A rough benchmark is that 1 doctor is needed for every 1 000 people, although experts stress that target ratios may differ based on factors like disease profile and population density. According to a 2025 parliamentary answer, the ratio in KwaZulu-Natal stood at around 0.38 doctors per 1 000 people – according to the District Health Barometer it was at just under 0.4 in 2024.
Though the KwaZulu-Natal Department of Health does not describe the situation as a crisis anywhere we could find, they do acknowledge shortages. Their 2025-2026 annual report largely blames a budget crunch. “The ongoing budget cuts due to implementation of austerity measures have had a significant impact on the ability of the department to fill vacant critical posts especially among clinical specialists (nurses and doctors), allied health professionals including in finance and human resource administrative posts,” the report reads.
Protests in Pietermaritzburg
On 17 June this year, a large group of unemployed doctors protested outside Natalia, which houses the KZN Department of Health and the Office of the Premier, to call on the provincial government to act urgently to create jobs for the numerous unemployed medical professionals.
With many wearing scrubs and holding placards, the doctors voiced their willingness to serve their communities. They highlighted the shortage of qualified doctors, the systemic strain in provincial hospitals and clinics, and a poor doctor-to-patient ratio in the province.
The protesters also pointed out that some doctors have been waiting for years for jobs; and that their ambitions to specialise in various medical areas were being severely hindered because of the lack of government posts.
They submitted a memorandum addressed to KZN Premier, Thami Ntuli, Health MEC Nomagugu Simelane, and head of the health department, Penny Msimango. Among others, the protestors demanded that the provincial health department advertise all the vacant medical officer positions at various public healthcare institutions within 14 days and that it develops a sustainable long-term plan to provide posts annually and address doctor unemployment beyond 2026.
Not enough money
In a written response to the protestors, the department said: “A filling of vacant posts is dependent on the availability of funds to compensate employees. The department is underfunded for 2026/7 financial year, therefore not all vacant posts can be filled.” They said that, due to the budgetary constraints, they could not commit to timelines for filling posts.
Spotlight sent the KwaZulu-Natal Department of Health a detailed set of questions (which you can read here) on the afternoon of Thursday15 October. We gave them a deadline of end of business on Tuesday 20 October. While the department acknowledged that they received our questions, they did not provide responses by the deadline.
On July 6, Simelane met with representatives of the unemployed doctors and representatives from the South African Medical Association Trade Union (SAMATU) (the unemployed doctors say that SAMATU had to be present since the department does not recognise the group of unemployed doctors).
According to Sibiya, the meeting did not go well. “Their clear message was that the department has enforced austerity measures and they do not have money to fund posts. They committed to try and look for 20 posts but that was all they could promise,” he says. In his view, 20 is not nearly enough. The department later upped the number of newly released posts to 50. The unemployed doctors say that while these jobs have been advertised, there have been no further movement.
But what stung Sibiya more was the sense he got that the department had accepted the situation and given up. “What was really astonishing was that they said they are comfortable with the numbers of doctors in the province on paper,” he says. Spotlight asked the department whether this characterisation is accurate, but did not receive an answer.
“Our response is that …. if something’s declared a crisis, finances are moved to meet that crisis, be it at provincial or national level,” Sibiya says. “I’m sure the public feels the same way: the doctors on the ground by no means meet the demand. They could hire all the unemployed doctors in the province, and still the demand wouldn’t be met.”
“We are not trying to fight”
As the 2026 convenor of the KZN Unemployed Doctors group, Sibiya has been in the middle of much of these developments. The group was formed a few years back with the goal of communicating with the provincial health department to raise doctors’ concerns about unemployment. It was only after several other efforts at engaging the department had not gone anywhere that they decided to protest.
In the meeting, he says they stressed “that we’re not here to fight”. “We understand the department has financial constraints. But we’re talking about the health of the entire province resting on a few shoulders who are really tired; and people ready to work cannot be integrated into the system because of austerity measures”, he says.
“I think we must all agree it’s a crisis. Once we do this, I’m certain funds can be mobilised from somewhere,” he says. “Alternatively, we could expand the system of employing sessional medical officers, where doctors work for a certain number of hours in clinics and hospitals, and earn less.”
But, says Sibiya, “it’s almost as though they’ve given up”.
That sense that those in power are not hearing them was recently reinforced when premier Ntuli reportedly called on doctors who have left the province to return home and help strengthen the health system. More than one unemployed doctor told Spotlight that they were enraged by the comments in the context of their struggle to get jobs. “It’s ridiculous,” says Sibiya. “After all our efforts to speak to the government, and being ignored, now this.”
“Just go private!”
Meanwhile, Sibiya and scores of other young, unemployed doctors are still having to scramble to make ends meet.
Sibiya says people often say to unemployed doctors that they should go private. “Yes, that’s an option, but from the point of view of specialising, it destroys the pipeline. And if all of us go private, then in upcoming years, we will be talking about a shortage. And, in a time of NHI, why are doctors having to work in private”, he asks.
“It’s worse for us coming from Ingwavuma, funded by Umthombo, where when we signed the contract, we were told, ‘You’re going to come back and serve your community’. I was happy to do that,” he says. Umthombo is a scheme that supports young people from rural KwaZulu-Natal to study medicine and then to return to serve their communities once qualified.
Despite all the setbacks, the dream of serving his community remains alive for Sibiya. His eyes light up when he talks of his dream to work rurally, preferably at the hospital he loves, Manguzi.
But, right now, that dream seems far away. He says his main focus at the moment is just to survive.
Almost 3000 scans performed in five months as Bophelo First Trust and Dis-Chem Better Tomorrow Starts Here strengthen diagnostic capacity across six public hospitals
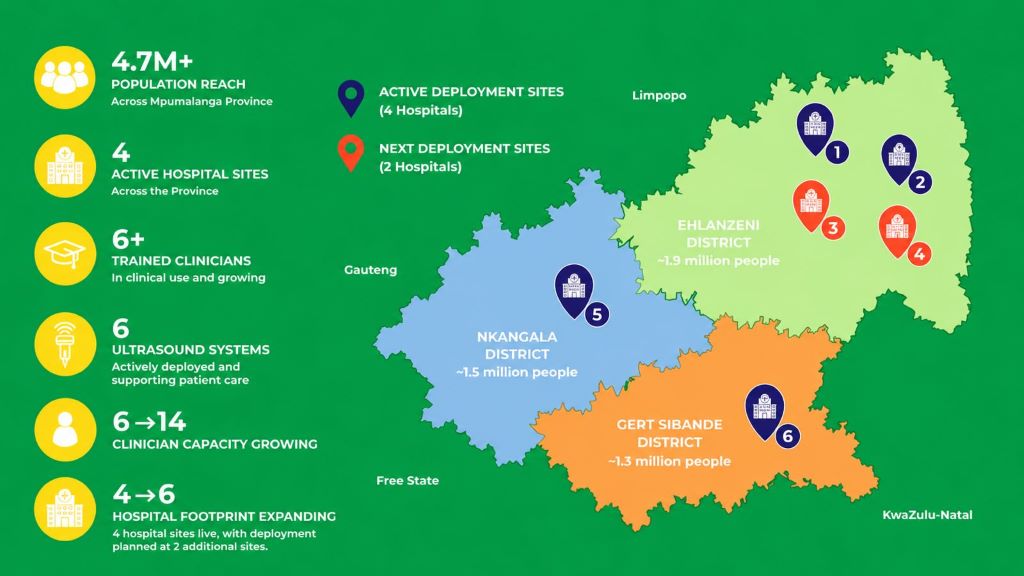
Patients at five Mpumalanga hospitals are benefiting from faster diagnosis following the launch of a point-of-care ultrasound programme by Bophelo First Trust (BFT), a South African Public Benefit Organisation (PBO), in partnership with Dis-Chem. The initiative has so far trained 14 clinicians and deployed 10 portable ultrasound machines, enabling surgical, emergency and trauma teams to scan patients at the bedside and reduce the need for referrals to other facilities.
BFT’s model strengthens existing public health systems through structure, continuity and measurable impact. It enables targeted operational support programmes that help unlock underutilised healthcare infrastructure and increase patient access to care. Through collaborative partnerships, it develops and implements scalable healthcare support initiatives focused on reducing surgical backlogs, increasing procedural throughput, expanding access to diagnostic capability, strengthening operational healthcare capacity and supporting long-term public-sector sustainability.
Uptake has been strong since the programme launched in May, says BFT CEO Dr Mark Wadley. “Targeted operational interventions have the potential to unlock additional healthcare capacity within existing public-sector infrastructure. With point-of-care ultrasound, a trained clinician can perform a focused scan beside the patient and interpret the findings in real time. This means patients can be assessed sooner and, where appropriate, avoid the need to travel elsewhere for imaging.”
The programme addresses a significant diagnostic gap in a province serving close to five million people. Since May, clinicians had performed 2,865 scans covering abdominal, vascular, trauma and musculoskeletal applications.
“Better Tomorrow Starts Here addresses pressing societal health challenges across South Africa and looks to find practical ways to improve access to quality care,” says Joshila Shiba, Dis-Chem’s Head of Health Equity and Sustainability. “This programme shows how targeted, practical interventions can unlock additional healthcare capacity within existing public-sector infrastructure and aligns with Dis-Chem’s purpose of increasing access to quality healthcare access. We want to help build, support and strengthen healthcare ecosystems across South Africa.”
“Our Better Tomorrow Starts Here initiative reflects our commitment to societal health challenges by aligning our business goals with sustainable development in South Africa and connecting our overarching “Better Health Starts Here” purpose with a broader commitment to contributing positively to the country’s future.”
Dr David Marubini, one of the 14 clinicians trained through the programme, says access to ultrasound is particularly valuable in surgical care, where delays in diagnosis can affect treatment decisions.
“Before we had ultrasound in our department, a patient arriving with severe abdominal pain or injuries from a road accident often had to wait before we could see what was happening internally. Sometimes they had to be transferred to another hospital first,” says Dr Marubini.
“Now I can scan at the bedside within minutes and answer urgent questions straight away. Is there internal bleeding? Does this patient need to go to theatre now, or can we safely manage them here? It doesn’t replace a full radiology service, but it allows us to make decisions sooner and with greater confidence.”
Dr Wadley says the initiative could provide a scalable model for strengthening diagnostic capacity in public hospitals across South Africa.
“Clinician participation is expanding and more hospitals are showing interest. The next phase will focus on improving how the clinicians’ ultrasound images and video clips are stored and uploaded to the cloud. This will support AI-assisted quality assurance and training, helping to maintain scanning standards as more clinicians are trained. In turn this will further strengthen diagnostic capacity in the province” concludes Dr Wadley.
Statistics South Africa (Stats SA) recently released its report on deaths that occurred in 2024. The headline findings contain a sobering, recurring truth: diabetes was once again the country’s leading underlying natural cause of death.
In 2024 alone, 28 767 people died from complications caused by diabetes, accounting for 6.1% of all deaths nationwide. That is an average of nearly 79 deaths every day.
Diabetes also claimed the top spot in 2022 and 2023. These numbers cannot be accepted as South Africa’s new normal. Behind every data point is a human life, a grieving family and, all too often, years of encounters with a health system that missed opportunities to diagnose, treat and support people in time.
As a public health specialist and chairperson of the non-profit organisation Diabetes Alliance, I view this three-year trend as an unacceptable tragedy. Diabetes is manageable. With timely support, people can lead long, healthy lives free from preventable complications. Acknowledging this crisis is the start, but recognition must give way to political action. The Department of Health must establish a national diabetes strategy with clear targets for prevention and care. The finance minister must resource it. And the Presidency must lead a coordinated, whole-of-government response.
The broader health landscape is equally stark. Noncommunicable diseases accounted for 60.7% of all recorded deaths in 2024. The top three causes of natural death – diabetes, hypertensive diseases and cerebrovascular diseases – frequently overlap in the same individuals. Managing these interconnected conditions through isolated disease programmes makes little sense for primary care clinics or the patients navigating them.
Reading beyond the numbers
At first glance, the 2024 total is 800 deaths higher than the revised 2023 figure of 27,967 (5.8% of recorded deaths). Stats SA compiles these mortality figures from death notification forms filed through the Department of Home Affairs. Medical practitioners record the cause of death, which Stats SA then classifies using international coding standards. Late death registrations and administrative backlogs are processed retroactively; this leads to revision or updating of prior years’ totals.
The updated count for 2022 stood at 33,126, higher than diabetes deaths recorded in 2023 and 2024. Diabetes has remained South Africa’s single largest natural killer for three consecutive years.
The diabetes burden is also deeply unequal:
Women bear the heaviest loss: diabetes was the leading recorded natural cause among women, claiming 17,429 lives (7.9% of all female deaths) and 11,334 or 4.5% of all male deaths.
Working-age adults are hard hit: it ranked first among people aged 45-64, accounting for 9,364 deaths (7.9% of deaths in this group).
Geographic split: diabetes ranked as the top natural cause in five provinces, Western Cape, KwaZulu-Natal, Limpopo, Eastern Cape and Gauteng, while hypertensive diseases led in the remaining four provinces. These provincial rankings are not a measure of individual care quality or residency. They are a starting point for region-specific questions about access and system performance.
The geographic split shows the need to investigate whether access to diagnosis, treatment and good quality care differs between and within provinces.
A death certificate is only the final chapter
Mortality statistics record the primary cause listed on a death notification, but remain blind to what happened along the way.
They cannot tell us how many South Africans live with undiagnosed diabetes. They cannot show whether a patient had consistent access to insulin and testing supplies, whether their blood sugar was adequately controlled, or whether a simple follow-up could have prevented a fatal complication. Nor do they capture the full toll of diabetes when another condition is listed as the underlying cause.
Those are the questions we must answer while patients are still alive.
In my work on strengthening diabetes care, including the Tshwane Insulin Project – a nurse-led programme that helped people with type 2 diabetes start and adjust insulin treatment in primary care, with follow-up support at home – I have seen where care pathways break down, and where they succeed. Survival rarely hinges on high-tech interventions. It depends on the links in primary healthcare:
a trained clinic nurse with the time to act
a reliable supply chain for medicines and diagnostics
routine follow-up mechanisms when a patient misses an appointment
regular screening for kidney, eye and vascular (blood vessel) complications
support systems that respect the economic reality of a person’s daily life.
We need real-time clinical data that helps a facility respond today, not a national death tally published two years later.
Turning policy into frontline care
South Africa already has a framework: the National Strategic Plan for Non-Communicable Diseases and its 90-60-50 targets. This cascade aims to ensure that 90% of adults know their blood pressure and blood glucose status, 60% of those with elevated levels receive treatment, and 50% of those receiving care achieve clinical control.
The challenge is making policy work in practice.
Tools like the National Health Laboratory Service diabetes dashboard offer valuable insights into blood sugar levels control across districts. But to close the loop, South Africa urgently needs a national diabetes registry and integrated digital tracking to understand who enters care, who remains in care, and who is being left behind.
From declaration to delivery
After the 2025 Diabetes Summit, the Diabetes Alliance launched the Johannesburg Declaration for Accelerated Action on Diabetes. The declaration calls for coordinated national leadership, sustainable financing, decentralised primary care, and direct participation by people living with diabetes. It asks the Presidency to lead a multisectoral response and calls on the National Treasury and health sector to match policy commitments with financial resources.
The latest mortality report gives this agenda even more urgency. There are three practical priorities:
Connect early diagnosis to sustained care. Screening is only useful if a positive result leads to uninterrupted treatment, reliable medicines, blood glucose monitoring and clinical review.
Measure quality of care: publish a picture of diagnosis, treatment, retention and complication rates by district and province.
Address the conditions in which health choices are made. Food prices, transport barriers and economic hardship shape health outcomes.
People living with diabetes must help define what quality care looks like. Their experience should guide national policy and daily clinic operations alike.
Millions of South Africans still struggle to access consistent, quality primary healthcare. Language barriers, distance from facilities and a shortage of trained health workers are just a few of the factors impacting the standard of care. Tshikululu Social Investments and Dr Sophia AI are addressing this gap through a new partnership to advance health equity across South Africa.
Dr Sophia AI is an Australian-developed, clinically governed decision support platform that helps clinics deliver consistent, high-quality care at the point of consultation. Through this partnership, small and medium healthcare practices in South Africa will gain access to AI-assisted clinical support that strengthens the care they provide. As these practices grow, more communities gain reliable access to primary healthcare.
The technology is intended to support — not replace — healthcare professionals. It guides structured assessments, helps identify potential risks and drug interactions, and supports clinical documentation, while clinicians remain responsible for reviewing and approving recommendations. The platform is built around explainability, traceability and clinician oversight, with an audit trail designed to support clinical governance and accountability.
A pilot is already under way with nurses working in community-based primary healthcare settings in the Western Cape. This is this first phase in testing how Dr Sophia AI can strengthen healthcare systems, and small businesses, in under-resourced communities.
The pilot will focus on localising Dr Sophia AI for South African community healthcare settings. This includes embedding South Africa’s Essential Medicines Lists and relevant clinical guidelines, refining the platform for local care pathways and testing its language capabilities in the context of how patients and healthcare professionals communicate in practice. The pilot will also gauge how the platform can grow revenue streams in small businesses by streamlining operations. Insights from the pilot will be used to continually refine the platform for the local context and inform its potential wider deployment.
Alongside the pilot, Tshikululu and Dr Sophia AI are designing a funding model that could complement traditional grant funding by linking commercial growth to social impact. The concept would see a percentage of future revenue generated through Dr Sophia AI’s commercial deployment directed towards a grant fund. This fund will be channelled towards initiatives that expand access to quality healthcare and support SMME growth, with Tshikululu bringing its experience in social investment and fund management to the model.
Dr Sophia AI complies with American FDA Clinical Decision Support Software requirements and is registered in Australia as Software as a Medical Device, Class I, Clinical Decision Support Software; providing an internationally recognised regulatory foundation for its use as clinical decision-support technology. Its South African deployment will equally align with applicable POPIA, SAHPRA and HPCSA requirements.
“Where you live, the language you speak or the availability of healthcare professionals in your community should not determine the quality of healthcare you can access,” says Leanne Emery-Hunter, CEO of Tshikululu Social Investments. “This pilot is about taking an established AI-assisted clinical platform and embedding it in the South African context — our clinical guidelines, our languages and the realities of frontline healthcare delivery.”
The partners are looking to engage funders, healthcare organisations, corporates and other potential partners interested in helping to shape and participate in the model. The ambition is to explore whether commercial adoption of the technology can create an ongoing source of funding that, in turn, supports grant-funded healthcare initiatives in underserved communities.
“Healthcare is deeply local, but the challenge of delivering consistent, high-quality care is global,” says Julia McCann, GM, Dr Sophia AI. “Our ambition is to build technology that can support healthcare professionals across very different health systems, languages and communities. South Africa is an important opportunity to demonstrate how a global platform can be meaningfully localised — combining international clinical capability with the guidelines, languages and realities of care on the ground.”
The partnership reflects a broader approach to social investment. It brings together technology, commercial and social-sector partners to develop new approaches to persistent social challenges and explore funding mechanisms that can complement traditional grant-making.
“This is the kind of social innovation we want to enable,” says Emery-Hunter. “It brings together technology, frontline expertise and a new approach to funding around a very practical question: how do we get better healthcare closer to people who have historically had the least access to it? We believe that will require collaboration, continuous learning and new ways of thinking about how social impact is funded.”
Tshikululu and Dr Sophia AI welcome conversations with organisations interested in partnering on the next phase of the initiative and helping to shape how the model could contribute to more equitable access to quality healthcare.
Hazel Moagi proudly shows off awards for her work as a specialist forensic nurse, which represent her commitment to the field. (Photo: Elna Schütz/Spotlight)
By Elna Schütz for Spotlight
In a country like South Africa which grapples with a high prevalence of gender-based violence, forensic nursing unfortunately remains a largely overlooked specialisation, with little incentive for remuneration. One nurse tells Spotlight every flicker of hope a patient carries home is a reminder of why she chose this path.
Sister Hazel Moagi has won quite a few accolades as a forensic specialist nurse. These certificates and trophies are displayed on a table in one corner of her office at the Bertha Gxowa Care Centre in Germiston on the East Rand of Gauteng.
To Moagi, this small table carries tremendous weight. It motivates her to keep pushing in a career that is much needed but often soft-pedalled in both recognition and remuneration. “I call it my place of safety,” she says. “Whenever I feel down or that I’m not okay, I look at the achievements, and I say, you need to stand up, pick up the pieces, and try to do more for the community because they need me to.”
She lets out a giggle as she shares that colleagues would fondly call her ‘Nurse Hero’ after she scooped a 2023 Nurse Hero award. “It’s so fulfilling, more than monetary remuneration,” she says, adding that it also brings a sense of pride to those who know her “because you know small things make people happy.”
Those who know her well enough may notice an absence of yellow merchandise among the trophies in her office. As a long-time supporter of the Kaizer Chiefs football club, it wouldn’t be amiss in the forensic nurse’s office. She says she makes sure to catch every game in person or on television to decompress, given the heavy and sensitive nature of her work.
As operational manager of the Care Centre, Moagi runs a forensic medical service that she says many do not know is available when they need it. The Centre, on the grounds of the Bertha Gxowa Hospital, provides inclusive and comprehensive patient management of people who experience gender-based violence, including vulnerable populations such as children and people with disabilities as well as cases linked to trauma and driving under the influence of alcohol.
Both suspected perpetrators and victims of crimes are helped in the building, but the sections are separate, with the entrances out of sight of each other. Inside, there are rooms for various parts of the investigative and medical process. There’s a swing set, playroom, and colourful doctor’s room meant to make children feel more comfortable.
From victim to survivor
“We are turning victims into survivors,” Moagi says. It is particularly important to her that all her clients are treated with dignity and respect, for instance, by offering them bathing facilities, fresh clothes, and food. Safe lodging, such as access to shelters is arranged if needed.
Moagi says that a lot of patients arrive scared, traumatised, and often in the same clothes they were wearing during the crime. But after testing, treatment and brief recovery, the physical and emotional change is so different that she says even police staff fetching patients are regularly surprised that this is the same person they dropped off earlier.
Moagi says she finds cases involving children, especially those abused by a family member, especially difficult to handle.
“It’s so painful to see … abuse that happened within a space where it’s supposed to be a safe environment, and somebody you trusted with your child.”
The specialised unit’s work includes collecting forensic samples and offering support in cases of gender-based violence. She explains that it usually starts with the gathering of DNA and other samples into a Sexual Assault Evidence Collection Kit if a person reports sexual assault within 72 hours.
“Then the history that the patient gives us also guides us in terms of where to collect,” Moagi says. She explains that carefully asking patients to detail what happened will help her know where on the body it’s best to swab. The whole process may take over three hours, and the DNA is particularly important in forensic cases where the perpetrator was unknown to the victim.
Sometimes Moagi says she and her team notices commonalities between patients, which she then relays to her supervisor and the police. For instance, there may be multiple people who have been raped describing similar perpetrators and circumstances in the same geographical area, even if they have gone to different police stations or places for help. “If there’s a specific trend that is currently happening, then we escalate to say we have noted that this and this is happening around the specific area,” she says.
When forensic samples are collected properly and each case is understood in its wider context, it can make the difference in helping police identify a serial rapist and build a case. Moagi says she has testified in court in several such cases.
While being mindful of sharing confidential details, she does remember one case in particular. “He’s currently serving more than 200 years,” she says. “It makes you feel good that at least we have saved more women from becoming his victims.”
Memory of a neat white dress
Moagi says her passion for nursing comes from her early childhood in a small village near Bushbuckridge.
“There was a nurse that I used to see wearing her uniform, going to work, and coming back, and that’s when I said I also want to be a nurse,” she recalls. She smiles at the memory of the neat white dress the nurse wore, and how competent she seemed whenever Moagi saw her. She says she held on tight to that vision throughout her school years.
Indeed, she studied nursing and a few years later the dream was fulfilled. She started working as a general nurse.
A few years later she attended a three-day workshop on forensic medicine organised by several government departments. It was there, listening to forensic nurses speak about their work, that something new clicked for her. She says during the break, she felt compelled to speak to them and learn more about the work they did. “Since that day, I started to fall in love with managing gender-based violence cases,” she says. Around a year later, she started studying forensic nursing at the University of the Free State.
Passion over money
In specialising in forensic nursing, Moagi chose her passion over the potentially higher salary she could potentially get with other nursing specialisations. This is because, unlike nephrology or orthopaedics, forensic nursing is not recognised by the South African Nursing Council (SANC) as a professional specialisation. The SANC’s website does list forensic nursing as a nursing competency, but it does not include it in the list of specialised nursing competencies, which would make someone an Advanced Practice Nurse, with greater recognition and higher renumeration.
A June 2026 parliamentary reply to a question to the Minister of Health alludes to the fact that this is due to the educational programmes used in the past, including the one Moagi studied, not being recognised in regulations. It notes that future qualified forensic nurses would likely be recognised. However, no current educational programmes appear to be approved for this yet.
The parliamentary answer indicates that even if newer qualification lists are recognised in the future, Moagi’s previous diploma will continue not to be recognised.
Moagi says she knew about this from the start and admits that it can be difficult with the current cost of living to see other nursing fields being paid more. She says she may see job posts with salaries posted for other specialties and feel a tinge of jealousy.
She says she knows of nurses who were eager to specialise in forensic nursing but have been unable to because the additional recognition and remuneration do not reflect the demands of the role. “I think as soon as the nursing council recognises it, then more nurses will join,” she says.
Doing this work for years to come
It has now been a decade since Moagi moved to Germiston and started managing the 24-hour clinical forensic medical care facility located on the corner of Hospital and Cross Streets. She says she loves working with her team and the various stakeholders, such as the police and the Department of Social Development.
If it is up to her, she will keep doing this work for many more years to come. She says that every patient who walks away with a little more hope after facing some of their darkest moments is a reminder of why she chose this path.
“It’s seeing victims of gender-based violence walking out with hope that there is still life, and they can still pick up the pieces and try to move on with their lives,” she says.
Meanwhile, another shiny trophy has been added to that table in the corner of her office. The Gauteng Department of Health’s Ekurhuleni Health District Services recently named her best female gender-based violence activist at their Annual Gender-Based Violence Awards.
The awards are nice, but speaking to Moagi it is clear that they, like the higher salaries she may have had with another specialisation, are secondary. What drives her is a deep passion to help and serve others.
“There are those days where you feel like no matter how bad the situation was, I did my best to make sure that the patient is managed,” Moagi says. “And by the time you go home, you know you have done something good for the patients.”
*Thisarticleis part of Spotlight’s 2026 Women in Health series, featuring the remarkable contributions of women to healthcare and science. Sign up to the Spotlight newsletter.
Environmental Health Practitioners regularly test drinking and recreational water to detect contamination and help prevent diseases such as cholera and typhoid. (Photo: Unsplash)
By Christina Pitt for Spotlight
From inspecting spaza shops to monitoring water quality, Environmental Health Practitioners help prevent disease before outbreaks occur. A Public Protector investigation reveals why Gauteng municipalities are struggling to deliver these essential public health services. The investigation also helps clarify what is at stake in South Africa’s local government elections in November.
Environmental Health Practitioners (EHPs) operate as the public health system’s early warning system. They are responsible for identifying and managing environmental health risks before they become public health emergencies.
Whether inspecting food premises, monitoring water quality or investigating environmental health hazards, their work is designed to avert illness. These preventative functions form part of the municipal health services that local governments are required by law to provide and what will be at stake in the local government elections in November.
The importance of these largely invisible health services came into sharp focus when Public Protector Advocate Kholeka Gcaleka released preliminary findings of an investigation into Gauteng’s food safety system on 17 July 2026.
The probe followed a series of food poisoning incidents involving children in 2024. Among the most high-profile was the death of six children who allegedly consumed contaminated food bought from a spaza shop in Naledi, Soweto.
Rather than focusing only on the poisoning incidents themselves, the Public Protector’s office examined whether Gauteng’s municipalities were adequately delivering the municipal health services responsible for regulating food safety and hygiene standards in the informal business sector.
As the local government elections draw closer, we unpack how municipalities use environmental health services to prevent harm and protect public health, and find out what happens when that system comes under strain.
To start with, we need to understand what municipal health services are, the responsibilities assigned to municipalities by law, and how those services are intended to function.
What are municipal health services?
Food safety is just one of many municipal health services.
Professor Jaap de Visser, National Research Chair in Multilevel Government, Law and Development at the Dullah Omar Institute at the University of the Western Cape, points to the National Health Act for the full list.
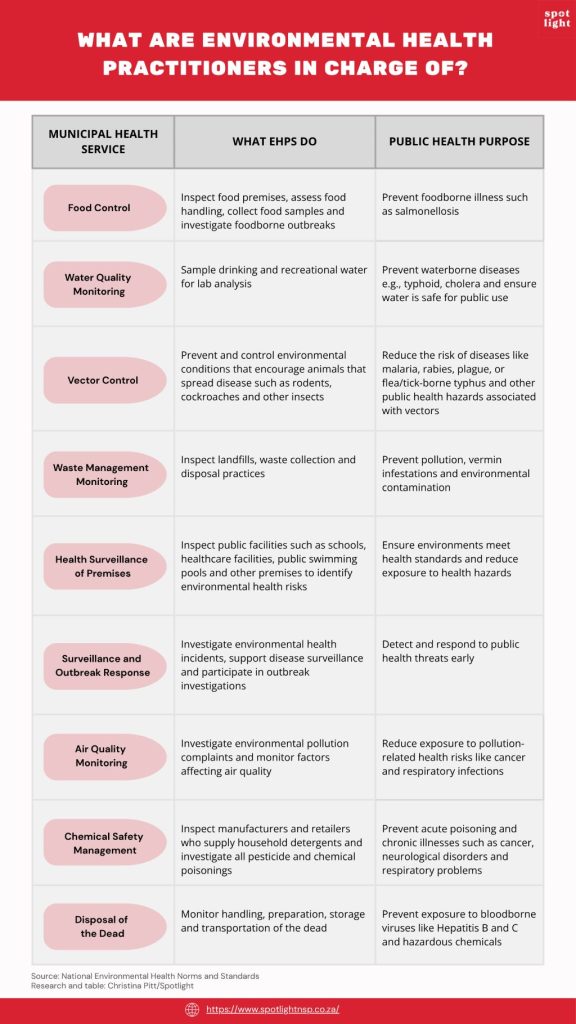
The Act defines municipal health services by naming nine preventative functions, including food control, water quality monitoring, waste management, vector control, and environmental pollution control.
For example, EHPs routinely collect drinking and recreational water samples for laboratory testing to detect contamination and reduce the risk of waterborne diseases such as cholera and typhoid.
This table below illustrates the key functions they perform to prevent disease before people become ill.
The National Environmental Health Norms and Standards requires EHPs to adopt a preventative, risk-management approach. In practice, this means rather than inspecting every premises equally, they prioritise activities and facilities that pose the greatest risk to public health.
“Higher-risk premises, for example, those handling high-risk foods, with a history of non-compliance, would be inspected more frequently and receive more intensive oversight,” explained National Department of Health spokesperson Foster Mohale. “Conversely, lower-risk premises with a strong record of compliance may be inspected less frequently, allowing EHP resources to be directed where they are most needed.”
EHPs also have enforcement powers when they identify breaches of prescribed health standards. They can issue compliance notices, requiring owners or operators to correct a problem within a specified period.
Their work also includes routine inspections, environmental health surveillance, investigating complaints, and educating communities and businesses.
Which municipality is responsible for delivering these services depends on where you live.
In metropolitan municipalities such as Johannesburg, Tshwane and Ekurhuleni, the municipality is responsible for providing municipal health services within its boundaries.
In non-metropolitan areas, the Municipal Structures Act provides that district municipalities are generally responsible, while local municipalities perform the function only where they have been authorised to do so in terms of the Act.
Although municipalities deliver these services, the National Health Act requires them to work as part of a coordinated health system. It establishes District Health Councils to support coordination between national, provincial and local government.
According to Mohale, municipal health services are intended to function as an integrated three-tier system in which national, provincial and district environmental health units work together to deliver municipal health services.
“Working together, these structures are intended to create a coordinated system in which national government sets the policy and regulatory framework, provinces provide oversight and technical support, and district structures coordinate and strengthen implementation at municipal level,” he said.
Food safety provides a useful example of how that system operates in practice.
From farm to fork
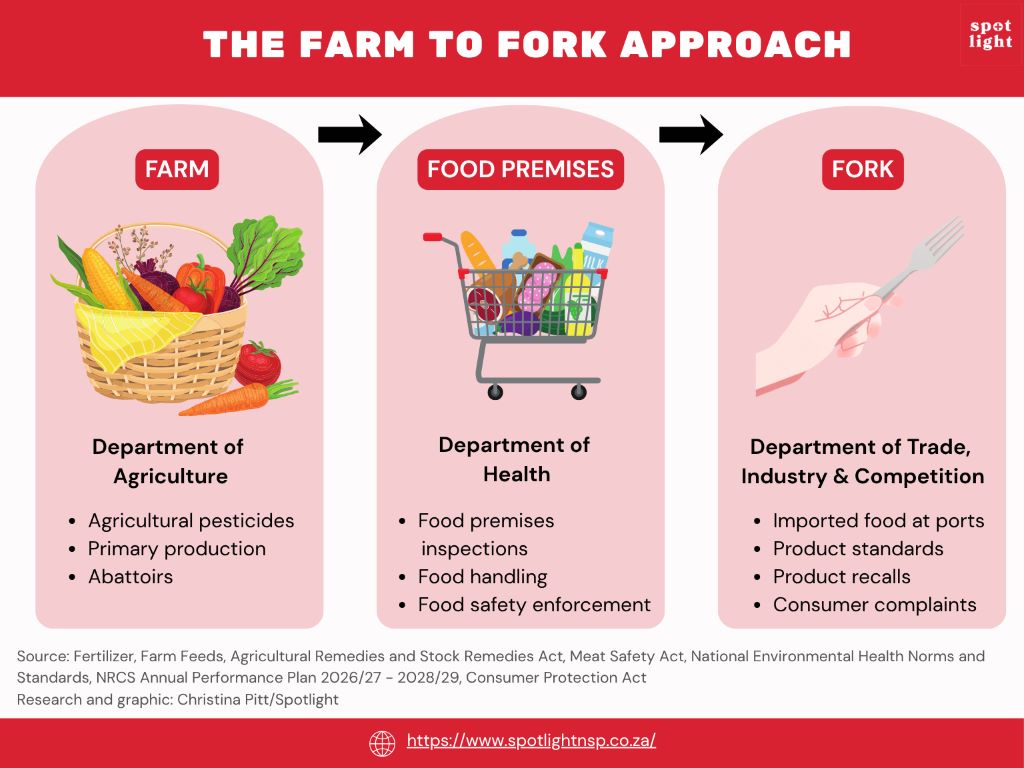
Food microbiologist and food safety expert Professor Lucia Anelich says South Africa follows a “farm to fork” approach, with different institutions responsible for different stages of the food chain.
The Department of Agriculture oversees food safety at the production stage by regulating agricultural pesticides and veterinary medicines as well as food safety in abattoirs.
Once food enters the retail environment, the Department of Health, through municipal EHPs, is responsible for inspecting food premises, checking how food is prepared and enforcing food safety requirements.
The Department of Trade, Industry and Competition provides an additional layer of oversight by inspecting certain imported food products at ports of entry, overseeing product recalls and investigating consumer complaints.
When food contamination is suspected, those responsibilities overlap as the relevant authorities work together to trace the source, remove contaminated products, and prevent further illness. The agencies involved depend on where the suspected source lies within the food chain.
The Public Protector’s Gauteng food safety investigation examined whether the preventative systems intended to identify and manage these risks before outbreaks occurred were functioning as intended.
A break in the chain
The level of coordination required for food safety is not the type of thing that happens by chance.
That is why District Health Councils are tasked with strengthening planning, oversight and coordination between national, provincial and local government.
According to Mohale, these structures are intended to provide a forum for regular engagement between stakeholders, monitor the implementation of environmental health programmes and “ensure that food safety risks are identified and managed proactively.”
Yet, the Public Protector identified a significant weakness in Gauteng’s food safety system with the absence of functioning District Health Councils.
Without them, coordination between different spheres of government becomes more difficult, weakening oversight, planning, and the implementation of municipal health services.
Delivering these services also depends on whether municipalities have enough EHPs to carry out routine inspections.
EHP employment gaps
One of the Public Protector’s clearest findings was that Gauteng municipalities lack sufficient EHPs to carry out their statutory functions.
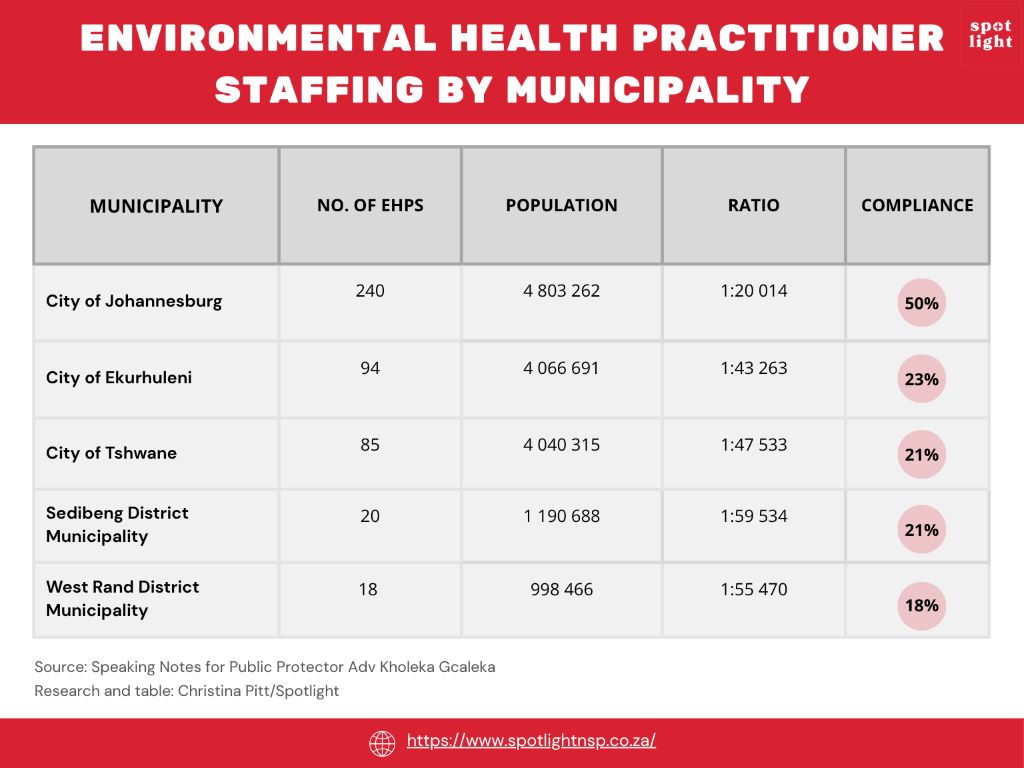
As of October 2025, every municipality fell short of the World Health Organisation (WHO) and the National Environmental Health Norms and Standards benchmark of one EHP for every 10 000 people.
Johannesburg had the largest absolute number of EHPs, with 240 practitioners serving a population of 4.8 million people. This gave it a ratio of one EHP for every 20 000 people, or 50% of the recommended benchmark.
Meanwhile, Ekurhuleni and Tshwane had fewer than one-quarter of the recommended number of EHPs.
According to City of Johannesburg spokesperson Nthatisi Modingoane, its current staffing complement is 213 EHPs, with eight funded vacancies. Despite ongoing recruitment, the City estimates that each EHP is still responsible for about 28 000 residents — almost three times the benchmark.
City of Ekurhuleni spokesperson Zweli Dlamini said the municipality now employs 98 EHPs, up from 94 during the Public Protector’s investigation. However, he acknowledged that the municipality still has a shortage of 309 EHP posts, leaving it well below the recommended staffing benchmark.
The City of Tshwane did not respond to Spotlight’s requests for updated staffing figures.
“The entire province is functioning at less than a third of the required EHP staffing capacity,” Gcaleka said about her findings, warning that the shortage threatens equitable access to environmental health services.
Anelich explained that staffing shortages are compounded by the breadth of EHPs’ responsibilities.
“EHPs are trained broadly, including water quality control and pollution monitoring — not only food,” she said.
“These people have multiple roles to play, which makes it very difficult for the system. We should have EHPs dedicated to food safety so municipalities can regulate food safety more effectively, particularly in the informal sector.”
The National Environmental Health Norms and Standards require EHPs to inspect high-risk food premises at least once every quarter. Maintaining those inspection frequencies becomes increasingly difficult when each practitioner is responsible for far more people than the recommended benchmark.
The capacity constraints extended beyond municipalities. The Public Protector found that the Department of Agriculture had filled only 27 inspector posts, which it described as insufficient to regulate agricultural pesticides effectively, weakening another part of the food safety chain.
But increasing staffing capacity depends on whether municipalities have the financial resources to create and sustain these posts.
Money troubles
The Public Protector also found that municipalities were not allocating enough funding to municipal health services, limiting their ability to recruit and retain EHPs.
Municipal health services are funded primarily through the local government equitable share. This is money allocated by National Treasury and transferred to municipalities to help provide basic services. Municipalities also use revenue from rates and taxes.
Because the equitable share is an unconditional grant, municipal councils decide how much funding is allocated to environmental health alongside their other constitutional responsibilities.
Although the National Department of Health is not responsible for funding municipal health services or employing EHPs, Mohale said it continues to support initiatives aimed at helping municipalities recruit, retain and train EHPs.
He also said the department engages with National Treasury and the Department of Cooperative Governance and Traditional Affairs to prioritise the appointment of EHPs and address staffing shortages.
The human cost
These system weaknesses had visible consequences on the ground. During blitz inspections cited by the Public Protector, EHPs repeatedly identified expired food, unlabelled products, poor hygiene, rodent infestations, and unsafe storage practices.
The Public Protector also found low levels of compliance with spaza shop licensing requirements.
Only 5% of spaza shops in Ekurhuleni were licensed or permitted, compared with 14% in Johannesburg and 30% in Tshwane, according to Gcaleka’s speaking notes. Across Gauteng, the compliance rate was 28%, meaning that for every licensed spaza shop, almost three were operating without the required license or permit.
“So many spaza shops aren’t licensed, so EHPs don’t even know where to look,” Anelich said.
“We can send EHPs into informal settlements to look for them, but that’s not a great use of resources that are already stretched.”
She also said the deaths highlighted what can happen when food safety systems fail. Adding that South Africa’s burden of foodborne disease remains poorly documented, making it difficult to understand the full scale of the problem.
A systemic failure
The Public Protector found that the problems extended beyond individual incidents.
In her speaking notes, Gcaleka says that the underlying governance weaknesses, severe staffing shortages, inadequate funding for municipal health services and capacity constraints in other parts of the food safety system were “not incidental, but systemic and far-reaching”.
She therefore made the preliminary finding that Johannesburg, Ekurhuleni, Tshwane, Sedibeng and West Rand had failed to properly enforce food safety and hygiene standards in the informal food sector.
As voters prepare to elect new local governments in November, the findings highlight a core municipal responsibility: preventing public health risks before they become public health crises.
If an HIV prevention pill that provides a month of protection at a time performs well in two ongoing clinical trials, it could become the next big thing in HIV prevention after the lenacapavir injection. A new licensing agreement is paving the way for South Africa’s Aspen Pharmacare to produce the pill should the study findings be positive and the drug be registered.
In June, South Africa’s health department started rolling out the six-monthly lenacapavir HIV prevention injection to around 10% of public sector clinics. While the rollout of this jab still has a long way to go, the next generation of HIV prevention products is already on the horizon.
Two of those new products stand out. One is a new formulation of lenacapavir that looks as if it can provide 12 months of protection at a time. While results so far are promising, the pivotal data on this once-yearly HIV prevention jab is only expected in a year or two.
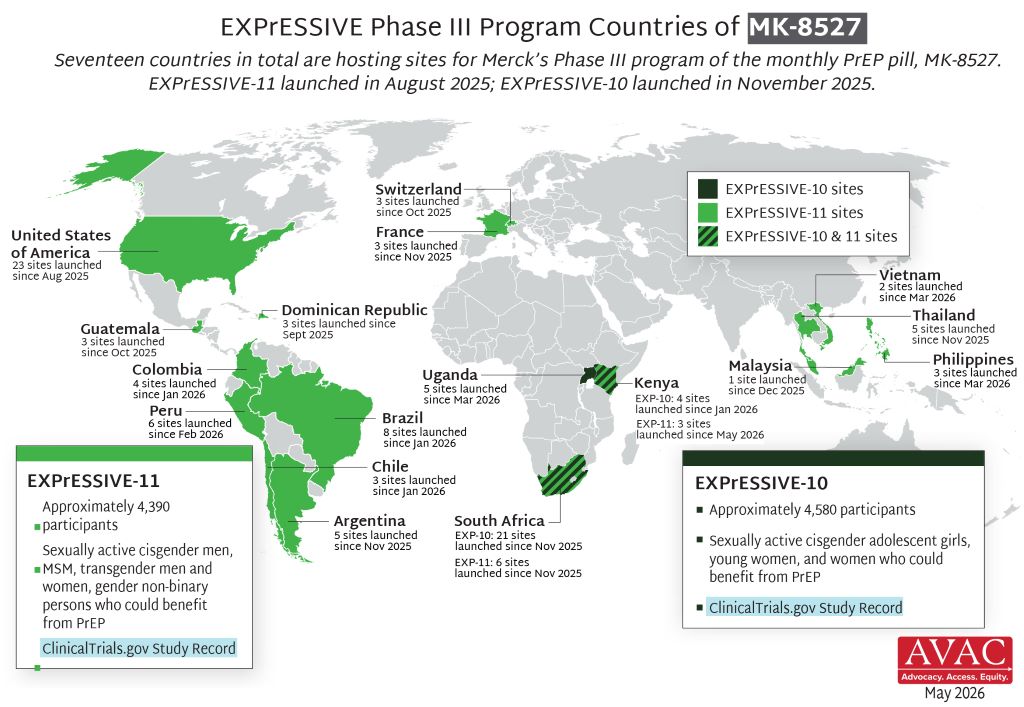
The other product that has many people in the HIV world excited is a monthly HIV prevention pill that contains a highly potent antiretroviral medicine called alimatravir (it was previously called MK-8527). It starts working within around an hour after someone takes it and appears to provide a month of protection at a time. One benefit of the pill, compared to the lenacapavir injection, is that it would be easier to distribute at scale, given that there is no need for a nurse to administer an injection.
As Spotlight reported in some depth last year, alimatravir looked very promising in a phase 2 study, although for now the jury is still out on the drug’s safety and efficacy. It is currently being evaluated in two pivotal phase 3 clinical trials called EXPRESSIVE-10 and EXPRESSIVE-11. Both these studies started last year and are expected to be completed by around mid-to-late 2027. Medicines are typically only registered for use after positive results in such phase 3 studies.
“The monthly pill offers an alternative for people who would like a long acting, less frequently dosed PrEP but not needle friendly … so it really is about giving more options especially on the pill side,” Professor Linda-Gail Bekker, primary investigator in South Africa on the EXPRESSIVE-10 study, told Spotlight. “You could imagine that just having to remember to take a small easy to swallow pill on the day you pay your bills monthly could be very easy for people. We understand that the packaging is also going to be very user friendly- looking more like a gum packet than a bottle of antiretroviral pills which may also reduce stigma.” (PrEP refers to pre-exposure prophylaxis like HIV prevention pills or injections.)
Licence to make generics
The prospects for future access to alimatravir got a major boost last week when the pharmaceutical company Merck (known as MSD outside of the United States and Canada) announced that it granted licences to seven different companies to produce generic versions of the monthly pill. One of the seven companies is South Africa’s Aspen Pharmacare. The others are Uganda’s Quality Chemical Industries Limited, Kenya’s Universal Corporation Ltd, and Aurobindo, Cipla, Emcure and Viatris in India.
Early responses to the licences have mostly been positive.
Having a generic company with a licence in South Africa is excellent news, said Bekker.
“It is particularly exciting to see manufacturers in Kenya, South Africa and Uganda included in these licenses,” Mitchell Warren, Executive Director of AVAC (a global HIV advocacy group), told Spotlight by e-mail. “These are the first generic PrEP licenses in East and Southern Africa, meaning manufacturing can happen where trials are happening, where need is greatest and where we have the largest PrEP markets.”
“Through our agreement with MSD (Merck), we have the opportunity to support the future supply of an innovative HIV prevention option while strengthening local pharmaceutical manufacturing and healthcare resilience across the continent,” Stephen Saad, Aspen Group Chief Executive, said in a media statement. Under the agreement, the company says it will receive a technical package from Merck, together with licensing rights covering 129 countries, including all African countries.
Speaking to Spotlight, Stavros Nicolaou, Aspen’s Head of Strategic Trade, described alimatravir as “ground-breaking and a potential game-changer”. He commended Merk for starting the licensing process so early. He framed the licence as an important step forward for both South Africa’s HIV response and for local production of antiretrovirals, although he also raised concerns about the procurement of locally manufactured antiretrovirals – the percentage of South Africa’s antiretroviral tenders awarded to local manufacturers has been trending downward.
According to earlier reporting by Business Day, Nicolaou has declined to give any indication as to a potential price for the pill, but he did tell the publication that they could potentially supply it for both South Africa’s public and private sectors.
There are indications that a relatively low price is on the cards. Research being presented at AIDS 2026 this week found that alimatravir could be mass produced and sold at a profit for as little as $15 (around R250 to R300) per person per year. This is less than half the $40 per person per year that South Africa is expected to pay for generic lenacapavir injections in a year or two from now.
“Merck expects to provide initial supply and continue supplying product as needed while licensed generic manufacturers complete development, obtain the necessary regulatory approvals and prepare to provide supply in the licensed territories. The goal is to help avoid delays in access by providing an initial supply pathway until generic manufacturing capacity is established and brought online,” the company said in a media statement.
Earlier licensing
The timing of the licensing announcement is somewhat unusual – such announcements are typically only made after phase 3 trials have been concluded and it is confirmed that the drug is safe and effective.
“Granting licensing agreements to generic manufacturers while clinical trials are still enrolling, before it is known if the product is effective, should significantly reduce the time to market for the product,” Warren said in an earlier AVAC media statement. “The timeline announced today gives us ample opportunity to work with ministries of health, donors, communities, and Merck to plan for broad access to the monthly PrEP pill.”
Warren told Spotlight that the small amount of active drug in alimatravir and the fact that it is an oral dose should make the technology transfer from Merck to generics quite quick. “The hope would be that genetic alimatravir reaches the market within months of the approval of the originator, compared to more than a year for lenacapavir,” he said.
Nicolaou was also upbeat about how quickly things are unfolding. He said that Merck’s decision to execute licences while the phase 3 clinical trials are ongoing allows for an earlier registration pathway (if phase 3 findings are positive, alimatravir will have to be filed for registration with regulators like the South African Health Products Regulatory Authority). He also pointed out that it is a small tablet and that it should be easier to manufacture than HIV prevention injections.
Nicolaou told Spotlight that the plan is for Aspen to do formulation of alimatravir in South Africa, but that they are not currently planning to produce the active pharmaceutical ingredient – this will likely be sourced from Chinese or Indian suppliers.
Some activist criticism
But while the timing has generally been welcomed, there has also been some criticism over the licenses.
A statement from activist group HealthGap points out that Latin American countries like Brazil, Argentina, and Colombia are not included in the list of 129 countries covered by the license, even though some of the phase 3 trial sites for alimatravir are in these countries. The HealthGap statement calls for compulsory licenses to be issued.
In an earlier statement, Merck said that, in recognition of the significant unmet need in Latin America, “Merck is in active discussions with organizations, including Fiocruz (a key player in medicines production and procurement in Brazil), with a goal to enable rapid availability and broad supply of alimatravir in the region”.
Disclosure: The Gates Foundation has provided financial support for clinical trials of alimatravir. Spotlight receives funding from the Gates Foundation, but is editorially independent – an independence the editors guard jealously. Spotlight is a member of the South African Press Council.