Category: Metabolic Disorders

New Obesity Definitions Better than BMI in Revealing Ill Health
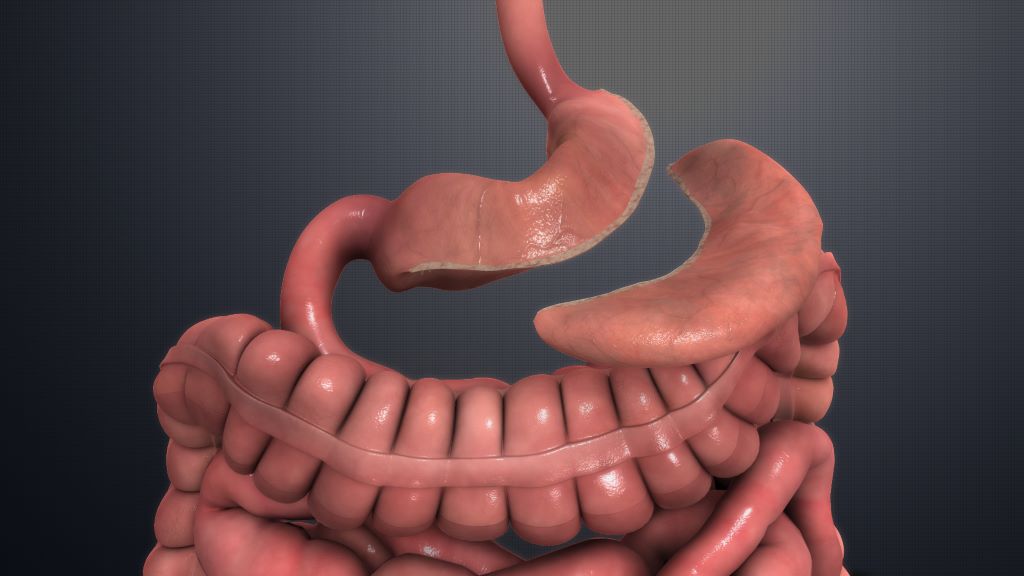
Sleeve gastrectomy. Credit: Scientific Animations CC4.0

An international study led by King’s College London has found that proposed new obesity definitions give greater insight into the ill health of metabolic bariatric surgery candidates compared with Body Mass Index (BMI).

The study, published in Jama Open Network, found that people considered for metabolic bariatric surgery had marked variation in disease burden – the number and severity of diseases – and operation-related risks, despite having similar BMI.

However, by reviewing clinical data from thousands of bariatric surgery candidates and applying new obesity definitions, the researchers were able to better understand their underlying health – which could have important implications for patient treatment and surgery prioritisation in the future.

Led by Professor Francesco Rubino, Chair of Metabolic and Bariatric Surgery at King’s College London, the researchers reviewed retrospective clinical data from 2,316 surgical candidates across four specialist centres – King’s College Hospital in the UK, and centres in France, Spain and Brazil.

They applied the new obesity definitions: clinical obesity, where there is clear evidence that excess fat, or adiposity, is causing organ damage, and preclinical obesity, where organ function is preserved despite excess adiposity.

From the surgical candidates, 73.8% had clinical obesity and 26.2% had preclinical obesity. Despite both groups of patients having similar BMI, patients with clinical obesity had far greater surgery-related and cardiovascular risks. They also had an overall high chance of death.

These findings suggest that distinguishing between clinical and preclinical obesity reveals key information about the health status and risks to surgery candidates that BMI alone cannot capture.

This study shows that the distinction between clinical and pre-clinical obesity is clinically meaningful even among surgical candidates with very high BMI levels, because BMI alone cannot tell us who has active disease.”Professor Francesco Rubino, senior author and Chair of Metabolic and Bariatric Surgery at King’s College London

He continued: “It is now essential that future surgical studies and registries systematically report patients’ clinical or pre-clinical obesity status, so that surgical safety, effectiveness and cost-effectiveness can be interpreted in the appropriate clinical context.”

Traditionally, obesity has been classified primarily using BMI, a measure of weight relative to height that provides limited information about whether excess fat is actually affecting a person’s health. BMI levels have historically played a central role in determining eligibility and priority for metabolic bariatric surgery – operations of the stomach that help people lose weight and fix health issues, such as type 2 diabetes.

In 2025, the Lancet Diabetes & Endocrinology Commission on Clinical Obesity proposed a new diagnostic framework. This distinguished between clinical obesity, where there is clear evidence that excess fat, or adiposity, is leading to organ dysfunction, from preclinical obesity, where organ function is preserved but future health risk is increased.

In the latest study, the researchers found that these differences in disease status were not reflected in BMI. In the UK centre, for example, BMI was roughly 47.5 among patients with clinical obesity and 48.5 among those with preclinical obesity. Yet those with clinical obesity were approximately 10 years older and had substantially higher risk of death, cardiovascular risk and operation-related risk.

The researchers argue that for patients with clinical obesity, surgery primarily represents treatment of established disease. On the other hand, for those with preclinical obesity, its key goal may instead be to reduce future health risk. Recognising this distinction could help clinicians plan surgery, as well as select and prioritise surgical candidates.

Read the full study here: https://jamanetwork.com/journals/jamanetworkopen/fullarticle/2852615

Source: King’s College London
Researchers Examine Unanticipated Benefits of GLP-1 Medications

Editorial highlights emerging benefits and questions surrounding this rapidly expanding class of medications

Photo by Haberdoedas on Unsplash

GLP-1 receptor agonists and dual agonists have transformed the treatment of obesity and other metabolic diseases, and a new editorial co-authored by Dr Steven Heymsfield of LSU’s Pennington Biomedical Research Center and Dr Adam Gilden of the University of Colorado examines what scientists are learning as these medications reach millions of people.

The editorial, “Unanticipated Effects of GLP-1 Receptor Agonists: A Net Positive,” was published in the journal Obesity and highlights additional benefits that were not fully anticipated when the drugs were initially developed.

“Most of the unanticipated side effects of GLP-1 receptor agonists have been positive,” the authors wrote.

The researchers highlight evidence suggesting GLP-1 medications may reduce inflammation and lower the risk of certain cardiovascular and musculoskeletal conditions. Emerging studies also suggest the medications may reduce alcohol consumption and the risk of certain substance use disorders, although additional clinical trials are needed to confirm these effects.

At the same time, questions remain about the medications’ effects on lean body mass and nutritional health. Weight loss associated with GLP-1 medications can include reductions in lean mass, including muscle, making it important to understand how to preserve muscle through exercise and appropriate nutrition. Reduced appetite may also increase the risk of micronutrient deficiencies in some patients.

“GLP-1 receptor agonists have already transformed the practice of medicine in the United States, and this change will continue as more medications come onto the market,” the authors wrote.

The researchers identify three key priorities for future GLP-1 research:

  • Understanding the mechanisms behind potential reductions in inflammation,
  • Conducting randomised trials to better understand changes in lean body mass and ways to preserve muscle,
  • Conducting larger randomised trials to determine whether these medications can reduce alcohol use disorders.

Despite the remaining questions, the authors conclude that the evidence available to date supports a favourable overall risk-benefit profile for GLP-1 receptor agonists and dual agonists.

Source: Pennington Biomedical Research Center

GLP-1 Drug Linked to Heart Benefits for High-risk Patients

Findings from clinical practice will help inform shared decision making

Human heart. Credit: Scientific Animations CC4.0

Adding the GLP-1 receptor agonist drug tirzepatide to standard care for patients with type 2 diabetes and heart disease is associated with a lower risk of a major cardiovascular event, such as a heart attack or stroke, finds a study published by The BMJ today.

Randomised trials and observational studies have shown non-inferior effects of tirzepatide compared to another GLP-1 receptor agonist, dulaglutide, for major adverse cardiovascular events (MACE) – a combined measure of heart attack, stroke, and death from any cause. But evidence on the effects of adding tirzepatide to standard care is more limited, resulting in uncertainty for both regulators and clinicians.

To address this, researchers analysed clinical practice data from two US health insurance claims databases between May 2022 and May 2025. They aimed to estimate the cardiovascular effects of adding tirzepatide to standard care for patients with type 2 diabetes, a body mass index of at least 25, and established heart disease by comparing the outcomes to sitagliptin, another diabetes drug.

Sitagliptin was chosen as a neutral placebo proxy based on several studies showing no effect on cardiovascular outcomes.

The main outcome of interest was a reduction in MACE, which was monitored from the first day of treatment up to one year, or until the individual stopped or switched treatment, or disenrolled from the health plan.

Factors including age, sex, race, body mass index, previous heart problems, other chronic conditions, and medication use were taken into account, and a technique called propensity score overlap weighting was used to balance out differences between the two groups to draw more reliable conclusions.

A total of 52,971 individuals were included in the analysis (average age 70 years; 51% female), of whom 35,353 started tirzepatide and 17,618 started sitagliptin.

At one year, the risk of MACE was 2.9% in the tirzepatide group and 4.4% in the sitagliptin group (a 32% relative reduction), and the researchers estimate that for every 70 patients starting tirzepatide, one case of MACE would be prevented.

For individual MACE components, tirzepatide was associated with a 33% lower risk of heart attack compared with sitagliptin, whereas ischaemic stroke showed no meaningful difference.

Infections requiring hospital admission were also lower with tirzepatide (one admission prevented for every 48 patients), as was infection related death (one death prevented for every 200 patients) and death from any cause (one death prevented for every 122 patients).

This is an observational study, but the researchers previously benchmarked their design, data, and analytics infrastructure against a randomised controlled trial before drawing conclusions about cause and effect.

They also acknowledge several limitations including a relatively short follow-up period, which may underestimate long term cardiovascular and safety effects, possible misclassification of treatment duration or outcomes, and findings may not apply to other healthcare systems or patients without established cardiovascular disease.

However, they conclude: “This study shows how trial-anchored evidence from clinical practice can estimate the expected cardiovascular benefit of initiating tirzepatide beyond standard background treatment and inform shared decision making.”

A linked editorial notes that while this study provides an important, transparent estimate of what initiating tirzepatide might achieve in routine care, it does not establish a mortality indication or define the best sequence for cardiometabolic therapy.

The authors say longer follow-up, randomised and pragmatic comparisons, and more studies of additive benefit on contemporary background treatment are needed. Furthermore, cardiovascular efficacy cannot benefit a population if cost, authorisation barriers, supply, and discontinuation prevent sustained treatment, they add.

As such, they conclude: “The signal is compelling; the causal and clinical placement questions remain open.”

Source: BMJ Group

South Africa’s Weight-Management Market Needs Stronger Safeguards for Women

By Dr Gerhard Vosloo, Founder and Head Consulting Practitioner at Dr GL Vosloo Medical Practice, managed by BioWell

Prescription-based weight management treatment has surged into the mainstream, giving more people with genuine clinical needs access to potentially life-changing care. However, the market’s growth has not been matched by consistently high standards of care. This Women’s Month, we must confront the fact that many women remain particularly vulnerable to inadequate clinical oversight, inappropriate prescribing practices, and black-market products that operate outside established medical safeguards.

Nearly seven in ten adult South African women are obese, compared to four in ten men. Women therefore account for a significant share of the weight-management market and, as a result, may face greater exposure to irresponsible medical practices and unregulated black-market options, where proper clinical support and control are virtually non-existent.

At Dr GL Vosloo Medical Practice, managed by BioWell, women make up the majority of patients seeking a holistic weight-loss and metabolic management programme, which may include prescription treatment where clinically justified. Concerningly, some patients arriving from other programmes report excessively high dosages of treatments, with scarce oversight or guidance. Others have used black-market products and later sought professional medical help after struggling to manage their treatment safely and effectively.

These experiences demonstrate exactly why prescription treatment should form part of a broader, medically-supervised programme rather than a medication-only approach. As more women seek treatment, the industry has a duty to help them understand what good clinical care and appropriate dosing practices involve, as well as how to distinguish a medically grounded programme from those built primarily around access to medication.

Not all weight-management programmes are created equal. Patients should look for a few key indicators that suggest a provider is delivering safe, responsible care:

  1. Screening should begin before the consultation

Before the first appointment is even scheduled, a reputable practice or physician should gather sufficient information to understand a patient’s medical history, current health status, and potential risk factors. For example, intake forms may ask about previous weight-loss treatments, allergies, pregnancy or breastfeeding status, eating habits, goals, and other information that may help the practitioner identify contraindications early.

Patients should expect this information to be reviewed before they proceed. Any omissions or concerns should be raised, while patients with possible contraindications, urgent medical issues, or conditions outside the programme’s scope should be informed and referred where necessary.

  1. The consultation should establish clinical need and risk

Patients should expect a thorough consultation that explores their concerns, goals, medical and treatment history, symptoms, and relevant lifestyle or health factors. It should also give the doctor an opportunity to clarify uncertainties, identify undisclosed contraindications, and assess appetite, eating behaviour, level of activity, sleep quality, and mental health.

For women, this may include menstrual health, contraceptive use, pregnancy plans, breastfeeding, menopause, polycystic ovary syndrome, hormone treatment, and previous gestational diabetes.

A medical assessment should establish whether prescription treatment is clinically appropriate, rather than being prescribed simply because a patient wants to lose weight. Relevant considerations may include body measurements, blood pressure, glucose, cholesterol, organ and thyroid function, vitamin and hormone levels, and pregnancy screening where relevant.

  1. Treatment decisions should be fully explained before consent

Doctors should provide a clear explanation of whether prescription therapy is appropriate, whether it should be delayed or avoided, or whether another treatment approach may be more suitable. Prescription-based medication should not be framed as the primary intervention, although it may form part of a broader programme covering nutrition, exercise, behaviour, supplementation, metabolic support, clinical monitoring, and guidance on how these elements work together.

Before written consent is given, patients should be informed about the expected benefits, potential side effects, serious risks, contraindications, alternatives, monitoring requirements, and circumstances under which treatment may be stopped. Women should also be informed about how pregnancy plans, breastfeeding, hormonal treatment, or changing health circumstances may affect whether treatment can begin or continue.

  1. Prescriptions should be individualised and closely monitored

Patients should be cautious of one-size-fits-all prescribing practices. Treatment should reflect the individual’s clinical needs and risk profile, using a conservative approach rather than a standard dose or automatic escalation schedule.

Ongoing follow-up is equally important. Regular check-ins should track progress, side effects, relevant eating and lifestyle factors, and any changes in health or medication use, with treatment adjusted accordingly. For women, this continuity is particularly important because hormonal, reproductive, and life-stage circumstances may change during treatment and affect how care is managed.

Women should not have to navigate a fast-moving treatment market through trial and error. By understanding the characteristics of safe, medically supervised care, patients are better equipped to make informed choices. Ultimately, however, the responsibility rests with practitioners and clinics to make ethical, medically-grounded care easy to recognise from the outset. Public trust in this treatment category will depend on how consistently the industry meets that standard.

Leg Ulcer Wraps Offer No Healing Advantage, Trial Finds

Photo by Etactics Inc on Unsplash

Compression wraps are unlikely to help venous leg ulcers heal faster than standard compression treatments, according to a clinical trial led by University of Manchester and York researchers. 

The findings of the study, funded  by the National Institute of Health and Care Research (NIHR) suggest the wraps may not be the best first-line option for patients receiving strong compression therapy. 

Venous leg ulcers affect thousands of people and can take months to heal, causing pain, reduced mobility and a significant burden on healthcare services. 

Strong compression is an important treatment for people with venous leg ulcers, to improve blood flow in the lower leg and support healing. 

It can be provided in different ways, including bandages systems that can have two or four layers, compression stockings that have two layers and adjustable compression wraps that fasten around the leg with Velcro-style straps. 

All these compression approaches aim to deliver the same level of compression but differ in how they are applied, how easy they are to use and how comfortable people find them. 

Wraps have become increasingly popular because they can be adjusted and, in some cases, self-applied by people with leg ulcers or those around them.  However, there has been limited high-quality evidence comparing compression wraps with other commonly used strong compression treatments. 

The researchers carried out a large randomised controlled trial involving 637 adults receiving care at 33 mainly community sites across the UK. 

Participants were assigned to be offered either compression wraps, two-layer compression bandages, or established evidence-based compression treatments (four-layer bandages or two-layer compression stockings).

The researchers found that ulcers healed more slowly in patients offered compression wraps than in those offered established evidence-based compression treatments. 

Patients receiving compression wraps also appeared to heal more slowly than those treated with two-layer compression bandages, although this difference was not statistically significant. 

The study found that two-layer compression bandages performed similarly to established evidence-based compression treatments. 

The findings provide some of the strongest evidence to date comparing commonly used compression therapies for venous leg ulcers. 

A separate companion process evaluation found patients liked compression wraps because they were comfortable, easy to adjust, and could be removed for showering, 

However, these same features may also mean that people are more likely to loosen or remove the wraps, potentially reducing the amount of therapeutic compression delivered and helping explain the slower healing observed in the trial. 

Together, the studies suggest compression wraps should not routinely be the first choice for most people with venous leg ulcers. 

However, they may still be appropriate for some patients where comfort, independence or self-management are particularly important, provided patients receive clear advice on maintaining effective compression. 

Jo Dumville, Professor of Applied Health Research from the University of Manchester said: “Venous leg ulcers can have a major impact people’s quality of life and place a significant burden on healthcare services, so it is important that health professionals have robust evidence to guide treatment decisions”. 

“Our study compared three commonly used strong compression approaches in a real-world NHS setting and suggested that  that compression wraps do not improve healing times when compared with established evidence-based treatments.” 

Catherine Arundel, Senior Research Fellow at the University of York said: “While some uncertainty remains, these findings suggest that compression wraps are unlikely to offer a healing advantage as a first-line treatment”. 

“The results will help clinicians, patients and healthcare providers make informed decisions about the most appropriate therapies for managing venous leg ulcers.” 

  • The paper Compression therapies for venous leg ulcers: The VENous Ulcer Study 6 (VenUS 6), an open, multicentre, randomised clinical trial is published in PLOS Medicine https://doi.org/10.1371/journal.pmed.1005154
  • The companion process evaluation Compression therapies for the treatment of venous leg ulcers: a mixed method process evaluation in a randomised controlled trial, VenUS6  is published in Trials https://doi.org/10.1186/s13063-023-07681-7

Source: University of Manchester

Newer Obesity Drugs Linked to Fewer Alcohol-related Hospitalisations

Use of newer GLP-1 receptor agonists for obesity or diabetes was associated with a reduction in hospital admissions suggesting a potential role for the treatment of alcohol-use disorder

Photo from Pixabay CC0

Use of newer GLP-1 receptor agonists (semaglutide or tirzepatide) for obesity or diabetes by people with alcohol-use disorder was associated with a reduction in alcohol-related admissions to hospital, finds a study published online in the open access journal BMJ Open.

The findings suggest a potential role for the drugs semaglutide and tirzepatide in the treatment of alcohol-use disorder.

While GLP-1 receptor agonists are used primarily for the treatment of type 2 diabetes and obesity, there have been reports of reduced alcohol consumption among patients taking the drugs, prompting the authors to investigate the potential impact on alcohol-related hospitalisations among adults with alcohol-use disorder.

The study compared alcohol-related hospitalisations in 40 703 adults with alcohol-use disorder and type 2 diabetes or obesity who started a newer GLP-1 receptor agonist (semaglutide or tirzepatide) or a comparator drug between 1 January 2018 and 31 December 2024. Participants were split across four trials involving clinically distinct populations – the anti-diabetic medication (ADM) trial, anti-obesity medication (AOM) trial, medications for alcohol use disorder with type 2 diabetes (MAUD- T2D) trial, and medications for alcohol-use disorder with obesity (MAUD-obesity) trial.

Compared to participants taking an active comparator drug, those taking GLP-1 receptor agonists had a lower risk of alcohol-related admission to hospital during all four trials.

Use of GLP-1 receptor agonists was associated with a 26% lower risk of alcohol-related hospital admission than other diabetes medicines during the diabetic medication (ADM) trial, and a 32% lower risk of alcohol-related hospital admission than other obesity medicines during the anti-obesity medication (AOM) trial.

In the MAUD trials, the active comparators were drugs for alcohol-use disorder including acamprosate, disulfiram and naltrexone. Compared with taking drugs for alcohol-use disorder, use of GLP-1 receptor agonists by adults with type 2 diabetes was associated with a 63% lower risk of alcohol-related admission to hospital during the trial, and for adults with obesity use of GLP-1 receptor agonists was associated a 65% lower risk of alcohol-related hospitalisations.

The authors acknowledge several limitations to their study. Most importantly, alcohol-use disorder is under-captured due in part to stigmatisation, and when documented, it may also be recorded variably with lower reporting in areas of high social deprivation. Alcohol-related outcomes may have been under captured as they were defined using diagnosis codes and laboratory testing for alcohol exposure, and the study captured hospitalisations from treatment initiation to discontinuation in a trial environment, so treatment effects in an average clinical setting may differ.

Finally, there may have been some confounding in relation to socioeconomic status, underlying clinical stability or alcohol-use disorder severity, and healthcare engagement, as newer GLP-1 receptor agonists are higher-cost therapies and patients with access to these medications may differ from comparator groups.

The risk of residual confounding was greatest in the MAUD trials, as reflected by the reduced risk of non-alcohol-related hospitalisations with use of GLP-1 receptor agonists. The authors say the results of the MAUD trials should be interpreted with greater caution as there were also high rates of treatment discontinuation increasing the potential for bias.

Nevertheless, the authors conclude, “Initiation of newer GLP-1 receptor agonists among patients with alcohol-use disorder was associated with a lower observed risk of alcohol-related hospitalisation, with similar associations across populations with type 2 diabetes and obesity.

“These findings may suggest a potential role for GLP-1 receptor agonists in the context of alcohol-use disorder.”

Source: The BMJ Group

Researchers Uncover Possible Cause of Muscle Pain from Statins

The discovery may explain side effects from taking statins, opening the door to future therapies that could make statins easier to tolerate.

Photo by Towfiqu Barbhuiya on Unsplash

Millions of people rely on statins to lower cholesterol and reduce the risk of heart attack and stroke. But for some, the drugs come with an unwelcome trade-off: muscle pain, weakness and exercise intolerance that can make it difficult to continue treatment.

Now, researchers at McMaster University have uncovered a biological pathway that may explain why those side-effects occur, opening the door to future therapies that could make statins easier to tolerate while maintaining their life-saving cardiovascular benefits.

Published in Science Advances, the study identifies an immune and metabolic mechanism that drives statin-induced muscle damage, challenging longstanding assumptions about how these side-effects develop.

“Statins are among the most effective medications we have for reducing cardiovascular disease risk and preventing early death,” said senior author Jonathan Schertzer, a professor in McMaster’s Department of Biochemistry and Biomedical Sciences.

“Unfortunately, muscle side-effects lead some people to reduce their dose or stop taking the medication altogether. We wanted to understand why this happens and whether it might be possible to separate the side effects from the benefits.”

Statin-associated muscle symptoms affect an estimated seven to 29 per cent of people who take the drugs. While researchers have long known that statins can sometimes cause muscle problems, the biological mechanisms behind those effects have remained unclear.

Led by first authors Nazli Robin and Nicole Barra of the Schertzer Lab at McMaster, the team found statins can disrupt how muscle cells produce energy, triggering an immune response that damages muscle tissue. In experiments using muscle cells and mouse models, researchers were able to prevent much of that damage by blocking the immune response.

“One of the most exciting findings of the research is that the mechanism causing muscle side-effects appears to be separate from the mechanism that lowers cholesterol,” said Schertzer. “That suggests it may one day be possible to target the side-effects without interfering with the cardiovascular benefits that make statins so valuable.”

The study also revealed an unexpected link between metabolism and immunity. Researchers found that changes in muscle-cell metabolism triggered an immune response within the cells themselves, providing new insight into how inflammation can contribute to drug side-effects.

Although additional research will be needed before the findings can be translated into therapies for patients, the discovery identifies several potential targets for future drug development aimed at preventing statin intolerance.

“These findings give us a clearer understanding of why some patients experience muscle symptoms and provide promising directions for making these important medications safer and more effective in the future,” added Schertzer.

Source: McMaster University

Some Blood Types May Have an Increased Risk of Mortality in Haemodialysis

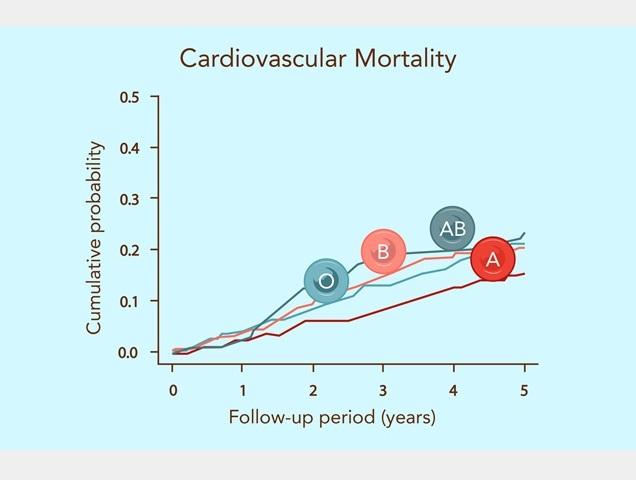
Cardiovascular mortality by blood type. Haemodialysis patients with blood type A were found to have lower risks of cardiovascular mortality. Credit: Osaka Metropolitan University

Few realise blood types could also be linked to disease risks. In the general population, people with blood type O have been reported to have a lower risk of cardiovascular disease and cardiovascular mortality. Other non-cardiovascular conditions are also associated with ABO blood types, such as certain cancers and infectious diseases. However, these numbers do not take into consideration the population of haemodialysis patients who face higher risks than the general population.

Cardiovascular disease is the leading cause of death among dialysis patients, but its relationship to blood type has often been overlooked. To address this, a research group, led by Dr Masafumi Kurajoh at Osaka Metropolitan University’s Graduate School of Medicine, conducted a large-scale prospective cohort study to examine whether the association between blood type and cardiovascular risk seen in the general population also exists in patients undergoing haemodialysis. The study included 1671 patients receiving haemodialysis at 17 medical facilities in Osaka Prefecture. Participants’ health was tracked for approximately five years, and the associations between ABO blood type and all-cause, cardiovascular, and non-cardiovascular mortality were analysed. 

By follow-up, 464 patients had died, including 278 from cardiovascular disease. The researchers found that patients with blood type A were associated with lower risks of both all-cause and cardiovascular mortality. In contrast, blood type was not associated with non-cardiovascular mortality, including deaths due to infections or malignancies.

“A particularly notable finding is that, while blood type O has been associated with lower cardiovascular risk in the general population, blood type A was associated with lower risk in dialysis patients,” said Dr Kurajoh. “These results suggest that cardiovascular disease may develop through different mechanisms in haemodialysis patients.”

More so, blood type O’s reputation of being at lower risk is partially due to lower plasma von Willebrand factor (VWF), a blood glycoprotein, and factor VIII, a blood-clotting protein. However, the result of blood type A dialysis patients having lower cardiovascular mortality risks shows that differences in VWF and factor VIII levels are unlikely to be the root cause.

“At present, our findings do not support changing treatment or prevention strategies based on blood type,” Dr Kurajoh added. “However, understanding why blood type A was associated with lower cardiovascular mortality may provide new insights into the mechanisms of cardiovascular disease in dialysis patients and help guide future preventive and therapeutic approaches.”

The findings were published in Kidney International Reports.

Source: Osaka Metropolitan University

Sun Pharma Launches Generic Semaglutide in South Africa

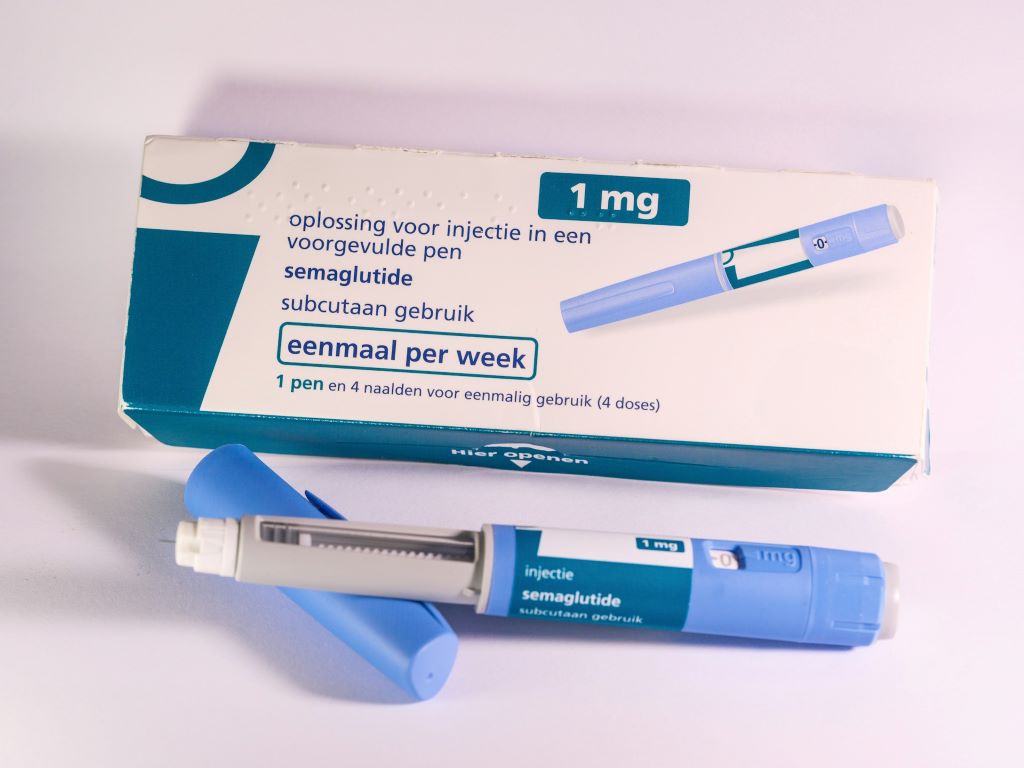
Johannesburg, 21 July 2026 — Sun Pharmaceutical Industries Limited (Reuters: SUN.BO, Bloomberg: SUNP IN, NSE: SUNPHARMA, BSE: 524715) (together with its subsidiaries and/or associated companies, “Sun Pharma”) today announced the launch of generic semaglutide, a once‑weekly GLP‑1 receptor agonist, in South Africa for the treatment of adults with inadequately controlled type 2 diabetes mellitus as an adjunct to diet and exercise.

The product is supplied in a pre‑filled, multi‑dose injectable pen in two strengths (2 mg/1.5 mL and 4 mg/3 mL) that allow flexible, once‑weekly dosing. The device features a smooth dialer for accurate dose selection and a concealed needle to improve handling safety and reduce injection anxiety. The pens are manufactured in Europe and developed with established pharmaceutical device suppliers.

“Type 2 diabetes remains a major public‑health challenge in South Africa,” said Malcolm Brown, Chief Executive Officer, Sun Pharma South Africa. “The availability of generic semaglutide strengthens the range of evidence‑based treatment options available to clinicians and patients. Our objective is to support better clinical outcomes by improving access to proven therapies that can be integrated into comprehensive diabetes care.”

Clinical context and public‑health relevance

  • Type 2 Diabetes remains one of South Africa’s most significant public health challenges. As per the International Diabetes Federation country report, it is estimated that 3.9 million patients aged 20-79 would be living with diabetes in South Africa by 2050.
  • South Africa faces a growing burden of type 2 diabetes, driven in part by rapid urbanization and changing lifestyles. This rising prevalence places significant pressure on patients and healthcare services. Improving access to effective therapies is therefore an important component of addressing this national health challenge.
  • With the launch of generic semaglutide in South Africa, Sun Pharma aims to provide clinicians and patients with an additional licensed option for comprehensive diabetes management, supporting better long‑term outcomes when used alongside diet and exercise.

Regulatory and medical review

Healthcare professionals are advised to consult full prescribing information and local treatment guidelines when considering semaglutide for individual patients. The company’s local medical team is available to assist clinicians with scientific inquiries and product information.

About Sun Pharmaceutical Industries Limited. (CIN – L24230GJ1993PLC019050)

Sun Pharma is a leading global pharmaceutical company with a presence in Innovative Medicines, Generics and Consumer Healthcare products. It is the largest pharmaceutical company in India and is a leading generic company in the US as well as Global Emerging Markets. Sun’s high growth Global Innovative Medicines portfolio spans innovative products in dermatology, ophthalmology, and onco-dermatology and accounts for about 22% of company sales. The company’s vertically integrated operations deliver high-quality medicines, trusted by physicians and consumers in over 100 countries. Its manufacturing facilities are spread across five continents. Sun Pharma is proud of its multi-cultural workforce drawn from over 50 nations. “For further information, please visit www.sunpharma.com and follow us on LinkedIn & X (Formerly Twitter).”

Muscles Matter for Diabetes Risk, New Study Finds

Photo by John Arano on Unsplash

A major new international study led by Curtin University, has found diabetes risk is about more than just body weight or obesity, revealing muscle health also likely plays a big role in whether people will develop the condition.

Published in one of the world’s leading diabetes journals, Diabetes Care, the study saw researchers from the Curtin School of Population Health and Dementia Centre of Excellence at the Curtin enAble Institute analyse health data from nearly 480 000 adults over 14 years – all of whom were diabetes-free at the beginning of the study.

The team found people with both excess body fat and poor muscle health – a condition known as sarcopenic obesity – were more than three-and-a-half times as likely to develop type 2 diabetes than people with healthy body composition.

It also found people with sarcopenic obesity were 19 per cent more likely to develop type 2 diabetes than people with obesity alone and 91 per cent more likely to develop type 2 diabetes than people with low muscle mass and strength (sarcopenia) alone.

Lead author and PhD candidate Zhongyang Guan said the findings challenge the common perception diabetes risk is primarily driven by body weight.

“Most people know carrying excess weight can increase the risk of type 2 diabetes, but our findings show muscle health is also an important piece of the puzzle,” Mr Guan said.

“People with both excess body fat and low muscle mass had a substantially higher risk of developing type 2 diabetes than those with obesity alone.

“This suggests we need to look beyond the number on the scales when assessing diabetes risk, as maintaining muscle strength and muscle mass may be just as important as managing body weight.”

The study found nearly 15 per cent of people with sarcopenic obesity developed type 2 diabetes within 10 years, compared with around 11 per cent of people with obesity alone and just 3 per cent of people without sarcopenia or obesity.

The link was particularly strong among women and adults under the age of 60.

Project senior lead Professor Mario Siervo said the results supported a broader approach to diabetes prevention.

“Healthcare professionals routinely monitor body weight and obesity, but our findings suggest assessing muscle health could help identify people at high risk earlier,” Professor Siervo said.

“As populations age and rates of obesity continue to rise, preserving muscle health through regular physical activity and healthy lifestyle habits could play an important role in reducing the burden of type 2 diabetes.”

Diabetes WA Clinical Services Manager Jessica Weiss said the findings highlighted the important role muscle plays in controlling blood sugar levels and reflected what health practitioners were seeing firsthand.

“We know our muscles use a lot of our glucose for fuel and working them during physical activity is a great way to help use up glucose from our blood and regulate glucose levels,” Ms Weiss said.

“Physical activity also reduces our body’s resistance to insulin, an important element to type 2 diabetes.

“The more muscle we have and the more regularly we use them, the better equipped our body is to prevent or manage type 2 diabetes.”

By Samuel Jeremic

Source: Curtin University