FDA Requires New Warning on GLP-1 Drugs for Rare Vision-Loss Risk
Labelling update will note potential association with NAION, a condition that can cause permanent monocular vision loss
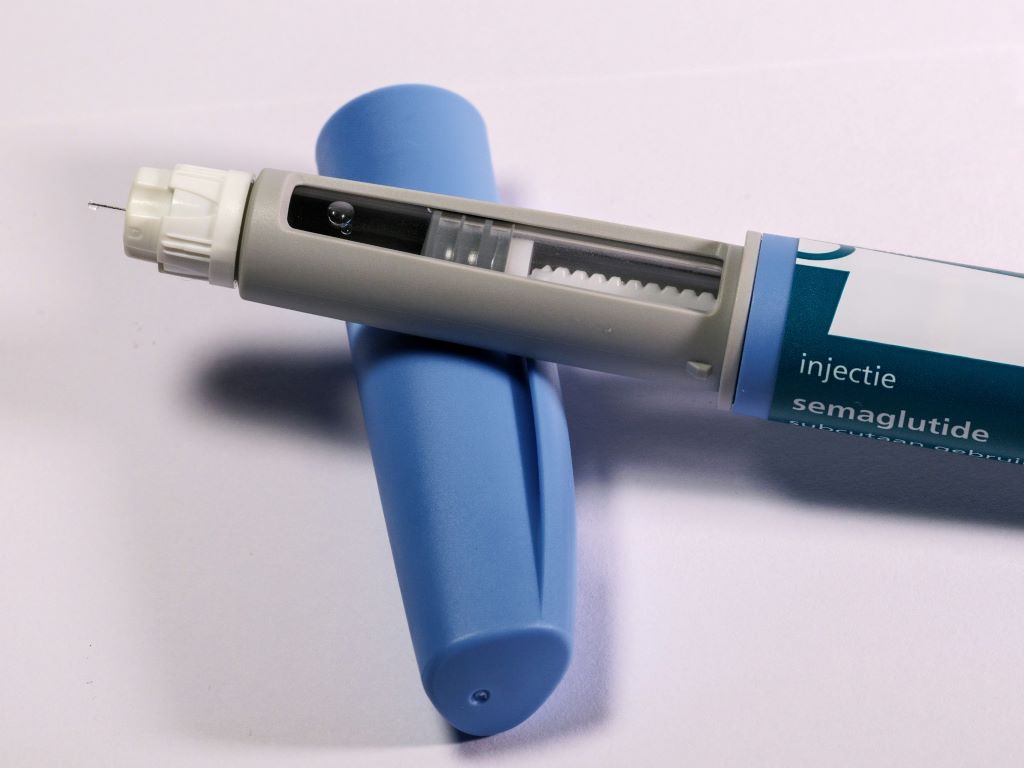
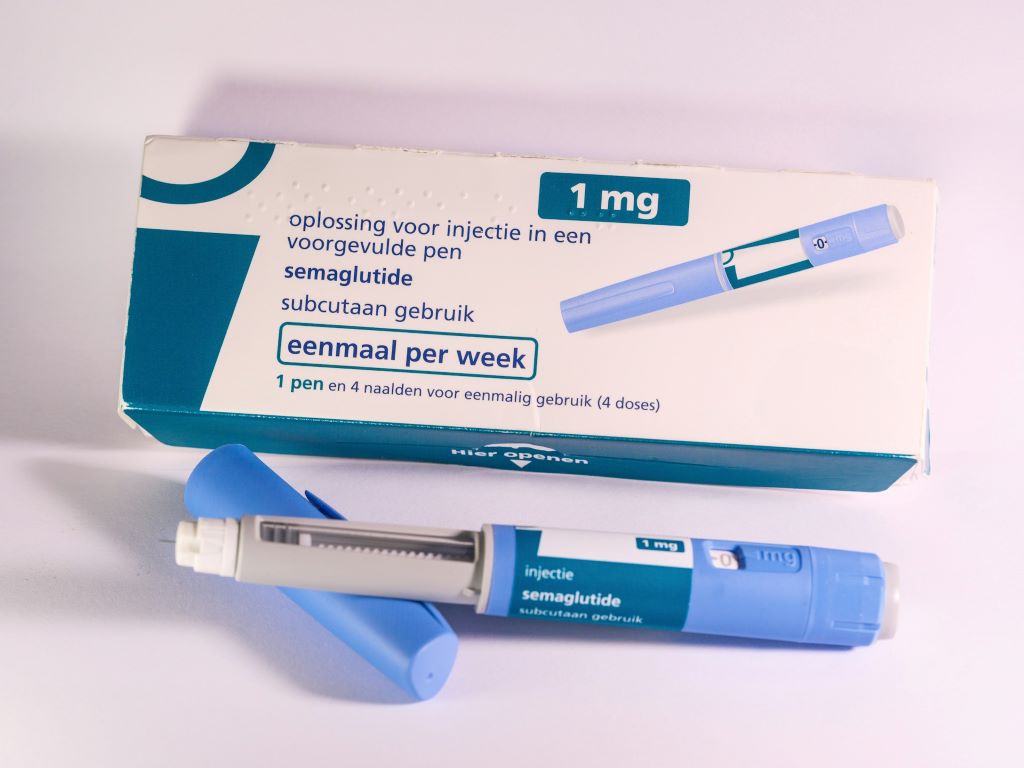
The U.S. Food and Drug Administration is requiring manufacturers of all glucagon-like peptide-1 receptor agonists (GLP-1 RAs) to add information about a potential increased risk of non-arteritic anterior ischaemic optic neuropathy (NAION) to the Warnings and Precautions section of product labelling.
NAION is a rare condition that can produce acute, painless vision loss in one eye, including permanent impairment, the agency said in a drug safety communication issued November 9, 2026. Cases have been reported with every currently marketed GLP-1 RA.
Key Takeaways
- FDA is requiring a class-wide Warnings and Precautions labelling change for GLP-1 RAs to note a potential increased risk of NAION.
- In an FDA meta-analysis of 126 randomised trials, the NAION incidence was 6.4 events per 100 000 person-years with GLP-1 RAs versus 3.8 with placebo or non-GLP-1 glucose-lowering drugs.
- Clinicians should counsel patients to report sudden painless monocular vision changes immediately and refer suspected cases promptly to ophthalmology; discontinuation should be considered unless benefits clearly outweigh risks.
The agency is requiring application holders for all GLP-1 RA medications to add information to the Warnings and Precautions section of labelling about the potential increased risk of NAION associated with use of these medications,” the FDA stated. NAION results from reduced blood flow to the optic disc; its precise pathophysiology is incompletely understood. Established risk factors include smoking, diabetes, hypertension, sleep apnoea, anaemia, and kidney disease. Occurrence in one eye elevates the risk of involvement of the fellow eye.
Symptoms typically include sudden, painless vision loss in one eye (often noticed on waking), visual-field defects such as blind spots or tunnel vision, colour distortion, and reduced central acuity. Patients should seek medical attention immediately if these occur. Individuals with a prior NAION event should discuss with their clinician whether to continue or stop the GLP-1 RA.
This requirement comes after a wave of studies pointing to a possible association between GLP-1 drugs and NAION, including a 2024 observational study involving semaglutide.
The agency examined clinical-trial data, animal studies, postmarketing reports, and observational analyses. A meta-analysis of 126 trials encompassing 134 253 patients (78 217 treated with a GLP-1 RA) and nearly 289 000 person-years of exposure identified 15 probable NAION events – 10 among GLP-1 RA recipients and 5 among those receiving placebo (none among recipients of other non-GLP-1 glucose-lowering agents). This yielded the 6.4 versus 3.8 per 100 000 person-years rates noted above. Background incidence in adults older than 50 years is estimated at 2.3 to 10.2 cases per 100 000p-y.
Europe’s drug regulator warned about the risk 17 months ago.
A separate FDA retrospective cohort analysis in adults with type 2 diabetes found no statistically significant increase in NAION risk with GLP-1 RAs versus SGLT-2 inhibitors, but a higher risk versus DPP-4 inhibitors. Animal data did not reveal a clear mechanism. The absolute risk remains low, and the FDA characterised the finding as a potential association rather than a confirmed causal relationship.
GLP-1 RAs (including semaglutide, tirzepatide, liraglutide, dulaglutide, and others) are approved for type 2 diabetes, chronic weight management, and selected cardiovascular, renal, and other indications. The labelling change applies across the class, including dual GIP/GLP-1 agonists and the oral agent orforglipron.
NAION presents as acute, painless monocular vision loss, often noticed upon awakening, with an altitudinal or other visual-field defect and a relative afferent pupillary defect. Fundoscopy typically shows disc oedema in the acute phase, followed by pallor. There is no established acute treatment that restores vision; management focuses on secondary prevention (control of vascular risk factors, smoking cessation) and counselling about the roughly 15–25% risk of sequential involvement of the fellow eye over subsequent years. Prompt ophthalmology or neuro-ophthalmology referral is essential both to confirm the diagnosis and to exclude arteritic causes (giant-cell arteritis), which require urgent systemic corticosteroids. In the GLP-1 RA context, shared decision-making about drug continuation should weigh the substantial cardiometabolic benefits against the small absolute increment in this rare event, particularly in patients with preexisting optic-nerve risk factors.
Healthcare professionals are advised to instruct patients to report sudden monocular visual changes immediately, refer suspected cases urgently, and consider discontinuing the GLP-1 RA unless treatment benefits clearly outweigh the risk.