Category: Cancer

Transperineal Prostate Biopsy is Safer than the Standard Technique
Credit: Darryl Leja National Human Genome Research Institute National Institutes Of Health

A multi-institutional clinical trial led by Weill Cornell Medicine and NewYork-Presbyterian investigators showed that a newer technique for collecting prostate biopsy samples reduced the risk of infection compared with traditional biopsy approaches and removed the need for prophylactic antibiotics. The results of the study appear in JAMA Oncology.

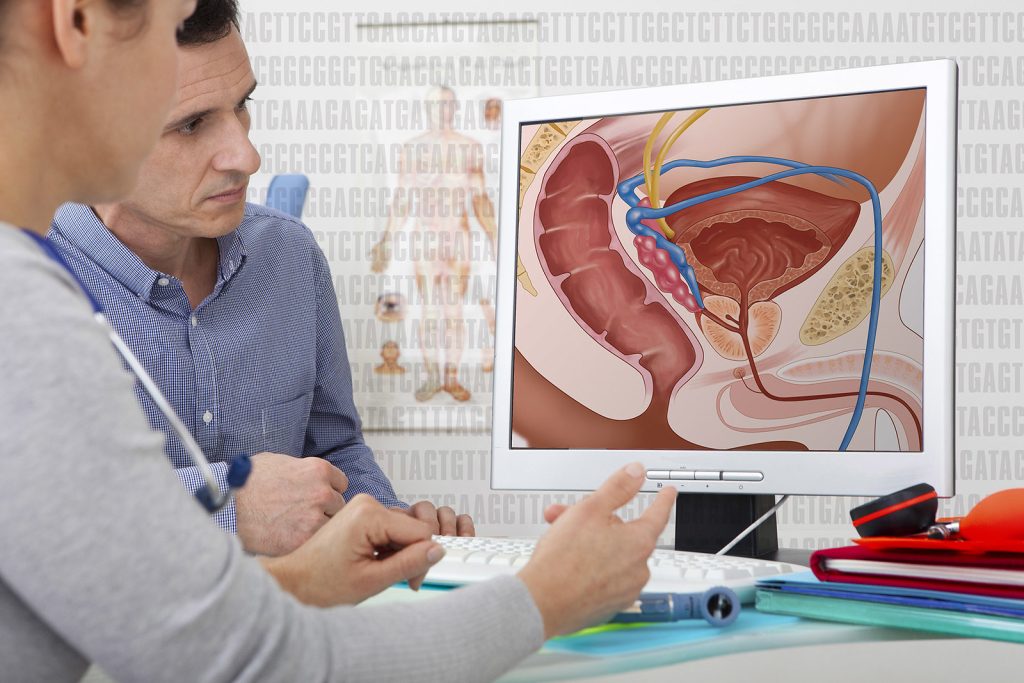
The technique, called transperineal prostate biopsy, collects prostate tissue via a needle through the skin of the perineum, the area between the rectum and the scrotum. The procedure, which uses local anesthesia to numb the area, allows physicians to bypass the traditional and more infection-prone route of collecting prostate biopsy tissue with a needle through the rectum.

The PReclude infection EVEnts with No prophylaxis Transperineal (PREVENT) trial, funded by the National Cancer Institute, part of the National Institutes of Health, was conducted at multiple sites, including NewYork-Presbyterian/Weill Cornell Medical Center, NewYork-Presbyterian Queens and NewYork-Presbyterian Brooklyn Methodist Hospital. The study found no infections among 382 men randomised to undergo the transperineal procedure compared with six infections affecting 1.6% of the 370 men randomised to undergo the traditional transrectal biopsy procedure. The lower infection rate is particularly remarkable because the men in the transrectal biopsy group received a targeted course of antibiotics designed to help reduce their infection risk, and the men in the transperineal group received no antibiotics.

“Transperineal biopsy should be the new standard of care for prostate biopsy,” said Dr Jim Hu, Professor of Urologic Oncology at Weill Cornell Medicine. “It was as effective as the traditional transrectal biopsy approach at detecting cancer, but without the risk of infection or the need for antibiotics.”

Prostate biopsies are an essential tool for detecting prostate cancer, and about 3 million people worldwide undergo the procedure each year. Dr Hu noted that physicians collect about 90% of these biopsies in the United States via a transrectal procedure. Yet studies have found that 5% to 7% of patients develop infections after biopsy, and 1% to 3% require hospitalisation for these complications, he said. To help prevent infections, physicians typically prescribe a prophylactic course of antibiotics before the procedure.

Dr. Hu noted that the investigators used a personalised approach to prophylactic antibiotics in the patients undergoing the transrectal biopsy procedure. Rather than giving the men a broad-spectrum antibiotic or multiple antibiotics, they matched the antibiotics to cultures obtained from the patient’s rectum during prostate exams before the procedure. This targeted antibiotic approach reduced the infection rate in those undergoing the traditional transrectal procedure substantially compared with the national infection rate for the procedure. Yet, they achieved a statistically significant reduction in infections in the transperineal group by eliminating infections altogether.

 “Transperineal prostate biopsy makes a common diagnostic procedure safer for men,” said Dr Hu, who is also a member of the Sandra and Edward Meyer Cancer Center at Weill Cornell Medicine. “It also eliminates the use of antibiotics, helping to reduce the emergence of antibiotic-resistant infections, a growing public health concern.”

Despite the promise of the new procedure, Dr. Hu acknowledged a few hurdles to making it more widely available to men in the United States. He explained that few physicians in the country have been trained in the perineal procedure. Additionally, he noted that US insurers pay the same amount for either procedure but the transperineal biopsy costs more and takes longer to perform, creating a financial disincentive for physicians to make the switch.

However, there is reason to think the status quo will change, Dr Hu said, noting the switch to transperineal prostate biopsies in Norway after a man died after a routine transrectal prostate biopsy. The change virtually eliminated biopsy-related infections and deaths in that country with the nationwide switch to transperineal biopsy, he said.

“There is a strong case to make the switch,” he said. “It will take time. But as more patients request the new procedure, we think it will become more widely available.”

Source: Weill Cornell Medicine

New Trial of Drug Shows Promise in Combating Cancer-caused Cachexia

Photo by Tima Miroshnichenko on Pexels

Researchers discovered a drug that safely and effectively helped cancer patients when they suffered from cachexia, a common condition related to cancer that involves weight loss and muscle wasting.

The results of the randomised phase 2 clinical trial, which included 187 individuals who experienced cachexia with pancreatic (32%), colorectal (29%) or non–small-cell lung (40%) cancer, appear in the New England Journal of Medicine.  Richard Dunne, MD, MS, a Wilmot Cancer Institute oncologist and cachexia expert was part of the large group of investigators who ran the nationwide clinical trial.

Cachexia involves loss of appetite and weight, muscle-wasting, fatigue, and weakness. It affects more than 50% of people who have cancer, and currently there are no FDA-approved treatments.

Scientists discovered that the monoclonal antibody ponsegromab blocks a hormone known as GDF-15 that regulates appetite and body weight. The patients in the trial had elevated levels of GDF-15, a primary driver of cachexia, and ponsegromab improved many aspects of cachexia and its symptoms.

Patients were randomised to receive ponsegromab at doses of 100mg, 200mg, or 400 mg, or to receive placebo. At 12 weeks, patients in the ponsegromab groups had significantly greater weight gain than those in the placebo group, with a median between-group difference of 1.22 kg in the 100mg group, 1.92 in the 200mg group, and 2.81 in the 400mg group. Improvements were observed across measures of appetite and cachexia symptoms, along with physical activity, in the 400mg ponsegromab group relative to placebo.

Drugmaker Pfizer supported the study, and released this news. Side effects were minimal, Dunne said, and in fact ponsegromab appeared to be safer than common appetite stimulants used by cachexia patients.

“This is super exciting,” said Dunne, an associate professor of Medicine at the University of Rochester Medical Center. “This study is an important step in providing treatment for the hundreds of thousands of patients who suffer from poor quality of life due to cachexia.”

Several academic medical centres participated in the clinical research, which was led by John D. Groarke, MB, BCh, MPH, at Pfizer. Investigators are continuing to study GDF-15 and the importance of the biomarker in several types of cancer. Other clinical trials are also testing additional cachexia treatments that do not target the GDF-15 pathway.

Source: University of Rochester Medical Center

Yes, Men can Get Breast Cancer

Dr Salomine Theron, a radiologist at the SCP Radiology and Dr Lizanne Langenhoven, who specialises in the treatment of breast cancer, talk about breast cancer in men, how prevalent it is as well as the radiology behind the diagnosis, treatment and surveillance for recurrence.

‘It may come as a surprise that men can develop breast cancer,’ says Dr Langenhoven. ‘In fact, about 1% of all breast cancer cases are diagnosed in men. Unfortunately, men often present with more advanced disease, because they are not aware that they can develop breast cancer in the first place.’

Dr Theron says radiology plays a pivotal role in the diagnosis and treatment of breast cancer in both men and women. However, there is a difference in terms of radiology’s initial role in screening for breast cancer. ‘In women over 40, we recommend an annual mammography,’ she says. ‘In other words, looking for cancers which are asymptomatic. So even if there are no changes to your breast visibly or a lump, we still screen for anything that may develop into breast cancer or has already.

‘In men, that is not standard practice’ Here radiology is diagnostic and the referral is as a result of a lump in the breast, under the arm, there’s puckering or nipple pain. The mammogram differs too. It is a single mammogram image of each breast so that a comparison can be made.  In men, it will also include breast ultrasound and evaluation of the lymph nodes under the armpit.

Dr Theron says, ‘the imaging of a lump may also be incidental. For example, when we do any form of CT imaging on the chest in a male, even when creating images of the lungs, we always look at the soft tissue in the breast area. If we see an asymmetric nodule with an irregular shape (almost like a star) we alert the patient’s healthcare provider, even though that wasn’t the reason for the CT scan’.

Is a breast lump always in men always cancer?

‘No,’ says Dr Langenhoven, ‘About 50% of males develop small lumps in each of their breasts during puberty, usually behind the nipples which can be tender. This is called gynaecomastia – colloquially a ‘stony’ and it’s perfectly normal. It usually goes away as they finish puberty.

‘Breast cancer, on the other hand, usually presents as a firm nodule in one breast that is not tender. There are some men who present with inflammatory breast cancer, where the breast is red, swollen and tender. This is however, a rare but aggressive type of invasive breast cancer in which cancer cells block lymph vessels in the skin.’

She says, ‘the first message is one of awareness.  Men can develop breast cancer.  And that they should see their GP if they become aware of a lump in their breasts which feels firm and asymmetrical or if the breast becomes red, swollen and tender.’

The second message is one of precaution

Women and men can inherit the harmful BRCA1 or BRCA2 gene mutation that belong to a class of genes, known as tumour suppressors and have an increased risk of breast cancer.

Dr Langenhoven says, ‘I have a patient in my practice who presented with a hard lump on his left breast. Because he was aware of his family’s history of breast cancer, he went to his GP for an examination. A mammogram and biopsy confirmed the diagnosis of breast cancer.

She says men with these genes should always be assessed by a genetic counsellor. In addition, should you have a family member diagnosed with male breast cancer, prostate cancer below the age of fifty or ovarian cancer (women), you should seek the opinion of a genetic counsellor to discuss the possible genetic risk and the option of genetic testing. Prevention is better than cure.’

The role of radiology in diagnosis

‘A suspicious lump or mass can only be definitively diagnosed by a biopsy,’ says Dr Theron. She explains that there are three biopsy options:

  • Ultrasound guided core biopsies, where a sample of tissue or blood is taken for testing by a pathologist and a marker is left in the lesion or lump where the sample was taken
  • A fine needle aspiration (FNA) is a procedure to obtain a sample of cells from your body for testing by a cytologist for cancer cells usually of a lymph node or occasionally of a breast mass
  • A vacuum-assisted biopsy can produce slightly larger samples of tissues which is sent to the pathology lab
  • If there is no lump visible on ultrasound, only suspicious calcification on the mammogram, stereotactic guided vacuum biopsy will be done. Put simply, a mammogram will help us find the abnormality to biopsy
  • If the lump is very small or has a cystic component, an ultrasound guided vacuum assisted biopsy will be performed

Radiology at every stage of cancer care

‘Radiology is integral to breast cancer management beyond diagnosis, providing critical information that guides clinical decisions at every stage of care,’ says Dr Theron. ‘This includes staging of the disease, it allows for precise treatment planning, guiding surgical procedures, effective monitoring of treatment responses, early detection of recurrence, all of which are essential for improving patient outcomes.’

Male breast cancer treatment

Men with breast cancer are treated exactly as their female counterparts. Based on the type of breast cancer and the extent (stage), treatment options include chemotherapy, hormone withdrawal therapy, targeted therapies, immunotherapy, surgery and radiotherapy.

‘Even though only one in a hundred diagnosed cases of breast cancer is men,’ says Dr Theron, ‘we still urge men and of course women to check themselves regularly and to see a doctor if they feel or see any changes in their breasts.’

Early detection can save your life.

Can a Cancer Diagnosis Cause Mental Health and Cardiovascular Problems in Family Members?

Study’s findings reveal increased risks, indicating the need for interventions to reduce stress for patients and their relatives.

Photo by Alex Green on Pexels

New research suggests that a family member’s cancer diagnosis may increase first-degree relatives’ and spouses’ risks of developing psychological and cardiovascular illnesses. The findings are published by Wiley online in CANCER, a peer-reviewed journal of the American Cancer Society.

Having a family member diagnosed with cancer can be a stressful and traumatic experience for the entire family. Because stress influences not only mental health but also cardiovascular health, investigators explored whether a cancer diagnosis contributes to negative psychological and cardiovascular outcomes in family members.

Using data from the Utah Population Database, the researchers identified 77 938 first-degree relatives and spouses of 49 284 individuals diagnosed with genitourinary cancer between 1990 and 2015, and they compared them with 81 022 relatives and spouses of 246 775 individuals not diagnosed with cancer.

The team found that 7.1% of relatives and spouses were diagnosed with a psychological illness within 5 years of a family member’s cancer diagnosis, and 7.6% were diagnosed with a cardiovascular illness. Compared with controls, they had 10%, 5%, and 4% higher risks of developing a psychological condition at 1, 3, and 5 years after a family member’s cancer diagnosis. They also had 28%, 16%, and 14% higher risks of developing cardiovascular disease at 1, 3, and 5 years.

Parents of children with cancer experienced the highest risks of developing negative health outcomes – a nearly 4-times increased risk at 1-year compared with other relatives. Also, a diagnosis of kidney or bladder cancer appeared to be the most stressful among genitourinary cancer types, while testis cancer was the least.

“A diagnosis of cancer is a life-changing event for patients and their families. With our group’s unique access to the Utah Population Database, we were able to create multi-generational networks highlighting the impact of a cancer diagnosis on families,” said lead author Mouneeb Choudry, MD, of the Mayo Clinic, in Phoenix, Arizona. “As health care professionals, we should take a multidisciplinary approach to addressing the stress of a cancer diagnosis by helping mitigate financial toxicity, treatment burden, and emotional impact on both the patient and their family.”

Source: Wiley

The Outcomes of Cancer Therapies and BMI Have a Complex Relationship

Risk of mortality during cancer treatment in relation to BMI. For non-small cell lung cancer treatment, immunotherapy seems to pose less risk for persons under a certain BMI, while conventional chemotherapy appears optimal for persons who might be overweight or obese. Credit: Osaka Metropolitan University

While being overweight increases the risk of developing lifestyle-related diseases, there is a phenomenon known as the obesity paradox where a decreased risk of death has been seen during cancer therapy. However, that paradox might not hold true for all cancer therapies, an Osaka Metropolitan University team reports in JAMA Network Open, a publication of the American Medical Association.

Led by graduate student Mr Yasutaka Ihara and Professor Ayumi Shintani of the Graduate School of Medicine’s Department of Medical Statistics, the team used a Japanese administrative claims database of more than 500 000 lung cancer patients and examined the relation between body mass index (BMI) and the risk of mortality during immunotherapy and conventional chemotherapy.

Focusing only on patients with advanced non-small cell lung cancer, the team found that the higher the BMI, the lower the risk of mortality when undergoing both immunotherapy and chemotherapy, though it does a U-turn around a BMI of 24. Patients with a BMI under 28 showed lower risk of mortality when undergoing immunotherapy compared to conventional chemotherapy, but for those at or over that figure, the risk increases with immunotherapy while it continues to get lower with chemotherapy.

“Immunotherapy might not always be the optimal treatment method for obese patients with advanced non-small cell lung cancer, so the use of conventional chemotherapy should also be considered,” Mr. Ihara stated. “In addition to BMI, age, hormones, and gut microbiota have been reported as factors that influence the effectiveness of immunotherapy. Evaluation of whether immunotherapy or conventional chemotherapy improves survival in the presence of these factors is expected to contribute to the development of precision medicine.”

Source: Osaka Metropolitan University

How Cancer Reprograms Immune Cells to Join the Enemy

Squamous cancer cell being attacked by cytotoxic T cells. Image by National Cancer Institute on Unsplash

Cancer has been described as “a wound that does not heal,” implying that the immune system is unable to wipe out invading tumour cells. A new discovery reported in PNAS confirms that a key molecule can reprogram immune cells into turncoats that promote cancer growth.

Studying the behaviour of these “pro-tumour” immune cells is important because they could be targets for therapies that block their harmful activity, said Minsoo Kim, PhD, corresponding author of the study and a research leader at the Wilmot Cancer Institute.

Kim led a team of scientists investigating the dynamic interactions that occur between cells in the tumor environment, and the underlying factors that cause the harmful transformation of immune cells from good to bad.

They found that PAF (platelet-activating factor) is the key molecule that controls the destiny of the immune cells. PAF not only recruits cancer-promoting cells, but it also suppresses the immune system’s ability to fight back. In addition, they found that multiple cancers rely on the same PAF signals.

“This is what could be most significant,” said Kim. “Because if we find a treatment that could interfere with PAF, it could potentially apply to many types of cancer.”

Much of the team’s work focused on pancreatic cancer cells. It is one of the most deadly cancers, with a five-year survival rate of about 12%, and is notoriously hard to treat because pancreatic tumours are surrounded by a toxic stew of proteins and other tissues that protect the cancer from the immune system’s natural role to attack invaders. They also studied breast, ovarian, colorectal, and lung cancer cells, using advanced 3D imaging technology to watch the behaviour of immune cells as they swarmed to the cancerous region.

Source: University of Rochester Medical Center

How, When and Where: Sex Matters in Melanoma Development

Photo by Rfstudio on Pexels

Melanoma rates differ consistently between men and women in terms of the ages at which melanomas occur and the locations on the body where they occur. Over time, melanoma rates have increased in both men and women, but the trends differ by body site. A new study in the Journal of Investigative Dermatology, published by Elsevier, presents the findings from a large-scale, long-term melanoma data analysis investigating incidence trends by age, sex, and anatomic site.

Lead investigator David C. Whiteman, MBBS, PhD, Cancer Control Group, QIMR Berghofer Medical Research Institute, and Faculty of Medicine, The University of Queensland, Brisbane, Australia, explains, “There has been a general observation in numerous populations that melanomas appear to arise at different rates in men and women. We decided to investigate this observation rigorously and assess whether these differences have been constant through time or across generations by using large-scale data from population registries to investigate long-term melanoma trends in men and women.”

The research team analysed more than 40 years of melanoma data from Queensland, Australia, the USA, and Scotland. These three populations were chosen because historically they have had high (Queensland), moderate (USA), and low (Scotland) rates of melanoma. Over time, the rates of melanoma increased in all three populations, especially among women. In women in all populations, melanomas arise most commonly on the limbs, whereas in men, melanomas arise most commonly on the trunk and head and neck. In both sexes, there has been a steady increase in melanomas on the head and neck with increasing age.

Researchers found that in virtually all investigated populations, women experience higher rates of melanoma than men in early life (up to age ~45 years), but men develop melanomas at higher rates than women later in life (from ages ≥ 65 years). Furthermore, these sex-specific trends reflect complex patterns of incidence across body sites that vary consistently with age. Thus, in early life, women experience higher rates of lower limb melanomas than men, which persists into older ages. Also, on the upper limbs, women experience substantially higher rates than men from young ages until middle age (45–64 years), after which men experience higher rates. In contrast, on the head and neck and the trunk, melanomas occur at higher incidence in men than in women early in life. On all body sites, the rate at which melanoma incidence rises with age is much more rapid for men than for women.

The study confirms that men and women experience melanoma in different ways. While this is most likely driven by different patterns of sun exposure between men and women, there appear to be inherent differences in the ways in which melanomas develop at different body sites in women compared with men. Understanding the underlying biological differences could provide important clues about the etiology of this enigmatic cancer.

Source: Elsevier

Novel Glass-based Bone Cancer Therapy has a 99% Success Rate

Photo by National Cancer Institute on Unsplash

Bioactive glasses, a filling material which can bond to tissue and improve the strength of bones and teeth, has been combined with gallium to create a potential treatment for bone cancer. Tests in labs have found that bioactive glasses doped with the metal have a 99% success rate of eliminating cancerous cells and can even regenerate diseased bones.

The research was conducted by a team of Aston University scientists led by Professor Richard Martin at the College of Engineering and Physical Sciences.

In laboratory tests 99% of osteosarcoma (bone cancer) cells were killed off without destroying non-cancerous normal human bone cells. The researchers also incubated the bioactive glasses in a simulated body fluid and after seven days they detected the early stages of bone formation. 

Gallium is highly toxic, and the researchers found that the ‘greedy’ cancer cells soak it up and self-kill, which prevented the healthy cells from being affected. Their research appears in the journal Biomedical Materials.

Osteosarcoma is the mostly commonly occurring primary bone cancer and despite the use of chemotherapy and surgery to remove tumours survival rates have not improved much since the 1970s. Survival rates are dramatically reduced for patients who have a recurrence and primary bone cancer patients are more susceptible to bone fractures. 

Despite extensive research on different types of bioactive glass or ceramics for bone tissue engineering, there is limited research on targeted and controlled release of anti-cancer agents to treat bone cancers.

Professor Martin said: “There is an urgent need for improved treatment options and our experiments show significant potential for use in bone cancer applications as part of a multimodal treatment.

“We believe that our findings could lead to a treatment that is more effective and localised, reducing side effects, and can even regenerate diseased bones.

“When we observed the glasses, we could see the formation of a layer of amorphous calcium phosphate/ hydroxy apatite layer on the surface of the bioactive glass particulates, which indicates bone growth.”
The glasses were created in the Aston University labs by rapidly cooling very high temperature molten liquids (1450°C) to form glass. The glasses were then ground and sieved into tiny particles which can then be used for treatment.  

In previous research the team achieved a 50% success rate but although impressive, this was not enough to be a potential treatment. The team are now hoping to attract more research funding to conduct trials using gallium.

Dr Lucas Souza, research laboratory manager for the Dubrowsky Regenerative Medicine Laboratory at the Royal Orthopaedic Hospital, Birmingham worked on the research with Professor Martin. He added: “The safety and effectiveness of these biomaterials will need to be tested further, but the initial results are really promising.

“Treatments for a bone cancer diagnosis remain very limited and there’s still much we don’t understand. Research like this is vital to support in the development of new drugs and new methodologies for treatment options.”

Source: Aston University

Common Skin Fungus Malassezia may Invade Tissue, Causing Breast Cancer

Photo by National Cancer Institute on Unsplash

A common skin fungus, Malassezia globosa may invade deep tissues through the skin or by other means, then cause tumour growth, according to a new study. The study results appear in mBio, an open access journal of the American Society for Microbiology.

“It is important to take care of skin not only for beauty, but also for health,” said corresponding study author Qi-Ming Wang, PhD, a professor in the School of Life Sciences, Institute of Life Sciences and Green Development, Hebei University, Hebei, China. “As a factor promoting tumour growth, intertumoural microorganisms need to be paid more attention.” 

Recently, an increasing number of studies have shown a relationship between fungus and cancer. In the new study, Wang and colleagues subjected mouse breast cancer cells to tumour transplantation and then injected the M. globosa into the mammary gland fat pad. At the end of the experiment, they collected the tumour tissue to measure the tumour size and observe the content of intertumoral M. globosa. The researchers discovered that M. globosa colonises in breast fat pads leading to tumour growth. As a lipophilic yeast, the breast fat pad may provide an external source of lipids for the development of M. globosa, said the researchers. They also found that the pro-inflammatory cytokine interleukin (IL)-17a/macrophage axis plays a key role in mechanisms involved in M. globosa-induced breast cancer acceleration from the tumour immune microenvironment perspective.

“Although still controversial, the relationship between microbes and cancer is gaining attention. The imbalance of the microflora in the tumour may lead to disorder in the tumour microenvironment,” Wang said. “For example, Helicobacter pylori emerged as a potential cause of gastric cancer. In addition, Fusobacterium nucleatum has been identified as a potential colorectal cancer biomarker in stool and is predominantly found in the tumour microenvironment. Bacteria or fungi may play a direct (eg, toxins) or indirect (eg, inhibition of anti-tumoural immune responses) role in the tumorigenesis pathways of many of these risk factors. The imbalance of microbial homeostasis in tumours has a certain significance for cancer diagnosis, treatment and prognosis.” 

According to Wang, although the researchers found that M. globosa can promote the growth of tumours, the related transmission route is still unclear. 

Source: American Society for Microbiology

Scars of Destroyed Brain Tumours are Fertile Grounds for Recurrence

Types of tumour cells. Credit: Scientific Animations CC4.0

A Ludwig Cancer Research study has discovered that recurrent tumours of the aggressive brain cancer glioblastoma multiforme (GBM) grow out of the fibrous scars of malignant predecessors destroyed by interventions such as radiotherapy, surgery and immunotherapy.

Led by Ludwig Lausanne’s Johanna Joyce, Spencer Watson and alumnus Anoek Zomer and published in the current issue of Cancer Cell, the study describes how these scars enable the regrowth of tumours and identifies drug targets to sabotage their malignant support. It also demonstrates the efficacy of such combination therapies in preclinical trials using mouse models of GBM.

“We’ve identified fibrotic scarring as a key source of GBM resurgence following therapy, showing how it creates a protective niche for the regrowth of the tumor,” said Joyce. “Our findings suggest that blocking the process of scarring in the brain by adding anti-fibrosis agents to current treatment strategies could help prevent glioblastoma from recurring and improve the outcomes of therapy.”

There is a great need for such interventions. GBM is the most common and aggressive form of brain cancer in adults. Despite considerable effort to develop effective therapies for the cancer, the average life expectancy of patients remains around 14 months following diagnosis.

The origins of the current study date back to 2016, when the Joyce lab reported in the journal Science its examination in mouse models of strategies to overcome resistance to a promising immunotherapy for the treatment of GBM. That experimental therapy, which inhibits signalling by the colony stimulating factor-1 receptor (CSF-1R) and currently in clinical trials, targets immune cells known as macrophages and their brain-resident versions, microglia, both of which are manipulated by GBM cells to support tumour growth and survival.

The Joyce lab has demonstrated that CSF-1R inhibition reprograms these immune cells into an anti-tumour state and so induces significant tumour regression. Yet, as the Science study showed, about half the mice show relapse following an initial response to the therapy. “What was most remarkable about that observation was that every single time a brain tumour recurred following immunotherapy, it regrew right next to a scar that had formed at the original site of a tumour,” said Joyce.

In the current study, Joyce, Watson, Zomer and their colleagues examined tumour samples obtained from patients undergoing GBM therapy and showed that fibrotic scarring occurs following therapy in humans as well – and that it is similarly associated with tumour recurrence. They also showed that the fibrotic scarring occurs in response to not only immunotherapy but also following the surgical and radiological removal of tumours.

To explore how fibrosis contributes to relapse, the researchers applied an integrated suite of advanced technologies to analyze the cellular and molecular geography of the scars and the microenvironment of resurgent tumors.

These technologies include the analysis of global gene expression in individual cells, the comprehensive analysis of proteins in the tissues as well a workflow and AI-powered suite of analytical methods for the spatial analysis of tissues named hyperplexed immunofluorescence imaging (HIFI). Recently developed by Watson and colleagues in the Joyce lab, HIFI permits the simultaneous visualisation of multiple molecular markers in and around cells across broad cross-sections of tissues, enabling the generation of granular maps of the tumour microenvironment.

“Applied together, these advanced methods allowed us to see exactly how fibrotic scars form,” said Watson. “They revealed that the fibrosis serves as a kind of protective cocoon for residual cancer cells and pushes them into a dormant state in which they are largely resistant to therapy. We found that it also shields them from surveillance and elimination by the immune system.”

Integrated analyses of the tissue microenvironment following therapy revealed that the descendants of cells associated with tumor-feeding blood vessels become functionally altered to resemble fibroblasts—fiber-producing cells commonly involved in wound-healing. These perivascular-derived fibroblast-like (PDFL) cells fan out across the region previously occupied by the regressing tumor, where they mediate the generation of fibrotic scars. These cells, the researchers found, are especially activated by neuroinflammation and immune factors known as cytokines, most notably one called transforming growth factor-β (TGF-β).

“To see if targeting fibrotic scarring could improve therapeutic outcomes for GBM, we devised a treatment regimen using existing drugs to block TGF-β signaling and suppress neuroinflammation in combination with CSF-1R inhibition and evaluated it in preclinical trials using mouse models of GBM,” said Joyce. “We also timed these additional treatments to coincide with the period of maximal PDFL activation identified by our studies. Our results show that the drug combination inhibited fibrotic scarring, diminished the numbers of surviving tumor cells and extended the survival of treated mice compared to controls.”

The researchers suggest that approaches to limit fibrotic scarring could significantly improve outcomes for GBM patients receiving surgical, radiation or macrophage-targeting therapies. Additional research, they note, will likely yield even better drug targets for such combination therapies.

Source: Ludwig Institute for Cancer Research