Tag: GLP-1 agonist

Sun Pharma Launches Generic Semaglutide in South Africa

Johannesburg, 21 July 2026 — Sun Pharmaceutical Industries Limited (Reuters: SUN.BO, Bloomberg: SUNP IN, NSE: SUNPHARMA, BSE: 524715) (together with its subsidiaries and/or associated companies, “Sun Pharma”) today announced the launch of generic semaglutide, a once‑weekly GLP‑1 receptor agonist, in South Africa for the treatment of adults with inadequately controlled type 2 diabetes mellitus as an adjunct to diet and exercise.

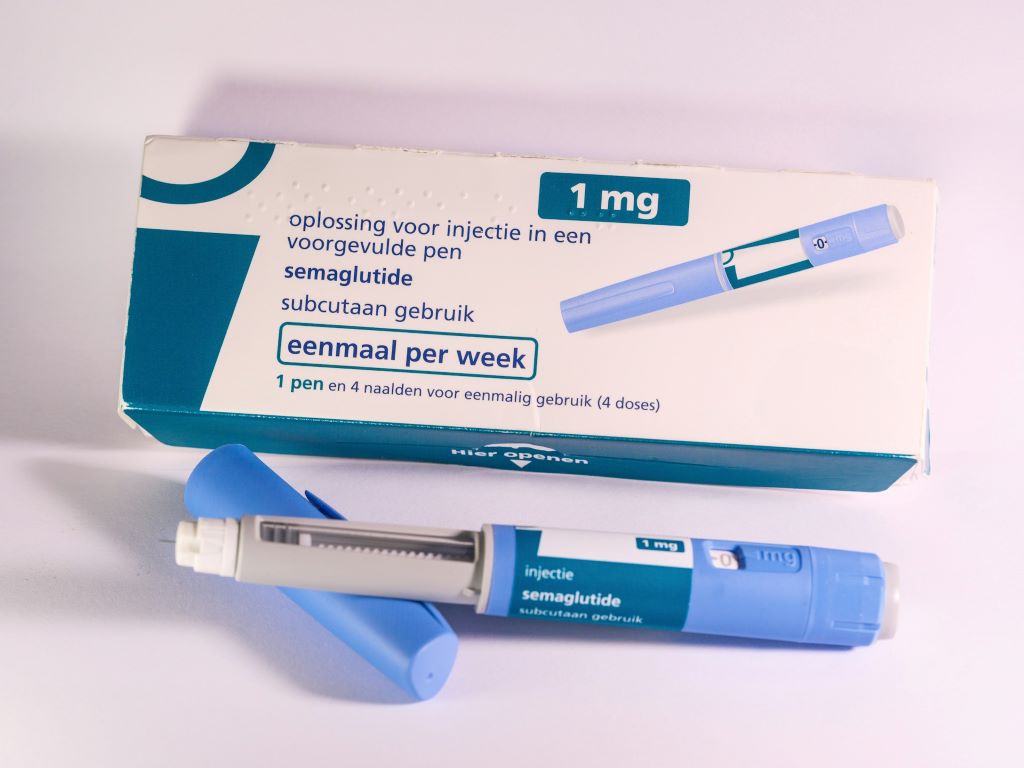
The product is supplied in a pre‑filled, multi‑dose injectable pen in two strengths (2 mg/1.5 mL and 4 mg/3 mL) that allow flexible, once‑weekly dosing. The device features a smooth dialer for accurate dose selection and a concealed needle to improve handling safety and reduce injection anxiety. The pens are manufactured in Europe and developed with established pharmaceutical device suppliers.

“Type 2 diabetes remains a major public‑health challenge in South Africa,” said Malcolm Brown, Chief Executive Officer, Sun Pharma South Africa. “The availability of generic semaglutide strengthens the range of evidence‑based treatment options available to clinicians and patients. Our objective is to support better clinical outcomes by improving access to proven therapies that can be integrated into comprehensive diabetes care.”

Clinical context and public‑health relevance

  • Type 2 Diabetes remains one of South Africa’s most significant public health challenges. As per the International Diabetes Federation country report, it is estimated that 3.9 million patients aged 20-79 would be living with diabetes in South Africa by 2050.
  • South Africa faces a growing burden of type 2 diabetes, driven in part by rapid urbanization and changing lifestyles. This rising prevalence places significant pressure on patients and healthcare services. Improving access to effective therapies is therefore an important component of addressing this national health challenge.
  • With the launch of generic semaglutide in South Africa, Sun Pharma aims to provide clinicians and patients with an additional licensed option for comprehensive diabetes management, supporting better long‑term outcomes when used alongside diet and exercise.

Regulatory and medical review

Healthcare professionals are advised to consult full prescribing information and local treatment guidelines when considering semaglutide for individual patients. The company’s local medical team is available to assist clinicians with scientific inquiries and product information.

About Sun Pharmaceutical Industries Limited. (CIN – L24230GJ1993PLC019050)

Sun Pharma is a leading global pharmaceutical company with a presence in Innovative Medicines, Generics and Consumer Healthcare products. It is the largest pharmaceutical company in India and is a leading generic company in the US as well as Global Emerging Markets. Sun’s high growth Global Innovative Medicines portfolio spans innovative products in dermatology, ophthalmology, and onco-dermatology and accounts for about 22% of company sales. The company’s vertically integrated operations deliver high-quality medicines, trusted by physicians and consumers in over 100 countries. Its manufacturing facilities are spread across five continents. Sun Pharma is proud of its multi-cultural workforce drawn from over 50 nations. “For further information, please visit www.sunpharma.com and follow us on LinkedIn & X (Formerly Twitter).”

Most Obesity Drugs Do Not Improve Quality of Life or Heart Health

Treatment decisions should be individualised, balancing expected benefits, harms, treatment burden, costs, availability, and patient preferences, say researchers

By HualinXMN – Own work, CC BY-SA 4.0

Despite substantial weight loss, most obesity drugs such as Wegovy and Mounjaro do not meaningfully improve quality of life and few show cardiovascular benefits at one year, finds an analysis of the latest evidence published by The BMJ today.

More weight loss is also generally accompanied by greater harms including stomach and bowel symptoms, fatigue, and loss of lean (muscle) mass – and improvements are not sustained after stopping treatment.

Several drugs for adults with overweight or obesity produce substantial weight loss, but most have not been compared directly in head-to-head trials, leaving uncertainty about the broader balance of benefits and harms.

To address this, researchers searched scientific databases for randomised controlled trials comparing one or more drugs with lifestyle changes, placebo, or another drug.

They found 262 eligible trials involving 99,791 participants (average age 49; 63% female; average BMI 35) that evaluated 19 currently available and emerging obesity drugs with follow-up from 12 to 172 weeks.

Benefits included changes in body weight, fat mass, and quality of life, while potential harms included changes in lean mass, gastrointestinal adverse events, gallbladder related disorders and fatigue.

The trials were of varying quality, but the researchers were able to assess the certainty of evidence using the recognised GRADE system.

Compared with lifestyle changes alone, the largest weight loss after one year was with tirzepatide (14.9%) and CagriSema (14.8%), followed by oral semaglutide (10.9%), orforglipron (9.9%), subcutaneous semaglutide (9.8%), and phentermine-topiramate (8.1%).

Emerging drugs – including retatrutide, ecnoglutide, and mazdutide – showed large effects on weight loss but are supported by low or very low certainty evidence.

Greater weight loss was consistently accompanied by higher rates of side effects and treatment discontinuation, which the authors say indicates a clear benefit-harm trade-off.

Tirzepatide reduced fat mass the most (by 25.7%) but also lean mass the most (8.3%). Subcutaneous semaglutide was the only drug associated with a reduced risk of death from any cause (19%), heart attack (28%), and heart failure (57%). Tirzepatide also reduced heart failure risk by 51%.

No drug convincingly reduced kidney failure or showed clinically important improvements in quality of life.

The authors acknowledge that most trials had relatively short follow-up, limiting conclusions about long term safety, quality of life, and effects on heart and kidney health. In addition, evidence for several newer drugs was sparse and of low certainty, and trial populations may not fully represent real world patients.

However, they say this review provides a comprehensive and up-to-date comparison of currently available and emerging obesity drugs across a broad set of outcomes important to patients, clinicians, and policymakers.

They conclude: “Treatment decisions for obesity should be individualised, balancing expected benefits, harms, treatment burden, costs, availability, and patient preferences.”

This study represents an important step in providing comparative information to inform patient-clinician discussions about obesity drugs in this rapidly evolving landscape of treatment options, say researchers in a linked editorial.

And they suggest future studies that incorporate individual characteristics, as well as long term outcomes, such as mortality, should provide additional data to inform individualised decision making.

Source: The BMJ Group

Popular GLP-1 Drug May Slow Down Biological Aging

By calming inflammation and reducing excess fat, semaglutide may postpone several molecular signs of aging, pointing to the potential of GLP‑1 receptor agonists to help prevent age‑related diseases.

Photo by Haberdoedas on Unsplash

Semaglutide slowed biological aging across multiple epigenetic clocks in a randomised, double-blind, placebo-controlled clinical trial. The strongest signals were seen in epigenetic measures linked to inflammation, brain, heart, blood, kidney, liver and metabolic health, suggesting that the drug may influence aging-related biology across multiple body systems. The findings offer early clinical evidence that GLP-1 receptor agonists may influence aging biology.

Glucagon-like peptide-1 (GLP-1) receptor agonist medications have gained widespread attention for effectively treating obesity, lowering blood sugar and decreasing the risk of cardiovascular disease. Some researchers have proposed that these drugs may also influence the biology of aging, but direct evidence in humans has remained limited. Now, a new study provides the first randomised, placebo-controlled clinical evidence that semaglutide, a widely used GLP-1 drug, slows down the accumulation of biological aging markers in the DNA of adults with HIV. The study is published in Nature Communications.

Researchers at the University of California San Diego and several partner institutions analysed data from a previously published clinical trial of 108 adults with HIV‑associated lipohypertrophy, a condition in which excess fat builds up around the abdomen. About half of the participants received weekly injections of semaglutide, with the rest receiving placebo injections.

The team used a set of biological “epigenetic clocks” to track cellular aging over the 32-week treatment period. These clocks detect DNA methylation, chemical marks on DNA that help regulate how genes are turned on or off without changing the genetic sequence itself. By measuring changes in these marks, the team could assess whether the treatment was associated with a slower or faster biological aging pattern.

People with HIV often experience accelerated aging, even if it is well-controlled with antiretroviral therapy, according to first author Michael Corley, PhD, associate professor at UC San Diego School of Medicine and the Stein Institute for Research on Aging. However, the study found compared to the placebo group:

  • Participants treated with semaglutide exhibited a broad pattern of slower biological aging across epigenetic clocks linked to inflammation and blood, brain, heart, kidney, liver and metabolic health.
  • The drug slowed the pace of biological aging by 9 %, as measured by the DunedinPACE epigenetic clock.
  • The drug significantly slowed biological processes associated with the risk of all‑cause mortality and age-related disease, as measured by the PCGrimAge epigenetic clock.

Research suggests there are several mechanisms by which semaglutide may influence biological aging. By reducing inflammation and metabolic stress, GLP-1 drugs decreased chronic immune activation, a primary driver of accelerated aging in people with HIV. They also reduce visceral and ectopic fat that accumulates around the abdomen and organs, which may help curb the inflammatory and metabolic signals that promote aging.

“Emerging data also suggest that GLP-1 drugs may reprogram certain cells in different organs, which could help explain why we see effects across multiple aging clocks,” said Corley.

While the study focused on people with HIV‑associated lipohypertrophy, Corley says it may also offer lessons for the wider population.

“Many of the biological processes we study in HIV are also central to aging in the general population,” he said. “Because these processes can emerge earlier or be more pronounced in people with HIV, this community can help us identify interventions that may improve healthspan more broadly.”

In a related pilot study published in npj Aging, Corley and another team of researchers found that taking semaglutide for 24 weeks:

  • Reduced the rate of biological aging for 42% of participants with HIV and metabolic dysfunction-associated steatotic liver disease (MASLD) as measured by the DunedinPACE epigenetic clock. Those participants also had a greater reduction in liver fat compared with participants whose pace of aging sped up.
  • Slowed aging associated with the risk of all‑cause mortality in 34% of participants as measured by the PCGrimAge epigenetic clock.
  • Increased the length of telomeres in nearly 49 % of participants as measured by the PCDNAmTL epigenetic clock. Those participants also tended to walk faster after treatment, suggesting better physical function.

Together, these studies add to growing evidence that GLP-1 drugs may influence pathways involved in biological aging.

“We are not saying that semaglutide reverses aging or makes people younger. What we are seeing is a signal that it may slow some of the biological processes associated with aging.”

— Michael Corley, PhD

“We are not saying that semaglutide reverses aging or makes people younger,” said Corley. “What we are seeing is a signal that it may slow some of the biological processes associated with aging. With newer GLP-1–based therapies now emerging, the field has an opportunity to test whether different drugs in this class have distinct effects on aging biology and to identify which patients may benefit most.”

Larger clinical trials are needed to confirm the findings, determine how long treatment effects last, and establish optimal dosing and treatment duration for both people with HIV and the broader population. Future studies will also be needed to test whether the effects of GLP-1 effects on aging biology are enhanced when combined with lifestyle interventions such as diet, exercise and sleep optimization.

The Stein Institute for Research on Aging plans to translate these results into individualized “aging dashboards” to track biological aging with epigenetic clocks, enabling clinicians to design personalised therapies that target the underlying mechanisms of aging and help prevent age‑related diseases.

By Susanne Clara Bard

Source: University of California San Diego

Can the Use of GLP-1RAs Reduce Behaviours Linked to Violent Crime?

Photo by Maxim Hopman on Unsplash

Glucagon-like peptide-1 receptor agonists (GLP-1 RAs) are widely prescribed for diabetes and obesity, but studies have found evidence that the medications may also influence behaviour, such as supporting impulse control and reducing substance use and alcohol consumption by potentially interacting with the brain’s reward and stress systems. New research in Criminology adds to this growing evidence.

When investigators analysed data from a 2025 nationally representative US survey involving 821 adults who had ever used GLP-1 medications, they found that while impulsivity and alcohol use were strongly associated with committing violent crime, these associations were significantly weaker among current GLP-1 RA users compared with former users. So even when a GLP-1 RA user drinks or acts impulsively, the situation is less likely to escalate into engaging in violent criminality. More thorough analyses showed that this finding was especially consistent related to impulsivity, but less so with alcohol use.

The findings suggest that GLP-1 RAs may lessen the extent to which certain established risk factors translate into violent behavior.

“As GLP-1 medications become increasingly widespread, understanding their broader behavioral effects becomes an important public health and criminological question that requires careful study,” said corresponding author Daniel C. Semenza, PhD, of Rutgers University.

Source: Wiley

Trade Marks, Trust and the GLP-1 Surge

The surge in demand for GLP-1 and GIP medicines—particularly those containing semaglutide and tirzepatide—has created significant commercial opportunity. It has also exposed a growing problem: the manufacture and sale of unregistered and potentially unlawful alternatives.

Recent enforcement action by the South African Health Products Regulatory Authority (SAHPRA) highlights the scale of the issue, particularly in relation to products marketed for weight loss (see SAHPRA and the SAPC Crack Down on Unlawful Manufacturing of Unregistered GLP-1/ GIP Medicines). While this is often viewed as a regulatory concern, it raises equally important questions for trade mark law.

Trade marks are traditionally seen as tools for distinguishing one trader’s goods from another’s. In the pharmaceutical sector, however, they do far more. They signal quality, safety, efficacy and regulatory legitimacy.

When those signals are misused, the consequences extend beyond commercial harm—they can directly affect public health.

More Than Molecules: Reputation as the Real Asset

The success of products such as OZEMPIC®, Wegovy® and MOUNJARO® is not driven by their active ingredients alone.

Through years of clinical research, regulatory scrutiny and market presence, these brands have accumulated significant reputational capital. Consumers are not simply looking for semaglutide or tirzepatide—they are looking for certainty.

Consumers want products backed by known standards of safety, tested efficacy and regulatory oversight.

In this context, the goodwill attached to a pharmaceutical trade mark reflects far more than brand recognition. It represents confidence in the entire lifecycle of the product—from development and approval to manufacture and distribution.

Reputation Laundering: Trading on Trust Without Earning It

In the current GLP-1 market, misuse of reputation does not always take the form of direct counterfeiting or even traditional trade mark infringement.

More often, products are marketed as alternatives, equivalents or substitutes for well-known medicines. Advertising often references established brands to attract consumer attention and to confer an aura of legitimacy on products that may not have undergone the same level of regulatory scrutiny.

This is where a more subtle form of exploitation emerges.

Even without reproducing a trade mark, these practices appropriate the trust associated with it. The result is what can aptly be described as reputation laundering, being the transfer of credibility from a trusted product to one that has not independently earned it.

From a trade mark perspective, the damage goes far beyond lost sales. It weakens the link between the brand and the qualities consumers expect from it.

The Consequences for Consumer Trust

The risks become most apparent when products fail to meet expectations- or worse, raise safety concerns.

If a consumer experiences harm after using a product marketed with reference to a well-known brand, the reputational fallout rarely remains confined to the seller. It can spill over to the genuine product.

This is what makes pharmaceutical trade marks unique. The goodwill they embody is inseparable from consumer trust in the safety and reliability of medicines.

Once that trust is compromised, the consequences extend beyond individual brand owners. They can influence patient behaviour, clinical decision and confidence in an entire class of treatments.

The Growing Union Between Regulatory Enforcement and Trade Mark Protection

Historically, regulatory compliance and trade mark enforcement have been treated as distinct legal disciplines. Increasingly, however, the two are becoming interconnected.

Regulatory authorities seek to protect consumers from unsafe or unapproved products. Trade mark owners seek to protect the reputation and goodwill associated with their brands. In many cases, these objectives are aligned.

SAHPRA’s recent focus on unregistered GLP-1 products illustrates this convergence. Both regulators and trade mark proprietors share an interest in ensuring that consumers are not misled regarding the nature, origin or reliability of pharmaceutical products.

As pharmaceutical brands continue to acquire substantial reputational capital, the distinction between consumer protection and brand protection becomes increasingly difficult to draw.

It is clear that pharmaceutical trade marks are no longer simply badges of origin. They have become proxies for trust. As the current GLP-1 market demonstrates, protecting that trust is not only a commercial imperative- it is increasingly a matter of public health.

New Study Links GLP-1 Agonists to Reduction of Asthma Exacerbations and Inhaler Use

Photo by Cnordic Nordic

New research presented at this year’s European Congress on Obesity in Istanbul, Turkey (12-15 May) shows the use of the new GLP-1 class of obesity drugs in people with asthma is associated with a 26% fall in the number of asthma exacerbations and a 14% drop in use of asthma inhaler reliever use. The study is by Simon Høj and Dr Kjell Erik Julius Håkansson Copenhagen University Hospital, Copenhagen Denmark and colleagues.

Glucagon-like peptide-1 receptor agonists (GLP-1 RAs) are now widely used to treat overweight, obesity and type 2 diabetes (T2DM), with growing evidence of benefits that extend beyond blood sugar control.

In asthma, where overweight, obesity and metabolic dysfunction can lead to increased severity of symptoms and adverse events such as acute exacerbations, the authors suggest that GLP-1 RAs may improve asthma outcomes through weight loss, modulation of airway inflammation, and improvements in metabolic functions. Reductions in occurrence of asthma exacerbations are likely to reduce systemic corticosteroid exposure (a common treatment for acute asthma exacerbations orally or intravenously) and thus may reduce the risk of corticosteroid exposure-associated adverse events such as osteoporosis or new-onset T2DM. As such, as the clinical use of GLP-1 RAs expands, reliable estimates of their impact on asthma control are needed for individuals living with both asthma and overweight, obesity or T2DM.

The researchers conducted a nationwide self-controlled cohort study using linked Danish health registers. Adult individuals with a prior asthma diagnosis or ≥2 asthma inhaler prescriptions redeemed within 12 months) were included on the date of their first GLP-1 RA dispensing (index date). Eligible individuals had continuous registration data for at least 12 months before and after the index date.

Individuals with COPD or patients with severe asthma treated with new and relatively expensive biologic drugs within 12 months before or after the index date were excluded. Overweight or obesity was defined using ICD-10 codes for those conditions. Those who had no evidence of T2DM – with no diagnosis recorded or no evidence of other first line diabetes drugs prescribed – were also placed in the with obesity/overweight group. Those with a T2DM diagnosis or prescriptions recorded for first line diabetes drugs such as metformin were placed in the T2DM group.

The primary outcome was exacerbations, defined as an inpatient asthma hospital contact(s) and/or systemic oral or intravenous corticosteroid course(s). Secondary outcomes were the use of rescue medication (inhaled short-acting β2-agonists), inhaled corticosteroid exposure, and chest infection events defined as redemption of antibiotics commonly used for lower airway infections

The cohort comprised 27,523 individuals (mean age 54 years, 66% female) with asthma and comorbid overweight or obesity (49%) or T2DM (61%) and 26% recorded as having both conditions. Around 50% of the GLP-1 prescriptions were liraglutide, 48% semaglutide, and 2% others (exenatide, dulaglutide, lixisenatide).

Compared with the year before GLP-1 RA treatment, GLP-1 RA treatment was associated with a 26% lower exacerbation rate overall; and 28% lower in men compared with 23% lower in women. When stratified according to GLP1 RA treatment indication, the analysis showed individuals with asthma and comorbid overweight or obesity and individuals with asthma and comorbid T2DM had similar effect estimates – a 22% reduction in those with overweight or obesity and a 26% reduction in those with T2D.

Reliever medication use fell by 14% overall, suggesting fewer symptoms despite daily inhaled corticosteroid exposure also decreasing by 23% (inhaled corticosteroids are used to prevent exacerbations and treat symptoms in asthma). Furthermore, pneumonia events were reduced by 10%. People also living with allergic rhinitis saw similar decreases (23%) in exacerbations to those living without allergic rhinitis (28%). The authors are also working on updated analyses to show differences between men and women for these specific outcomes.

The authors conclude: “In this nationwide cohort of over 27,000 individuals with asthma and also overweight, obesity or type 2 diabetes, use of GLP-1 drugs  was associated with significant reductions in exacerbation burden as well as reliever use, exposure to inhaled corticosteroids and pneumonia events, irrespective of whether the drugs were being used to treat obesity or type 2 diabetes.”

The authors explain that their study did not have access to clinical records (just if people had used GLP-1 and hospital admissions), so data on BMI and weight loss for participants were not available.

But Dr Håkansson says: “There’s a high chance that the weight loss is a major contributor to these results. A common symptom in both asthma and obesity is shortness of breath, and the presence of excess fatty tissue creates a pro-inflammatory state in the body in general. There’s also evidence from other studies suggesting that the inflammation caused by excess adipose tissue is distinct from the ‘classic’ asthma inflammation which often is driven by allergies or cells called eosinophils.”

And he adds: “As the use of GLP-1 therapies increase, researchers are finding an increasing number of effects outside of weight loss.”

Source: EurekAlert!

South Africa’s Weight-loss Revolution is Testing Medical Discipline

Photo by I Yunmai on Unsplash

One in every two South African adults is considered overweight or obese. It is not surprising, then, that potentially lifesaving prescription-based metabolic medicines are surging in popularity. The challenge: demand is rising faster than the clinical structure needed to support it, leaving many patients unsure what responsible, medically supervised care should look like.

It is a concern Dr Gerhard Vosloo, a prominent sports, exercise, and lifestyle physician, says he is encountering more frequently in clinical practice. “Expectations are becoming unreasonably high, while few understanding the level of medical oversight required to manage these therapies responsibly. It’s just not as simple as prescribing an aggressive regime and standing back.”

To address issues in today’s weight management sector, Dr Vosloo established Dr GL Vosloo Medical Practice, managed by BioWell, as a formal online medical practice built around sound clinical judgment, structured care, and meaningful patient oversight. He says, “We’re building a model – one that could serve as a stable structure for the wider industry, where sound medical judgment is consistently prioritised over the public’s growing appetite for weight loss drugs.”

The danger of normalising prescription therapy

Dr Vosloo cautions that the rapid rise of these medicines in the mainstream is oversimplifying a highly complex subject and making pharmaceutical use seem routine, when it should remain a final option after disciplined nutrition- and exercise-led approaches have been fully explored.

“Misinformation spreads like wildfire online. People are starting to view prescribed medicines as a routine diet option, when they should be a last resort. Pharmaceuticals are powerful tools for people who struggle to lose weight, but they should be introduced only when medically appropriate, and only after nutrition, exercise, and appropriate supplementation have been fully explored.”

He maintains that prescribed medicines should form part of a structured metabolic management programme that, when used correctly, will reduce cardiometabolic risk, improve insulin sensitivity, regulate appetite, and support meaningful body composition change. The goal is to improve metabolic health under disciplined supervision, and when treatment is not medically necessary, doctors must refuse to prescribe.

“Clinical eligibility must be determined by medical rationale,” he says. “A patient’s preference for medication, emotional pressure to start treatment, or the ability to pay cannot override clinical judgement. Where medical need is absent, a BioWell doctor will decline to prescribe and direct the patient to a non-pharmaceutical, doctor-supported metabolic management pathway.”

Dosing with discipline

Beyond unnecessary prescribing practices, Dr Vosloo stresses that the industry is undermined by over lenient dosing habits. As practiced on the BioWell platform, dosing decisions should instead follow a conservative model guided by clinical responses and tolerability rather than speed of weight loss. The objective is to protect overall health while supporting steady progress that the body can sustain.

“An unfortunate consequence of aggressive dosing is the loss of muscle mass. It’s easier for the body to draw from muscle than it is to mobilise fat, particularly when calories and protein are low – a hallmark of aggressive dosing protocols. The nutritional and training commitment needed to offset muscle loss under more radical regimens are difficult to manage for most people. It’s far safer and more sustainable to take low doses over a longer period.”

“BioWell doctors are more measured in our approach. Conservative dosing and escalation protocols help keep muscle loss to a minimum, while structured nutrition and exercise support plans strengthen the muscular system. This also reduces the risk of nutritional deficiency and limits the physiological stress that often accompanies poorly managed treatments.”

The end goal, Dr Vosloo explains, is to safely and gradually bring South Africa’s obesity crisis under control without creating any additional harm. “Prescription-based metabolic medicine is an undeniably powerful tool in the fight against obesity – one we cannot afford to lose. It’s a lifeline for people battling weight-related illness, but it’s also become a dangerous crutch for those willing to gamble with their health just to lose a few kilograms quickly. If we want to change the health trajectory of millions, we need to rein in aggressive dosing practices and establish a common-sense structure across the sector.”

GLP-1 Medications May Also Help with Symptoms of Anxiety and Depression

Photo by Sweet Life on Unsplash

GLP-1 medications used to treat diabetes and obesity were associated with a reduced need for hospital care and sickness absence due to psychiatric reasons, a new study shows. The large register-based study was carried out in collaboration between the University of Eastern Finland, Karolinska Institutet in Stockholm and Griffith University in Australia.

Diabetes and obesity are associated with an increased risk of mental health symptoms, and similarly, individuals with mental disorders have an elevated risk of metabolic diseases such as obesity and diabetes. Researchers have long been interested in the connections between these conditions and in how pharmacological treatments may affect both metabolic and mental health disorders.

The present study, published in The Lancet Pyschiatry, included nearly 100 000 participants, over 20 000 of whom had used GLP-1 medications. Participants were followed through Swedish national registers between 2009 and 2022.

The risk of substance use was also reduced

The results showed that the use of GLP-1 medications – particularly semaglutide – was associated with a reduction in sickness absence and hospital care due to psychiatric reasons. During periods of semaglutide use, the reduction was 42% compared with periods when GLP-1 medications were not used. For depression, the risk was 44% lower, and for anxiety disorders, 38% lower. 

In addition, semaglutide use was associated with a lower risk of substance use disorders: hospital care and sickness absence related to substance use were 47% lower during periods of semaglutide use compared with periods without GLP-1 medication. The use of GLP-1 receptor agonists was also associated with a reduced risk of suicidal behaviour.

One of the study’s authors, Professor Mark Taylor from Griffith University, says such results were to be expected: “An earlier study examining Swedish registers found the use of GLP-1 medications to be associated with a reduced risk of alcohol use disorder. Alcohol-related problems often have downstream effects on mood and anxiety, so we expected the effect to be positive on these as well.”

However, the magnitude of the association surprised the researchers:
“Because this is a registry-based study, we cannot determine exactly why or how these medications affect mood symptoms, but the association was quite strong. It is possible that, in addition to factors such as reduced alcohol consumption, weight loss-related improvements in body image, or relief associated with better glycaemic control in diabetes, there may also be direct neurobiological mechanisms involved – for example, through changes in the functioning of the brain’s reward system,” says Research Director, Docent Markku Lähteenvuo from the University of Eastern Finland.

Other recent evidence on the effects of GLP-1 medications on anxiety and depressive disorders has been somewhat inconsistent, but it has been largely based on small studies.

Source: University of Finland

Could a New Type of Weight‑loss Pill Shake up the Market? Here’s What to Know About Orforglipron

Photo by Sweet Life on Unsplash

Martin Whyte, University of Surrey

A new type of daily pill has proven more effective for weight loss and blood sugar control than its currently available counterparts, according to a recent trial. The drug, known as orforglipron, could be a game-changer in the rapidly expanding oral weight-loss drug market.

The advent of the injectable weight-loss drug semaglutide (known better by its brand names Wegovy and Ozempic) marked a distinct shift in the weight-loss drugs market when it became available just a few years ago.

Semaglutide is a class of glucagon-like peptide-1 (GLP-1) medication. These drugs mimic the gut hormone GLP-1, which is released soon after eating. This hormone signals fullness to the brain, slowing digestion and stimulating the release of insulin. By replicating the action of this hormone, GLP-1 drugs have proven highly effective at managing type 2 diabetes and promoting weight loss.

Although semaglutide is widely used, a key issue with the drug is that it needs to be injected into the belly, thighs or back of the arm. This can make it difficult for patients with needle phobia or who don’t want to self-inject due to the inconvenience.

Another logistical issue with injectable GLP-1 drugs is that they require refrigeration throughout the supply chain. This can pose a challenge in low- and middle-income countries.

It’s for these reasons that researchers and developers have started investigating the efficacy of oral versions of semaglutide.

Based on current research, it appears that oral semaglutide is very effective. However, it must be taken on an empty stomach – and users must wait 30 minutes before eating or drinking.

Alongside being expensive to produce, it also has poor bioavailability compared with injectable semaglutide. This means only about 1% of the ingested drug is absorbed and able to exert its effects.

But a recent phase 3 clinical trial has shown that a new type of oral weight-loss pill may have overcome these issues – proving to be more effective than the current oral semaglutide products on the market.

Oral weight-loss pill

The recent 52-week phase 3 trial involved 1,698 adults with type 2 diabetes across six countries. It set out to compare current oral semaglutide products against orforglipron, which is also taken as a daily tablet.

The primary measure researchers were looking for was a reduction in HbA1c. This blood test reflecting average blood sugar levels over three months is the standard indicator of diabetes control. Diabetes is present if HbA1c is 6.5% or more.

From a baseline average HbA1c of 8.3%, it was found that after 52 weeks, orforglipron was able to reduce this value by an average of 1.71–1.91%. In comparison, oral semaglutide only reduced HbA1c by 1.47%.

Not only did orforglipron meet the trial’s goals of proving it was as effective to oral semaglutide, it proved it was superior for lowering blood sugar. The participants who took orforglipron also lost more weight – an average of 6.1kg-8.2kg, compared with 5.3kg in those taking semaglutide.

However, a key issue highlighted by the trial was one of tolerability.

GLP-1 drugs can cause gastrointestinal side-effects such as nausea, vomiting, diarrhoea and constipation. In this latest trial, around 59% of participants on orforglipron reported such symptoms, compared with 37–45% on semaglutide.

The reason for this difference may be the more prominent, daily peak drug concentrations with orforglipron. The consequence was that around 10% of orforglipron participants discontinued treatment due to adverse effects. Just 4-5% of those taking semaglutide discontinued treatment.

Future studies may want to look at how orforglipron compares with injectable semaglutide. Photo by Haberdoedas on Unsplash

No head-to-head trials have been done of injectable GLP-1 versus orforglipron. However, the weight loss seen in this study of people with type 2 diabetes is broadly comparable with that previously observed with injectable GLP-1.

Market implications

The trial’s results show that orforglipron, which was developed by Eli Lilly, can be considered one of semaglutide’s most credible challengers.

Another remarkable thing about orforglipron is that it belongs to a new category of drugs called small-molecule drugs. This means it’s a synthetic chemical compound small enough to be absorbed directly through the gut wall. There, it’s able to act on GLP-1 receptors, even though it isn’t of a similar structure to a GLP-1 hormone.

Oral semaglutide, on the other hand, is a peptide drug. This means the structure of its amino acids (one of the building blocks of protein) closely resembles that of the natural GLP-1 hormone.

As a small-molecule drug, orforglipron is cheaper and simpler to manufacture than peptide-based drugs such as semaglutide.

And as with oral semaglutide, it requires no refrigeration. This gives it a logistical advantage over injectable GLP-1 formulations – a potentially important consideration for expanding access in low- and middle-income countries, where cold chain infrastructure is unreliable.

It remains to be seen, however, how orforglipron will perform against oral semaglutide in the broader market.

Although this latest trial has shown it is superior for controlling blood sugar and aiding weight loss, its higher rate of side-effects and treatment discontinuation may temper enthusiasm. In a crowded and competitive market, long-term adherence – shaped as much by tolerability as by efficacy – is probably a critical differentiator.

Orforglipron is still undergoing trials in patients with obesity but without diabetes.

Martin Whyte, Associate Professor of Metabolic Medicine, University of Surrey

This article is republished from The Conversation under a Creative Commons license. Read the original article.

How do GLP-1 Agonists Improve Pancreatic Beta Cell Health?

Salk Institute researchers find protein that connects GLP-1 agonist drugs to long-term, broad genomic responses that can promote pancreatic health and resilience

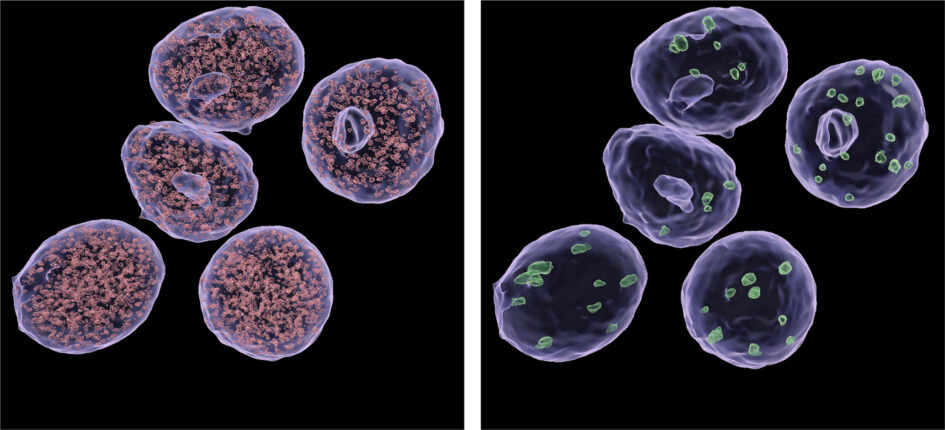
Small (left) and large (right) condensates of the Mediator complex inside nuclei of a pancreatic beta cell-derived cell line. Salk researchers discovered that GLP-1s interact with the multi-protein complex called Mediator to cause a broad genomic response.
Click here for a high-resolution image.
Credit: Salk Institute

GLP-1s are building a reputation as “wonder drugs.” First characterised for their ability to improve insulin release and treat diabetes, the drugs were later found to promote weight loss and improve cardiovascular health. In addition to these surprising bonus benefits is the ability of GLP-1 drugs to improve pancreatic beta cell health. But how, exactly, are they doing that?

Salk Institute researchers are burrowing down into the mechanistic details behind how GLP-1 drugs promote viability and stress resistance in pancreatic beta cells. Since cellular performance adaptations arise from gene expression changes, the team screened for regulatory proteins that can flip “on” advantageous gene programs during prolonged GLP-1 use. They identified a protein called Med14, part of a larger protein complex called Mediator, that was enabling the GLP-1-dependent changes in gene expression that lead to pancreatic health benefits.

The study was published in Proceedings of the National Academy of Sciences on March 4, 2026, and was funded by federal research grants from the National Institutes of Health and private philanthropy.

“The broad salutary effects of GLP-1 drugs in diabetes, cardiovascular disease, and obesity have sparked a wave of exciting scientific research at the mechanistic level. We’re left wondering,  ‘How are GLP-1s causing these effects?’” asks senior author Marc Montminy, MD, PhD, a biochemist, physiologist, and distinguished professor emeritus at Salk. “We were able to single out a protein, Med14, whose activation downstream of GLP-1 helps reprogram pancreatic beta cell gene expression to improve the cells’ viability and insulin production.”

What are GLP-1 drugs?

Often simply called “GLP-1 drugs” or “GLPs,” glucagon-like peptide-1 receptor agonists work by mimicking a hormone our bodies naturally make. The hormone, called glucagon-like peptide-1, helps regulate blood sugar.by promoting the secretion of insulin. They do so by attaching to corresponding GLP-1 receptors on pancreatic beta cells, which then produce and release insulin into the body.

But GLP-1 drugs differ in one significant way from their natural counterpart: Unlike human-made GLP-1 hormones that appear and disappear quickly around mealtimes, artificial GLP-1 receptor agonists can stick around much longer. The Salk researchers suspect this longer-term presence may explain some of the “wonder drug” benefits of GLP-1 drugs. But what, exactly, on the molecular level, are GLP-1 drugs doing when they stick around? And how does their staying power turn into effects like lower risk of stroke or improved osteoarthritis?

“The fact that these drugs based off our hormones are stable seems to be important to the longer-term effects we’re witnessing in pancreatic beta cells and other tissues,” says first author Sam Van de Velde, PhD, a staff scientist in Montminy’s lab. “To understand how we are getting these longer-term effects, we need to study these drugs on a longer time scale – and that’s exactly what we did.”

How do GLP-1 drugs influence pancreatic health?

When the hormone GLP-1 finds a pancreatic beta cell, the ensuing chain of signals, proteins, and gene expression changes that lead to insulin secretion is very well documented. On the other hand, the mechanisms and changes on the longer-term GLP-1 drug scale are poorly understood.

So, the researchers set out on a molecular fishing expedition in a pancreatic beta cell line. The team was hoping to hook a protein (or proteins) that, post-GLP-1 activation, had a particular chemical modification called phosphorylation. And that’s exactly what they found in Med14.

Med14 is a subunit in a multi-protein complex called Mediator, which is a well-described general regulator of gene expression throughout the genome. To confirm whether Med14 was an integral link between GLP-1 drugs and ultimate changes in gene expression and pancreatic beta cell behavior, the researchers decided to mutate Med14, making the protein resistant to phosphorylation.

The gene expression patterns associated with prolonged GLP-1 drug exposure disappeared in a Med14 mutant pancreatic beta cell line and in beta cells of a Med14 mutant mouse model. With working Med14, the helpful gene programs were activated – supercharging pancreatic beta cells to grow and better handle sugar-rich environments after meals.

How else might GLP-1 drugs affect the body?

None of the Salk team’s experiments were conducted in humans, yet the relevance remains. For example, some of the genes regulated by Med14 phosphorylation are known to be linked to type 2 diabetes susceptibility in humans.

“Our findings unexpectedly reveal that phosphorylation of just a small part of the Med14 protein plays a significant role in the response to GLP-1 drugs – and in the metabolic response to hormones more broadly,” says Reuben Shaw, PhD, a professor and holder of the William R. Brody Chair at Salk, and director of the National Cancer Institute-Designated Salk Cancer Center. “Now there are many new questions to answer, from validating our findings in human tissues to seeing whether Med14 has a similar role in other cells and organs.”

The team is especially curious about the effects of prolonged GLP-1 exposure beyond pancreatic beta cells. One of the messenger molecules between GLP-1 and Med14, called cAMP, is a commonly used messenger molecule in many other situations that don’t include GLP-1. With that in mind, could other drugs or hormones activate genetic programs similar to GLP-1? And what’s going on in other metabolically intensive tissues, like fat?

The questions keep coming for the so-called “wonder drug,” and Salk scientists are enthusiastically working to answer them.

Source: Salk Institute