The new implant carries a reservoir of glucagon that can be stored under the skin and deployed during an emergency — with no injections needed.
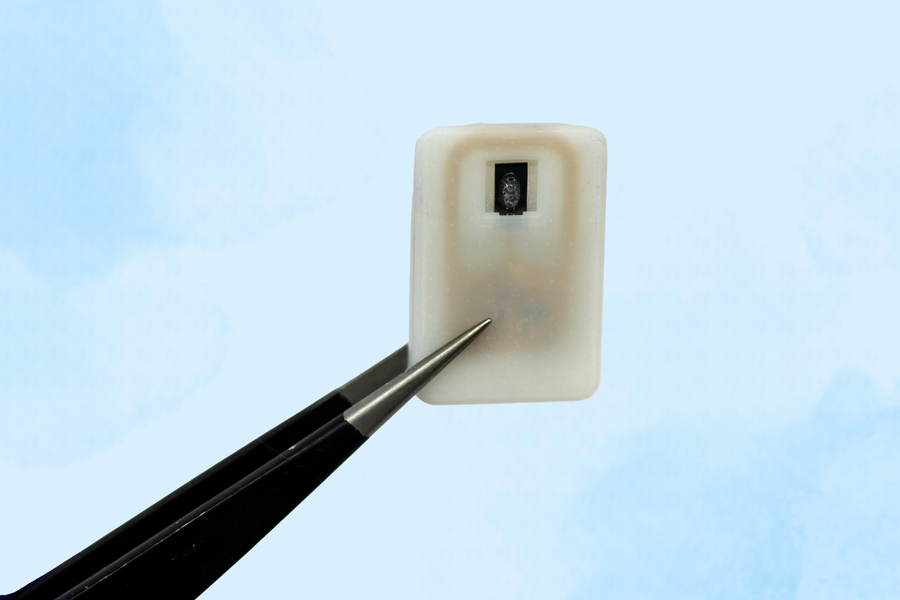
Caption:A new implantable device carries a reservoir of glucagon that can be stored under the skin and could save diabetes patients from dangerously low blood sugar.
Image: Courtesy of the researchers
For people with Type 1 diabetes, developing hypoglycaemia, or low blood sugar, is an ever-present threat. When glucose levels become extremely low, it creates a life-threatening situation for which the standard treatment of care is injecting a hormone called glucagon.
As an emergency backup, for cases where patients may not realise that their blood sugar is dropping to dangerous levels, MIT engineers have designed an implantable reservoir that can remain under the skin and be triggered to release glucagon when blood sugar levels get too low.
This approach could also help in cases where hypoglycaemia occurs during sleep, or for diabetic children who are unable to administer injections on their own.
“This is a small, emergency-event device that can be placed under the skin, where it is ready to act if the patient’s blood sugar drops too low,” says Daniel Anderson, a professor in MIT’s Department of Chemical Engineering, a member of MIT’s Koch Institute for Integrative Cancer Research and Institute for Medical Engineering and Science (IMES), and the senior author of the study. “Our goal was to build a device that is always ready to protect patients from low blood sugar. We think this can also help relieve the fear of hypoglycaemia that many patients, and their parents, suffer from.”
The researchers showed that this device could also be used to deliver emergency doses of epinephrine, a drug that is used to treat heart attacks and can also prevent severe allergic reactions, including anaphylactic shock.
Siddharth Krishnan, a former MIT research scientist who is now an assistant professor of electrical engineering at Stanford University, is the lead author of the study, which appears today in Nature Biomedical Engineering.
Emergency response
Most patients with type 1 diabetes use daily insulin injections to help their body absorb sugar and prevent their blood sugar levels from getting too high. However, if their blood sugar levels get too low, they develop hypoglycaemia, which can lead to confusion and seizures, and may be fatal if it goes untreated.
To combat hypoglycaemia, some patients carry preloaded syringes of glucagon, a hormone that stimulates the liver to release glucose into the bloodstream. However, it isn’t always easy for people, especially children, to know when they are becoming hypoglycaemic.
“Some patients can sense when they’re getting low blood sugar, and go eat something or give themselves glucagon,” Anderson says. “But some are unaware that they’re hypoglycaemic, and they can just slip into confusion and coma. This is also a problem when patients sleep, as they are reliant on glucose sensor alarms to wake them when sugar drops dangerously low.”
To make it easier to counteract hypoglycaemia, the MIT team set out to design an emergency device that could be triggered either by the person using it, or automatically by a sensor.
The device, which is about the size of a quarter, contains a small drug reservoir made of a 3D-printed polymer. The reservoir is sealed with a special material known as a shape-memory alloy, which can be programmed to change its shape when heated. In this case, the researcher used a nickel-titanium alloy that is programmed to curl from a flat slab into a U-shape when heated to 40 degrees Celsius.
Like many other protein or peptide drugs, glucagon tends to break down quickly, so the liquid form can’t be stored long-term in the body. Instead, the MIT team created a powdered version of the drug, which remains stable for much longer and stays in the reservoir until released.
Each device can carry either one or four doses of glucagon, and it also includes an antenna tuned to respond to a specific frequency in the radiofrequency range. That allows it to be remotely triggered to turn on a small electrical current, which is used to heat the shape-memory alloy. When the temperature reaches the 40-degree threshold, the slab bends into a U shape, releasing the contents of the reservoir.
Because the device can receive wireless signals, it could also be designed so that drug release is triggered by a glucose monitor when the wearer’s blood sugar drops below a certain level.
“One of the key features of this type of digital drug delivery system is that you can have it talk to sensors,” Krishnan says. “In this case, the continuous glucose-monitoring technology that a lot of patients use is something that would be easy for these types of devices to interface with.”
Reversing hypoglycaemia
After implanting the device in diabetic mice, the researchers used it to trigger glucagon release as the animals’ blood sugar levels were dropping. Within less than 10 minutes of activating the drug release, blood sugar levels began to level off, allowing them to remain within the normal range and avert hypoglycaemia.
The researchers also tested the device with a powdered version of epinephrine. They found that within 10 minutes of drug release, epinephrine levels in the bloodstream became elevated and heart rate increased.
In this study, the researchers kept the devices implanted for up to four weeks, but they now plan to see if they can extend that time up to at least a year.
“The idea is you would have enough doses that can provide this therapeutic rescue event over a significant period of time. We don’t know exactly what that is — maybe a year, maybe a few years, and we’re currently working on establishing what the optimal lifetime is. But then after that, it would need to be replaced,” Krishnan says.
Typically, when a medical device is implanted in the body, scar tissue develops around the device, which can interfere with its function. However, in this study, the researchers showed that even after fibrotic tissue formed around the implant, they were able to successfully trigger the drug release.
The researchers are now planning for additional animal studies and hope to begin testing the device in clinical trials within the next three years.
“It’s really exciting to see our team accomplish this, which I hope will someday help diabetic patients and could more broadly provide a new paradigm for delivering any emergency medicine,” says Robert Langer, the David H. Koch Institute Professor at MIT and an author of the paper.
Other authors of the paper include Laura O’Keeffe, Arnab Rudra, Derin Gumustop, Nima Khatib, Claudia Liu, Jiawei Yang, Athena Wang, Matthew Bochenek, Yen-Chun Lu, Suman Bose, and Kaelan Reed.
The research was funded by the Leona M. and Harry B. Helmsley Charitable Trust, the National Institutes of Health, a JDRF postdoctoral fellowship, and the National Institute of Biomedical Imaging and Bioengineering.
A healthy lifestyle has important benefits, but weight alone might not give an adequate picture of someone’s health, say experts
Source: Pixabay CC0
Focusing solely on achieving weight loss for people with a high body mass index (BMI) may do more harm than good, argue experts in The BMJ.
Dr Juan Franco and colleagues say, on average, people with high weight will not be able to sustain a clinically relevant weight loss with lifestyle interventions, while the potential harms of weight loss interventions, including the reinforcement of weight stigma, are still unclear.
They stress that a healthy lifestyle has important benefits, but that weight alone might not give an adequate picture of someone’s health, and say doctors should provide high quality, evidence based care reflecting individual preferences and needs, regardless of weight.
Lifestyle interventions that focus on restricting an individual’s energy intake and increasing their physical activity levels have for many decades been the mainstay recommendation to reduce weight in people with obesity, explain the authors.
However, rigorous evidence has indicated that these lifestyle interventions are largely ineffective in providing sustained long term weight loss and reducing cardiovascular events (eg, heart attacks and strokes) or death.
Even though a healthy lifestyle provides important benefits, acknowledging that weight alone might not give an adequate picture of someone’s health, and recognising the limitations of lifestyle interventions for weight loss, could pave the way for more effective and patient centred care, they say.
Focusing on weight loss might also contribute to societal weight bias – negative attitudes, assumptions, and judgments about people based on their weight – which may not only have adverse effects on mental health but may also be associated with disordered eating, the adoption of unhealthy habits, and weight gain, they add.
They point out that recent clinical guidelines reflect the growing recognition that weight is an inadequate measure of health, and alternative approaches, such as Health at Every Size (HAES), acknowledge that good health can be achieved regardless of weight loss and have shown promising results in improving eating behaviours.
While these approaches should be evaluated in large clinical trials, doctors can learn from them to provide better and more compassionate care for patients with larger bodies, they suggest.
“Doctors should be prepared to inform individuals seeking weight loss about the potential benefits and harms of interventions and minimise the risk of developing eating disorders and long term impacts on metabolism,” they write. “Such a patient centred approach is likely to provide better care by aligning with patient preferences and circumstances while also reducing weight bias.”
They conclude: “Doctors’ advice about healthy eating and physical activity is still relevant as it may result in better health. The main goal is to offer good care irrespective of weight, which means not caring less but rather discussing benefits, harms, and what is important to the patient.”
Scientists have produced the first detailed characterisation of the changes that weight loss causes in human fat tissue by analysing hundreds of thousands of cells. They found a range of positive effects, including clearing out of damaged, ageing cells and increased metabolism of harmful fats.
The researchers say the findings help to better understand how weight loss leads to health improvements at a molecular level. In the future this could help to inform the development of therapies for diseases such as type 2 diabetes.
The study
The study, published in Nature, compared samples of fat tissue from healthy weight individuals with samples from people with severe obesity, meaning a BMI over 35, undergoing bariatric weight loss surgery.
The weight loss group had fat samples taken during surgery and more than five months after surgery, at which point they had lost an average of 25kg.
Lipid recycling
The researchers, who were from the Medical Research Council (MRC) Laboratory of Medical Sciences and Imperial College London, analysed gene expression in more than 170,000 cells that made up the fat tissue samples, from 70 people.
They unexpectedly found that weight loss triggers the breakdown and recycling of fats called lipids.
This recycling process could be responsible for burning energy and reversing the harmful build-up of lipids in other organs like the liver and pancreas.
The researchers say that further study will be needed to establish if lipid recycling is linked to the positive effects of weight loss on health, such as remission of type 2 diabetes.
Senescent cells
They also found that the weight loss cleared out senescent cells, which are ageing and damaged cells that accumulate in all tissues.
The senescent cells cause harm because they no longer function properly and release signals that lead to tissue inflammation and scarring.
Immune system
In contrast, the researchers found that weight loss did not improve the effects of obesity on certain aspects of the immune system.
They found that inflammatory immune cells, which infiltrated the fat of people with obesity, did not fully recover even after weight loss.
This type of inflammatory cell memory could be harmful in the long term if people regain weight.
Detailed map of what drives health benefits
Dr William Scott, from the MRC Laboratory of Medical Sciences and from Imperial College London, who led the study, said:
We’ve known for a long time that weight loss is one of the best ways to treat the complications of obesity, such as diabetes, but we haven’t fully understood why. This study provides a detailed map of what may actually be driving some of these health benefits at a tissue and cellular level.
Fat tissues have many underappreciated health impacts, including on blood sugar levels, body temperature, hormones that control appetite, and even reproductive health.
We hope that new information from studies like ours will start to pave the way for developing better treatments for diabetes and other health problems caused by excess body fat.
The skeletal muscles of men and women process glucose and fats in different ways. A recently published study now provides the first comprehensive molecular analysis of these differences. The results possibly give an explanation why metabolic diseases such as diabetes manifest differently in women and men – and why they respond differently to physical activity.
Skeletal muscles are far more than just “movement driving motors.” They play a central role in glucose metabolism and therefore also in the development of type 2 diabetes. This is due to the fact that around 85% of insulin-dependent glucose uptake takes place in the muscles. This means that if muscle cells react less sensitively to insulin, for example in the case of insulin resistance, glucose is less easily absorbed from the blood. This process is specifically counteracted by physical activity.
Women’s and Men’s Muscles Work Differently
The degree to which muscles work differently in women and men has long been underestimated. It is precisely this issue which has now been investigated by researchers at the Institute for Diabetes Research and Metabolic Diseases at Helmholtz Munich, the University Hospital of Tübingen and the German Center for Diabetes Research (DZD) e.V. The researchers, led by Dr Simon Dreher and Prof Cora Weigert, examined muscle biopsies from 25 healthy but overweight adults (16 women, 9 men) aged around 30 years. The test subjects had not taken part in regular sporting activities beforehand. Over a period of eight weeks, they completed one hour of endurance training three times a week, consisting of 30 minutes of cycling and 30 minutes of walking on the treadmill.
Muscle samples were taken before they started, after they had the first training session and at the end of the program. Using state-of-the-art molecular biological methods, including epigenome, transcriptome and proteome analyses, the team investigated sex-specific differences at various levels.
Men React with more Stress to Exercise
The result: The first training session triggered a stronger stress response at the molecular level in men, which became manifest in the increased activation of stress genes and the increase in the muscle protein myoglobin in the blood. In addition, male muscles showed a distinct pattern of what are called fast-twitch fibers, which are designed for short-term, intensive exercise and preferably use glucose as an energy source.
Women had significantly higher amounts of proteins that are responsible for the absorption and storage of fatty acids: an indication of more efficient fat utilisation. After eight weeks of regular endurance training, the muscles of both sexes matched and the muscle fibre-specific differences decreased. At the same time, women and men produced more proteins that promote the utilisation of glucose and fat in the mitochondria.
“These adjustments indicate an overall improvement in metabolic performance, which can help to reduce the risk of type 2 diabetes,” says Weigert. “In future, our new findings might help to better predict individual diabetes risks and tailor recommendations for exercise therapies more specifically to women and men.”
The scientists next want to investigate the role sex hormones play in these differences – and how hormonal changes in old age influence the risk of metabolic diseases.
Original publication
Dreher et al., 2025: Sex differences in resting skeletal muscle and the acute and long-term response to endurance exercise in individuals with overweight and obesity. Molecular Metabolism. DOI: 10.1016/j.molmet.2025.102185
About the scientists
Prof. Cora Weigert is head of the research group “Molecular Diabetology and Exercise” at the Institute for Diabetes Research and Metabolic Diseases at Helmholtz Munich and Professor at the University of Tübingen.
Dr. Simon Dreher is scientist at the Institute for Diabetes Research and Metabolic Diseases at Helmholtz Munich and at the University of Tübingen.
A drug commonly used to treat type 2 diabetes may reduce excess fluid in the brains of patients with hydrocephalus, which could help treat the disease less invasively than current treatments, according to a Northwestern Medicine study published in theJournal of Clinical Investigation.
Normal pressure hydrocephalus occurs when excess cerebrospinal fluid builds up inside the skull and puts pressure on the brain. The cause of the condition is elusive and affects up to three percent of individuals over the age of 65, with symptoms including cognitive decline, difficulty walking and bladder problems.
Patients are typically treated with permanent ventriculoperitoneal shunts, which are surgically implanted in the front or back of the skull and are connected to a valve that diverts excess cerebrospinal fluid away from the brain and into the abdomen where it is absorbed. The procedure has been shown to dramatically improve mobility, bladder control and cognitive functioning in patients with hydrocephalus, according to senior study author Stephen Magill, MD, PhD.
“It’s a great procedure because it’s one of the few things you can do that actually reverses these symptoms,” said Magill, who is assistant professor of Neurological Surgery.
There is, however, no pharmacological treatment currently approved to treat hydrocephalus. Additionally, nearly 20% of patients with normal pressure hydrocephalus also have type 2 diabetes and take sodium/glucose cotransporter 2 (SGLT2) inhibitors to manage their blood sugar, cardiovascular and kidney function, and weight loss.
Magill recently observed a reduction in the brain ventricle size in a patient with hydrocephalus who had a ventriculoperitoneal shunt surgically implanted and then began taking SGLT2 inhibitors to treat their type 2 diabetes. This phenomenon prompted Magill to further investigate the impact of SGLT2 inhibitors on ventricular size in patients with hydrocephalus.
“The medication inhibits a receptor found in the kidneys, which is where it works for diabetes. However, that receptor is also expressed in the choroid plexus, which is the structure in the brain that secretes the spinal fluid. Although this was known from animal studies, the clinical aspects of this biology have not been fully appreciated,” Magill said.
In the current study, three patients with hydrocephalus underwent CT scans both before and after surgery for ventriculoperitoneal shunts. After surgery, each patient began taking SGLT2 inhibitors for a medical indication and then underwent additional CT scans.
From analyzing these scans, Magill’s team discovered that all three patients showed a reduction in ventricle size as well as structural changes in their brains after starting SGLT2 therapy. One patient demonstrated dramatic ventricle size reduction due to ventricular collapse and required a shunt valve adjustment to reduce cerebrospinal fluid drainage.
“It’s a really interesting clinical observation because it raises the possibility that these medications could be used to treat normal pressure hydrocephalus in the future, which would normally require surgery,” Magill said.
Magill said the findings have sparked a new line of research in studying how SGLT2 inhibitors could help prevent hydrocephalus, adding that his team is now studying SGLT2 knockout mouse models to better understand the drug’s impact on ventricular size.
Their findings could ultimately inform new therapeutic strategies for treating normal pressure hydrocephalus as well as post-traumatic hydrocephalus, or the buildup of cerebrospinal fluid after traumatic brain injury, according to Magill.
“This sparks a new line of research on how normal pressured hydrocephalus develops, what causes it, how this protein works in creating and secreting spinal fluid, and has direct translational implications,” Magill said. “There’s a whole new avenue of potentially treating this disease that might save a patient from having surgery, and there’s always risks with surgery. It will also evolve our understanding of how these drugs work.”
It is well known that preventing the onset of diabetes reduces the risk of death, and that managing blood glucose levels is key to preventing diabetes. However, it remains unclear whether there are specific ranges within “normal” blood glucose levels that are associated with even lower mortality risks.
A small farming community in the Tohoku Region of northern Japan has possibly provided researchers with further insights.
For over 40 years, the Ohasama Study, named after a town in Iwate Prefecture, has tracked the long-term health of Ohasama’s local population. Since 1986, the study has collected health and medical data through regular checkups and tests.
As part of the study, participants have undergone a glucose tolerance test every four years. This test, which is commonly used to diagnose diabetes, measures blood glucose levels before and 120 minutes after drinking a glucose-containing beverage.
Now, a research team has analysed the glucose tolerance test data from the Ohasama Study, publishing their findings in the journal PNAS Nexus. Junta Imai and Hideki Katagiri from Tohoku University led the study.
“We first examined the relationship between mortality and various health test results, including but not limited to glucose tolerance tests, for 993 individuals,” explains Imai. “Even after adjusting for known risk factors such as age, obesity, and smoking, the one-hour post-glucose load blood glucose level showed a strong correlation with mortality.”
Participants were then divided into two groups based on the median one-hour post-glucose load blood glucose level of 162mg/dL. The survival analysis showed significantly better outcomes in the lower-glucose group.
Since some participants had already developed diabetes, the researchers narrowed their focus to 595 individuals with normal glucose tolerance. They analysed which glucose threshold had the strongest correlation with mortality and found that 170mg/dL was the most predictive.
Using this threshold, Imai and his colleagues conducted a survival analysis, comparing those with post-glucose load blood glucose levels below and above 170mg/dL. After 20 years, nearly 80% of the under-170mg/dL group were still alive, while almost 50% of the over-170mg/dL group had died – a statistically significant result.
Further analysis of cause-of-death data revealed that individuals with one-hour post-glucose load blood glucose levels under 170mg/dL had significantly fewer deaths due to heart disease caused by atherosclerosis (p < 0.0001) and malignant tumours (p < 0.0014) compared to those with higher levels.
“These findings demonstrate that even within the range considered ‘normal,’ there is a subset of blood glucose levels associated with a lower risk of death,” adds Imai. “Besides taking measures to prevent diabetes, greater efforts towards managing blood glucose spikes shortly after eating could help prevent heart disease and cancer, ultimately leading to longer, healthier lives.”
For many, fitness trackers have become indispensable tools for monitoring how many calories they’ve burned in a day. But for those living with obesity, who are known to exhibit differences in walking gait, speed, energy burned and more, these devices often inaccurately measure activity – until now.
Scientists at Northwestern University have developed a new algorithm that enables smartwatches to more accurately monitor the calories burned by people with obesity during various physical activities.
The technology bridges a critical gap in fitness technology, said Nabil Alshurafa, whose Northwestern lab, HABits Lab, created and tested the open-source, dominant-wrist algorithm specifically tuned for people with obesity. It is transparent, rigorously testable and ready for other researchers to build upon. Their next step is to deploy an activity-monitoring app later this year that will be available for both iOS and Android use.
“People with obesity could gain major health insights from activity trackers, but most current devices miss the mark,” said Alshurafa, associate professor of behavioral medicine at Northwestern University Feinberg School of Medicine.
Current activity-monitoring algorithms that fitness trackers use were built for people without obesity. Hip-worn trackers often misread energy burn because of gait changes and device tilt in people with higher body weight, Alshurafa said. And lastly, wrist-worn models promise better comfort, adherence and accuracy across body types, but no one has rigorously tested or calibrated them for this group, he said.
“Without a validated algorithm for wrist devices, we’re still in the dark about exactly how much activity and energy people with obesity really get each day — slowing our ability to tailor interventions and improve health outcomes,” said Alshurafa, whose team tested his lab’s algorithm against 11 state-of-the-art algorithms designed by researchers using research-grade devices and used wearable cameras to catch every moment when wrist sensors missed the mark on calorie burn.
The findings will be published June 19 in Nature Scientific Reports.
The exercise class that motivated the research
Alshurafa was motivated to create the algorithm after attending an exercise class with his mother-in-law who has obesity.
“She worked harder than anyone else, yet when we glanced at the leaderboard, her numbers barely registered,” Alshurafa said. “That moment hit me: fitness shouldn’t feel like a trap for the people who need it most.”
Algorithm rivals gold-standard methods
By using data from commercial fitness trackers, the new model rivals gold-standard methods of measuring energy burn and can estimate how much energy someone with obesity is using every minute, achieving over 95% accuracy in real-world situations. This advancement makes it easier for more people with obesity to track their daily activities and energy use, Alshurafa said.
How the study measured energy burn
In one group, 27 study participants wore a fitness tracker and metabolic cart – a mask that measures the volume of oxygen the wearer inhales and the volume of carbon dioxide the wearer exhales to calculate their energy burn (in kilocalories/kCals) and resting metabolic rate. The study participants went through a set of physical activities to measure their energy burn during each task. The scientists then looked at the fitness tracker results to see how they compared to the metabolic cart results.
In another group, 25 study participants wore a fitness tracker and body camera while just living their lives. The body camera allowed the scientists to visually confirm when the algorithm over- or under-estimated kCals.
At times, Alshurafa said he would challenge study participants to do as many pushups as they could in five minutes.
“Many couldn’t drop to the floor, but each one crushed wall-pushups, their arms shaking with effort,” he said, “We celebrate ‘standard’ workouts as the ultimate test, but those standards leave out so many people. These experiences showed me we must rethink how gyms, trackers and exercise programs measure success – so no one’s hard work goes unseen.”
Health workers have long relied on Body Mass Index as a way to measure whether people are within a healthy weight range. Now, a collection of top researchers have made the case for a new way to understand and diagnose obesity. In part two of this special Spotlight series, we take a look at what this new framing might mean for South Africa.
If we are going to tackle the global rise in obesity, our understanding of the condition needs to change. That is according to a Lancet Commission convened by a global group of 58 experts from different medical specialties. While we have historically thought of obesity as a risk factor for other diseases like diabetes, the commission’s recent report published in the journal Lancet Diabetes and Endocrinology concludes that obesity is sometimes better thought of as a disease itself – one that can directly cause severe health symptoms (see part one of this series for a detailed discussion of this argument).
By categorising obesity as a disease, public health systems and medical aid schemes around the world would be more likely to cover people for weight-loss drugs or weight-loss surgery, according to the report. At present, these services are often only financed if a patient’s obesity has already led to other diseases. This is given that obesity is not viewed as a stand-alone chronic illness.
But if we’re going to redefine obesity as a disease, or at least some forms of it, then we need good clinical definitions and ways to measure it. For a long time, this has posed challenges, according to the Lancet report.
The perils of BMI
At present, health workers often rely on Body Mass Index (BMI) to gauge whether a patient is within a healthy weight range. BMI is measured by taking a person’s weight in kilograms and dividing it by their height in meters squared.
A healthy weight is typically considered to be between 18.5 and 25. A person whose BMI is between 25 and 30 is considered to be overweight, while someone with a BMI of over 30 is considered to have obesity. But according to the Lancet report, this is a crude measure, and one which provides very little information about whether a person is actually ill.
One basic issue is that a person can have a high BMI even if they don’t have a lot of excess fat. Instead, they may simply have a lot of muscle or bone. Indeed, the report notes that some athletes are in the obese BMI range.
Even when a high BMI does indicate that a person has obesity, it still doesn’t tell us where a person’s fat is stored and this is vital medical information. If excess fat is stored in the stomach and chest, then it poses more severe health risks than when it is stored in the limbs or thighs. This is because excess fat will do more harm if it surrounds vital organs.
The lead author of the Lancet report, Professor Frances Rubino, says that the pitfalls of BMI have long been understood, but practitioners have continued to use it.
“BMI is still by and large the most used approach everywhere, even though medical organisations have [raised issues] for quite some time,” he tells Spotlight.
“The problem is that even when we as individuals or organisations say BMI is no good, we haven’t provided an alternative. And so, inevitably, the ease of calculating BMI and the uncertainties about alternatives makes you default back to BMI.”
To deal with this problem, the report advocates for several alternative techniques for measuring obesity which offer more precision.
The first option is to use tools that directly measure body composition like a DEXA scanner. This is a sophisticated x-ray machine which can be used to distinguish between fat, bone and muscle. It can also be used to determine where fat is concentrated. It’s thus a very precise measurement tool, but the machines are expensive and the scans can be time-consuming.
Alternatively, the report recommends using BMI in combination with another measure like waist-to-hip ratio, waist-to-height ratio or simply waist circumference. If two of these alternative measures are used, then BMI can be removed from the picture.
These additional metrics are clinically useful because they provide information about where fat is stored. For instance, a larger waistline inevitably indicates a larger stomach. Indeed, studies have found that above a certain level, a larger waist circumference is linked to a higher chance of dying early, even when looking at people with the same BMI.
The report thus offers a more accurate way to measure obesity in the clinical setting. But its authors argue that this is only the first step when making a diagnosis. The second is to look at whether a patient’s obesity has actually caused health problems as this isn’t automatically the case. They acknowledge for instance that there are some people with obesity who “appear to be able to live a relatively healthy life for many years, or even a lifetime”.
The report refers to these cases as “preclinical obesity”. Such patients don’t have a disease as such, according to the report, but still have an increased risk of facing health issues in the future. As such, the report’s authors argue that they should be monitored and sometimes even treated, depending on factors like family history.
By contrast, cases of obesity which have directly caused health problems are referred to as “clinical obesity”. These cases, according to the report, should be treated immediately just like any other serious disease. It lists a series of medical symptoms associated with clinical obesity that would allow health workers to make an appropriate diagnosis.
The recommendation is thus for health workers to determine whether a person has obesity through the metrics listed above, and then to determine whether it is clinical or preclinical by evaluating a patient’s symptoms. This will inevitably guide the treatment plan.
How does this relate to SA?
Professor Francois Venter, who runs the Ezintsha research centre at WITS university, says the Lancet report offers a good starting point for South Africa, but it has to be adapted for our own needs and context.
“It’s a big step forward from BMI which grossly underdiagnoses and overdiagnoses obesity,” says Venter, who adds that additional metrics like waist circumference are a “welcome addition”.
The view that clinical obesity is a disease that needs to be immediately treated is also correct, according to Venter. Though he adds that the public health system in South Africa is not in a financial position to start handing out weight-loss medicine to everyone who needs it.
“The drugs are hugely expensive,” says Venter, “and they have side effects, so you need a lot of resources to support people taking them.” But while it may not yet be feasible to treat all cases of clinical obesity in South Africa, Venter believes we should use the diagnostic model offered by the Lancet Commission to begin identifying at least some people with clinical obesity so that they can begin treatment.
“You have to start somewhere, and for that you need a good staging system,” he says. “Let’s use the Lancet Commission and start to see if we can identify a few priority people and screen them and start to work on the drug delivery system.”
Yet while Venter believes that the commission makes important contributions, he also cautions that we need more data on obesity in Africa before we can apply all of its conclusions to our own context.
“If you go to the supplement of the Lancet Commission, there’s not a single African study there. It all comes from Europe, North America and Asia. It’s not the commission’s fault but [there is a lack of data on Africa].”
This is important as findings that apply to European or Asian populations may not necessarily hold for others. Consider the following case.
As noted, the commission states that BMI is not sufficient to determine whether someone is overweight and must therefore be complemented with other measures. But it states that if someone’s BMI is above 40 (way above the current threshold for obesity), then this can “pragmatically be assumed” without the need for further measures.
But this may not hold in Africa, says Venter.
“The commission says that if your BMI is over 40, which is very big, you can infer that this person has got obesity and they are sick and need to lose weight. I don’t know if we can say that in Africa, where we often have patients who are huge, and yet they are very active, and when you [look at] their blood pressure and all their metabolics, they’re actually pretty healthy,” he notes. “So, I think they’re sometimes jumping to conclusions about African populations that we don’t have data on,” adds Venter.
Is South Africa ready to move past BMI?
Another concern is that while the Lancet Commission may offer useful recommendations for advanced economies, its starting assumptions may not be as relevant for countries like South Africa.
For instance, while specialists agree that BMI is a crude measure of obesity, direct measures like DEXA scans are “out of our reach economically”, according to Professor Susan Goldstein, who leads PRICELESS-SA, a health economics unit at the South African Medical Research Council.
And while supplementing BMI with the other metrics like waist circumference may be doable, health experts told Spotlight that at present healthcare workers in South Africa aren’t even measuring BMI alone.
Dr Yogan Pillay, a former deputy director-general at the national health department who now runs TB and HIV delivery at the Gates Foundation, told Spotlight: “I can’t tell you how few people in the public sector have their BMI monitored at all. Community health workers are supposed to be going out and measuring BMI, but even that’s not happening”.
Goldstein also suggests that the monitoring of BMI in South Africa is limited. “If you go into the clinic for your blood pressure, do they say: ‘How’s your BMI?’ No, I doubt that,” says Goldstein. “It’s just not one of the measures that [gets done].”
She adds that South Africa could introduce the combination of metrics proposed by the commission, like waist circumference combined with BMI, but says it would simply require “a lot of re-education of health workers”.
Prevention vs treatment
For Goldstein, the commission is correct to regard clinical obesity as a disease which needs to be treated, but we also shouldn’t view medication as the only way forward.
“We have to remember that prevention is very important,” says Goldstein. “We have to focus on food control, we have to look at ultra-processed foods, and unless we do that as well [in addition to medication] we are going to lose this battle.”
The National Health Department already has a strategy document for preventing obesity, but some of its recommendations have been critiqued for focusing on the wrong problems. For instance, to prevent childhood obesity, the strategy document recommends reforming the Life Orientation curriculum and educating tuck shop vendors so that both students and food sellers have more information about healthy eating. But as Spotlight previously reported, there are no recommendations to subsidise healthy foods or to increase their availability in poor areas, which several experts believe is more important than educational initiatives.
Venter also highlights the importance of obesity prevention, though he emphasises that this shouldn’t be in conflict with a treatment approach – instead, we need to push for both.
“The [prevention] we need to do is fix the food supply… and the only way you do that is to decrease the cost of unprocessed food.” But while this may help prevent future cases of obesity, it doesn’t help people who are already suffering from obesity, says Venter. And since such people comprise such a large share of the population, we can’t simply ignore them, he says.
“Even if you fix the entire food industry tomorrow, those [people who are already obese] are going to remain where they are because simply changing your diet isn’t going to do diddly squat [when you already have obesity],” he adds. (Part 1 discusses this in more detail).
Goldstein adds that increasing access to treatment would also inevitably reduce the costs of “hypertension, diabetes, osteoarthritis, and a whole range of other illnesses if it’s properly managed”.
One way to advance access to medication would be for the government to negotiate reduced prices of GLP-1 drugs, she says. (Spotlight previously reported on the prices and availability of these medicines in South Africa here.)
Funding
A final concern that has been raised about the Lancet commission is about its source of funding.
“I don’t know how one gets around this,” says Goldstein, “but there were 58 experts on the commission, 47 declared conflicts of interest.”
Indeed, the section of the commission that lists conflicts of interest spans over 2 000 words (roughly the size of this article). This includes research grants and consulting fees from companies like Novo Nordisk and Eli Lilly, which produce anti-obesity drugs.
In response, Rubino told Spotlight that “people who work in the medical profession obviously work and consult, and the more expertise they have, the more likely they are to be asked by somebody to advise. So sometimes people have contracts to consult a company – but that doesn’t mean that they necessarily make revenue if the company has better sales. You get paid fees for your services as a consultant”.
Rubino says this still has to be declared as it may result in some bias, even if it is unconscious, but “if you wanted to have experts who had zero relationship [to companies] of any sort then you might have to wonder if there is expertise available there… the nature of any medical professional is that the more expertise they have, the more likely that they have engaged in work with multiple stakeholders”.
For Venter, there is some truth to this. “It’s very difficult to find people in the obesity field that aren’t sponsored by a drug company,” he says. “Governments don’t fund research… and everyone else doesn’t fund research. Researchers go where the research is funded.”
This doesn’t actually solve the problem, says Venter, as financing from drug companies can always influence the conclusions of researchers. It simply suggests that the problem is bigger than the commission. Ultimately, he argues that the authors should at least be applauded for providing such granular details about conflicts of interest.
Rubino adds that while researchers on the commission may have historically received money from drug companies for separate research studies or consulting activities, none of them received money for their work on the commission itself.
“This commission has been working for more than four years since conception… An estimate of how many meetings we had is north of 700, and none of us have received a single penny [for doing this],” he says.
Disclosure: The Gates Foundation is mentioned in this article. Spotlight receives funding from the Gates Foundation but is editorially independent – an independence that the editors guard jealously. Spotlight is a member of the South African Press Council.
A new study in teenagers with type 1 diabetes shows promise in reducing chronic kidney disease and informing future precision care.
Photo by Nataliya Vaitkevich on Pexels
A clinical trial involving adolescents with type 1 diabetes (T1D) has found a combination therapy may reduce chronic kidney disease and improve health outcomes. The findings could help guide more precision care for young people with T1D.
Led by Dr Farid Mahmud, Associate Scientist in the Translational Medicine program and Staff Physician in the Division of Endocrinology at The Hospital for Sick Children (SickKids), and published in Nature Medicine, the study evaluated a therapy that combines standard insulin treatment with the investigational drug dapagliflozin. Results of this combination therapy showed improved blood sugar control and kidney function, and reduced weight gain in adolescents with T1D.
While most people with T1D are diagnosed as adults, the condition often starts in childhood and early adolescence. The lifelong insulin therapy needed can lead to side effects such as weight gain and chronic kidney disease. In the trial, participants who received dapagliflozin alongside insulin had fewer of these side effects and better overall health outcomes.
“Our findings showed that adolescents who received this combination therapy were able to improve many symptoms typically associated with insulin-managed type one diabetes,” says Mahmud. “This could inform a new early intervention strategy for the growing population of teenagers with type one diabetes.”
Patient partner key to trial success
While previous research has shown similar results in adults, Mahmud’s team focused on designing a clinical trial specifically for teenagers, a group often underrepresented in clinical trials. Hormonal changes, psychological development, and the shared responsibility between teens and their parents for managing treatment protocols can make trial participation more complex for this age group.
To address these challenges, the research team worked closely with patient partner Lynne McArthur. Together, they enrolled 98 participants between 12 and 18 years old in the study, known as the ATTEMPT study, across three sites.
McArthur’s involvement in research began when one of her twin sons was diagnosed with T1D following a trip to the SickKids emergency department at just 18 months old. A few years later, his twin was also diagnosed. That experience led McArthur to become more involved in research efforts to improve diagnosis and treatment options for families like hers.
“Deciding to participate in a clinical trial is an important decision, but my goal has always been disease prevention. I knew that our participation could help build a future where children don’t get T1D.”
Lynne McArthur
Now that her sons are older, McArthur continues to be involved as a patient advisor. She reviews recruitment materials and provides feedback on trial design, helping ensure the research stays connected to the lived experience of people managing T1D.
“Participating in research, whether in a trial or as an advisor, is hugely rewarding. With my experience as trial participant, I can see how the plans on paper would impact the real lives of people living with diabetes,” explains McArthur.
Eating a high-fat diet containing a large amount of oleic acid – a type of fatty acid commonly found in olive oil – could drive obesity more than other types of dietary fats, according to a study published in the journal Cell Reports.
The study found that oleic acid, a monounsaturated fat associated with obesity but also tentatively linked to cardiovascular benefits and often touted as a ‘healthy’ fatty acid, causes the body to make more lipid cells. By boosting a signalling protein called AKT2 and reducing the activity of a regulating protein called LXR, high levels of oleic acid resulted in faster growth of the precursor cells that form new lipid cells.
“We know that the types of fat that people eat have changed during the obesity epidemic. We wanted to know whether simply overeating a diet rich in fat causes obesity, or whether the composition of these fatty acids that make up the oils in the diet is important. Do specific fat molecules trigger responses in the cells?” said Michael Rudolph, PhD, assistant professor of biochemistry and physiology at the University of Oklahoma College of Medicine.
Rudolph and his team fed mice a variety of specialised diets enriched in specific individual fatty acids, including those found in coconut oil, peanut oil, milk, lard and soybean oil. Oleic acid was the only one that caused the precursor cells that give rise to fat cells to proliferate more than other fatty acids.
“You can think of the fat cells as an army,” Rudolph said. “When you give oleic acid, it initially increases the number of ‘fat cell soldiers’ in the army, which creates a larger capacity to store excess dietary nutrients. Over time, if the excess nutrients overtake the number of fat cells, obesity can occur, which can then lead to cardiovascular disease or diabetes if not controlled.”
Unfortunately, it’s not quite so easy to isolate different fatty acids in a human diet. People generally consume a complex mixture if they have cream in their coffee, a salad for lunch and meat and pasta for dinner. However, Rudolph said, there are increasing levels of oleic acid in the food supply, particularly when access to food variety is limited and fast food is an affordable option.
“I think the take-home message is moderation and to consume fats from a variety of different sources,” he said. “Relatively balanced levels of oleic acid seem to be beneficial, but higher and prolonged levels may be detrimental. If someone is at risk for heart disease, high levels of oleic acid may not be a good idea.”