A new drug is effective at decreasing recurrence of and death from endometrial cancer, a landmark international study shows. The drug, called sacituzumab tirumotecan (sac-TMT), attaches to a protein on the surface of tumour cells and then delivers a targeted dose of a chemical that leads to cancer cell death.
Cancers of the endometrium are the most common in the female reproductive system. They are becoming more deadly and have few effective treatment options, especially if diagnosed late, researchers say. Moreover, until now, no standard therapies have existed to prevent or stall its recurrence after initial chemotherapy and immunotherapy.
In the phase 3 TroFuse-005/ENGOT-en23/GOG-3095 trial (NCT06132958), sac-TMT reduced the risk of progression by 41% and death by 32% versus chemotherapy in patients with advanced or recurrent endometrial cancer previously treated with chemotherapy plus pembrolizumab.
Objective response rates were 35.1% with sac-TMT versus 17.3% with chemotherapy. Common adverse events included anaemia, neutropenia, stomatitis and ocular toxicity, described as manageable. The antibody–drug conjugate targets Trop-2, which is highly expressed on endometrial cancer cells.
Results were presented at ESMO 2026 and published simultaneously in The Lancet. Dr Bhavana Pothuri (NYU Grossman School of Medicine) stated that the findings establish sac-TMT as a new standard after immunotherapy and will require guideline reassessment. Dr Michelle Lightfoot noted the particular relevance for aggressive subtypes that disproportionately affect Black patients, who have roughly double the mortality risk. The drug may also be relevant to other Trop-2-overexpressing tumours (lung, breast, ovary, gastrointestinal).
People with severe mental illness experienced more rapid increases in both weight and long-term blood sugar levels during the first three months after starting treatment with antipsychotic medication. This is shown by a study from Karolinska Institutet and University College London, published in The Lancet Psychiatry.
The researchers analysed electronic health records from nearly 97 000 people in England aged between 18 and 59 with severe mental illness. The aim was to investigate how weight and HbA1c, changed before and after treatment with second-generation antipsychotic medication was initiated.
During the first 90 days after treatment began, HbA1c increased by an average of 0.12mmol/mol per week and weight by 0.21kg per week. Before treatment, the corresponding increases were 0.01mmol/mol and 0.02kg per week, respectively.
After the first three months, the rate of change slowed. From day 91 and up to two years, HbA1c again increased by 0.01 mmol/mol per week, while weight increased by 0.03 kilograms per week.
The study is based entirely on health record data and shows how the values changed around the start of treatment, rather than reporting results from a randomised treatment study. In addition, only around a quarter of the participants had at least one recorded HbA1c measurement and just over three-quarters had at least one weight measurement.
Early follow-up may be important
“The results show that the greatest changes occur early after treatment is initiated. This suggests that both weight and HbA1c need to be monitored from the start of treatment and during the first three months, alongside what is clinically appropriate for each patient,” says Magnus Boman, professor at the Department of Medicine, Solna, Karolinska Institutet, and one of the authors of the study.
The changes differed between medications. The largest increases were seen with olanzapine treatment. Quetiapine, by contrast, was associated with weight gain but only a small change in HbA1c. The increases were generally greater among women.
People who already had prediabetes when treatment began also had a higher risk of developing type 2 diabetes. The estimated proportion who developed the disease within two years was 19 per cent in this group, compared with 3 per cent among people who had normal HbA1c levels at the outset.
An AI model created by researchers at King’s can detect signs of faulty DNA-repair mechanisms in ovarian cancer cells, potentially enabling a low-cost, widely accessible diagnostic tool.
By analysing tissue images, the model recognised tumours with defective DNA-repair mechanisms, which could help clinicians select treatments that exploit this vulnerability.
We are unlocking information hidden in microscopic images of cancer tissue that could transform how we match patients to treatments. By using AI to reveal defects in DNA repair, we could make precision cancer medicine faster, more affordable and accessible to more women with ovarian cancer, not just in the UK but around the world.
Dr Heba Sailem, Reader in Computational Pathology at King’s College London
The study focused on high-grade serous tubo-ovarian carcinoma (HGSOC). Homologous recombination deficiency (HRD), often arising from BRCA1/BRCA2 or related mutations, impairs DNA-damage repair and increases vulnerability to platinum chemotherapy and PARP inhibitors. HRD is therefore a useful biomarker for treatment selection, but current tests require genomic analysis that is costly and less accessible in resource-limited settings.
In the study, published in Nature Communications and led by Dr Heba Sailem, researchers developed HRDPath. Rather than sequencing DNA, HRDPath analyses high-resolution digital histopathology images. It was trained on images from patients with known genomic HRD status and correctly identified approximately 91% of HRD-positive cases, particularly when multiple images per patient were considered.
HRD-positive tumours showed subtle morphological differences, including rounder nuclei and denser cellular packing in certain regions. Defects in DNA repair therefore appear linked to tissue-architecture changes recognisable by AI but difficult to detect by conventional microscopy.
If validated in larger cohorts, HRDPath could use images already acquired for diagnosis, reducing reliance on expensive genomic testing and widening access to platinum and PARP-inhibitor selection for patients whose tumours are likely to benefit.
Researchers have identified two common drugs that may, when given together during pregnancy, prevent premature births.
The finding comes from a new, Stanford Medicine-led, artificial intelligence-powered technique for screening drugs to prevent early labour. It uses a comprehensive atlas of the immune system, accurate at cell-by-cell level, to create ‘digital twins’ of the immune systems of individual pregnant women for virtual drug testing.
The study, published online 21 October in Science Advances, builds on two decades of Stanford Medicine research on maternal immune shifts during pregnancy. When the immune clock of pregnancy runs too quickly, preterm labour can result.
After screening several possible treatments with the digital twin system, the researchers identified one drug combination that promises to markedly lower the risk of early labour. It shows sufficient potential that researchers are starting a clinical trial.
“We’re on the brink of having a real impact for the treatment of preterm birth, a global health problem that affects 10% of pregnancies worldwide,” said senior study author Dr Brice Gaudilliere. It has been decades since a new pharmacological intervention for preventing preterm birth.
The winning combination was aspirin and lansoprazole. Low-dose aspirin alone has a modest ability to prevent premature birth; lansoprazole is sometimes used in pregnancy for acid reflux.
“In the digital twin system, these two drugs in combination had a large effect on the delay of labour, 15 times higher than aspirin alone,” Gaudilliere said.
Modelling how the immune clock ticks
Although triggers of labour remain incompletely explained, Stanford Medicine research has shown immune signals play a key role. Early in pregnancy the maternal immune system adjusts to tolerate the fetus. Late in pregnancy, immune changes – including a switch toward pro-inflammatory signals – prepare the body for labour. When pro-inflammatory signals activate too soon, early labour can result.
The new system, SIMCO (simulated immune modelling of clinical outcomes), uses AI and machine-learning to integrate extensive data on immune-cell behaviour during pregnancy.
Researchers collected blood samples from pregnant women and exposed immune cells to multiple drugs. “We measured responses from a quarter of a billion cells, training the algorithm on a massive single-cell dataset,” Gaudilliere said.
“A digital twin has the prerequisite that you understand a biological system very well,” said co-lead author Dr Jakob Einhaus, postdoctoral scholar at Stanford Medicine. “The digital twin represents the complexity and connections in the immune system.”
Einhaus shares lead authorship with graduate students Peter Neidlinger and Olivier Fondeur, and with Dr Masaki Sato (now at the National Center for Child Health and Development, Tokyo).
Longitudinal data from 63 pregnancies were integrated to link cell-behaviour patterns to clinical outcomes and capture inter-patient variability. The algorithm predicts individual immune-cell responses to drugs and, from limited patient data (e.g., a small blood sample), the likely clinical effect on the immune clock of pregnancy.
“You’re making the prediction for one individual based on knowledge of millions of single cells from dozens of patients,” Einhaus said.
Common medications may delay delivery
After validating that SIMCO forecasts time to labour, the team evaluated nine pregnancy-safe drug regimens identified via a drug-repurposing pipeline developed by a group led by Dr Marina Sirota (University of California, San Francisco). Multiple digital-twin copies compared treated versus untreated scenarios for each individual.
The model strongly predicted that the aspirin–lansoprazole combination would delay labour. “Our findings suggest that salicylic acid [aspirin] and lansoprazole act synergistically … this synergy may enhance their immunomodulatory effect,” the investigators write.
Folic acid also delayed immunological progression toward labour. “We’re giving folic acid for spina bifida prevention, but maybe, unknowingly, we’re also helping the maternal immune system adapt to pregnancy,” Einhaus said.
The model indicated specific immune-signal changes: for the aspirin–lansoprazole combination, processes supporting pregnancy continuation are enhanced while those triggering labour are inhibited.
Because the model captures patient variation, it can identify likely responders and non-responders, potentially allowing smaller, more efficient trials restricted to predicted responders.
The combination delayed labour onset in an animal model of inflammatory pregnancy; FDA approval was obtained for a human trial.
South Africa’s public healthcare system finds itself caught between two incomplete revolutions – the democratic dream of a decentralised District Health System, and the march toward National Health Insurance. Health systems experts argue that structural changes won’t save a system that is scared stiff. The most urgent task facing the system, they say, is to help frontline doctors and nurses reimagine what is possible.
Part of what makes an octopus such a nimble, wily creature is that there’s more brain outside its head than in it.
In fact, about two-thirds of an octopus brain is spread across its eight tentacles, each one controlled by a tangle of neurons, its own mini-brain.
These semi-autonomous processing centres allow the octopus to control hundreds of individual suckers, which means tentacles can investigate crevices the eyes can’t see, and even learn from each other without much of the big brain’s help.
The suckers can sample the seafloor and decide whether what it finds is safe to eat, at which point a tentacle turns into a temporary elbow to bring the morsel to its beak.
This is the kind of intelligent and adaptable network that was envisioned for South Africa’s District Health System (DHS).
Where apartheid-era planning demanded top-down compliance, among others to enforce racial oppression and dispossession, the DHS, with its 52 districts and 240 sub-districts, promised to empower staff to respond to patients’ everyday realities, whether they live in a city or a rural village.
In reality, much of the system’s financial and administrative power has pooled at provincial head offices, trapping staff on the ground in the old command-and-control way of doing things.
As a result, frontline healthcare workers clock in every day with the task of executing more than 175 new clinical guidelines (that’s just since 2012) while also racing to meet sometimes out-of-touch performance targets. That is according to 2020 research conducted among district managers in the Eastern Cape, Western Cape, KwaZulu-Natal and Limpopo.
What’s more, layers of red tape added to catch corruption have not deterred politically connected syndicates. Research suggests it has only overwhelmed clinical managers and facility heads who are held accountable for patient experiences but can’t replace even the most basic equipment needed for care, such as a scale, without kicking off a months-long procurement effort.
Under these conditions, health workers have said repeatedly that the work of caring for people gives way to constant administrative self-preservation.
One Eastern Cape manager told researchers: “We will comply now and complain later. If you don’t comply, it means you are failing your district, or your sub-district, or your clinic or your people.”
Much like an octopus might become a danger to itself if it only believes its eyes, the health system’s top-down leadership style is damaging to those it employs and ultimately, to those it serves.
Fear and loathing in the platinum belt
It is possible to bring the original DHS dream to life by shaking the systemic fear out of daily operations.
Leading the charge is SALAD, the South African Learning Alliance for the District Health System.
Established in 2023, SALAD connects academic researchers across several South African universities (including UWC, UCT, NWU, and Stellenbosch) with national, provincial, and district health managers, clinicians, and non-profits to help tackle governance problems.
The team recently completed a pilot project in the North West province’s Rustenburg sub-district with more than 50 managers.
“We started at the sub-district level because if you can strengthen it there, you can learn a lot. There’s much less politics than at the top,” explains Beth Engelbrecht, the former Western Cape health department head and an adjunct professor at NWU and UCT.
Their initial analysis revealed staff were dealing with a mix of helpful and harmful experiences. Mistrust was among the more pervasive issues. “Even in regular meetings, it’s a toxic space,” Engelbrecht says. “If you don’t achieve your target, it’s like a ton of bricks coming down on you.”
To address all this, SALAD teamed up with the North West Systems Leadership Development Programme and the provincial health department to co-design a four-pronged plan.
The executive team got support to transform review meetings into learning spaces, managers attended an accredited short course, and everyone received mentoring, and real-time evaluation.
The most important part of the plan was that all the learning and assessment was happening in sub-district’s wards and daily meetings, using the real problems it faces. Workshops ran in short one or to day blocks spaced over four months, which also minimised disruption to clinic operations.
“When people see the effect of adopting different leadership processes in their relationships with colleagues, that builds its own desire to keep working differently,” explains Lucy Gilson, professor of Health Policy and Systems at UCT.
They gave staff explicit permission to stop expending energy on systemic issues (such as national budget cuts) they cannot alter, says Professor Helen Schneider, a professor of public health at UWC.
“Acknowledge the system-wide issues, but don’t kill yourself worrying about them,” she explains, “focus on what you can do, and then suddenly people discover a certain kind of agency, and they recognise they do have power.”
For instance, managers and clinicians can directly control in their immediate daily operations, how facility meetings are structured, staff schedules, internal communication tone, queue management, and creating psychological safety within their immediate team.
Outside their own facility, they can build strategic alliances, Schneider says, by navigating local trade union relations or engaging clinic committees, negotiating with sub-district support units, or coordinating across public-private boundaries.
The pilot is complete, and the SALAD team is still in touch with health authorities in the North West to figure out how to scale the programme.
This will take time, Gilson says, because leadership development is not written into provincial annual performance plans. Although it’s a frontline change that’s needed, backing from the top is still crucial.
Engelbrecht and Gilson met with a number of national oversight bodies (including the Department of Planning, Monitoring and Evaluation, the Department of Public Service and Administration, and the National Department of Health) to figure out how leadership was being managed on a national level.
“All three of those national bodies said leadership is critical, but all of them confirmed that leadership development is nowhere in any plan an explicit, funded priority.”
Unlike most other national or provincial departments, the Western Cape has embedded leadership development into its structures, budgets and working practices.
Through the Partnership for Health Leadership and Management Capacity Development (PAHLM), for instance, the Western Cape health department and three universities developed a leadership competency framework and a leadership behaviours charter. The framework was tested and developed through two rounds of workshops involving more than 800 public health-system managers and was commissioned and approved by the provincial health department.
The case of the disappearing paramedic examiners
Years of fear and resentment can crystallise in unexpected ways.
In KwaZulu-Natal, a meticulously planned paramedic examination was nearly derailed when a number of paramedic educators and examiners booked off sick at the same time, Caleb Wang tells those gathered for a SALAD online seminar.
Wang, who coordinates in-service training for clinical employees in KZN, is a paramedic by training. Paramedics are an important link connecting household emergencies, clinics, and district hospitals, though training colleges are often regional or provincial facilities.
These assessments are labour intensive, Wang says, and they require large panels of examiners for clinical skills, oral boards, and simulation exercises. It’s a high-stakes situation for students too, since failing means they can’t progress, get promoted or qualify for salary increases.
The exams continued with fewer examiners for the sake of the students, but the sudden changes created a high-pressure environment for everyone involved.
At first, Wang and his colleagues suspected a stomach bug might be behind the chaos, but upon closer inspection, a stranger reality emerged; the examiners were afraid to attend the assessment, and afraid of saying why.
As it turned out, course coordinators leading the different academic tracks were locked in interpersonal feuds. Educators felt helping to assess a rival coordinator’s exam could be seen as a betrayal. Unsure of how to raise such worries without also facing reprisals, people instead took sick leave in self-defence.
Such a fraught emotional landscape can’t be fixed with rules and reprimands. Though managers started to track sick leave application trends for signs of a coming crisis, the underlying issues could only be remedied using a more collaborative, relational style of leadership.
Wang focussed directly on the relationships between co-ordinators. After they had completed a series of communication exercises, management also instituted regular meetings where structured, open dialogue was encouraged.
Topics previously taboo in administrative settings (feelings, assumptions, perceptions, and hidden dynamics) were reframed as important operational intel.
The formerly warring co-ordinators aren’t personal friends today, Wang says, but the approach succeeded in breaking down the seemingly intractable silos and has restored cooperation across the different academic components.
These days, paramedic examinations go off without a hitch.
People who have the confidence to speak up, admit mistakes, or take calculated clinical risks are much better at saving lives and preventing hospital infections than those who keep their head down out of fear.
Nomlindo Makubalo, a paediatrician in an Eastern Cape district clinical specialist team, has seen this first-hand.
Speaking during a webinar on psychological safety in the DHS, she shares an anonymised story of a junior medical officer and ward nurses at a cash-strapped district hospital who were confronted with a critically ill, ventilated 11-month-old infant.
The baby urgently needed intensive care but there were no available ICU beds in the regional or central referral complexes. The rural ward nurses had no formal ICU ventilation training.
In a traditional, fear-based culture, the local team might have panicked and passed responsibility upward or allowed the infant to deteriorate while waiting for official transport sign-off.
But Makubalo and the district clinical specialist team had intentionally built a relationship of psychological safety, so the junior doctor felt safe to call her directly.
She reassured the team and provided real-time, telephonic clinical supervision for two consecutive nights.
The hospital management authorised additional nursing support to relieve ward strain. Supported by this protective leadership umbrella, the frontline team safely ventilated the infant locally for 48 hours until an ICU bed opened.
The baby was transferred and made a complete recovery.
Makubalo says: “Psychological safety and trust translate directly into quality care. When people know you have their back, they will do everything to save a life.”
The physics of success versus failure
In the Western Cape, the provincial government explicitly measures the energy all civil servants expend that never reaches the public.
In a healthcare setting, patients might lose out because health workers’ energy is spent navigating internal friction, administrative hierarchies and coping with interpersonal conflict.
The technical term used across the province is “organisational entropy”. Very loosely related to the scientific concept of entropy, it measures the percentage of total energy within an institution consumed by unproductive work.
In the proprietary tool used by the Western Cape government, called The Barrett Model®, wasted energy is measured using a survey. It offers a list of personal and organisational values and asks staff to choose 10 personal values, 10 values that describe the current culture of the organisation, and 10 organisational values they’d like to see in the future.
The cultural entropy score comes from the percentage of current organisational values staff pick that the Barrett Model classifies as “limiting,” such as conflict, friction, and frustration.
At the Retreat Community Health Centre, a facility that provides 24-hour emergency and maternity care in Cape Town, researchers found staff operated in a pervasive climate of fear. Their baseline survey suggested that staff viewed management as administrative police designed to catch staff making mistakes, and as a result, communication broke down into departmental silos.
The three key facility leaders, the facility manager, family physician, and nursing manager underwent leadership assessments and six months of individual coaching. They engaged in weekly reflective learning sets, mapping out communication flows, and examining how their own management behaviours generated fear.
The results were transformative.
When researchers followed up 18 months later, limiting values had dropped out of the top 10 current organisational values, although they still represented 13% of all values selected (down from 33%). In their place emerged positive, unifying values: caring, open communication, teamwork, respect, fairness, and accountability.
This phenomenon is not confined to isolated research sites. The Western Cape Department of Health and Wellness formally tracked cultural entropy across its entire workforce as an official performance metric, achieving a department-wide entropy reduction from 23% to 20.9% between 2013 and 2016.
This systematic drop in friction directly correlated with improved employee retention, stronger teamwork, and smoother service delivery across health districts.
The latest annual report puts cultural entropy cross the provincial public health system at 16%.
The province also tracks leadership skills on an individual, team, and system level.
Tendani Mabuda, who leads the provincial health department’s People’s Development team, argues the proof of the value of strong leadership can be found in the department’s eight year run of consecutive unqualified audits.
“Leadership development cannot alone resolve structural failures or challenges, but it enables managers to be agile and cope with the environment they are facing,” he says.
‘Trust is not a luxury’
For three decades, the unwritten rule within South Africa’s public sector clinics and hospitals has been to hide errors, follow flawed directives to the letter, and brace for new instructions from headquarters.
Stamping out this culture of fear in favour of psychological safety will be crucial to the success of South Africa’s next big healthcare revolution, the National Health Insurance (NHI) scheme.
The scheme, which currently faces about a dozen legal challenges, will change the way resources and healthcare services are pooled and purchased.
At the moment, most provincial health funding comes from nationally raised revenue transferred by National Treasury to provincial governments. The amount each province gets is determined by the provincial equitable share equation. The formula determines each province’s share using factors such as population, poverty and demand for health and education services. Provincial governments then decide how much of their budgets to allocate to their health departments. Separately, the national health department administers conditional grants for specified health services and programmes.
Under the proposed new system, funding would shift from this passive approach, where facilities receive budgets shaped by previous allocations to cover costs such as salaries and supplies, to strategic purchasing.
This means actively deciding which services a population needs, which providers should deliver them and how to pay those providers, with funding decisions guided by health needs and provider performance rather than simply historical spending.
For primary healthcare, contracting units would organise networks of public clinics, district hospitals and participating private providers to serve people within a sub-district, with the NHI Fund purchasing services through these arrangements.
These are hardware updates but, as multiple governance studies have shown, a hardware solution won’t fix a software problem.
And strategic purchasing will require sophisticated cultural software and strong leadership from district and sub-district managers with the ability to build trust, negotiate, manage networks that combine public primary care clinics, district hospitals, private doctors, nonprofits, and municipal health services.
At the heart of all of this, is trust between people, explained health economics professor Susan Cleary during a June webinar.
“You don’t get good quality results if you don’t have good quality relationships, they’re part of performance, and trust is not a luxury.”
Incidentally, an octopus can overcome incredible barriers once it decides to seek safety.
In 2016, staff at the Napier Aquarium in New Zealand arrived at work to find that Inky, one of its star inhabitants, had escaped. Finding the glass lid of his tank left slightly ajar after routine maintenance, he slipped out overnight, navigated a 50-metre drainpipe, and disappeared into the sea.
In the movie “The Matrix”, seeing two black cats was a sign of déjà vu. Photo by Viktor Talashuk on Unsplash
In the realm of human cognition, few phenomena captivate and mystify as much as the workings of memory. For centuries, researchers have dedicated themselves to understanding the intricate mechanisms behind the ability to retain and retrieve information.
Colorado State University psychology Professor Anne Cleary is one of them. She is a leading expert in the field of metacognition and was one of the first to shed light on enigmatic experiences such as déjà vu and the ‘tip-of-the-tongue’ phenomenon through her research on recognition without identification.
These strange but widely experienced phenomena are intriguing aspects of human memory and cognition.
Cleary gathered much of her data using ‘list learning’, where participants are given a list of words to study and are then tested by being asked to recall whether or not fragments of words were in the original list.
Recognition without identification was the finding that people could still recognise which word fragments came from studied words and which did not, even if they couldn’t identify the word it came from. This idea is a general phenomenon that can be extended to other stimuli, including pictures, scenes, and faces.
Similarly, Cleary used the Sims video game to simulate déjà vu experiences. In Sims, you can design unique layouts of rooms, which Cleary did, creating an aquarium that has the same layout as a reception area, for example. This created spatial similarities, which Cleary has formerly shown to cause a déjà vu experience in participants.
With the help of virtual reality headsets and the Sims video game, Cleary was able to send a person into a room and then later a spatially similar room, causing them to sometimes feel a sensation of déjà vu. This research led Cleary and others in the research community to empirically support a hypothesis for a phenomenon that was formerly believed to be in the realm of pseudoscience. Instead of déjà vu being a paranormal phenomenon, Cleary discovered that déjà vu is experienced in real-life scenarios when there are spatial similarities in our surroundings to somewhere someone really has been before.
In a recent study, Cleary explored the potential of smartwatches for augmenting learning beyond classroom environments. Through a series of five experiments, it was found that when participants received review questions via smartwatches after reading scientific passages, they exhibited improved retention of information and reduced their likelihood of forgetting after a two-day interval.
The delivery of the information also proved to be important. A test question popping up first, followed by its answer, was more beneficial than a mere restatement of the initial information.
The study revealed that the beneficial effect of smartwatch prompts on retention remained consistent regardless of participants’ activities, such as reading magazines, watching Netflix episodes, or engaging with their smartphones during the prompting process. This research highlights the strategic potential of utilising technology and Cleary’s commitment to staying in the vanguard of scientific exploration.
By exploring how individuals discern familiar stimuli and unravelling the intricacies of déjà vu experiences, Cleary has made groundbreaking contributions to the field of metacognition. She said her tactics to test these theories are a “unique paradigm and unique methodology that has never really been a mainstream approach.”
Cleary applies procedures that are tested in other studies but has been the first to do so in relation to recognition without identification and déjà vu. “These phenomena offer insights into memory’s inner workings,” Cleary said. “A purpose of this sense may be to direct our attention inward toward a search of memory to try to seek out the memory. Déjà vu, tip of the tongue, and recognition without identification may be giving us a glimpse of how our attentional focus is modulated. They refocus our attention toward our memories.”
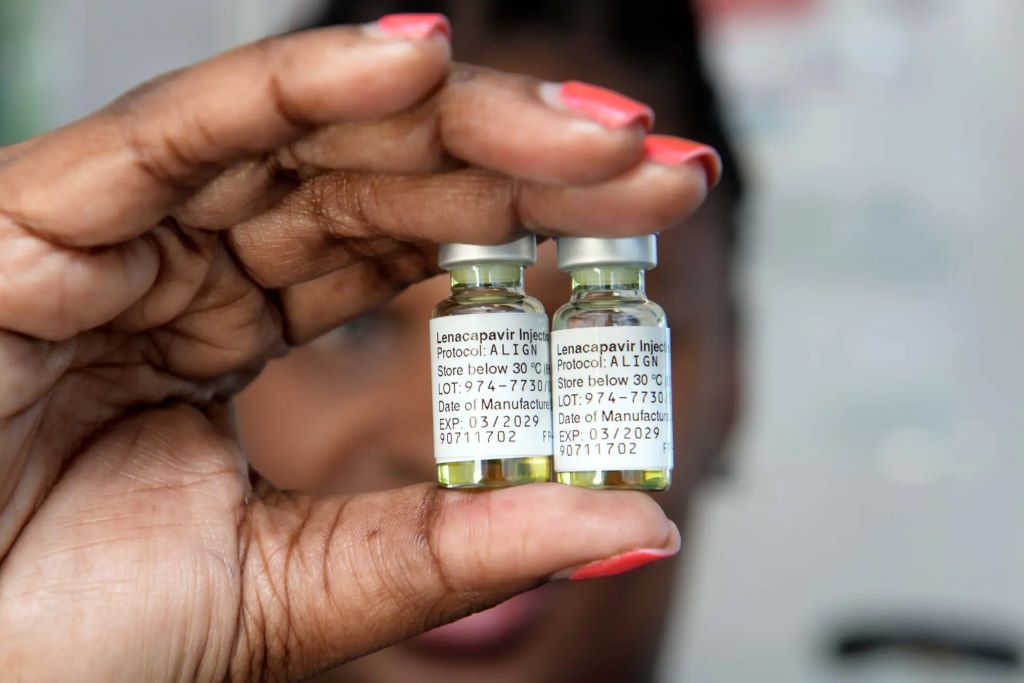
Lenacapavir is administered via two injections of 1.5ml each in the buttocks, thigh, abdomen or upper arm. (Photo: Nasief Manie/Spotlight)
South Africa’s rollout of lenacapavir, a six-monthly HIV prevention injection, requires nurses to learn, adapt and find ways to make it work for patients.
After 26 years in nursing, Sister Keitumetse “Tumi” Senokwane still had something new to learn about giving injections.
The six-monthly HIV-prevention jab, lenacapavir, often referred to as just LEN, presented a unique challenge.
“You know, lenacapavir is different. As much as I’ve got experience with injections, the needle size is different from the subcutaneous (beneath the skin) injections we are used to, and the solution is quite thick,” says Senokwane. “Because we were not used to it, the practical training helped us to get used to it.” She practised withdrawing the yellow liquid, using cooking oil as a stand-in.
That kind of preparation matters because lenacapavir for HIV prevention is being introduced at a time when South Africa still has a substantial need for effective HIV prevention options. The country had an estimated 140 000 new HIV infections in 2025. Modelling suggests that scaling up lenacapavir to 1.4 million to 2.1 million initiations a year by 2030 could avert an average of 32 200 to 51 700 infections annually.
But realising lenacapavir’s potential will depend on more than getting the injection into clinics. It also requires nurses to administer it correctly, answer patients’ questions, and adapt services to their needs.
Getting to grips with lenacapavir
Senokwane is a professional nurse and site manager at Maria Rantho Community Health Centre and Phedisong 1 Clinic in Tshwane, which are participating in the Wits RHI Len4PrEP study.
“LEN4PrEP is an implementation research study, so looking at how we can deliver the product in a real-world setting,” says study investigator Dr Catherine Martin.
The researchers recruited 1 544 participants between November 2025 and June 2026, with follow-up continuing until June 2027. The study began several months before South Africa’s national rollout of lenacapavir on 5 June 2026, when the injection was launched at 360 public health facilities across six provinces.
By 8 October, 76 922 people had initiated LEN nationally, including 36 733 in 133 facilities in Gauteng, according to health department spokesperson Foster Mohale.
For Senokwane and her colleagues, administering lenacapavir meant learning a new HIV prevention method.
Nurses first had to complete a compulsory Nurse-Initiated Management of Antiretroviral Therapy (NIMART) course, which provides a theoretical foundation for managing HIV and antiretroviral treatment. This was followed by practical training in preparing and administering LEN.
Training also covered eligibility, side effects, HIV testing and counselling, with videos and clinical mentorship providing additional support.
Mohale says feedback from early-rollout clinics, nurses and patients would help the department refine its training and guidelines.
At the study clinics, nurses also had to adapt the service to patients’ needs and fit the new injection method into existing care.
The one-stop shop
The Department of Health’s lenacapavir implementation guidelines emphasise counselling clients on their HIV prevention options and helping them choose a method that suits their needs.
At the study clinics, nurses incorporated LEN into existing sexual and reproductive health services, allowing clients to access HIV prevention alongside services such as family planning and STI screening and treatment during a single visit.
“You will get all services in one room like a one-stop shop,” says Senokwane.
“Maybe you are here for lenacapavir, but we also check whether you are on a family planning method. If not, we will give you information and provide a family planning method for you, where we screen you for STIs, and then if you’ve got some infections, we also treat you,” she says.
The LEN4PrEP study also used a mobile clinic to bring HIV prevention and sexual and reproductive health services to young people in their communities.
“So many of our clients already know us. They know how we treat them and the quality of service we provide,” she says.
Initial LEN consultations took longer as nurses explained the available prevention methods and how soon each would offer protection against HIV.
“We give you the information and explain how each method works, how long until it is effective. Participants would like to know when they are going to be protected from HIV if they take this specific method,” says Senokwane.
At the Southern African HIV Clinicians Society’s Long-Acting Antiretroviral Treatment Conference in Johannesburg in September, Wits RHI’s Professor Saiqa Mullick, Director of Implementation Science, shared early findings from the LEN4PrEP study.
She reported that convenience was a major reason participants opted for the lenacapavir jab. They valued not having to take a daily pill or make frequent clinic visits, while the injection offered greater privacy for some. It also attracted people new to PrEP, alongside existing users seeking a method that better suited their lives.
Pre-exposure prophylaxis, or PrEP, refers to antiretroviral medicines taken to prevent HIV infection. When used as prescribed, oral PrEP has been shown to reduce the risk of HIV infection from sex. For several years now, HIV prevention tablets have been widely available in South Africa’s public healthcare system, although uptake has been somewhat muted with only around 350 000 people taking the tablets in mid-2025, according to estimates from Thembisa, the leading mathematical model of HIV in South Africa.
Of the 1 538 participants whose method choices were reported, 85.8% selected the lenacapavir shot, compared with 13.7% who selected the prevention pills and 0.5% who chose not to use PrEP.
“People want options that fit into their lives,” Mullick told delegates.
Sticking the landing
Patients could also choose where in the body to receive the injections: the upper arm, buttocks, abdomen or thigh.
Among the 1 319 participants who started LEN, Mullick says approximately 50% of women preferred the buttocks, while about 51% of men preferred the upper arm. The ongoing study will explore both men and women’s reasons for injection-site preferences.
For nurses, the challenge was to administer the injections correctly while making the process as efficient as possible.
Lenacapavir requires getting two injections during the same visit. Patients also need to take two lenacapavir tablets on the day of their first injections, followed by another two tablets 24 hours later. These tablets form part of the initiation dose before they continue with injections every six months.
Senokwane says a Wits RHI pharmacist taught her a way to withdraw the solution while keeping the vial upright, rather than turning it upside down.
“That was the best method for me because it worked faster,” says Senokwane.
“So with that method, you pull up 1.5 ml of air into the syringe and inject the needle into the vial. [The syringe] draws at least one ml by itself, without assistance, which allows the nurse to multitask. And then you also save time because you are able to prepare two injections at the same time,” she says.
But efficiency was only part of the learning curve. Because lenacapavir is a thick solution, it needs to be injected slowly.
“I wish I knew that you can’t inject it fast,” Senokwane said. The thick solution required a slower injection technique to reduce leakage.
Slow administration was included in nurses’ initial training, but its importance in minimising leakage was reinforced as they gained practical experience and shared lessons with colleagues.
Dr Martin says that in the early stages of implementation, nurses consulted experts, including those involved in clinical trials, on how to manage leakage at the injection site.
“As local experience grew, they learnt to reassure participants that minor leakage could occur and to assess more substantial leakage to determine whether further follow-up was needed.”
Answering patient concerns
Patients were also concerned about the side effects of lenacapavir.
Lumps or small nodules at the injection site are a common side effect of lenacapavir. In one clinical trial, which included 2 140 participants who received lenacapavir, roughly 64% developed subcutaneous nodules at the injection site.
“Most of the clients were curious about the nodules. They were worried about whether they would be able to continue with their normal activities, especially those who wanted to exercise,” says Senokwane.
“They wanted to know how long the nodule would last and whether they would get another one when they came back for their second injection. Usually, by the time they came for their next injection, the nodule would have disappeared.”
Others were worried about the pain.
“We advise them that if the nodule comes with pain, just use a warm or cold compress, or you can even use a painkiller,” explains Senokwane.
Mullick says addressing these concerns and discussing them with clients in advance is part of making the injection work for patients in practice.
“This might seem something relatively small, but from an implementation perspective, it contributes considerably to the person receiving the product.”
Making it work in real time
As nurses became more familiar with administering lenacapavir, the clinics also refined how they moved patients through the service, from the initial consultation to receiving the injection.
Patients first met a navigator who explained the available services. After registration, an HIV test and a check of their vital signs, they saw the research nurse.
The clinics later began using the waiting time more effectively, with navigators introducing patients to PrEP and other services before their consultations.
Initially, appointments could take about an hour and a half. As the clinics refined their workflow and nurses became more familiar with the process, Senokwane says visits took about an hour or less.
“Training manuals and guidelines provide all the theoretical knowledge and framework for delivering lenacapavir,” Martin explains.
“But, that real-world experience gives you a little bit more insight into things that you can only learn by working with clients.”
Each one teach one
Senokwane’s experience eventually helped her become a mentor to other nurses.
“The mentorship was really very important. We’ve got support from our pharmacist, and then we’ve got support from our sub-investigator at site. So everyone needs to be mentored until you are really 100% sure that you can do it on your own,” she says.
When non-research nurses started providing lenacapavir in June at the study sites, she went there to demonstrate the technique. Some nurses she had trained also helped their colleagues.
“They were always grateful that we really helped them. So they really appreciated it. The more you practice, the better you become,” says Senokwane.
Lessons from the clinics also informed training. Videos demonstrating how to prepare and administer lenacapavir were produced by Wits RHI, alongside webinars. Martin says the videos would be incorporated into future training.
“It’s always helpful to see something in practice. With a new product, although it can be explained theoretically, it is helpful to actually see a provider and a client interaction,” she says.
JOHANNESBURG, 23 October 2026 – The South African National Blood Service (SANBS) is calling on eligible South Africans to donate blood as national stocks decline to 3.9 days’ cover, below the five-day minimum target. SANBS needs 3,500 units of blood every day to meet patient demand, but current collections are falling short.
With the festive season fast approaching, the declining supply raises concerns about SANBS’ ability to maintain adequate stocks during a period when demand remains high. Every day, patients rely on blood transfusions for life-saving surgery, complications during childbirth, cancer treatment and emergency care which highlights the need for a reliable blood supply.
Some regions are facing even greater pressure, with blood stocks below three days’ cover. Group O blood is particularly important in emergencies when there may be limited time to establish a patient’s blood group before a transfusion is needed.
“The current blood supply is under significant pressure, and we need the public’s support to rebuild stocks ahead of the festive season. We are appealing to active donors, lapsed donors and eligible South Africans who have never donated before to make time to give blood. Every donation counts and can help save lives,” says Monique Schreiner, Senior Manager: Donor Relations at SANBS.
SANBS encourages eligible donors to make blood donation a priority rather than postponing it until later in the year. Whether preparing for a holiday or returning to their usual routine, donors can help ensure that blood is available for patients who need it.
For more information or to find your nearest donor centre or mobile blood drive, contact SANBS on 0800 11 90 31 or visit www.sanbs.org.za
Bacillus Calmette-Guerin (BCG), a vaccine widely used to prevent tuberculosis and treat bladder cancer may also have properties that reduce the risk for dementia, according to new findings in a study of mice. BCG is a live, weakened vaccine made from an altered strain of the bacterium Mycobacterium bovis. The findings from this study, which was led by a team of Johns Hopkins Medicine researchers and funded by the National Institutes of Health, published today in Science Advances.
The researchers found that mice genetically engineered to have biological symptoms of dementia and that received the BCG vaccine were less likely to show hallmark signs of the disease, such as neurofibrillary (tau) tangles in the brain, sustained immune cell activation and memory loss compared to mice that received no vaccine.
“We’re hard at work trying to understand the detailed mechanism for how it works, but this research points to early clues that aspects of trained immunity are likely driving this response,” says William Bishai, MD, PhD, co-director of the Johns Hopkins Center for Tuberculosis Research.
Bishai explains that trained immunity refers to the ability of mammals’ innate immune system cells to take on an expanded role. Following an initial stimulus, innate immune cells, often monocytes and macrophages, learn how to identify and respond to future threats that are different from the first. (Typically, other immune system cells, like T cells, take on this type of adaptive and learned response.)
In this case, Bishai believes that myeloid cells – innate immune cells – in the central nervous system and brain are using information from BCG to recognise and help the body respond to the formation of plaques and tangles characteristic of Alzheimer’s disease and related dementias.
For this new study, Bishai and the researchers created a controlled experiment with mice with symptoms of dementia, specifically marked by tau pathology or a clumping of tau proteins in the brain representing late stages of the disease.
They divided mice into those that received the BCG vaccine and those that received a saline injection. An additional comparison group included age-matched mice that did not have dementia and that also received the saline injection.Mice in the BCG treatment group received the vaccine at 3 months of age. Multiple assessments, based on brain imaging, memory recall (through an object recognition test) and indicators of disease, including neuroinflammation and the expression of genes linked to Alzheimer’s disease, were conducted eight to nine months later.
The researchers found that mice who received BCG were about five times more likely to have signs of reduced tau deposits in their brain. They were also four times less likely to have markers of sustained inflammation – signalling that their immune cells had already likely responded to tau by clearing out some of the tangles and had created a stable or protective immune response.
Untreated mice also showed activation of 716 genes connected to Alzheimer’s disease, cell death and neuroinflammation, and BCG normalised all but nine of these. Compared to untreated mice, the mice who received BCG were less likely to have signs of brain atrophy and also more likely to live longer and perform better on tasks related to remembering and identifying objects.
BCG seems to be reducing the degree of hyperinflammation in the brain – which is a good thing – and it may be doing it through a trained immune cell mechanism,” says Bishai. “There are a number of other characteristics of trained immunity that we are studying in the lab now.”
This research, Bishai says, is believed to be the first to study BCG and dementia in mouse models with tau pathology (specifically showing how immune cells may play a role in clearing neurofibrillary tangles). Others have found similar findings with BCG and improved cognition in amyloid mouse models – which represent earlier stages of the disease marked by plaque formation.
These findings also follow observational studies in humans – those not designed to show cause and effect – that have linked off-target effects of vaccines to a reduced incidence of dementia.
Several previous studies, which are cited in the paper, have found that BCG used as an immunotherapy for non-muscle invasive bladder cancer was linked to a 12% to 78% reduced risk of dementia throughout a three- to 15-year period. The shingles vaccine has also been linked to a 20% reduced incidence of dementia.
A first-of-its-kind clinical trial has launched in the UK, which could cut years from the search for treatments that work for people with Alzheimer’s disease.
The national trial is called AD-SMART (Alzheimer’s disease Systematic Multi-arm Adaptive Randomised Trial). It is led by the UK Dementia Research Institute (UK DRI) and Alzheimer’s Research UK (ARUK), in partnership with the National Institute for Health and Care Research, the Medical Research Council (MRC) and Health Data Research UK, with ongoing UK government funding.
It will test multiple drugs simultaneously, starting with two repurposed medicines already used to treat type 2 diabetes and attention deficit hyperactivity disorder. Groups of participants will each begin treatment with a different drug. The study will examine whether these medicines can lessen symptoms such as memory and thinking problems, and help people maintain their quality of life as the disease progresses. Testing drugs that are already approved to treat other conditions and known to be safe means that, if successful, treatments can reach people living with Alzheimer’s much faster than a medicine developed from scratch. As well as repurposed drugs, the trial is designed to test new potential treatments coming through the research pipeline.
Heather Ransome, 67, from the Isle of Wight, was diagnosed with Alzheimer’s in 2024. She said: “Before my diagnosis, my partner and I were going on lots of cruises and coach holidays, enjoying retirement together. We still enjoy life, but I’m worried about my condition getting worse. I’m not the sort of person who gets upset, but being told you have Alzheimer’s is quite upsetting. There weren’t many treatment options available, and the one drug I was offered has been around for many years. Getting involved with AD-SMART has given me some hope for the future. It’s not too taxing, just some extra tablets to take every day. I don’t know whether I’m being given the active treatment, but if it helps me, or helps others in future, that feels positive. I would encourage anyone who thinks they might be eligible to sign up and speak to the team.”
The Prime Minister Andy Burnham said: “I know how it feels to lose a loved one to dementia and have seen first-hand the devastating impact this illness has on families. That’s why I’m proud to see this trial being launched in the UK, so that cutting edge treatments can reach patients here as soon as possible. I have made dementia research a national priority. I want Britain to be the leading nation, making the breakthroughs that change people’s lives.”
AD-SMART is a multi-arm, multi-stage platform trial. Several drugs are tested at the same time, and the results compared with one group of participants taking a dummy drug (placebo). This means more people receive an active treatment than would in a traditional trial. Results are checked at regular stages throughout the trial and any drug that isn’t showing benefit can be dropped quickly, with new drugs added in its place. Overall, this means fewer participants end up receiving ineffective drugs. Testing several drugs against one shared placebo group means that compared with a traditional trial, the time to evaluate treatments can be more than halved, which also reduces costs.
The trial is being delivered by a team at Imperial College London, the UCL Innovative Clinical Trials Unit and the MRC Centre of Research Excellence in Clinical Trial Innovation (UCL), the University of Oxford, and Dementias Platform UK. Leading Alzheimer’s experts from across the UK will be providing support.
Chief Investigator, Dr Paresh Malhotra, Group Leader at the UK Dementia Research Institute (UK DRI) Centre for Care Research and Technology at Imperial College London, said: “For too long, Alzheimer’s research has moved at the pace of one drug, one trial, one answer, sometimes taking a decade or more before we know if we’ve found something that works. We are applying advances from cancer and other conditions to accelerate testing of treatments for people with Alzheimer’s disease. The way AD-SMART is set up means we’re testing several treatments at the same time, and those that don’t show promise can be quickly stopped. Then we can start testing something else. That’s the best way to get effective treatments to patients as quickly as we can.”
The first trial participants have been recruited at Cambridgeshire and Peterborough NHS Foundation Trust and Surrey and Borders Partnership NHS Foundation Trust. Sites based at Imperial College Healthcare NHS Trust, Edinburgh and Southampton are also now open. Up to 20 NHS sites are expected to open across the UK over the next 12 to 18 months and more than 30 are planned overall. Researchers aim to recruit 1,200 participants across the UK to test these first two drugs. They expect to finish evaluating the first drugs in 2030, in around four years’ time. During this initial four-year period, the team expect additional drugs to be added into the trial for testing.
AD-SMART is the first trial of this kind for people living with Alzheimer’s, but the model has already proven itself in the UK. MND-SMART, a similar platform trial for motor neuron disease, also led by the UK DRI, concluded that its first drugs tested were ineffective in just over three years. This process would normally take at least eight years. The trial has now moved on to testing other promising drugs.
MRC Executive Chair Dr Patrick Chinnery said: “Innovative clinical trials like AD-SMART are crucial to accelerating progress in health research, generating robust evidence at pace and supporting faster translation of research into patient benefit. This is particularly important in dementia and Alzheimer’s disease research, where there is an urgent clinical need for new therapeutic options. This UK DRI-led trial draws on expertise across the MRC’s institutes, the MRC Centre of Research Excellence in Clinical Trial Innovation, and the Dementia Trials Accelerator, which speeds up recruitment into clinical trials, to evaluate promising interventions more rapidly, and hopefully bring new treatment options to the people who need them.”
Science Minister, Chris McDonald MP said: “Dementia has a devastating impact on millions of people, both for those living with the illness and for their friends and families. There is still so much we need to learn about how this disease works so we can then find the best ways to treat it, but this programme can help us bridge the gap. AD-SMART will help to uncover potential new treatments faster by exploring how existing drugs might be used to treat dementia, giving hope that we might be able to find ways to improve patients’ quality of life in the future.”