Tag: Spotlight

Angst as South Africa’s HIV & TB Healthcare Worker Hotline Goes Offline

South Africa’s HIV & TB Healthcare Worker Hotline service is run by the University of Cape Town’s Medicines Information Centre. (Photo: Unsplash)

By Adiel Ismail for Spotlight

A crucial hotline run for nearly 20 years from the slopes of Devil’s Peak in Cape Town for healthcare workers anywhere in South Africa, from the country’s busiest urban hospitals to far flung resource strained rural clinics, has been suspended due to a lack of funding.

Around two decades ago when Dr Laurel Giddy first started working with people living with HIV, they were already very ill. She remembers five of her patients that she put on antiretroviral treatment dying. She says it was heartbreaking.

“I was just at sea. I felt like I was in the deep ocean, and it was very difficult to get help. There just wasn’t a lot of knowledge going around at the time,” she tells Spotlight. “Getting trapped in an environment where you’re not sure what you’re doing and where people die and you feel unsupported is just demoralising.”

This is the kind of high-stakes situation that the team at the South African National HIV & TB Healthcare Worker Hotline responded to when South Africa’s antiretroviral rollout started gathering steam after the end of state-sponsored AIDS denialism.

And with their help, the milestones at Giddy’s HIV treatment clinic that she help set up at the Knysna Provincial Hospital followed: first 100 people on HIV medicine and a couple of years later, 5 000.

“I’m getting quite emotional, but they helped our programme just fly,” says Giddy.

18 years of national support

The free hotline has to date answered more than 86 000 queries from doctors, nurses and pharmacists in public and private healthcare facilities in all corners of the country. The service is run by the University of Cape Town’s Medicines Information Centre.

“Over 18 years, the hotline has provided trusted, evidence-based clinical support to healthcare workers across South Africa, contributing significantly to patient care and strengthening health system capacity,” Annoesjka Swart, manager of the Medicines Information Centre, tells Spotlight.

But now the phone lines have fallen silent.

“Regrettably, we no longer have the financial resources required to sustain the service, having received no funding support for the hotline since April 2025,” she says. “Although we submitted a bid for a tender that was released on 1 April 2026, to our knowledge the bid has not yet been awarded.”

SA’s troubled twins

The suspension of a free hotline service dedicated to providing clinical advice for the management of HIV and TB is particularly worrying in South Africa where the two diseases remain deeply intertwined public health crises.

South Africa has one of the highest TB incidence rates in the world and the largest HIV epidemic in any single country. TB and HIV is among South Africa’s leading causes of death. Each is estimated to claim over 50 000 lives per year, although there is substantial overlap between the two since TB is the top killer of people with HIV.

The connection between HIV and TB is relatively straightforward. People with untreated HIV infection typically suffer severe damage to their immune systems, which dramatically increases the risk of falling ill with TB and dying of it.

One study showed how usage of the hotline by nurses increased dramatically in its first few years. Such support for nurses is particularly important in the context of the health department’s decision to authorise specially trained nurses to diagnose HIV and prescribe antiretroviral medicines in terms of its NIMART (nurse-initiated Management of Antiretroviral Therapy) programme. NIMART has been lauded as one of the reasons why South Africa’s HIV treatment programme could grow as fast as it did in the 2010s. Prior to NIMART, only medical doctors could prescribe antiretrovirals.

The team behind the hotline has also been involved with research – such as this study on healthcare workers’ knowledge of interactions between a widely used antiretroviral and other medicines.

How the hotline works

Swart explains that queries received by phone, e-mail, WhatsApp and ‘please call me’ go directly to one of the specially trained information pharmacists, who record all the details in a password-protected database. “Details recorded include caller demographics – profession, sector, facility, province – and relevant patient details – antiretroviral therapy history, medical history, laboratory results and other conditions/treatment and the question.”

The pharmacist then researches the query using up-to-date, evidence-based references and, where necessary, consults an expert clinician. “All references used and clinician input is recorded on the database. Most queries are answered on the same day,” says Swart.

As the patient of a healthcare worker who calls the hotline, she says that patient can be assured that the best possible treatment has been discussed with a multi-disciplinary team, where needed, without having to leave their local clinic.

Swart adds that hotline pharmacists have access to many clinical experts, based at the University of Cape Town’s medical school, Groote Schuur Hospital, Red Cross Children’s Hospital and more.

“Up to the end of August 2026, the hotline had answered 86 672 queries,” she says. Over the last five years from 2020 to 2025, Swart says the hotline managed about 380 to 430 HIV/TB queries per month, around 18 to 20 healthcare worker consultations every working day, or an estimated 90 to 100 consultations every week.

Most queries are received from the Western Cape, Eastern Cape, Gauteng, and KwaZulu-Natal. “Over the past 5 years, we’ve seen a steady increase in calls from Mpumalanga – 347 in 2021 to 571 in 2025 – and Limpopo – from 90 in 2021 to 201 in 2025,” she says.

Practical resources

While the primary focus of the hotline is to provide clinical support to healthcare workers across South Africa, Swart says her team also develops and designs easy-to-use posters, booklets and tools based on national guidelines.

There is also an associated SA HIV/TB Hotline app available on Google Play and the Apple App Store. It includes a drug-drug interaction checker allowing healthcare workers to check multiple medicines against all HIV medicines, a step-by-step tool on how to manage skin, renal and liver adverse drug reactions to antiretrovirals and TB medicines, and a dosing tool for prescribing HIV medicines for children. “The app had over 6 000 active South African users between April and June 2026,” says Swart.

She adds that a Facebook page was created in 2016, which posts daily news and a weekly query of the week on Fridays to a following of over 12 500 people.

In one query posted on Facebook, a nurse from the Eastern Cape wanted to know if she should recall a patient earlier than the month she instructed. She initiated the 23-year-old male, who had been diagnosed with HIV three days earlier, onto the single-pill, once-a-day antiretroviral regimen of Tenofovir disoproxil fumarate, Lamivudine, and Dolutegravir. While he was clinically well, results for his CD4 count – the number of blood cells in a cubic millimetre of blood which gives an indication of the health of a person’s immune system – was 179 and he tested positive on a cryptococcal antigen test (CrAg).

The hotline’s experts advised the nurse to recall the client urgently, within 1 to 3 days and was pointed to the country’s guidelines which state that any client with a first or new CrAg-positive result should be called back for an urgent lumbar puncture and clinical assessment for meningitis, regardless of whether symptoms of meningitis are present. (Read Spotlight’s special briefing on cryptococcal meningitis, which is a serious fungal infection causing inflammation of the lining of the brain and one of the top killers of people living with HIV in South Africa.)

Swart says based on knowledge gaps that the pharmacists on the hotline pick up through the queries received, the hotline service has provided weekly WhatsApp-based microlearning sessions to three groups of healthcare workers. Since May 2025, 723 nurses, 915 pharmacists and doctors, and 375 community health workers joined these sessions on a wide spectrum of HIV and TB topics.

“The closure of the hotline will result in the unavailability of free clinical support for healthcare workers across the country managing people living with HIV and TB,” Swart says. “In addition, no posts will be added to the Facebook page, no new posters or tools will be designed, the weekly training has stopped, and the app will be maintained but not expanded.”

The funding conundrum

Swart explains that the hotline service has been funded throughout its existence, and most recently through a service level agreement with the National Department of Health from a Global Fund grant. “Our last Global Fund tranche finished in March 2025, and all documents to renew the contract were previously submitted in May 2024 for a new contract to start on 1 April 2025,” she says.

The Global Fund, established in 2002 to provide funding for HIV, TB and malaria programmes, announced in May last year that it was reducing funding to over 100 countries amidst shortfalls. It has indicated that it’s final grant to South Africa of around US$403 million will be for the period running from April 2031 to March 2034.

Swart says her team was informed in November 2024 that the team in charge of the Global Fund grant at the National Department of Health were planning to implement a tender process and was reassured that the hotline activities will still be supported.

“Several delays then ensued in combination with the global funding cuts across the board in February 2025. In April 2026, the service was put out on tender, and we successfully progressed through Phases 1 and 2 of the evaluation process. Following an invitation to present on 15 May 2026, we have unfortunately not received any further feedback, despite follow-up efforts made in a manner that respects the integrity and confidentiality of the procurement process. There has also been no information that another bidder was successful.”

Swart says the hotline’s activities came under strain in October 2025 when significant cuts in staff time were implemented and emergency funding was used to sustain the service.

“While we have always needed to seek and apply for funding, we have kept the service going and never had to face suspension before. Unfortunately, the massive budgetary constraints can no longer be overcome with emergency and cross funding endeavors,” she says. “It will remain suspended until alternative funding can be secured or the tender is awarded, so that we can reopen the hotline and continue all advisory activities.”

Spotlight sent questions to the National Department of Health, but had not received a response by time of publication.

What it means for healthcare workers

The news of the suspension of the National HIV and TB Healthcare Worker Hotline has prompted widespread concern.

Southern African HIV Clinicians Society CEO Dr Fiona Storie says it has promoted the use of the hotline to their extensive network of healthcare workers throughout the years.

“We believe the hotline provides an integral support service to clinicians in the country. The suspension of the hotline represents a significant loss of a valuable resource that enhances evidence-based HIV and TB management in South Africa.”

Noluthando Swartbooi, an occupational health nurse practitioner at Kwazakhele Clinic in Nelson Mandela Bay, tells Spotlight she has been using the hotline for about four years now. “HIV and TB management continues to require ongoing support, up to date knowledge and at times specialist guidance. Having access to experience through the hotline has been extremely helpful,” she says.

With chronic shortages of healthcare workers in the public sector among other challenges, she says she is worried about the suspension of the service. “The cases we deal with are not straight textbook examples so guidance from experts is beneficial. Suspending the hotline could place a strain on healthcare workers as they may have fewer options of teams that may assist in management of patient cases. This may affect the quality of care provided to patients,” she says.

A clinical pharmacist in Mpumalanga, who has been using the hotline for around five years, says she is daunted because most practitioners she works with don’t keep updated with current national treatment guidelines. She says it falls on her with the help of the hotline to ensure that all patients are taking appropriate treatment and the right doses.

“I do not know who I’ll be seeking help from moving forward, especially for patients that need dose adjustments according to the liver and kidney function tests as well as paediatrics since there’s some TB medication that’s out of stock. Their absence will make my workload even heavier than it already is right now,” she says.

For her part, Swart seems committed to limiting the disruption and finding a way to getting the hotline up and running again.

“While the suspension of services represents a significant and regrettable setback, we remain fully committed to preserving the hotline and are actively exploring funding opportunities that may allow us to resume operations in the future,” she says. “Should funding become available, we will work diligently to restore the service as soon as possible.”

Giddy says she is devastated that the hotline service is on its knees. “They supported us in our sorrows, and they rejoiced in our triumphs with us for years,” she says.

*This article was first published by Spotlight – health journalism in the public interest. Sign up to the Spotlight newsletter.

Can SA’s New Director-General for Health Turn Around a Struggling Department?

Dr Thembisile Xulu is the newly-appointed Director General of the National Department of Health. (Photo: Denvor de Wee/Spotlight)

By Marcus Low

Dr Thembisile Xulu is South Africa’s sixth permanent Director-General of health since the dawn of democracy. How will she measure up against her predecessors?

In recent months, we’ve been keeping an especially close eye on the media statements following the twice-monthly meetings of South Africa’s cabinet. Then last week, we finally spotted the line we had been waiting for – the announcement of South Africa’s new Director-General (DG) for Health. 

The name of the country’s sixth permanent DG since 1994 was a familiar one. Back in 2020, Spotlight interviewed Dr Thembisile Xulu when she was appointed CEO of the South African National AIDS Council (SANAC) – the national body established by Cabinet to coordinate South Africa’s response to HIV, Tuberculosis, and Sexually Transmitted Infections. 

In moving from the job of SANAC CEO to health DG, Xulu follows in the footsteps of Dr Sandile Buthelezi, who was CEO of SANAC from 2017 to 2020 and DG for Health from 2020 to early 2026, when he was suspended along with two other senior officials in the department. 

Prior to her time at SANAC, Xulu worked at the non-profit Right to Care for around a decade and a half. She is a medical doctor and has a master’s degree in public health. As far as we can tell, she is well liked in healthcare circles.

A huge task

The job facing Xulu is a daunting one. 

First, she will have to sort out problems within the department itself. As we pointed out in an editorial published in April, the department hasn’t gotten a clean audit in any of the last five years. The Digital Vibes scandal and the suspension of several senior officials earlier this year relating to another matter paints a bleak picture. While we know there are several committed and capable people working in the department, organisationally it seems to be exhibiting all the classic signs of chronic dysfunction and a lack of effective leadership. 

Maybe the most urgent task facing Xulu then is simply to turn the health department into a more professional organisation. This will require strong leadership and management skills, but it will also require her to more effectively protect the department from whatever the political whims of the day may be. Ultimately, a DG that always says, “yes Minister”, isn’t actually doing the Minister, or the public, any favours. 

But it won’t be easy. When the DG job was advertised back in March, the advert did not open by referencing the Constitution or the National Health Act, as one might expect, but by stating that the DG will be responsible for implementing the Presidential Social Compact for transformation of the health sector. The last health compact, signed in 2024, was a controversial document that did not get buy-in from several key business and healthcare worker organisations. That the job advert starts by referencing the compact rather than the relevant laws, seems an ominous sign for the DG’s chances of building a more capable, less politicised, department. 

Second, getting the department’s house in better order will help with what is of course Xulu’s main job – helping to address the country’s many health challenges. Top of the list is the chronic shortages of healthcare workers in the public sector. We have seen an important policy document and some extra funds for healthcare workers, but the incisive leadership and sustained commitment and planning needed to really get on top of the problem has been absent. 

There is a worrying pattern whereby government looks into a problem, maybe a committee of some sort is set up, the intentions are all good, but then everything stalls once some implementation challenge or political complication arises. We need a DG who does not allow important health issues to drift in this way, but who has the focus and determination to find workable solutions and to see them through. 

And then there is NHI

The NHI Act might currently be tangled up in a thicket of litigation, but whatever happens in the courts, NHI will be a big part of the DG’s work in the coming years (DGs are appointed for five years at a time). This may take the form of implementing some elements of the current NHI Act, or working with a revised Act, we just don’t know at this stage. 

But there will be many other bread and butter issues besides NHI demanding Xulu’s attention. In our analysis, the department has badly dropped the ball on urgent issues such as healthcare worker shortages, the regulation of private healthcare, and improving the quality of public healthcare services in areas such as mental health, diabetes, and hypertension. Hopefully under the new DG, the department will find ways of better addressing these issues in parallel with its work on NHI. 

A chance at renewal

There is some reason for optimism. With the appointment of Xulu as DG, and that of Dr Nonhlanhla Ndlovu before that as the department’s HIV czar, new people are now in two of the most important positions in the department. Such leadership changes offer a unique opportunity for organisational renewal. 

Spotlight has requested an interview with Xulu and we hope to get some time with her once she’s been in the job for a few weeks. We will ask her the tough questions, but we will also be fair and give her time. After all, we all want to see a health department and a health system that works. 

– Low is editor of Spotlight

This article was first published by Spotlight – health journalism in the public interest. Sign up to the Spotlight newsletter.

Exploited and Exhausted, SA’s Ghost Doctors Start to Rattle Their Chains

By Joan van Dyk for Spotlight

For years, hospitals have relied on the unpaid, unprotected labour of trainee-specialists to fill their rosters, but these doctors are reaching a breaking point.

Across South Africa’s public sector hospitals, a growing number of aspiring specialists are choosing to work for free — sometimes for years at a time — in pursuit of the coveted title.

Nearly every step of the 12 to 15 years of training required to specialise or sub-specialise can only happen in the public sector, but provincial health departments, bruised by more than a decade of austerity and graft, have few paid posts to offer.

As a result, hundreds of local doctors and hopeful specialists are stuck in a nightmarish competition to be the most impressive candidate. There are waiting lists for both paid and unpaid positions.

Once the paid positions are filled, doctors from poorer backgrounds who did not get placed are at a dead end, perpetuating historical injustices and undercutting transformation targets. “A new apartheid,” several doctors call it.

The volunteer specialists Spotlight interviewed knew they were lucky to have the option to specialise, but their stories suggest it’s a dubious privilege.

They endure the financial and emotional stress of specialising without pay for a number of reasons, passion, to take over the family practise, or, most commonly, to secure a ticket out of the public healthcare sector.

But to reach the predictable hours and high income of specialist private practise, they must first navigate a clinical wasteland left behind by years of budget cuts and mismanagement by provincial health departments.

The gruelling unpaid route to specialisation they describe crosses a financial abyss with toll gates guarded by sometimes powerful bullies and dotted with legal and professional traps that could cast a long shadow over the futures they’re working to build.

How to spot a clinical spectre

South Africa’s phantom doctors have many names; they’re called fellows, volunteers or supernumeraries, depending on the facility.

The role was originally created as part of a regional programme that allows foreign doctors to train in South African hospitals. These trainees’ salaries are covered by their home governments and they’re not guaranteed a work visa through the Department of Home Affairs or accreditation from the Health Professions Council of South Africa (HPCSA) once they are qualified. Only 3% of the 5 772 doctors added to the government’s payroll between January and May were not South African citizens.

In recent years, so many South African doctors have accepted such unpaid positions that some provincial health departments advertise such “opportunities” and plan their budgets accordingly.

Spotlight was unable to quantify South Africa’s unpaid trainee specialist workforce. Only two of the eight medical schools surveyed between April and July provided trainee data and requests for the HPCSA’s list of active training codes for specialists and sub-specialists went unanswered. A training code is a non-negotiable prerequisite for sitting specialist exit exams regardless of funding source or employment status of the trainee. When cross-referenced with provincial payroll data, such a list could help estimate the extent to which the health system relies on unpaid expertise.

Anecdotal evidence suggests however that the trend started around 2020 in the Western Cape, where many interviewees say they wouldn’t mind working for the state. These days, Gauteng and KwaZulu-Natal’s cohorts of unpaid citizen specialists appear to be increasing too.

Interviews with numerous local supernumeraries suggest they often endure toxic hierarchies, bullying and administrative neglect, but they prefer to suffer in silence, terrified that seniors will fail them in expensive tests.

Specialist exams are officially set by the Colleges of Medicine (CMSA), but there are usually only a few qualified specialist examiners for each academic circuit. So, in reality, trainees are often being examined by their own department heads or a close colleague.

Pride, debt and resentment

The cutthroat race to build a standout CV starts as soon as medical students graduate. It’s no longer enough to gain experience as a medical officer and then to apply for a job as a registrar a couple of years later, there simply aren’t enough paid positions for either.

Any job posting can draw hundreds of applications from equally qualified candidates.

The resulting competition is harsh, and requirements ever shifting and often unstated.

Naeema Govender*, an aspiring anaesthesiologist in Gauteng, says it took her a couple of failed interviews to figure out how to decode a government job ad.

Experience in intensive care and internal medicine, she says, are now de facto requirements for anyone applying for a job as an anaesthesia registrar (or trainee-specialist) whether the advert says so or not, and “anaesthesia experience” really means a minimum of two years’ experience.

In highly competitive fields such as urology, registrar candidates are now expected to have completed two out of three major specialist exams (usually written during training) before they even apply.

Pulling shifts for free ends up being a good way to get an edge over others.

After a string of unsuccessful interviews for paid jobs, Meera Patel*, another anaesthesiologist-in-training, says she accepted a supernumerary post at Steve Biko Academic Hospital in Tshwane out of sheer desperation.

“I used to tell anyone who would listen that I would never subject myself to it,” she says. The extra experience did help Patel to get a paid registrar job in the Western Cape, but it left her feeling deep resentment for having to compromise her principles and work without pay to crack the system.

In Johannesburg, Govender says she also reluctantly took an unpaid position to beef up her CV. She’s still conflicted about the exploitation she felt forced into.

“I don’t know if I should be proud or ashamed,” she tells Spotlight.

Paranormal planning

The unpaid trainee specialist workforce does little to eventually increase the number of qualified specialists available to the public at government hospitals, so private healthcare appears to be the overall winner.

Once doctors are qualified specialists, they often flee to the private sector or emigrate. This is perhaps illustrated by the fact that 30% of the 22 405 doctors employed by the state are under the age of 35.

The trend has ultimately turned the public sector clinical platform into a subsidised training ground for private healthcare, argues Bernhard Gaede, an associate professor and head of the Department of Family Medicine at the University of KwaZulu-Natal.

There also seems to be an element of privatisation-by stealth unfolding.

Trainees are increasingly being supported by foundations or private hospital groups to fill a growing niche for sub-specialists, says Marthinus Dicks, a member of the South African Medical Association’s (SAMA) subcommittee for registrars.

At the Groote Schuur Hospital unit where Dicks is training to be a clinical haematologist, he says he’s one of only two who are paid a government salary. He also logged unpaid hours before he was offered a paid post.

He worries that the private money is taking pressure off the government to fulfil its training role. At the same time, he knows his already high workload would be much heavier without his three fellowship-supported colleagues. “It’s just not a life I want to imagine,” he says.

Between the free labour, private funding and foreign trainees, there’s little incentive for cash-strapped health provincial health departments to create permanent posts, according to a SAMA submission to the ministerial advisory committee on health staff.

The unpaid trainee specialist workforce isn’t mentioned in the health department’s health staffing reform plan, which lapses in 2030. The document does outline a five-year plan to improve clinical supervision, boost specialist retention and to develop a broader network of clinical support for trainees by 2025.

A progress report was submitted to Health Minister Dr Aaron Motsoaledi in March but critics say the plan is unlikely to have made a difference because the government lacks the high-quality data on public and private sector personnel that would be needed for implementation.

South Africa needs a Workforce Intelligence Authority that collates and cleans workforce data to be used for planning, suggests governance expert Professor Alex van den Heever. In July, he presented a draft policy brief to SAMA which also proposes ring-fencing training funds to protect salaries from provincial mismanagement and extending training subsidies and accreditation to private health facilities.

Without structural changes to address waste and mismanagement, Van Den Heever argues, simply giving provinces more money to counteract austerity will make no difference.

In the meantime, the government now deliberately budgets for clinical gaps to be filled by volunteers, says Sharon Twum-Boafo, head of SAMA’s registrar subcommittee.

“It’s ludicrous,” she says, “without the volunteers, many hospitals would simply not have enough doctors to cover 24-hour rosters.”

A legal void

Unpaid trainee specialists carry a heavy workload with few administrative and legal protections.

Since they lack a payroll number, they’re locked out of the blanket indemnity for healthcare workers employed by the state. Instead, government compels them to buy expensive private malpractice cover just to log hours for free in public hospitals.

Once they’re in the facility, Spotlight is told that it is possible they might be pressured to perform unsupervised, high-risk procedures far beyond their insured scope.

Speaking to Spotlight, several of these phantom physicians described their fear of being held personally liable for costs in potential lawsuits. Some are privately insured for millions of rands, which means that they would make for more lucrative targets than the government, where mediation often leads to lower payouts.

Ruan Vlok, head of SAMA’s employment law unit, agrees that unpaid specialists might become litigation lightning rods.

“It could become an easy making money machine for attorneys,” he says.

There are long term risks too.

Private insurance premiums are tied to clinical outcomes, so a pattern of bad events could drive up a doctor’s insurance premiums, or even render them uninsurable, the ultimate career-ending risk for a specialist.

Unfinished business

Some unpaid trainees face another tough reality.

They are often summoned to fill critical service gaps left by paid, full-time consultants who have vanished to moonlight in the private sector.

Dual practise is allowed within certain parameters, but enforcement of the rules is patchy across provinces and facilities. Money is one of the factors driving moonlighting among the state’s contracted specialists, whose salaries have not kept pace with inflation. A SAMA report estimates that in 2022, doctors were earning about as much as they were in 2013.

In order to save money, provincial health departments have limited the number of paid overtime hours that consultants can log. In this case, says Vlok, doctors are fully within their rights to refuse to work for free.

Ironically, this is when those who choose to work for free become extra useful in hospitals.

Yet should the phantom doctors  themselves attempt to pull a paid shift to survive, they could be threatened with disciplinary action, heavy fines, or the immediate deactivation of their training numbers.

Under HPCSA and university rules, trainee registrars are legally barred from doing private paid work. Worse still, when a crisis occurs, these supernumeraries find themselves locked in dual contracts with universities and hospitals, with little protection from either.

An uneasy peace

The rights of the health system’s unpaid workforce have never been challenged in court, Vlok says, in part because doctors fear that any litigation would lead to them being targeted or failed in their exit exams.

Because supernumeraries aren’t officially employees, they’re also excluded from recourse through the country’s labour dispute resolution body, the Commission for Conciliation, Mediation and Arbitration and the Bargaining Council, leaving them with no mechanism for redress.

Local supernumeraries technically sign away they rights by agreeing to work without pay, but Vlok argues the state is taking advantage of a vulnerable group because the public sector is the only route to specialisation.

The regulations that allow foreign trainees to work in South Africa do not cater to or even make provision for South African citizens, Vlok says. In his view, the Labour Relations Act and the Basic Conditions of Employment Act should take legal precedence, under which he believes unpaid trainees clearly meet the criteria of an employee.

“I don’t use this word lightly,” he says, “this is abuse.”

It’s unclear how much longer the strained peace will hold.

One exhausted trainee specialist told Spotlight: “We have to fix the medical system, it’s broken. Who is going to look after us when we’re old?”

*Spotlight granted the doctors quoted in this article anonymity because of the risk of reprisals from provincial health departments and the hospitals where they are working.

*This article was first published by Spotlight – health journalism in the public interest. Sign up to the Spotlight newsletter.

“This One was Brought by God Himself” – the Doctor Helping People See Again in Rural KZN

Dr Hennie Hamilton with his wife Sylivia and son near their home in Ingwavuma in northern KwaZulu-Natal. (Photo: Halden Krog/Spotlight)

By Sue Segar for Spotlight

As a young doctor working in rural KwaZulu-Natal, Hennie Hamilton lived with a Zulu family for four years, an experience which, he says, changed him forever. Twenty-three years later, he’s still working in the area as medical manager at Mosvold Hospital and doing cataract surgery on patients from five rural hospitals.

In the corner of a small ward in a rural hospital in northern KwaZulu-Natal, an elderly woman with a plastic shield covering her left eye sits up in bed. Her daughter, seated on a chair beside the bed, is holding her hand.

There’s silence, an air of quiet anticipation as a tall doctor leans over the woman and, in deep concentration, slowly removes the eye shield and the eye pad underneath it.

Next, the doctor gently eases her eye open and looks closely into her face to see her response. “Uya bona, Mama?” (Can you see, Mama?) Dr Hennie Hamilton asks the woman, keeping a hand on her shoulder.

The woman, Duduzile Phakathi from Mthubathuba, flickers her eyes. Her grip tightens on her daughter’s hand. “Yebo,” she answers, almost inaudibly, and her face breaks into a smile as she focuses, incredulously, on the tall man in front of her. “Ngiyabonga,” (Thank you) she says. The room erupts into excited chatter as mother and daughter start praying out loud, pouring blessings onto the doctor.

Eye patients from five hospitals – and further

It’s not yet 07:00, and Hamilton, medical manager at Mosvold Hospital in the mountain town of Ingwavuma, is already walking the wards. Every Monday, this quietly spoken man performs cataract surgery on patients from all over the uMkhanyakude district of KwaZulu-Natal. Besides coming from the area served by Mosvold Hospital, patients are referred to him from the other four hospitals in the district – Manguzi, Bethesda, Mseleni and Hlabisa. Tuesdays are for opening the eyes and checking the surgery has been effective.

After losing her sight to cataracts, Duduzile Phakati is overjoyed to see again and get back to caring for her chickens. (Photo: Halden Krog/Spotlight)

As a shaft of morning sunlight beams into the room and onto the faces of the two women, Hamilton, dressed in a black embroidered African work tunic called a Dashiki, explains what he’s doing. He speaks with a strong Afrikaans accent, despite his English last name.

“This patient had what is known as a dense cataract and was completely blind. We operated on her right eye in June, and yesterday we did her left eye. Today, we’re opening the eye and checking whether the operation has been a success,” he says.

A cataract, he explains, is an opacity, or cloudiness, of the lens in the eye, which blocks the passage of light and causes a person’s vision to blur or dim. “It normally happens in old age. Sometimes it arises from diabetes or injuries or trauma, or it can be caused by medication. Some people are born with it, but 95 percent of the patients we see have it because of old age.”

He continues: “Most people will eventually get a cataract. The big difference in this area is that people present very late. In rural areas like this, 20 percent of the patients we operate on are already blind in both eyes. People just wait for longer before they finally come for help.”

Cataract surgery, he says, is a short, painless procedure which involves numbing the eye using eyedrops and an injection; making an incision in the cornea; creating a small “tunnel” on the white of the eye; removing the cataract lens through the tunnel; and then, by folding and inserting it through the incision, replacing the inside of the lens with an artificial lens, made from synthetic material. The incision self-seals and needs no stitches and patients experience an improvement in their vision shortly after the procedure.

“Brought by God himself”

Phakathi’s daughter, Dorothy Mbonambo, says her mother who has diabetes, has been struggling with her eyes for some time. “She was a very busy woman, who loved looking after, and selling her chickens.” But she became totally blind in February, and suddenly she couldn’t do anything for herself.

“We had to feed her, bathe her, and dress her at home, where we all live together. We did not anticipate this at all, and we had to adapt. My mother was really struggling,” says Mbonambo.

Translating for her mother, she continues: “My mother is excited that she can see again. She loves to count her money from selling chickens. It has been frustrating not to be able to do that. She can’t wait to get back to her business, to her normal life.”

Mbonambo says the family was determined to get their mother to Mosvold Hospital for the surgery. “We knew about Dr Hamilton because people talk about this man who came here when he was young, and speaks isiZulu and does the eyes and other operations too.”

Still holding her beaming mother’s hand, Mbonambo points to Hamilton, saying: “This one was brought by God himself.”

“Before, everything was blank”

Next, Hamilton walks into another ward, bigger than the last, where seven more women who had cataract surgery the day before, are recovering. Similar scenes play out as he removes the eye shields for each woman.

Primrose Gina who works as a porter at Mseleni Hospital, says she started struggling with her eyes about three years ago. As the condition of her eyes worsened, it became increasingly difficult to see, and she was told it was cataracts.

After three years of struggling with her vision, Primrose Gina celebrates a new beginning following cataract surgery. (Photo: Halden Krog/Spotlight)

As Hamilton opens her eyes, she lets out an exhilarated shout and tells him she can see.

Gwendolin Mthethwa, a teacher from Ndumo, says her eyes still feel “cloudy” after her operation. This, Hamilton explains, is because, besides the cataract, she also has glaucoma in both eyes.

“Glaucoma is a disease of the optic nerve at the back of the eye which is caused by a build-up of fluid pressure inside the eye, causing damage to the nerve, often due to natural drainage systems being faulty.

“The difference between glaucoma and cataracts is that, with glaucoma, if the damage has happened to the nerve, we cannot reverse it,” Hamilton explains. “We can only try and prevent it from getting worse. But for a cataract, a patient can go from blindness to normal vision again.”

A busy day in the life of a medical manager

It’s nearly 08:00 and Hamilton has already seen eight eye patients. As he strides through the large female ward, the room erupts into song as nurses and some patients gather in the communal ward. “Every morning, we pray together, to connect with the Lord before we start our duties,” a nurse explains.

Next up is a meeting with the hospital’s CEO, Dr Bernard Mung’omba. As part of the hospital’s senior leadership team, Hamilton is closely involved in audits for the provincial health department and overall hospital decisions. As medical manager, he oversees medical care for patients – supervising the doctors, allied health professionals and all other departments including the pharmacy and the hospital’s social workers.

The 186-bed hospital employs 17 doctors and serves seven clinics and a community health centre in the uMkhanyakhude district. The area is characterised by poverty, with many people relying on grants and government work opportunities and living in mostly rural homesteads. Unemployment, teenage pregnancy and substance abuse are big challenges.

As a rural hospital, Hamilton says, “we do bits of everything”. “Last night, I was on call and at 23:30, was in theatre doing a caesarean section.” As medical manager, he says he plays less of a frontline than an advisory role, helping with emergencies from ectopic pregnancy to premature babies, and appendicitis. “We also deal with many diabetic and hypertensive-related emergencies like heart failure, and see many strokes, among older people,” he says.

“The spectrum is extremely wide. We’re a team of people with different strengths and we all rely on one another,” he says.

But it’s the eye operations which he says he finds most rewarding. “Ag, I love it … it gives me so much joy,” he says. “The patients often bless me. They say, ‘may God bless you’. I’m often in tears in the morning when I open their eyes.”

A long history

Mosvold Hospital was founded in 1908 by Christian missionaries and started out as a small stone rondavel. It was taken over by Scandinavian missionaries in the 1930s. The hospital is named after a Norwegian nurse, Esther Mosvold, who worked there in the 1940s, fell in love with the area, and raised money through her wealthy shipping family to expand the hospital. In 1978, the then Natal provincial government took over the hospital and the mission doctors slowly departed.

Hamilton shows us the original stone clinic next to an old chapel which, he says, resignedly, is now used for storage; and a house once lived in by missionaries, which is now the admin office. He points to a site where the provincial government is building a children’s ward and a lodge for mothers to stay while visiting children in hospital; and, on the other side of the hospital, a complex of 40 bachelor flats being built for staff at a cost of R400 million. The project should be completed next year, he says, adding it will be a “gamechanger” for Mosvold. “Mothers visiting their children in hospital currently sleep on mattresses on the floor.”

On our tour, we visit the ward where Hamilton’s eldest child was born in 2007. “It’s grown so much since then,” he says. Around us, the different departments – therapy, dental, radiography, and the pharmacy – are all bustling. In the children’s ward, manager Noziphe Gumbi says they’re seeing way fewer burn wounds this year. “We’ve really focused on outreaches to educate people on the dangers of burns among children,” she says.

Hamilton says he has seen many changes at Mosvold over the years, the biggest being the number of staff. “We’ve almost doubled the number of doctors, so we can spend much more time with patients. There was a time when there were only four doctors. Now, with 16, sometimes 17 doctors, we don’t have to run, run, run like we used to,” he says. “When I arrived, we were only white doctors, now I’m the only white doctor here which helps a lot in terms of language and knowing the people.”

A life in medicine

Hamilton was born in Johannesburg and studied medicine at Pretoria University. In 1997, he started his internship at McCord Hospital, then a mission hospital, in Durban. In 1998, he moved to Bethesda Hospital where, he learnt how to be “an all-round doctor”. He went on to complete qualifications in obstetrics and orthopaedics and trained to do cataract surgery at Edendale Hospital.

He worked at Bethesda at a time when HIV was “completely overwhelming”, he says. A large part of his work was supporting HIV patients clinically and he started a home-based care programme there. In 2003, he met his wife, Sylvia, a Swiss nurse, who, having previously worked in northern KwaZulu-Natal, had returned to start a home-based care programme at Mosvold. They married four months after meeting, and Hamilton moved to Mosvold in 2003, eventually becoming medical manager in 2015.

Why he stayed

“While I was working at McCord’s Hospital in 1997, I met another doctor, Colin Pfaff, who was working at Manguzi Hospital, who was living with a Zulu family,” Hamilton recalls. “When Colin told me about his experience, something just jumped in me. I believe it was God. I realised this was what I wanted to do.”

Less than a year later, while working at Bethesda Hospital, Hamilton moved in with the Nhlekos. “I lived in a mud hut with no running water or electricity. The house was about six kilometres from Bethesda and I’d cycle up and down the mountain to work every day. I became part of the family. In the evenings, I’d sit in the kitchen with my gogo. I learnt to speak fluent isiZulu.

“It was an amazing time, even though it was only for four years. It was the most beautiful place on earth,” he says.

Hamilton shuts his eyes and says: “This experience changed me forever. I was raised very much in an Afrikaner setting. During my high school, our family moved to a farm in the Free State. We lived completely separate from black people, eating from different plates, using separate toilets. There was always this issue of race which I just accepted.”

He continues: “Living with an isiZulu family completely changed that. They gave me a Zulu name, Sandiso, which means spreading God’s grace. People still call me ‘Mgilitsha’, the clan name for the Nhlekos. I learnt to see all people as people, to trust, and to love. It was a heart thing, the most life-changing part of my life.”

This article was first published by Spotlight – health journalism in the public interest. Sign up to the Spotlight newsletter.
This Specialist Forensic Nurse in Germiston Helped Put a Serial Rapist Behind Bars

Hazel Moagi proudly shows off awards for her work as a specialist forensic nurse, which represent her commitment to the field. (Photo: Elna Schütz/Spotlight)

By Elna Schütz for Spotlight

In a country like South Africa which grapples with a high prevalence of gender-based violence, forensic nursing unfortunately remains a largely overlooked specialisation, with little incentive for remuneration. One nurse tells Spotlight every flicker of hope a patient carries home is a reminder of why she chose this path.

Sister Hazel Moagi has won quite a few accolades as a forensic specialist nurse. These certificates and trophies are displayed on a table in one corner of her office at the Bertha Gxowa Care Centre in Germiston on the East Rand of Gauteng.  

To Moagi, this small table carries tremendous weight. It motivates her to keep pushing in a career that is much needed but often soft-pedalled in both recognition and remuneration. “I call it my place of safety,” she says. “Whenever I feel down or that I’m not okay, I look at the achievements, and I say, you need to stand up, pick up the pieces, and try to do more for the community because they need me to.”  

She lets out a giggle as she shares that colleagues would fondly call her ‘Nurse Hero’ after she scooped a 2023 Nurse Hero award. “It’s so fulfilling, more than monetary remuneration,” she says, adding that it also brings a sense of pride to those who know her “because you know small things make people happy.” 

Those who know her well enough may notice an absence of yellow merchandise among the trophies in her office. As a long-time supporter of the Kaizer Chiefs football club, it wouldn’t be amiss in the forensic nurse’s office. She says she makes sure to catch every game in person or on television to decompress, given the heavy and sensitive nature of her work.  

As operational manager of the Care Centre, Moagi runs a forensic medical service that she says many do not know is available when they need it. The Centre, on the grounds of the Bertha Gxowa Hospital, provides inclusive and comprehensive patient management of people who experience gender-based violence, including vulnerable populations such as children and people with disabilities as well as cases linked to trauma and driving under the influence of alcohol. 

Both suspected perpetrators and victims of crimes are helped in the building, but the sections are separate, with the entrances out of sight of each other. Inside, there are rooms for various parts of the investigative and medical process. There’s a swing set, playroom, and colourful doctor’s room meant to make children feel more comfortable.  

From victim to survivor 

“We are turning victims into survivors,” Moagi says. It is particularly important to her that all her clients are treated with dignity and respect, for instance, by offering them bathing facilities, fresh clothes, and food. Safe lodging, such as access to shelters is arranged if needed.   

Moagi says that a lot of patients arrive scared, traumatised, and often in the same clothes they were wearing during the crime. But after testing, treatment and brief recovery, the physical and emotional change is so different that she says even police staff fetching patients are regularly surprised that this is the same person they dropped off earlier. 

Moagi says she finds cases involving children, especially those abused by a family member, especially difficult to handle.

“It’s so painful to see …  abuse that happened within a space where it’s supposed to be a safe environment, and somebody you trusted with your child.”  

The specialised unit’s work includes collecting forensic samples and offering support in cases of gender-based violence. She explains that it usually starts with the gathering of DNA and other samples into a Sexual Assault Evidence Collection Kit if a person reports sexual assault within 72 hours.

“Then the history that the patient gives us also guides us in terms of where to collect,” Moagi says. She explains that carefully asking patients to detail what happened will help her know where on the body it’s best to swab. The whole process may take over three hours, and the DNA is particularly important in forensic cases where the perpetrator was unknown to the victim.  

Sometimes Moagi says she and her team notices commonalities between patients, which she then relays to her supervisor and the police. For instance, there may be multiple people who have been raped describing similar perpetrators and circumstances in the same geographical area, even if they have gone to different police stations or places for help. “If there’s a specific trend that is currently happening, then we escalate to say we have noted that this and this is happening around the specific area,” she says. 

When forensic samples are collected properly and each case is understood in its wider context, it can make the difference in helping police identify a serial rapist and build a case. Moagi says she has testified in court in several such cases.

While being mindful of sharing confidential details, she does remember one case in particular. “He’s currently serving more than 200 years,” she says. “It makes you feel good that at least we have saved more women from becoming his victims.” 

Memory of a neat white dress 

Moagi says her passion for nursing comes from her early childhood in a small village near Bushbuckridge.   

“There was a nurse that I used to see wearing her uniform, going to work, and coming back, and that’s when I said I also want to be a nurse,” she recalls. She smiles at the memory of the neat white dress the nurse wore, and how competent she seemed whenever Moagi saw her. She says she held on tight to that vision throughout her school years. 

Indeed, she studied nursing and a few years later the dream was fulfilled. She started working as a general nurse. 

A few years later she attended a three-day workshop on forensic medicine organised by several government departments. It was there, listening to forensic nurses speak about their work, that something new clicked for her. She says during the break, she felt compelled to speak to them and learn more about the work they did. “Since that day, I started to fall in love with managing gender-based violence cases,” she says. Around a year later, she started studying forensic nursing at the University of the Free State. 

Passion over money 

In specialising in forensic nursing, Moagi chose her passion over the potentially higher salary she could potentially get with other nursing specialisations. This is because, unlike nephrology or orthopaedics, forensic nursing is not recognised by the South African Nursing Council (SANC) as a professional specialisation. The SANC’s website does list forensic nursing as a nursing competency, but it does not include it in the list of specialised nursing competencies, which would make someone an Advanced Practice Nurse, with greater recognition and higher renumeration.  

A June 2026 parliamentary reply to a question to the Minister of Health alludes to the fact that this is due to the educational programmes used in the past, including the one Moagi studied, not being recognised in regulations. It notes that future qualified forensic nurses would likely be recognised. However, no current educational programmes appear to be approved for this yet.  

The parliamentary answer indicates that even if newer qualification lists are recognised in the future, Moagi’s previous diploma will continue not to be recognised.  

Moagi says she knew about this from the start and admits that it can be difficult with the current cost of living to see other nursing fields being paid more. She says she may see job posts with salaries posted for other specialties and feel a tinge of jealousy. 

She says she knows of nurses who were eager to specialise in forensic nursing but have been unable to because the additional recognition and remuneration do not reflect the demands of the role. “I think as soon as the nursing council recognises it, then more nurses will join,” she says.  

Doing this work for years to come 

It has now been a decade since Moagi moved to Germiston and started managing the 24-hour clinical forensic medical care facility located on the corner of Hospital and Cross Streets. She says she loves working with her team and the various stakeholders, such as the police and the Department of Social Development.  

If it is up to her, she will keep doing this work for many more years to come. She says that every patient who walks away with a little more hope after facing some of their darkest moments is a reminder of why she chose this path. 

“It’s seeing victims of gender-based violence walking out with hope that there is still life, and they can still pick up the pieces and try to move on with their lives,” she says. 

Meanwhile, another shiny trophy has been added to that table in the corner of her office. The Gauteng Department of Health’s Ekurhuleni Health District Services recently named her best female gender-based violence activist at their Annual Gender-Based Violence Awards. 

The awards are nice, but speaking to Moagi it is clear that they, like the higher salaries she may have had with another specialisation, are secondary. What drives her is a deep passion to help and serve others. 

“There are those days where you feel like no matter how bad the situation was, I did my best to make sure that the patient is managed,” Moagi says. “And by the time you go home, you know you have done something good for the patients.” 

*This article is part of Spotlight’s 2026 Women in Health series, featuring the remarkable contributions of women to healthcare and science. Sign up to the Spotlight newsletter.

With over 3 600 Western Cape Users, Lenacapavir is “Cool”

Lenacapavir is administered via two injections of 1.5ml each in the buttocks, thigh, abdomen or upper arm. (Photo: Nasief Manie/Spotlight)

By Biénne Huisman for Spotlight

From counselling about small nodules to overcoming people’s fears of needles, Spotlight takes the pulse of a new HIV prevention injection’s rollout in the Western Cape.

At Cape Town’s Philippi Village, beside a rainbow-emblazoned mobile clinic, Olwam Plaatjie says she switched from the two-monthly cabotegravir HIV prevention injection to the six-monthly injectable lenacapavir. Despite small nodules forming at the two jab sites on her abdomen, the 20-year-old is delighted with the new HIV prevention medicine.

Plaatjie, who is from Crossroads and who started taking cabotegravir injections three years ago, says: “I see many people who are HIV positive. Many of them are girls. Guys often don’t even want to be tested; my boyfriend didn’t want to go for HIV tests. So that’s why I started to have a fear. I was like, you know, maybe there is something he is hiding.”

Plaatjie is one of a stream of young women now taking their health in their own hands as they personally implement HIV prevention strategies, thanks to national government and research campaigns aimed at this vulnerable group.

According to Foster Mohale, spokesperson for the National Department of Health, as of 23 August, there have been 3 641 initiations of lenacapavir, or LEN for short, across the 22 government clinics in the province that are offering the injection. Nationally, the number stood at 47 934.

Due to severely constrained supply, lenacapavir is for now only being rolled out to 360 health facilities across six provinces (Free State, Limpopo, and Northern Cape are not currently included). Gauteng accounts for over a third of facilities and KwaZulu-Natal for around a quarter. The Western Cape’s 22 facilities makes up only around 6% of the total. The selection of facilities was in part informed by how well facilities had been doing in the provision of HIV prevention pills, currently available in almost all the country’s public sector health facilities.

Mohale said the three clinics with the highest administrations in the Western Cape as of August 26, were the Khayelitsha Community Health Centre, Michael Mapongwana Community Health Centre, in Khayelitsha, and Nolungile Community Health Centre, also in Khayelitsha.

Uptake in adolescent girls and young women

Asked about the high uptake in this area, Director of Service Priorities Coordination for the Western Cape Government Department of Health and Wellness, Hilary Goeiman, pointed out the community’s large population of adolescent girls and young women, who are being targeted in the medicine’s roll-out strategy.

“Nolungile Community Day Centre has demonstrated strong clinical leadership and effective implementation of the programme, successfully integrating lenacapavir into routine HIV prevention services,” she said.

On the demographics of the administrations, Goeiman said: “Most recipients are women, in line with the initial rollout focus on adolescent girls and young women, women of reproductive age, and pregnant and breastfeeding women who are at substantial risk of HIV acquisition.”

Mohale said 258 pregnant women had been initiated on lenacapavir at the 22 clinics across the Western Cape, since June.

Science in tandem with government

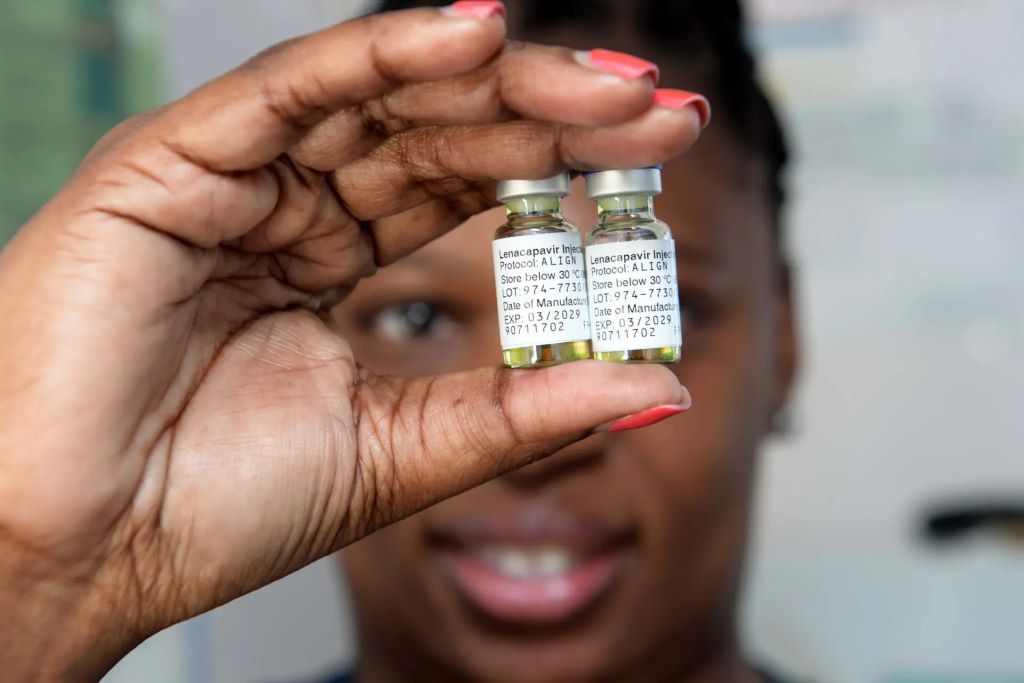
Meanwhile, Plaatjie was part of an initial cohort of 15- to 35-year-olds who received lenacapavir jabs in February, as part of a study spearheaded in the area by the Desmond Tutu Health Foundation. The study, called ALIGN, will evaluate implementation strategies for lenacapavir and how to encourage continued use.

The research is unfolding in collaboration with the Western Cape Department of Health and Wellness and the National Department of Health, but with a separate stock of the drug, independently sourced by the scientists. Social behavioural expert at the foundation, Elzette Rousseau, says their goal is to enrol at least 1 500 people on lenacapavir and to follow them for 18 months. She adds that at this stage, their data is still too limited to have any clear findings.

Cool, but a fear of needles

At Philippi Village, next to Plaatjie, Lutho Windvoel reflects on lenacapavir. He says that to his knowledge, men can be afraid of injections, and thus of HIV prevention through jabs. But, to him the benefit of protection over six months outweighs a fear of needles. “It’s just cool,” says Windvoel, who is wearing a black T-shirt with a pink teddy bear graphic.

At Philippi Village in Cape Town, a rainbow-emblazoned mobile clinic operated by the Desmond Tutu Health Foundation provides Lenacapavir injections. From left to right: Olwam Plaatjie, Sinovuyo Plaatjie, Lutho Windvoel, and Okuhle Trinity Potelwa. (Photo: Nasief Manie/Spotlight)

“LEN makes life easier. People are excited. Before, I took PrEP tablets daily but I worried that I would forget.”

Also in the conversation is Sive Mphambaniso, youth reference engagement facilitator at the Desmond Tutu Health Foundation. On a fear of injections, particularly among men, Mphambaniso agrees: “Most of them [men], when we talk about injections, they’re like, ‘nah.’ Many men are afraid of needles. Especially when we talked about cabotegravir when it arrived. So many of them preferred to take the oral PrEP, actually. Until the six month injection came in. Now people are saying, ‘it’s better for me to just have the guts to take the injection, rather than taking pills every day’. It’s the promise of six months that makes you just say, ‘Now let me have the guts to do this thing’.”

On some men being resistant to HIV testing or prevention, he says: “To be honest, it’s a struggle. And talking to men about HIV prevention, it’s quite a challenge, but it is happening. And I would say it is better for them to come to the mobile clinic rather than to go to a traditional clinic. Sometimes men don’t like people to think that they are sick. So they come here, it’s quite quick and it’s efficient.”

From the researchers’ side, Rousseau pointed out that one in four of their clients for lenacapavir had been men, “similar numbers to those accessing oral PrEP,” she says.

Small nodules that disappear

Speaking to Spotlight, Plaatjie and Windvoel, along with Sinovuyo Plaatjie, 22, and Okuhle Potelwa, 19, who were also in the initial cohort in the study led by the Desmond Tutu Health Foundation, agree that small nodules formed under the skin where the lenacapavir was injected. “It was like small bumps,” said Plaatjie. “It’s not even visible, but you can just feel it when you touch yourself. And it’s not sore.”

Lenacapavir is administered via two injections of 1.5ml each in the buttocks, thigh, abdomen or upper arm. Speaking to Spotlight, the four recipients say the nodules had not been painful, and that the bumps started growing smaller after about a month and eventually disappeared. They did not experience any other side effects.

Inside the “Tutu teen truck” mobile clinic parked at Philippi Village, nurse Zimasa Zwide elaborates on the nodules. “Most of the time they form immediately, especially on the slimmer people,” she says. “So what I normally do when I’m injecting people, I ask them to feel the nodules so that they won’t be surprised at home later. They get smaller with time and they disappear depending on the body of each participant. And most of them are not reporting any pains.”

However, at a workshop hosted by the Bhekisisa Centre for Health Journalism at the end of August, Spotlight heard from two lenacapavir users, who did report initial pain along with “bumps” at the injection sites – for a few weeks following administration. At some facilities, icepacks are used to numb the injection site, either before or after the injection is administered, or both.

Glass vials of pale yellow liquid

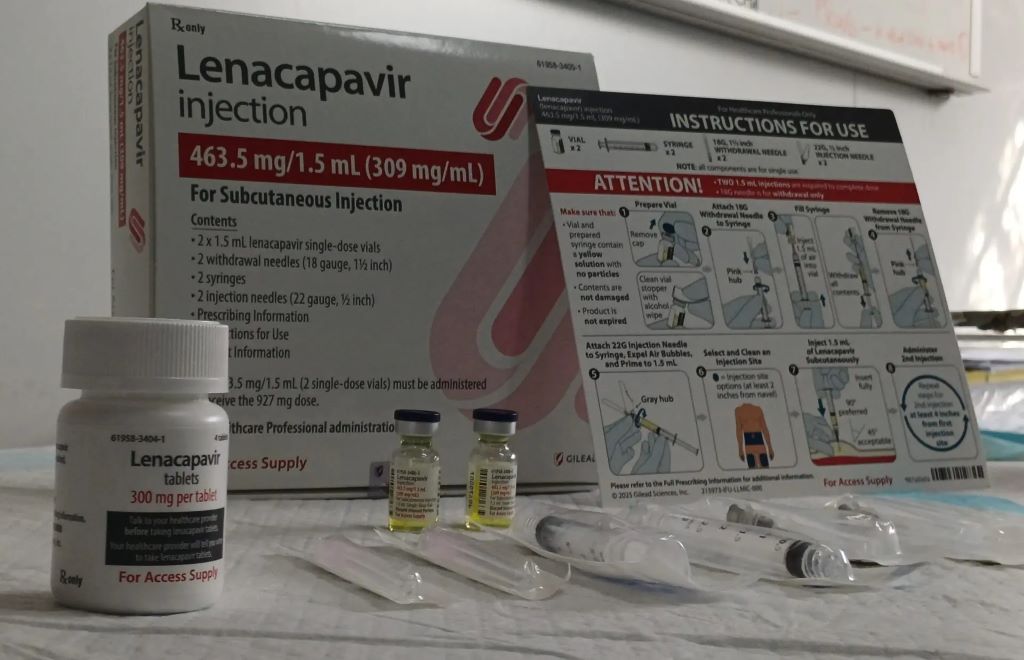
During our conversation, Zwide opens a lenacapavir dosing kit. Inside there are two syringes, two glass vials of pale yellow liquid, and a plastic container with tablets.

She says: “It’s two injections. One on each side of the abdomen, well depending on the injection site that they are choosing. And two tablets which are taken on the day of the injection, plus two tablets that I give them to take home, and which needs to be taken exactly 24 hours later. The tablets, it’s a form of speeding up the absorption process of the lenacapavir.”

If these steps are followed, she says, a recipient is fully protected against HIV three days later. The recipient needs to visit the clinic a month later for an HIV test and follow-up treatment. Zwide says the most patients she have injected with lenacapavir in her mobile clinic in a day were around six or seven people. This is her maximum capacity, she says, as the required administration takes around two hours per person.

Demand for the jab

On demand for the jab, Zwide says: “On a daily basis, there are a lot of people who are interested in lenacapavir. When we started rolling out LEN, there were a couple of participants who were coming in, even ones who were older than 35. Unfortunately, in our service, we take from 15 to 35 years, so we couldn’t give them. But luckily as it was now rolled out at the local clinics, we can refer them to Phumlani Clinic [three kilometres away].” Phumlani Clinic is one of the 22 facilities in the Western Cape offering the injection.

Contents of a Lenacapavir injection kit, including the drug vials, syringes, needles and instruction pamphlet, alongside a plastic pill container holding lenacapavir tablets. (Photo: Elri Voigt/Spotlight)

Responding to Spotlight’s questions around education on lenacapavir and demand creation in South Africa, Rousseau spoke highly of government’s rollout efforts.

“The national launch of lenacapavir in early June has created great demand and awareness of lenacapavir,” she says.

In addition, Mphambaniso points out the value of creating awareness about HIV prevention strategies and lenacapavir on channels that reach young people, specifically social media like TikTok.

Goeiman explained distribution of the medicine around the country. “Lenacapavir is procured centrally by the National Department of Health and distributed to provinces through phased deliveries. The Department continues to actively manage available stock to ensure equitable access throughout the phased rollout.” Technically, the department is procuring the medicines from the pharmaceutical company Gilead Sciences using money from the Global Fund (a large multinational donor).

For now, lenacapavir supply in South Africa remains highly constrained. That is expected to change once generic versions of the drug are registered and marketed in South Africa. Gilead have granted several companies licenses to produce generics. One of those, the Indian pharmaceutical company Hetero, has already filed a lenacapavir generic with the South African Health Products Regulatory Authority.

It seems plausible that the first lenacapavir generics will be approved in the first half of 2027 and indications are that the Department of Health will be quick to move to procuring lenacapavir generics on tender. Once that happens, the programme should expand rapidly with the aim of eventually covering all public healthcare facilities in the country.

This article was first published by Spotlight – health journalism in the public interest. Sign up to the Spotlight newsletter.

SA is One Step Closer to a New TB vaccine, but There is a Lot of Work Ahead

By Russell Rensburg

Russell Rensburg is the Divisional Director of the Rural Health Advocacy Project which hosts the TB Accountability Consortium. (Photo: Supplied)

In March 2024, a pivotal clinical trial was launched to evaluate what might well become the first new tuberculosis vaccine on the market in more than a century. As anticipation mounts for the trial to deliver results, Russell Rensburg argues that we need to start preparing for a rollout of the jab, but that we should think of preparation more widely than just the technicalities of regulatory approval and drug supply.

Over the past few weeks, there have been ongoing discussions about a potential new TB vaccine coming to South Africa.

The leading new vaccine candidate M72/AS01E TB or M72 for short is currently being evaluated in a large phase three clinical trial that started in March 2024. The trial has been running ahead of schedule and it is possible that results might be ready in the next year. If those results are positive, registration with the South African Health Products Regulatory Authority should follow quite soon after.

As all this happens, preparations for possible future manufacturing of the jab are already underway. In July, the Serum Institute of India announced an agreement with the Gates Medical Research Institute to prepare for large-scale production should the trial be successful and the vaccine approved.

And at the same time South Africa’s National Department of Health has started to engage in discussions about the roadmap for a possible vaccine rollout.

The optimism is high, and rightly so. It’s the first time in more than 100 years that we have reached this point with a new TB vaccine. Given the size of South Africa’s population at approximately 63 million people, its share of TB deaths worldwide is striking. WHO data shows that of the over 1.2 million TB deaths, around 54 000 were reported in South Africa. The idea that a new jab can arrest the alarming death rate of this curable disease and change the trajectory of TB in the country is exciting.

But the point that we are at should also prompt an urgent question. If a new TB vaccine proves successful, will South Africa actually be ready to use it?

For a country carrying one of the world’s highest TB burdens, a successful vaccine could fundamentally change our response to the disease. But the regulatory approvals that we will hopefully see next year or the year after would only be the beginning.

Getting community buy-in

To effectively roll out this vaccine, South Africa would need the buy-in of communities who trust that this vaccine could help them and are willing to encourage their fellow community members to take it up.

This negotiation could be harder than we think.

The country does not have to wait for the vaccine to be approved to begin this work. The opportunity to start building the community trust already exists. How? With the current rollout of a new TB test.

The National Department of Health is implementing a demonstration project to assess the health system’s readiness to introduce a new near point-of-care TB diagnostic test into the public healthcare system. The test would mean that people can get TB tests done at the clinic and get a result virtually immediately.

Many of South Africa’s TB deaths are due to late diagnosis. The new test presents the opportunity to shorten the gap between testing and diagnosis (samples don’t have to be sent off to labs) and could result in earlier initiation into care, which will potentially contribute to reduced mortality.

The near point-of-care testing sites are being deployed across the country in district hospitals, community health centres and primary healthcare clinics.

But a very important part of that work is not simply understanding whether the health system is ready for this diagnostic approach, it’s how communities are engaged and mobilised to understand and use it.

Testing community engagement

The community mobilisation and demand-creation component allows us to work directly with communities to understand what it takes to introduce a new TB intervention in a way that does not simply place a new technology into the health system and assume that people will use it.

Alongside measuring diagnostic performance, we should be deliberately testing models of community engagement: working with community health workers, TB survivors, civil society organisations and trusted local leaders; building people’s understanding of TB; listening to their concerns; identifying misinformation early; and understanding which messages, platforms and messengers people trust.

If we do this well, when a TB vaccine eventually becomes available, we will not be starting the conversation from zero. We will already have communities that have been part of the journey of TB innovation, systems for listening and responding to their concerns, and trusted people who can help communities navigate new information. That is what genuine vaccine preparedness should look like. It is not only preparing the regulatory pathway, procurement systems and cold chain. It is preparing the people and communities for whom the vaccine is ultimately intended.

Yet community engagement is too often treated as something that happens at the end of the process: develop the intervention, approve it, procure it and then ask civil society to persuade people to use it.

Trust cannot be manufactured through a communications campaign launched three months before rollout. Trust in a vaccine is inseparable from trust in the health system delivering it. That is why community investment should be considered part of vaccine preparedness itself—not an optional communications budget added later.

The civil society bridge

Civil society has a particularly important role here. Government develops policy, researchers generate evidence and health workers deliver services. Civil society often provides the bridge between those systems and communities.

Community organisations understand local languages, stigma, misinformation, barriers to accessing care and, importantly, the questions people may be reluctant to ask government or healthcare providers.

We should therefore begin strengthening community systems now: building the capacity of trusted community leaders; developing TB vaccine literacy; establishing mechanisms for community-led monitoring; and integrating conversations about vaccination into existing TB, HIV and primary healthcare services.

This is not about convincing people to take a vaccine that has not yet been approved. It is about creating the conditions in which people can eventually make informed decisions.

Ultimately, the measure of success will not be how quickly South Africa approves or procures a new TB vaccine. It will be whether the people who stand to benefit from it understand it, trust the systems delivering it, and are able and willing to access it.

The scientific breakthrough may happen in a laboratory. But whether it changes the trajectory of TB in South Africa will be decided in our communities.

– Rensburg is divisional director of the Rural Health Advocacy Project, which hosts the TB Accountability Consortium.

Disclosure: This piece was published by Spotlight – health journalism in the public interest. The Gates Medical Research Institute mentioned in this article is a non-profit organisation and subsidiary of the Gates Foundation. Spotlight receives funding from the Gates Foundation but is editorially independent – an independence that the editors guard jealously. Spotlight is a member of the South African Press Council.

What are Broadly Neutralising Antibodies and What do They Mean for the Fight Against HIV?

After several years of living with HIV, some people are able to produce a special type of antibody known as broadly neutralising antibodies. (Photo: Pixabay)

By Catherine Tomlinson for Spotlight

HIV is known for its ability to outsmart our immune system’s normal defences. A small number of people living with the virus are however able to generate unusually effective immune responses. In this special briefing, Spotlight zooms in on broadly neutralising antibodies, the secret sauce in these immune responses, and their potential role in the future of HIV treatment and prevention.

Our immune systems are highly effective at identifying and fighting off foreign invaders, such as viruses. One way our immune systems does this is by producing antibodies. In short, antibodies recognise viruses and then latch on to them. This blocks the viruses from entering our cells and flags them for destruction by other parts of the immune system.

One of the most remarkable things about our immune system is that it is able to create an enormous variety of such antibodies tailored to each different virus and other disease-causing pathogen that we encounter over our lifetime.

The human immunodeficiency virus (HIV), however, outsmarts our bodies’ normal immune responses by constantly changing the parts of its surface that antibodies recognise. This makes HIV difficult for antibodies to attach to and neutralise.

After several years of living with HIV, some people are able to produce a special type of antibody, known as broadly neutralising antibodies, or bNAbs. These antibodies are more effective at neutralising HIV than regular antibodies because they recognise parts of the virus that change very little, known as ‘conserved regions’. By targeting parts of the virus that are less prone to change, bNAbs are more effective than regular antibodies in identifying and neutralising the constantly changing virus.

“About 20 percent of people living with HIV naturally develop bNAbs, after many years,” explains AVAC, a US-based NGO seeking to advance the development of HIV prevention tools. “By the time bNAbs have developed in these individuals, the constantly mutating HIV has outpaced these defenders, changing too fast and too significantly for bNAbs to be effective in that individual. But that same bNAb, or a combination of them, may work in someone else,” they say.

A vibrant area of research

Researchers first identified bNAbs in a person living with HIV in the 1990s. Since then, they have discovered many more bNAbs and papers and presentations on the topic have become a staple at HIV conferences. At the 2026 International AIDS Conference held in Rio de Janeiro, Brazil, in July, there were 21 abstracts related to the topic.

Since the 1990s, researchers have learned how to replicate and produce bNAbs in the lab. They have conducted early-stage trials showing that bNAbs can be safely administered to people and they have learned how to engineer bNAbs to increase their potency and make them last longer in our bodies.

Currently, researchers are studying whether bNAbs, given by infusion or injection, can prevent HIV infection in people who are HIV negative and control the virus in people who are already living with it. There is also an interesting cross-over with vaccine research, whereby researchers are trying to develop HIV vaccines that prompt the body into making bNAbs.

Before we dig into the details, it is worth stressing that all of this research is still at an early stage. Whereas bNAbs show promise, they have neither set the world alight, nor completely failed. For now, antiretroviral medicines remain the only effective form of HIV treatment, as well as being an extremely effective form of HIV prevention. It is not clear whether bNAbs will ever reach the high bar set by antiretrovirals.

bNAbs for HIV prevention

One of the big HIV stories of the last decade or so has been the use of antiretrovirals to prevent HIV infection. Antiretroviral tablets to prevent HIV infection are already widely available in the public sector, and since June this year, government has been rolling out the six-monthly lenacapavir HIV prevention injection to around 10% of clinics. Such pre-exposure prophylaxis, taking something to prevent infection, is commonly referred to as PrEP.

One of the big hopes for bNAbs is that an infusion of the cells could similarly work as a form of HIV PrEP. The thinking is that these ‘smarter’ immune responses will be more effective than our regular immune responses in recognising and neutralising the shape-shifting virus, and thus clearing it before it can get a foothold in the body.

Substantial research has already been done in this area with two landmark studies, the AMP trials, having garnered the most attention. In the two trials, researchers evaluated an infusion of a bNAb called VRC01 to prevent HIV acquisition in men and transgender people who have sex with men, as well as in cis-gender women. The trials were conducted by the HIV Vaccine Trials Network (HVTN) and the HIV Prevention Trials Network (HPTN).

The AMP trials found that VRC01 did not prevent HIV infection. While this was disappointing, the studies did make a breakthrough by showing that bNAbs could neutralise strains of the HIV virus under certain conditions. While HIV could shape-shift enough to get around VRC01 and cause HIV infection, VRC01 was able to neutralise the HIV strains that were vulnerable to this specific bNAb.

This pattern of bNAbs blocking some, but not all strains of HIV, has been seen in several other studies. It provides both reason for hope, since there is clearly some efficacy, but also frustration, since the efficacy is not nearly as good as what is achieved with antiretrovirals.

Learning from the AMP trials, scientists are now studying whether combining different bNAbs that target a broader range of HIV strains, as well as different regions of the virus’ surface, into a single infusion or injection can be used to prevent HIV.

HVTN and HPTN’s planned Combo-AMP trial will evaluate whether providing people with a combination of different bNAbs can prevent HIV, explained Fred Hutchinson Cancer Center’s Holly Janes at the recent AIDS Conference.

Beyond the AMP trials, the Durban-based research group CAPRISA has also led important studies on the use of bNAbs for HIV prevention. They recently announced the results of a trial called CAPRISA 012C that evaluated the use of a combination of two bNAbs to prevent HIV acquisition in young women in Southern Africa.

Disappointingly, the combination bNAb provided in this trial did not prevent HIV infection. However, CAPRISA reported that “a positive finding was that there was a trend towards protection when the viruses were sensitive to both or one of the two bNAbs compared to when the viruses were resistant to both bNAbs.” In other words, HIV infections occurred more frequently with strains of the virus that were resistant to the bNAbs studied than with strains that were sensitive to them.

“The CAPRISA 012C trial is a culmination of 22 years of research – while it has not led to a new HIV prevention product, it provides valuable information to guide further bNAb research,” said CAPRISA, adding that sensitivity to bNAbs in contemporary circulating viruses will need to be factored into planning future trials of bNAbs.

bNAbs for HIV treatment

bNAbs are also being evaluated as potential treatment for HIV. Researchers are trying to understand whether, under what circumstances, and for how long bNAbs can control the virus in people living with HIV, with the goal of developing products that can achieve long-lasting HIV control without antiretroviral treatment.

This is important because the emotional and psychological burden of having to adhere to a life-long daily pill regimen to treat HIV is a known cause of poor treatment adherence. For infants and young children there are also practical challenges to swallowing and keeping down daily treatment.

One of the main ways that researchers are evaluating the potential of bNAbs to treat HIV is through analytical treatment interruption (ATI) studies. In ATI studies, people living with HIV are given bNAb infusions or injections –  sometimes in combination with long-acting injectable antiretroviral drugs – and then temporarily taken off their regular antiretroviral treatment under close medical observation.

Researchers then monitor how long HIV remains suppressed in order to learn whether and how well bNAbs can control HIV infection.

The results from ATI studies, including the RIO and FRESH trials, have been tantalizing. bNAb infusions have allowed some study participants to remain off antiretroviral treatment for more than a year without the virus rebounding in their bodies.

Yet, the studies have also raised questions about how and why bNAbs have such mixed efficacy. Researchers are still trying to understand why some people are able to maintain periods of viral control after receiving bNAbs, while others experience rapid viral rebound. The reasons for this appear to extend beyond a person’s sensitivity to the specific bNAbs being used to also include other factors related to the characteristics of one’s HIV infection and immune response.

At the 2026 AIDS Conference, Michel Nussenzweig, senior physician at the Rockefeller University, told delegates that research so far indicates that bNAb therapy is more likely to deliver periods of post-treatment control in individuals with a less diverse HIV reservoir, pre-existing autologous antibodies, and pre-existing stem cell like CD8+ T cells.

Scientists are now considering whether the factors associated with bNAb treatment success can be boosted through other interventions, said Nussenzweig.

Another important area of research is whether bNAbs can be used as a form of treatment for infants and young children living with HIV. An infusion or injectable treatment could be a gamechanger for this group, given the challenges faced by caregivers in getting infants and young children to swallow and keep down daily antiretroviral treatment.

The Tatelo and Tatelo Plus studies conducted in Botswana were set up to evaluate whether young children given bNAbs can maintain viral suppression after stopping antiretrovirals. Results from the Tatelo study reported in 2022 showed that some children (44%) who received a combination of two bNAbs were able to maintain a period of viral control (24 weeks) after stopping HIV treatment. The Tatelo Plus study, now underway, is evaluating whether and for how long a combination of three bNAbs can maintain HIV suppression in young children after antiretrovirals are stopped.

bNAbs for HIV vaccination

While bNAbs have not yet been shown to be a practical and effective form of HIV prevention or treatment, research has demonstrated that, under the right conditions, they can protect against and suppress HIV strains that are susceptible to them.

These findings have generated excitement about using bNAbs as a target for HIV vaccines. Unlike research into bNAbs for PrEP or HIV treatment, in which laboratory made bNAbs are infused or injected directly into our bodies, some HIV vaccine researchers are trying to figure out how to trigger our bodies to produce their own bNAbs.

In other words, vaccine researchers are trying to make our bodies, rather than laboratories, the factories that make bNAbs against HIV.

At this stage, scientists do not expect that a single vaccination will be able to trigger our bodies to produce mature bNAbs capable of combating HIV. Instead, they anticipate that a vaccine protocol that involves a series of vaccines will be needed to coax our immune systems to produce mature bNAbs.

While this branch of research remains at its early stages, many HIV researchers are hopeful that it may one day produce an effective vaccine protocol against HIV.

One study to watch is a Phase 1 safety and dosing trial launched by the International AIDS Vaccine Initiative (IAVI) and partners in South Africa at the end of 2025. “The hypothesis being tested is that highly specialized vaccine immunogens, delivered in a specific sequence, can target certain B cells within the immune system and coach them toward the production of broadly neutralizing antibodies against HIV,” says IAVI, adding “scientists widely believe that a vaccine inducing broadly neutralizing antibodies (bNAbs) could provide broad protection against many strains of HIV.”

Where to from here?

Since the first bNAbs against HIV were discovered in the 1990s, scientists have made important, but incremental, progress towards translating these immune responses into tools that can prevent and treat HIV.

As we’ve seen in this Spotlight special briefing, research into bNAbs for HIV treatment is arguably the furthest along, with bNAbs already demonstrating the ability to control HIV during extended periods of antiretroviral treatment interruption in some people. But why some people respond to this treatment and not others remains uncertain. This is an important area for future research.

In the HIV prevention space, bNAbs have delivered protection against HIV strains susceptible to the specific bNAbs studied, but this protection has not been broad enough to protect against HIV infection by the highly diverse, mutating virus. Hope however remains that combining different bNAbs that target different conserved regions of the HIV virus, as well as currently circulating viruses, could broaden protection enough to prevent HIV infection. Here too, as with attempts to develop vaccines that spark the production of bNAbs, it is imperative that the research continues.

Of course, even if scientists can crack the code and find a way to produce highly effective bNAbs, the road ahead might not be a smooth one. For these products to have an impact in the developing world, where they are most needed, they will have to be cost-effective compared to cheap antiretroviral therapy. They will also have to be easy to administer in often stretched and under-resourced healthcare systems.

While much remains to be done, the scientific leads are certainly there, waiting to be explored.

This special briefing is part of a series by Spotlight – health journalism in the public interest. Sign up to the Spotlight newsletter.

This World-class Scientist from Cape Town Used to Cut up her Dolls and Perform Imaginary Transplant Surgeries

UCT’s Professor Liesl Zühlke has won a global women in science award for her groundbreaking work in improving care for children with cardiovascular disease. (Photo: Supplied)

By Sue Segar for Spotlight

Long before she became a pioneering scientist, Professor Liesl Zühlke insisted on seeing her tonsils after they were removed when she was just five years old. Today, paediatric cardiology is close to her heart, and her research has helped answer critical questions in the entire pipeline of heart disease.

In the mid-2000s, while working as a trainee in paediatric cardiology at the Red Cross War Memorial Children’s Hospital, Liesl Zühlke helped treat a 12-year-old patient who had an unusual congenital heart condition.

“His heart was so weak that he was dying,” she says. “He was thin, short of breath and very tired. He’d had multiple admissions to hospital and numerous health folders, tied together with elastic. On the front of his folder, the letters DNR (meaning do not resuscitate) were written in black khoki-pen.”

Zühlke recalls requesting an ultrasound of the heart, among other tests that eventually led to a diagnosis of a coronary artery anomaly. “This is a structural heart defect, present at birth, where the major coronary artery supplying the heart itself has the wrong origin, resulting in oxygen-poor blood supplying the heart muscle, causing it to die,” she explains. (See this Cleveland Clinic page for more on the condition.)

Fortunately, the defect is treatable with cardiac surgery to move the coronary artery to the correct place. Within a year of having this operation, the boy’s heart function had returned to normal.

A journey to research

This encounter was something of a turning point in Zühlke’s life. Till then, she’d only done clinical work, but the case piqued her interest in this particular lesion.

This experience, she says, was a lesson in looking beyond the obvious, re-examining a patient with a fresh approach, and asking new questions. “By thinking differently, we changed the trajectory of his life and many others.”

Zühlke did a small study looking at 30 cases of this lesion, and found it was more common than thought. “Our work led us to being able to diagnose this condition much earlier, before heart damage could happen, and children with the lesion could get surgery earlier. It made me realise why research and evidence-based medicine are so important … if one wants to impact not just the patient in front of you but multiple patients.”

A lifetime steeped in medicine

Zühlke, who was born and raised in Athlone, Cape Town, was from childhood fascinated about the inner workings of the human body.

“My siblings remember me cutting up my dolls and doing transplants with pieces of chicken,” she recalls with amusement.

When she had her tonsils removed at a tender five years old, she insisted on seeing the fleshy lymph node masses.

“My grandmother worked as a domestic worker in a residence at the University of Cape Town (UCT) and told us stories about students and what was happening there. Apparently, from when I was three or four, I said I wanted to study medicine,” says Zühlke.

It thus came as no surprise that she ended up studying medicine and surgery at the UCT. In 2015, she completed her PhD on the outcomes of asymptomatic and symptomatic rheumatic heart disease, which was supervised by the late Professor of Cardiology Bongani Mayosi. She calls him her “academic father” and “the man who saw something in me that I didn’t”.

In 2019, Zühlke was the first woman in South Africa to be appointed as a full professor in paediatric cardiology.

“It was always going to be paediatrics,” she says, adding “there was always a kid on my hip during ward rounds. With children, it’s not about status but about caring, and meeting them at their level.”

Losing patients, Zühlke says, is part of any doctor’s experience, “but it’s terrible telling a mother their child hasn’t got a normal heart and that there’s a possibility of death. To do that with compassion … is what we’re put in this world for.”

She says while her work started with research into rheumatic heart disease, her focus later evolved. “I started looking more at the reasons why we have the outcomes we do; the overarching determinants of why people are diagnosed late, why they don’t have enough treatment, and enough surgery; and why they have poorer outcomes.”

Today, Zühlke is vice-president of the South African Medical Research Council, and at Red Cross she is director of the Children’s Heart Disease Research Unit and a paediatric cardiologist in the Division of Paediatric Cardiology.

What types of things go wrong in children’s hearts?

Heart disease in children refers to any problem with the structure or work of the heart, explains Zühlke. There are two main types: congenital heart disease which relates to structural problems with the heart that are present at birth; and acquired heart disease that develops later.

“The heart is complete between six and eight weeks in utero. With congenital heart disease, the structural abnormalities are there already,” she says.

“The heart can be viewed as a house with four rooms or chambers, with walls that separate them, and veins or arteries going in or out to allow blood to move from one chamber to the next, through four valves or doors. There can be problems with any of those, for example, a hole in the heart, which is one of the most common things we see. If there’s a hole in one of the walls separating these chambers, then oxygen-rich and oxygen-poor blood can mix, making the heart and lungs work harder,” Zühlke says.

She says that a much more serious problem is when, instead of being born with four parts of the heart, a child is born with three or there’s obstruction to blood flow to the body. “This critical cardiac lesion requires surgery to reorganise the circulation. No surgery almost certainly means death. The range of structural abnormalities ranges from mild to critical. Congenital heart disease is the most common birth defect, affecting one in 50 children,” Zühlke says.

Explaining rheumatic heart disease, she says: “This is acquired later in life, particularly in children between the ages of five and fifteen, as a consequence of an infection called Streptococcus pyogenes (Strep A) which causes a sore throat or a skin infection and sets off an abnormal immune response. The body attacks and damages the tissue in the heart, an acute illness follows called Rheumatic fever and the permanent heart valve damage which results is known as Rheumatic Heart Disease.”

Zühlke believes not enough studies have been done to prove categorically what the prevalence of heart disease is in children in South Africa. “It’s hard to do a true birth prevalence study. But we’ve done a lot of work (through extrapolating numbers from other studies) to fill in the data gap showing that the prevalence in South Africa is similar to other parts of the world.” She says congenital heart disease is within the top five killers of children and more common than any other birth defects combined.

Unclear causes

The causes of congenital heart disease could include genetic changes, like chromosomal disorders like Down syndrome; maternal health issues like diabetes, obesity or infections; or exposure to smoke, alcohol or restricted medications during pregnancy.

The causes of acquired heart disease are similarly varied, ranging from environmental causes to and infections. It can take many forms. Kawasaki disease is a childhood illness that causes inflammation in the walls of blood vessels, resulting in fever, rashes and swelling; cardiomyopathy is a disease of the heart muscle that makes it harder for the heart to pump blood to the rest of the body. HIV-associated heart disease comes about because people living with HIV face a higher risk of developing cardiovascular disease.

The symptoms of heart disease, Zühlke says, include rapid breathing, an increased heart rate, and excessive sleepiness. Babies can be pale or blue around the fingers, toes or lips, and can tire when drinking or have problems gaining weight.

There are several possible diagnostics, but they are not always available in the public healthcare system. These include heart ultrasound, electrocardiograms, X-rays, and checking the amount of oxygen in the blood soon after birth, with a pulse oximetry test.

In addition, Zühlke says that some provinces such as the Northern Cape and Mpumalanga lack a paediatric cardiologist to make the diagnosis. “There are also issues with referrals to get diagnosed patients to centres for timeous attention. Sadly, people are dying without even knowing they had heart disease,” she says.

What we can do differently

Asked what could be done differently in the public sector to improve early diagnosis of heart issues, she says pulse oximetry screening is a simple, cost-effective, efficient test to rule out critical congenital heart disease. Zühlke says there are plans to incorporate it into the Road to Health Booklet used by health professionals and parents to monitor a child’s health and development.

“It wouldn’t be difficult to add pulse oximetry screening as a check before a baby is discharged from a hospital. It’s been well proven that it works. All that’s needed is a probe and somebody to do it; and it can tick a box on the child’s Road-to-Health chart.

“But that requires money because you need a particular newborn probe to do it … and people are busy in the clinics,” she says.

On rheumatic heart disease, Zühlke says it’s “unethical” that an entirely preventable disease is still such a problem in SA and Africa. “We need research, funding, and advocacy to change that, improving diagnosis, treatment and long-term care. Also, we need to make sure there’s a vaccine to treat strep A.”

First prize, she says, would be to enable immediate diagnosis of rheumatic fever. “Currently, there’s no one test to say a person has acute rheumatic fever.”

“Next, we need a different way of treating it (the current penicillin injection is extremely painful for children); and getting a vaccine in countries where it actually matters. In the meantime, the goal is to ensure people living with the disease get access to care.”

Zühlke says she’s following the work on a vaccine for rheumatic heart disease closely and is involved in a vaccine collaborative which is working to ensure that when the vaccine becomes available, it is accessible and affordable.

‘Some of them were my heart patients as children’

Meanwhile, her “varied, mad, interesting” life sees her overseeing numerous intra- and extramural research projects for the SAMRC and directing her childrens heart research unit at UCT. She still works in a multi-disciplinary clinic for women with cardio-vascular disease in Groote Schuur’s maternity centre which she loves.

“Some of them were my heart patients as children,” Zühlke says, adding that transitional care is a priority “because patients with congenital and rheumatic heart disease become adults, we need to ensure that they can get the best possible life-long care.”

Her big vision has always been “to integrate research into the clinical space, so that as you see patients, it goes into the research, and as you research, it goes back to the patient.” Zühlke adds: “Being part of the research landscape at the SAMRC is deeply gratifying. What I’d like to see, most importantly, is childhood onset heart disease recognised as an entity, part of policy … and in the national action plans.”

She is the 2026 laureate for Africa and the Arab States in the L’Oréal-UNESCO For Women in Science International Awards for her pioneering work in improving care for children with cardiovascular disease, particularly rheumatic heart disease. Given to the top five female scientists globally, the distinguished award recognised her for “combining cutting-edge science with social justice” and “turning the fight against childhood heart disease into a public policy priority”.

Zühlke is married to Alexander Zühlke, a plastic surgeon at Tygerberg Hospital in Cape Town, and together they have two children.

*This article is part of Spotlight’s 2026 Women in Health series, featuring the remarkable contributions of women to healthcare and science. Sign up to the Spotlight newsletter.

Inside The Box with Dr Andy Gray | Are Complementary Medicines Effectively Regulated in South Africa?

#InsideTheBox is a column by Dr Andy Gray, a pharmaceutical sciences expert at the University of KwaZulu-Natal and Co-Director of the WHO Collaborating Centre on Pharmaceutical Policy and Evidence Based Practice. (Photo: Supplied)

By Dr Andy Gray for Spotlight

The regulation of complementary and alternative medicines in South Africa has been hotly contested in recent decades, including in court rooms. In his latest column for Spotlight, Dr Andy Gray unpacks the legal background and the current state of this still unfolding regulatory saga.

Multivitamin and mineral supplements are commonly found in many South African retail outlets, from pharmacies to health shops and supermarkets. Some outlets will stock a wider range of medicines, perhaps on shelves marked as “complementary”, or among other non-prescription medicines available for self-service.

Are these medicines regulated in the same way as other medicines, including those available on prescription?

The concept of a “call-up notice”

When South Africa’s medicines legislation was first passed in 1965, there were already many medicines on the local market which had not been assessed for safety, efficacy or quality. As all such medicines could not be immediately “called up” for registration, a stepwise approach had to be followed.

Between 1967 and the mid-1980s, medicines were identified for registration by pharmacological classification. The remnant of that approach is still evident in section 14(1) and (2): of the Medicines and Related Substances Act, 1965:

(1) Save as provided in this section or sections 21 and 22A, no person shall sell any medicine, … which is subject to registration by virtue of a declaration published in terms of subsection (2) unless it is registered.

(2) (a) The Authority may from time to time determine that a medicine, …, or class or category of medicine, … or part of any class or category of medicine, … mentioned in the declaration, shall be subject to registration in terms of this Act.

(b) Any such declaration may also relate only to medicines, … which were available for sale in the Republic immediately prior to the date on which it comes into operation in terms of paragraph (c) or only to medicines, … which were not then so available.

The declaration that a category or class of medicine is subject to registration is referred to colloquially as a “call-up notice”. A notice could be applied to those medicines already marketed, or only to those not yet marketed. Medicines which were already marketed but exempted from a full registration process were then regulated as “old medicines”. They are still subject to control according to their scheduling status and their production still needs to be in accordance with Good Manufacturing Practice. In time, new brands of some of the “old medicines” have been registered.

By the mid-1980s, the process of working through the pharmacological classifications was concluded. Thereafter, every new medicine would need to be registered before being marketed. In other words, a manufacturer or importer would need to provide sufficient evidence of the medicine’s safety, efficacy and quality to justify registration.

However, an important exception was created in 1986, which exempted homeopathic medicines from the full registration process. Two important restrictions were included. Firstly, no medical claims could be made for the medicine. Secondly, the following wording was to be included on the label of such medicine: “Homeopathic Medicine” and “WARNING: Use only as directed by a medical practitioner, pharmacist or homeopath”. The provision applied to homeopathic mother substances and so-called “minute-dose forms” made in accordance with homeopathic principles.

Broadening the scope of complementary medicines

Homeopaths are one of several complementary and traditional health professions regulated by the Allied Health Professions Council of South Africa. Medicines legislation has been amended to accommodate this wider range of complementary and traditional medicines.

A separate South African Health Products Regulatory Authority (SAHPRA) web site is dedicated to what are termed Category D medicines, also known as complementary medicines.

The General Regulations issued in terms of the Medicines Act includes a definition of complementary medicines which has two components: health supplements and medicines used in accordance with a “discipline as determined by the Authority”. The pharmacological classifications listed in Annexures 1 (human) and 2 (veterinary) medicines list the “disciplines” as Aromatherapy, Homeopathy, Phytotherapy, Traditional Chinese Medicine, Unani Medicine, Western Herbal Medicine, Combination Products and Other Herbal. The Annexures also list the types of health supplements, including amino acids, mineral, probiotics and vitamins. Two elements are important here – the nature of the substance included in the complementary medicine and the claims made in relation to that medicine.

Since 2013, the intention has been to progressively bring all complementary medicines under effective regulation, using a risk-based approach to identify those requiring registration and full assessment of safety, efficacy and quality data. The first pharmacological classifications identified were those claiming antiviral properties, and those intended to treat diabetes, cardiac conditions and cancer. However, no complementary medicines have yet been registered and the initial “call-up notices” have been repealed.

Like much of South Africa’s medicines regulatory space, this process has been affected by litigation. A challenge of the complementary medicines regulatory scheme by the Alliance of Natural Health Products (South Africa) was finally decided by the Supreme Court of Appeal in 2022. The court confirmed the finding that SAHPRA should have no regulatory power over substances and preparations that did not meet the definition of a medicine. A preparation that seeks to supplement a diet or provide a nutritional benefit is not a medicine, but a foodstuff. Draft amendments to the 2017 General Regulations, informed by the court judgment, were published for comment in March 2023, but have yet to be issued in final form.

Not a total lack of regulation

The hiatus in finalising regulations does not mean, however, that there is no regulatory control over complementary or Category D medicines. The initial “roadmap” outlined in the 2013 regulations has been replaced by a series of guidelines. The progressive, developmental approach to the regulation of complementary medicines remains in place, albeit delayed and as yet incomplete.

The overall roadmap was updated in 2021. All manufacturers, wholesalers or distributors of complementary medicines are required to be licensed by SAHPRA, but this process relies on an applicant’s “attestation of compliance with minimum requirements at the time of application and the payment of the required licence application, and desktop evaluation fees”, rather than the full Good Manufacturing Practice inspection applied to manufacturers of other medicines. However, SAHPRA reserves the right to conduct inspections where warranted. A similar approach is applied to the regulation of medical devices and diagnostic tests.

In the meantime, while no complementary or alternative medicines have been registered by SAHPRA, there is relatively strict regulation of what companies can say about the unregistered complementary medicines that they market in South Africa.

As with the 1986 exclusion for homeopathic products, all category D products which have not been registered have to include the following statement on the label: “This unregistered medicine has not been evaluated by the SAHPRA for its quality, safety or intended use”. The guideline also distinguishes between low risk and high-risk claims, in either labelling or advertising. Low risk claims are those for general health enhancement without any reference to specific diseases; health maintenance; or the relief of minor symptoms (not related to a disease or disorder).

The guideline is specific about a widely used wording: “Unregistered complementary medicines making use of the terms “Clinically proven” or any similar expression … shall also be considered to be HIGH RISK and may be subject to individual call-up in terms of section 14(2) of the Medicines Act.” Examples of acceptable low risk claims are provided, such as “Helps enhance/promote joint health”. Further guidance on the evidence to be relied upon for low risk and high-risk claims has been provided for the discipline-specific complementary medicines.

Manufacturers and importers of health supplements are only allowed to make low risk claims, and the relevant guideline provides Annexures (from Annexure A to O), showing the allowable levels and claims for each type of supplement. For example, a single component vitamin B3 (nicotinamide) product sold for adults may not contain more than 500mg per dose, and can only make a claim of “Helps to metabolise carbohydrates, fats and proteins”, “Contributes to normal growth and development” or “A factor in the maintenance of good health”.

A key document is the current guideline on the regulation of discipline-specific complementary medicines. An additional guideline was updated in 2022, which provides guidance on caffeine, menthol, camphor and cannabidiol. Low-dose cannabidiol can be sold as either a discipline-specific complementary medicine or a health supplement. At a dose not exceeding 20mg per day or 600mg per pack, it can be sold as a Schedule 0 product.

As no complementary medicines have yet been registered, none have as yet been specifically included in any of the Schedules, and they are therefore assumed to be controlled as Schedule 0 products, which can be sold in any retail outlet. One exception would be any injectable product, as those are automatically included in Schedule 3 and are prescription-only.

Important sources of information

The SAHPRA complementary medicines website provides a crucial resource which can be accessed by the public. The list of licensed complementary medicines manufacturers, importers and exporters is accessible here. There are currently 117 entries on the list. Each entry also provides a list of the products provided by that licensed entity, with details of ingredients, recommended doses and intended uses, whether discipline-specific or health supplement. The entire database is also searchable.

The site also enables anyone to lodge a complaint about a complementary medicine, including anonymous complaints.

Gaps in the system

While some progress has been made, the regulatory scheme for complementary medicines remains incomplete. Apart from finalising the regulations after the court challenge, a risk-based “call-up” process still needs to commence. Moving from an attestation process to confirmation that every manufacturer has met current Good Manufacturing Practice standards is still necessary.

Currently, the proprietary (brand) names used for complementary medicines are not pre-approved by SAHPRA, and many are in contravention of the naming guidelines applied to other medicines.

Effective oversight of advertising and marketing practices remains elusive, not only in respect of complementary medicines.

The dictum traditionally applied to consumer goods of “let the buyer beware” (in Latin, “caveat emptor”) is no longer considered appropriate. The Consumer Protection Act, 2008 seeks to protect the public against unsafe products and unfair marketing. Medicines are treated as a special category of goods, deserving closer regulatory control. The remaining gaps in the medicines regulatory system need to be plugged. One very particular gap, which has never been adequately addressed, is the regulation of African traditional medicines, which are not currently captured in the definition of Category D medicines.

 – Gray is a Senior Lecturer at the University of KwaZulu-Natal and Co-Director of the WHO Collaborating Centre on Pharmaceutical Policy and Evidence Based Practice.

Disclosure: Gray serves on three technical advisory committees at the South African Health Products Regulatory Authority.

*This column was published by Spotlight – health journalism in the public interest. Sign up to the Spotlight newsletter.