An analysis in the Journal of the American Geriatrics Society reveals that older inpatients admitted to physicians who prescribe higher amounts of first-generation antihistamines face an elevated risk of delirium while in the hospital.
First-generation antihistamines, such as diphenhydramine, are among the leading causes of medication-related harms in older adults, and although these medications are indicated for histamine-related conditions such as hives and anaphylaxis, they may be prescribed inappropriately.
When investigators analysed data on 328 140 patients aged 65 years and older who were admitted by 755 attending physicians to 17 hospitals in Ontario, Canada in 2015–2022, they found that the overall prevalence of delirium was 34.8%. Patients admitted to physicians who more commonly prescribed first-generation antihistamines had 41% increased odds of experiencing delirium compared with patients admitted to physicians who rarely prescribed first-generation antihistamines.
“We hope our study raises awareness among hospitalists that sedating antihistamines can be harmful, and should be prescribed with caution,” said corresponding author Aaron M. Drucker, MD, of the University of Toronto and Women’s College Hospital.
Allen Institute scientists are learning why vaccines can trigger a weaker response in older adults, around age 65, and what can be done to improve them. These insights open the door to designing more effective vaccines.
In the largest study of its kind, published in Nature, scientists discovered that T cells undergo profound and specific changes as we age. These changes, far from being random or a byproduct of chronic disease and inflammation, are a fundamental feature of healthy aging and will happen to all of us as we get older.
“We were surprised that inflammation is not driving healthy aging. We think inflammation is driven by something independent from just the age of a person,” said Claire Gustafson, PhD, assistant investigator at the Allen Institute and one of the lead authors of the study. “This is important because there’s been research showing similar findings that inflammation and aging don’t go hand in hand, and your immune system is just changing with age.”
The changes also point to why vaccines, including the annual flu shot and COVID-19 boosters, tend to be less effective in older adults.
The changes scientists discovered
T cells are a critical part of our immune system that help “train” B cells, to produce antibodies in response to viruses and vaccines. But this study found that memory T cells in older adults undergo a dramatic shift toward what is known as a “Th2-like” state, which is a change in gene expression that fundamentally alters how these cells respond to threats. Researchers found this shift directly affects B cells’ ability to generate strong antibody responses. In other words, the flu shot might still deliver the right viral components, but if the memory T cells aren’t functioning properly, the body struggles to respond effectively.
How this could lead to better vaccines
With this insight, doctors may be able to use a person’s immune profile to predict how well they’ll respond to a vaccine. Now that scientists can pinpoint how T cells become less effective with age, they can also start designing new vaccine formulas or immune-boosting treatments to address these issues.
Since T cells in older adults function differently, scientists could reformulate vaccines to compensate specifically for age-related cellular changes rather than using a one-size-fits-all approach. Gene-editing tools like CRISPR could also be used to reprogram a person’s T cells before vaccination, essentially re-programming older immune cells to make them respond to vaccines like younger cells do—like CAR-T cell therapy that reprograms immune cells to fight cancer.
Researchers say this work goes beyond just vaccines and reveals how our immune systems change in all of us as we get older and how our bodies fight age-related disease and viruses. It also opens the door to interventions like new therapies to restore key immune cells.
How researchers made the discovery
Scientists tracked more than 96 healthy adults ages 25–65 for over two years in collaboration with Benaroya Research Institute. The researchers then used cutting-edge techniques like single-cell RNA sequencing, proteomics, and spectral flow cytometry to profile the immune system of these individuals over time. The scientists then used this data on the immune system to create a detailed Human Immune Health Atlas, an online resource mapping 71 different immune cell types and how they change over time, and why those changes matter. Then, they applied this Atlas to study over 16 million individual immune cells from healthy adults 25–90+ years of age, offering an unprecedented tool for researchers worldwide to better understand, and support, the aging immune system. This online resource is the largest of its kind and freely available to researchers worldwide.
“This research illustrates how working collaboratively can make a significant impact on our understanding of the immune system, both now and in the future,” said Jane Buckner, MD, president of the Benaroya Research Institute. “It was made possible through the combined efforts of several Seattle-based research institutions, dedicated scientists, clinicians and research coordinators, as well as the individuals who generously volunteered their time, samples, and health information.”
The significance of this work extends beyond aging research and provides a roadmap for understanding how immune dysfunction develops over time, offering concrete targets for intervention and potentially transforming how we approach immune health across the entire human lifespan.
“There’s so much more information to be gained by looking at this dataset we’ve produced,” said Gustafson. “My hope is that it will be used for a long time to enable other researchers to look more deeply and find more insights into human immunity.”
A new study co-authored by a University of Wisconsin-Madison professor finds that life expectancy gains made by high-income countries in the first half of the 20th century have slowed significantly, and that none of the generations born after 1939 will reach 100 years of age on average.
Published in the journal Proceedings of the National Academy of Sciences, the study by Héctor Pifarré i Arolas of the La Follette School of Public Affairs, José Andrade of the Max Planck Institute for Demographic Research, and Carlo Giovanni Camarda of the Institut national d’études démographiques analysed life expectancy for 23 high-income and low-mortality countries using data from the Human Mortality Database and six different mortality forecasting methods.
“The unprecedented increase in life expectancy we achieved in the first half of the 20th century appears to be a phenomenon we are unlikely to achieve again in the foreseeable future,” according to Pifarré i Arolas. “In the absence of any major breakthroughs that significantly extend human life, life expectancy would still not match the rapid increases seen in the early 20th century even if adult survival improved twice as fast as we predict.”
From 1900 to 1938, life expectancy rose by about five and a half months with each new generation. The life expectancy for an individual born in a high-income country in 1900 was an average of 62 years. For someone born just 38 years later in similar conditions, life expectancy had jumped to 80 years on average.
For those born between 1939 and 2000, the increase slowed to roughly two and a half to three and a half months per generation, depending on the forecasting method. Mortality forecasting methods are statistical techniques that make informed predictions about future lifespans based on past and current mortality information. These models enabled the research team to estimate how life expectancy will develop under a variety of plausible future scenarios.
“We forecast that those born in 1980 will not live to be 100 on average, and none of the cohorts in our study will reach this milestone. This decline is largely due to the fact that past surges in longevity were driven by remarkable improvements in survival at very young ages,” according to corresponding author Andrade.
At the beginning of the 20th century, infant mortality fell rapidly due to medical advances and other improvements in quality of life for high-income countries. This contributed significantly to the rapid increase in life expectancy. However, infant and child mortality are now so low that the forecasted improvements in mortality in older age groups will not be enough to sustain the previous pace of longevity gains.
While mortality forecasts can never be certain as the future may unfold in unexpected ways – by way of pandemics, new medical treatments or other unforeseen societal changes – this study provides critical insight for governments looking to anticipate the needs of their healthcare systems, pension planning and social policies.
Although a population-level analysis, this research also has implications for individuals, as life expectancy influences personal decisions about saving, retirement and long-term planning. If life expectancy increases more slowly as this study shows is likely, both governments and individuals may need to recalibrate their expectations for the future.
4000 steps once/twice weekly is associated with 26% lower risk of death rising to 40% if done on 3 days of the week – but it’s daily step count rather than number of days that matters, findings suggest
Photo by Teona Swift on Unsplash
Clocking up at least 4000 daily steps on just 1 or 2 days per week is linked to a lower risk of death and cardiovascular disease among older women, according to research published online in the British Journal of Sports Medicine.
This large prospective study examined not only how many steps older women take but how often they reach their step targets across the week, addressing a key gap in current physical activity guidelines.
Researchers found that achieving at least 4000 steps per day on 1-2 days per week was associated with a significantly lower risk of death and lower risk of cardiovascular disease (CVD), compared with not reaching this level on any day.
A large body of evidence shows that lifelong physical activity is important for improving the healthspan, say the researchers. But it’s not entirely clear how much physical activity people should do as they age to reap appreciable health benefits, particularly in respect of step counts which are yet to make it into physical activity guideline recommendations, they add.
To explore this further, they set out to look at the associations between daily step counts of between 4000 and 7000 and death from all causes and from cardiovascular disease in older women.
They also wanted to find out if the total number of daily steps might drive any observed associations, rather than the frequency of achieving step count thresholds, with a view to informing future guidelines–in particular the US Physical Activity Guidelines, the next edition of which is planned for 2028.
The study followed 13547 women (average age 71) from the US Women’s Health Study who wore accelerometers (activity trackers) for seven consecutive days between 2011–2015 and were tracked for nearly 11 years. The women were free of cardiovascular disease or cancer at the start of the study.
During the monitoring period of nearly 11 years up to the end of 2024, 1765 women (13%) died and 781 (5%) developed cardiovascular disease.
Clocking up at least 4000 steps/day on 1–2 days of the week was associated with a 26% lower risk of death from all causes and a 27% lower risk of a cardiovascular disease death compared with not reaching this threshold on any day of the week.
For those achieving this step count on at least 3 days of the week, the lower risk of death from any cause increased to 40%, but remained at 27% for the risk of cardiovascular death.
But while higher daily step counts of 5000 to 7000 on 3 or more days of the week were associated with a further fall in all-cause mortality risk (32%) they were associated with a levelling out in cardiovascular disease mortality risk (16%).
When the findings were adjusted to take account of average daily steps, previously observed associations weakened, suggesting that [average] steps is the key driver of the protective effect, suggest the researchers.
This is an observational study, and as such, no firm conclusions can be drawn about cause and effect. The researchers also acknowledge that physical activity was assessed only for 1 week, and therefore couldn’t account for variations in behaviour over longer periods, nor did they have information on dietary patterns.
Nevertheless, they suggest: “The present study….suggests that frequency of meeting daily step thresholds is not critical (even 1–2 days/week of ≥4000 steps/day was related to lower mortality and CVD), and that step volume is more important than the frequency of meeting daily step thresholds in the older population.”
And they go on to explain: “An important translational implication of these findings is that since step volume is the important driver of the inverse associations, there is no ‘better’ or ‘best’ pattern to take steps; individuals can undertake [physical activity] in any preferred pattern (eg, ‘slow and steady’ vs ‘bunched patterns’) for lower mortality and CVD risk, at least among older women.”
They conclude: “These findings provide additional evidence for considering including step metrics in the next [physical activity] guidelines, and that ‘bunching’ steps is a viable option for health.”
A new biomarker for mental health called FGF21 offers a window into aging and disease risk
Photo by Usman Yousaf on Unsplash
A long-studied metabolic hormone, FGF21, also acts as a stress hormone – a discovery that helps explain how psychological stress causes metabolic dysregulation and drive physical disease, according to a new study published in Nature Metabolism.
FGF21 (fibroblast growth factor 21) has been researched for over two decades for its role in metabolism, glucose regulation, and diabetes.
“This is the first human evidence that FGF21 responds to mental stress, acting as a hormonal bridge between body and mind,” said senior author Martin Picard, PhD, associate professor of behavioural medicine at Columbia and co-director of the Columbia Science of Health programme. “It integrates psychosocial experiences with systemic metabolic signalling – expanding the neuroendocrine framework beyond traditional stress hormones.”
The study tracked hormonal changes following acute psychological stress in both healthy individuals and patients with mitochondrial disease, a group of genetic disorders that impair cellular energy transformation. In healthy participants, FGF21 levels on average dropped immediately after exposure to a standardised stressor, returning to baseline within 90 minutes – demonstrating a tightly regulated, dynamic hormonal pattern.
In contrast, participants with mitochondria that cannot transform energy normally showed a different pattern: FGF21 levels rose following stress and peaked at 90 minutes, indicating a fundamentally different stress response, likely regulated by mitochondrial biology.
“These results reveal a new axis of vulnerability,” said Mangesh Kurade, lead author on the study at Columbia. “The way our social environment and psychological experiences interact with mitochondrial health may directly shape metabolic outcomes and long-term disease risk.”
To validate their findings, the team analysed data from more than 20 000 participants in the UK Biobank and also drew on data from their ongoing MiSBIE study (Mitochondrial Stress and Biomarkers in Emotion), which investigates how psychosocial variables map onto biological processes.
The results showed that loneliness, childhood neglect, or recent relationship breakdowns including marital separation was linked to higher FGF21, while individuals with stronger social ties and emotional well-being – including frequent social interactions and high couple satisfaction and social support, were associated with lower levels – providing population-level evidence that FGF21 tracks with psychosocial conditions.
“Our findings suggest that the stress hormone and mitochondrial disease biomarker FGF21 signals not just acute stress, but also reflects a person’s social and emotional life over time,” said co-author Michio Hirano, MD, professor of Neurology at Columbia University Irving Medical Center who led the clinical portion of the study.
This cross-validation strengthens the case for FGF21 as a reliable biomarker of how psychological and social environments shape metabolic biology and perhaps also the clinical trajectory of mitochondrial diseases. By identifying FGF21 as both a biological mediator and potential biomarker of psychological stress, the study opens new avenues for research and clinical monitoring.
“This study bridges traditionally separate fields – metabolism and stress biology – suggesting that future precision mental health strategies may benefit from incorporating FGF21 and other biomarkers to monitor metabolic stress vulnerability and therapeutic responses,” said Kurade.
As a hormone once studied strictly within metabolic disease contexts, FGF21 now appears to straddle the boundary between mind and body, offering biological insight into how we age, adapt, and break down under pressure.
“This is about more than a single hormone,” said Picard, who is also associate professor at the Columbia Butler Aging Center. “It’s about understanding how our lived experience – our relationships, our stress, our resilience – gets translated into biology. A more accurate, holistic picture of human health is emerging. It’s an exciting time for science and medicine.”
Quitting smoking in middle age or later is linked to slower age-related cognitive decline over the long term, according to a new study by UCL researchers.
The study, published in The Lancet Healthy Longevity, looked at data from 9436 people aged 40 or over (average age: 58) in 12 countries, comparing cognitive test results among people who quit smoking with those of a matched control group who kept smoking.
The research team found that the cognitive scores of those who had quit smoking declined significantly less than their smoking counterparts in the six years after they quit. For verbal fluency, the rate of decline roughly halved, while for memory it slowed by 20%.
Since slower cognitive decline is related to reduced dementia risk, their findings add to a growing body of evidence suggesting quitting smoking might be a preventative strategy for the disease. Still, more research is needed to confirm this.
Lead author Dr Mikaela Bloomberg (UCL Institute of Epidemiology & Health Care) said: “Our study suggests that quitting smoking may help people to maintain better cognitive health over the long term even when we are in our 50s or older when we quit.
“We already know that quitting smoking, even later in life, is often followed by improvements in physical health and well-being. It seems that, for our cognitive health too, it is never too late to quit.
“This finding is especially important because middle-aged and older smokers are less likely to try to quit than younger groups, yet they disproportionately experience the harms of smoking. Evidence that quitting may support cognitive health could offer new compelling motivation for this group to try and quit smoking.
“Also, as policymakers wrestle with the challenges of an ageing population, these findings provide another reason to invest in tobacco control.”
Smoking is thought to harm brain health in part because it affects cardiovascular health – smoking causes damage to blood vessels that supply oxygen to the brain. Smoking is also thought to affect cognitive health by causing chronic inflammation and directly damaging brain cells through oxidative stress (due to the creation of unstable molecules called free radicals).
Co-author Professor Andrew Steptoe (UCL Institute of Epidemiology & Health Care) said: “Slower cognitive decline is linked to lower dementia risk. These findings add to evidence suggesting that quitting smoking might be a preventative strategy for the disease. However, further research will be needed that specifically examines dementia to confirm this.”
Previous studies, the researchers noted, had found a short-term improvement in cognitive function after people stopped smoking. But whether this improvement was sustained over the longer term – particularly when people quit smoking later in life – was not known.
To answer this question the research team looked at data from three ongoing studies* where a nationally representative group of participants answered survey questions every two years. The studies covered England, the US, and 10 other European countries.
More than 4,700 participants who quit smoking were compared with an equal number of people who carried on smoking. The two groups were matched in terms of their initial cognitive scores and other factors such as age, sex, education level, and country of birth.
The research team found that the two groups’ scores in memory and verbal fluency tests declined at a similar rate in the six years prior to participants of one group quitting smoking. These trajectories then diverged in the six years following smoking cessation.
For the smokers who quit, the rate of decline was about 20% slower for memory and 50% slower for verbal fluency. In practical terms, this meant that with each year of ageing, people who quit experienced three to four months less memory decline and six months less fluency decline than those who continued smoking.
This was an observational analysis, so unmeasured differences between smokers who quit and continuing smokers could remain; while the trends before quitting were similar, the study cannot prove cause and effect.
However, the research team noted their findings were consistent with earlier studies showing that adults aged over 65 who quit smoking during early- or mid-life have comparable cognitive scores to never smokers, and that former and never smokers have a similar risk of dementia a decade or longer after quitting.
*The longitudinal studies were the English Longitudinal Study of Ageing (ELSA), the Survey of Health, Ageing and Retirement in Europe (SHARE), and the Health and Retirement Study (HRS).
New research from Edith Cowan University (ECU), Curtin University and the University of Western Australia has found no evidence that calcium monotherapy increases the long-term risk for dementia, helping to dispel previous concerns about its potential negative effects on brain health in older women.
This study, which leveraged outcomes from prior research that provided calcium supplements or a placebo to 1460 older women over a five-year period, found that the supplement did not increase the long-term risk of dementia.
“Calcium supplements are often recommended to prevent or manage osteoporosis,” said ECU PhD student Ms Negar Ghasemifard.
Around 20 per cent of women over the age of 70 are affected by osteoporosis and calcium supplementation is widely recommended as a preventative measure against fracture.
“Previous research has raised concerns around the impacts that calcium supplements could have on cognitive health, particularly dementia. Results from our study provides reassurance to patients and clinicians regarding the safety of calcium supplements in the context of dementia risk for older women,” Ms Ghasemifard said.
ECU Senior Research Fellow Dr Marc Sim noted that when the analysis was adjusted for supplement compliance, a range of lifestyle factors, including dietary calcium intake and genetic risk, the results remained unchanged.
“Previous research suggesting potential links between calcium supplement use and the risk for dementia was purely observational in nature. Our research, in comparison, consisted of a post-hoc analysis from a 5-year double-blind, placebo controlled randomised clinical trial on calcium supplements to prevent fracture. Whilst our study is still epidemiology, its design does reduce the likelihood of unmeasured confounding”
“Some 730 older women were given calcium supplements over five years, and a further 730 were given placebo. This study design offers more accurate data on dosage and duration, and we had a long follow-up period of 14.5 years, which strengthens our results,” Dr Sim said.
While these findings may alleviate concerns regarding calcium supplementation and all-cause dementia risk in older women, particularly after the age of 80 years, Professor Simon Laws, Director of ECU’s Centre for Precision Health, said further research was required.
“Whether this extrapolates to other demographics, such as men or even women commencing supplementation earlier in life, remains unknown. To confirm the current findings, particularly regarding brain health, and to address these population gaps, future clinical trials of calcium supplements, with or without vitamin D, would need to be undertaken. These should include specific and robust assessments of brain health as the primary outcome measures.”
Curtin University’s Professor Blossom Stephan, Director of the Dementia Centre of Excellence and a Dementia Australia Honorary Medical Advisor said the research highlighted a very important finding that provides reassurance to clinicians and patients about the long-term safety of calcium supplementation.
“Given calcium’s critical role in multiple physiological functions, including bone health, these results provide reassurance that long-term calcium supplementation did not increase dementia risk in older women,” she said.
Study of 2,800 patients suggests moving beyond chronological cut-offs in cancer care
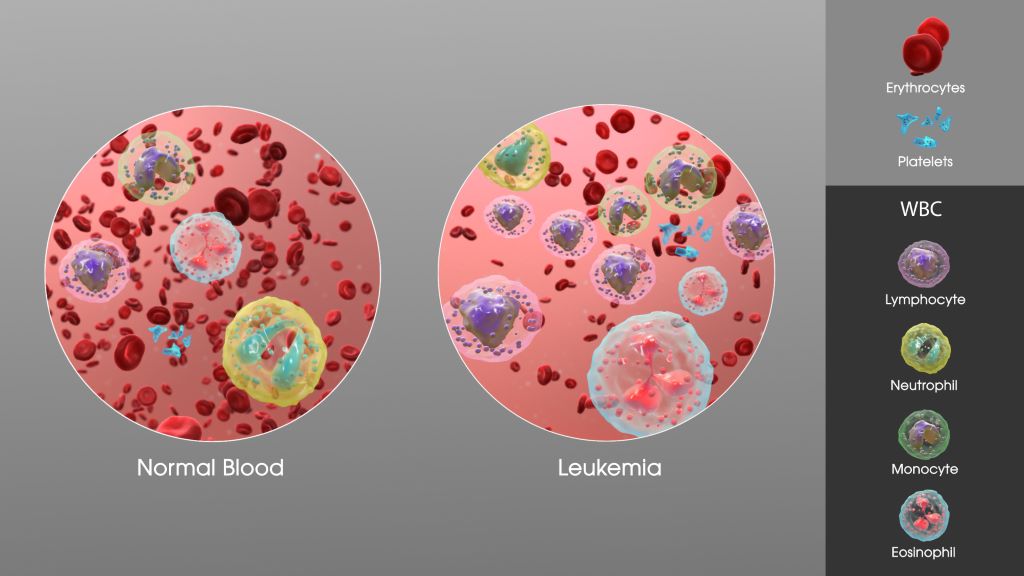
SAG Leukaemia. Credit: Scientific Animations CC0
An international study conducted by the Alliance for Clinical Trials in Oncology and the Acute Myeloid Leukemia Cooperative Group reveals that age-based classifications in the treatment of acute myeloid leukaemia (AML) may be outdated and overly simplistic.
AML is a fast-growing cancer of the blood and bone marrow that disproportionately affects older adults. Historically, age has been a key factor in determining treatment intensity, eligibility for clinical trials, and access to targeted therapies. However, this new research suggests that age alone is not a reliable indicator of disease biology or prognosis.
“Our findings support a more flexible, biology-driven approach to AML treatment and trial design. Age alone should not be a gatekeeper to potentially life-saving therapies,” said Alliance researcher and lead author Ann-Kathrin Eisfeld, MD, associate professor of Internal Medicine and director of the Clara D. Bloomfield Center for Leukemia Outcomes Research at The Ohio State University. “Our results suggest reconsidering age-based eligibility criteria for treatments. By focusing on molecular and genetic profiles rather than chronological age, clinicians may better tailor treatments to individual patients, improving outcomes and expanding access to novel therapies.”
Published in Leukemia, the study analysed data from 2823 adult AML patients treated in the setting of large cooperative group frontline trials across the United States (CALGB/Alliance) and Germany (AMLCG), uncovering nuanced age-related trends in genetic mutations and survival outcomes that challenge current clinical practices. This research is the first large-scale, cross continental study to analyse the mutational patterns and outcomes among patients of all age groups with AML.
The analysis included patients treated with frontline cytarabine-based chemotherapy between 1986 and 2017. Molecular profiling was conducted using targeted sequencing platforms, and survival outcomes were assessed using the 2022 European LeukemiaNet (ELN) genetic-risk classification.
The study found no clear age threshold that could biologically or prognostically separate patients into distinct groups. Instead, genetic mutations and survival outcomes varied continuously across the age spectrum. This challenges the long-standing practice of using arbitrary age cut-offs, such as 60 or 65 years, to guide treatment decisions.
Survival outcomes also declined steadily with age, even among patients classified as having favourable genetic risk. For example, patients aged 18 to 24 with favourable-risk AML had a five-year overall survival rate of 73%, while those aged 75 and older had a survival rate of just 21%. This trend was consistent across all risk categories, indicating that age negatively impacts prognosis regardless of genetic classification.
“This research arrives at a critical moment in oncology, as precision medicine continues to transform cancer care,” added Dr Eisfeld. “Most targeted treatment options are still only available for patients above a certain age threshold that is dictated by corresponding inclusion criteria of pivotal clinical trials, even though patients outside of that age range might equally benefit from these often less toxic treatments.”
Photo by Kampus Production: https://www.pexels.com/photo/a-man-in-blue-sweater-sitting-beside-man-in-white-long-sleeves-7551646/
Low cholesterol can reduce the risk of dementia, a new University of Bristol-led study with more than a million participants has shown.
The research, led by Dr Liv Tybjærg Nordestgaard while at the University of Bristol and the Department of Clinical Biochemistry at Copenhagen University Hospital – Herlev and Gentofte, found that people with certain genetic variants that naturally lower cholesterol have a lower risk of developing dementia.
Some people are born with genetic variants that naturally affect the same proteins targeted by cholesterol-lowering drugs, such as statins and ezetimibe. To test the effect of cholesterol-lowering medication on the risk of dementia, the researchers used a method called Mendelian Randomisation – this genetic analysis technique allowed them to mimic the effects of these drugs to investigate how they influence the risk of dementia, while minimising the influence of confounding factors like weight, diet, and other lifestyle habits.
By comparing these individuals to individuals without these genetic variants, the researchers were able to measure differences in the risk of dementia. They found reducing the amount of cholesterol in the blood by a small amount (one millimole per litre) to be associated with up to 80% reduction in risk of developing dementia for certain drug targets.
“What our study indicates is that if you have these variants that lower your cholesterol, it looks like you have a significantly lower risk of developing dementia,” said Dr Nordestgaard, who now works in the Department of Clinical Biochemistry at Copenhagen University Hospital – Bispebjerg and Frederiksberg hospital.
The results suggest that having low cholesterol, whether due to genes or medical treatment, can help reduce the risk of dementia. However, the study does not say anything definitive about the effect of the medicine itself.
One of the challenges is that dementia typically does not appear until late in life, and therefore research in the area typically requires a very long period of follow-up.
It is still not known exactly why high cholesterol can increase the risk of dementia, but one possible explanation proposed by Dr Nordestgaard is that high cholesterol can lead to atherosclerosis.
“Atherosclerosis is a result of the accumulation of cholesterol in your blood vessels,” Dr Nordestgaard said. “It can be in both the body and the brain and increases the risk of forming small blood clots – one of the causes of dementia.
“It would be a really good next step to carry out randomised clinical trials over 10 or 30 years, for example, where you give the participants cholesterol-lowering medication and then look at the risk of developing dementia,” Dr Nordestgaard added.
The study used data from the UK Biobank, the Copenhagen General Population Study, the Copenhagen City Heart Study, the FinnGen study, and the Global Lipids Genetics Consortium.
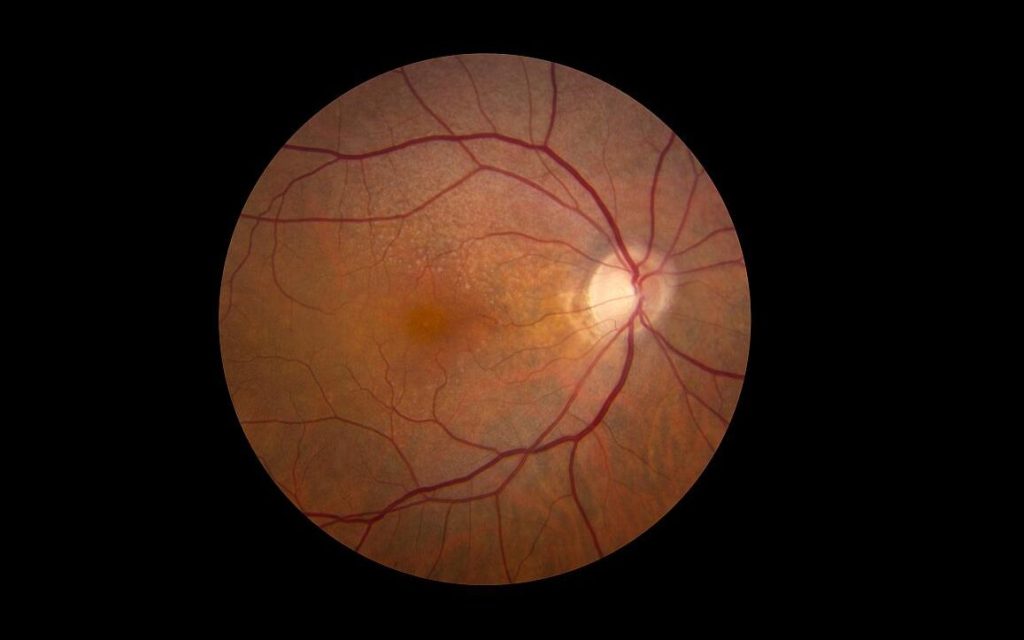
Retina showing reticular pseudodrusen. Although they can infrequently appear in individuals with no other apparent pathology, their highest rates of occurrence are in association with age-related macular degeneration (AMD), for which they hold clinical significance by being highly correlated with end-stage disease sub-types, choroidal neovascularisation and geographic atrophy. Credit: National Eye Institute
In a new study, UC Irvine researchers explore a possible therapy for addressing “aging” in the eye and for preventing diseases such as age-related macular degeneration (AMD).
“We show the potential for reversing age-related vision loss,” says Dorota Skowronska-Krawczyk, PhD, an associate professor in the Department of Physiology and Biophysics and the Department of Ophthalmology and Visual Sciences. The study was a collaboration between researchers from UC Irvine, the Polish Academy of Sciences, and the Health and Medical University in Potsdam, Germany.
The work is a follow-up to an earlier study on Elongation of Very Long Chain Fatty Acids Protein 2 (ELOVL2), an established biomarker of age. “We showed that we have lower vision when this ELOVL2 enzyme isn’t active,” says Skowronska-Krawczyk, also a faculty member in the Robert M. Brunson Center for Translational Vision Research at the UC Irvine School of Medicine. In that work, the researchers found that enhancing ELOVL2 gene expression in aging mice boosted levels of the omega−3 fatty acid docosahexaenoic acid (DHA) in the eye and improved vision.
The more recent study sought to identify a way to bypass the need for the ELOVL2 enzyme.
As we age, changes in lipid metabolism lead to a decline in very-long-chain polyunsaturated fatty acids (VLC-PUFAs) in the retina, which in turn affects our vision and can lead to AMD. The ELOVL2 gene is a key enzyme in the production of VLC-PUFAs as well as DHA.
Injecting aged mice with the polyunsaturated fatty acid improved visual function. “It’s a proof-of-concept for turning lipid injection into a possible therapy,” says Skowronska-Krawczyk. “What is important is that we didn’t see the same effect with DHA.” Others have also questioned the ability of DHA to slow AMD progression.
“Our work really confirms the fact that DHA alone cannot do the work, but we have this other fatty acid that is seemingly working and improving vision in aged animals,” says Skowronska-Krawczyk. “We have also shown on a molecular level that it actually reverses the aging features.”
Furthermore, the researchers found genetic variants in the ELOVL2 enzyme that correlate with faster progression of AMD. “Now we actually have a genetic connection to the disease and its aging aspect,” says Skowronska-Krawczyk, “so we could potentially identify people at higher risk for vision loss progression.” This could lead to not only therapeutic treatment options but also targeted interventions for prevention.
These findings have only further solidified Skowronska-Krawczyk’s view of the importance of the ELOVL2 enzyme. “I am pretty convinced it’s one of the top aging genes that we should look at when we think about anti-aging therapies.”
Looking Beyond the Retina
In a collaboration with researchers from UC San Diego, Skowronska-Krawczyk has also started to explore the role of lipid metabolism in immune system aging. That study found that the lack of ELOVL2 enzyme induces accelerated aging of immune cells, suggesting that systemic lipid supplementation could potentially counteract the effects of age on the immune system. It also suggested that lipid metabolism might play a role in blood cancers.
“Our first study explored a potential therapy to address vision loss,” says Skowronska-Krawczyk, “but with the information we’ve since learned about immune aging, we are hopeful the supplementation therapy will boost the immune system as well.”