Category: Medical Research & Technology

Cannabis Use Risks Harmful Drug–Drug Interactions

Photo by Crystalweed Cannabis on Unsplash

Using cannabis alongside other drugs may come with a significant risk of harmful drug-drug interactions, according to a pair of new studies in the journal Drug Metabolism and Disposition.

The researchers examined cannabinoids and their major metabolites found in the blood of cannabis users and found that they interfere with two families of enzymes that help metabolise a wide range of prescription drugs. Because of this, the drugs’ effectiveness might decrease or their negative effects might increase with too much building up in the body, causing unintended side effects such as toxicity or accidental overdose.

The authors note that despite the early stage of this research, it is important to be careful when using cannabis with other prescription drugs.

“Physicians need to be aware of the possibility of toxicity or lack of response when patients are using cannabinoids,” said Professor Philip Lazarus, senior author on the papers. “It’s one thing if you’re young and healthy and smoke cannabis once in a while, but for older people who are using medications, taking CBD or medicinal marijuana may negatively impact their treatment.”

One study focused on a family of enzymes known as cytochrome P450s (CYPs), whereas the other looked at UDP-glucuronosyltransferases (UGTs), another enzyme family. Together, these two enzyme families help metabolise and eliminate more than 70% of the most commonly used drugs from the body.

While some previous research focused on potential drug interactions caused by cannabinoids, this new research provides the first known comprehensive look at the interaction between three of the most abundant cannabinoids (tetrahydrocannabinol (THC), cannabidiol (CBD) and cannabinol (CBN)) and their metabolites and all of the major CYP enzymes. This is also the first known research that looked for interactions between these cannabinoids and UGT enzymes, specifically.

“Cannabinoids stay in your body only for about 30 minutes before they are rapidly broken down,” said first author Shamema Nasrin. “The metabolites that result from that process stay in your body for much longer – up to 14 days – and at higher concentrations than cannabinoids and have been overlooked in previous studies, which is why we thought we should focus on those as well.”

Using human kidney cells, they found that cannabinoids and the major THC metabolites strongly inhibited several CYP enzymes. One key discovery was that one of the most abundant THC metabolites, called THC-COO-Gluc seems to play a major role in inhibiting several key enzymes in the liver. Looking at the UGT enzyme family, the researchers found that all three cannabinoids, but especially CBD, inhibited two of the primary UGT enzymes present in the liver. CBD was also found to block three enzymes that account for about 95 percent of kidney UGT metabolism, which helps clear toxins and certain drugs from the body.

“If you have a kidney disease or you are taking one or more drugs that are metabolised primarily through the kidney and you’re also smoking marijuana, you could be inhibiting normal kidney function, and it may have long-term effects for you,” Prof Lazarus said.

Nasrin added that these interactions between CBD and UGT enzymes could be inhibiting kidney function in patients with acute kidney disease or kidney cancer, who may be using CBD to treat pain or to try to reduce the side effects from anti-cancer drugs.

“Taking CBD or marijuana might help your pain but could be making the other drug you’re taking more toxic, and that increase in toxicity may mean that you can’t continue taking that drug,” Nasrin said. “So, there could be serious ramifications for anti-cancer drugs, and that’s only one example of the many drugs that could potentially be affected by the cannabinoid-enzyme interactions we’re seeing.”

Source: Washington State University

US Army Scientists Develop Novel Anthrax Treatment

Capsule removal from Bacillus anthracis by treatment with Capsule Depolymerase (capsule shown in red). Credit: Photomicrograph by Wilson J. Ribot, USAMRIID

By modifying an enzyme produced by the bacterium that causes anthrax, US Army scientists were able to protect mice from infection with the deadly disease. 

Their findings, published in Science Translational Medicine, suggest a potential therapeutic strategy for treating multidrug-resistant strains of anthrax, and could aid in the development of new treatments for other bacterial infections.

Bacillus anthracis, the bacterium that causes anthrax, is one of the most significant bioterrorism threats, as well as a public health challenge in many places around the world. Its disease-causing capability arised from three main components – lethal toxin, oedema toxin, and the capsule. Researchers in this study developed a method to degrade the capsule surrounding the bacterium, allowing it to be ingested and destroyed by white blood cells, reducing virulence.

There is increasing concern about strains of anthrax that appear to be resistant to treatment with known antibiotics, said Arthur M. Friedlander, MD, the paper’s senior author. He and his team explored alternative treatment approaches that do not rely on the use of antibiotic drugs.

One promising avenue is to make the bacterium more susceptible to the innate immune system. Enzymes known as capsular depolymerases, which are naturally produced by several classes of bacteria, have emerged as a potential new line of antivirulence agents.

“Identification of the capsule depolymerase enzyme within the anthrax bacillus led us to attempt to use that enzyme to remove the capsule,” said Friedlander. “When this proved successful, we utilised recombinant DNA technology and protein engineering methods to engineer and reconfigure the enzyme in new ways.”

Those “engineering changes” included enhancing stability and making production easier, and pegylation, to improve pharmacokinetics. The team then tested the pegylated enzyme, known as PEG-CapD-CPS334C, to be sure it had retained its enzymatic activity.

In the study, 10 out of 10 mice infected with anthrax spores from a nontoxigenic encapsulated strain were completely protected after treatment with PEG-CapD-CPS334C, compared to only 1 of 10 control mice surviving. Similarly, treatment of mice infected with a fully virulent encapsulated strain using PEG-CapD-CPS334C protected 8 of 10, while only 2 of 10 controls survived.

“This strategy renders B. anthracis susceptible to the innate immune responses and does not rely on antibiotics,” the authors concluded. “These findings suggest that enzyme-catalysed removal of the capsule may be a potential therapeutic strategy for the treatment of multidrug-resistant anthrax and other bacterial infections.”

It could also allow the treatment of soldiers exposed to anthrax through natural means or enemy attacks.

Source: EurekAlert!

Differences in Drug Onset Explain Development of Resistance

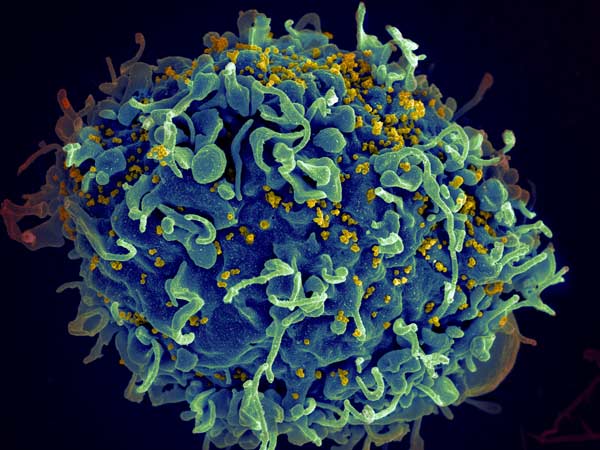
HIV invading a human cell
HIV invading a human cell: Credit NIH

Researchers examining the development of resistance to HIV drugs have uncovered a mechanism of drug resistance development in combination therapy, where ‘windows’ open up for resistance to develop.

In the late 1980s, when HIV treatments were first introduced, patients would often develop resistance to those treatments within six months. The introduction of triple-drug treatment regimens in the 1990s was intended to rectify that. Even if the virus developed resistance to one drug, two others would still knock it out – in theory. Unfortunately, some patients still develop resistance, leaving scientists with a critical question to answer: Why?

“There’s all these things that we still don’t understand, like why do we even get resistance when treating with three drugs,” said San Francisco State University Associate Professor of Biology Pleuni Pennings. “We understand why it is becoming less common, but it should have been zero all along.”

Prof Pennings and her colleagues offer explanations for this phenomenon in a study published in eLife.

Several interesting observations were noted from analysis of HIV patient records. Drug resistance can evolve years after successful therapy, often the result of sequential mutations that occur in a predictable order. Current models could not explain these observations, and while some studies identify mutations that confer drug resistance, they don’t address how and where they arise.

Drawing on two computational models, the researchers suggest that these observations may result from drug heterogeneity over time and throughout the body. While patients receive three HIV therapies simultaneously, drugs have different half-lives and patients do not always adhere to therapy regimens. This could create opportunities for drug resistance evolution, during a window when only one drug is active. Drugs also don’t uniformly penetrate the entire body, meaning that in some locations in a patient’s body, only one of the drugs might be active, creating another evolution and escape opportunity.

“I think one main reason why we should care is actually not because of HIV but because of drug resistance in other situations,” Prof Pennings explained.

Although drug resistance among patients with HIV is fairly low, drug resistance to multidrug therapies is a big problem for diseases such as malaria and tuberculosis. In addition, the COVID pandemic and the rise of variants show how our understanding of evolving pathogens is still lacking.

“In a way, HIV is the poster child of how we solved drug resistance. … [But] if we don’t understand how we did it, then it’s really hard to take these lessons to other situations,” Prof Pennings said.

Source: San Francisco State University

Understanding Mechanisms of Antibiotic Resistance

Source: NCI

If nothing is done, the problem of multidrug-resistant bacterial infections could be catastrophic by 2050, killing nearly 10 million people each year, according to experts’ predictions.

One person seeking solutions is Joseph Boll, assistant professor of biology at The University of Texas at Arlington, to identify and inhibit the defense mechanisms of Acinetobacter baumannii, a common pathogen in hospitals and clinical settings.

A. baumannii can cause infections in the blood, urinary tract and lungs, or in wounds in other parts of the body. Antibiotics are usually used to treat the infections, but many strains are resistant, including drugs of last resort, carbapenems.

“In previous research, we discovered that when A. baumannii experiences stress, such as antibiotic treatment, it modifies its cell envelope to tolerate the antibiotic for extended periods of time,” Prof Boll said. “Specific modifications allow the bacteria to survive long enough to acquire true antibiotic resistance, which can lead to antibiotic treatment failure. This can happen within 24 hours of antibiotic exposure.”

His team expects to identify what adaptations in the cell envelope allow the pathogen to survive in the presence of antibiotics and how survival contributes to the acquisition of true resistance.

In a recent study published in mBio, the team demonstrated that two LD-transpeptidase enzymes remodel A. baumannii’s cell envelope to promote its survival when under stress, such as the kind experienced during antibiotic treatment.

With this breakthrough, Hannah Bovermann, a senior double-major in biology and microbiology, is dissecting the genes that encode the bacteria’s LD-transpeptidases to learn what stress conditions induce their activation. She isolates the LD-transpeptidase promoters, the part of the DNA that controls when other parts of DNA are used, and glues it to a different gene whose function is to turn the bacterial cell blue. When the cell is in an environment where it wants to modify its cell envelope to protect itself, it turns blue, letting her observe the timing of the change.

To provoke this reaction, she administers antibiotics, experiments with various temperature changes, exposes the cell to pH gradients and subjects the cell to nutrient deprivations.

“Each response brings us closer to an understanding of how cell envelope modifications keep the bacterial cell intact in stress,” Bovermann said.

The researchers hope to find new targets on the cell surface for antibiotics to attack, strengthening existing medications’ potency against A. baumannii infections.

Clinicians have been pushed into using combinatorial therapies, where multiple drugs are employed to treat bacterial infections, but even those methods are becoming increasingly ineffective, Prof Boll said.

“It has become a game. Researchers discover a new antimicrobial, then bacteria become resistant to it. We are running out of options,” Prof Boll said. “Bacterial resistance is quickly outpacing new antibiotic development.”

Source: EurekAlert!

Nicotine Linked to Sleep Apnoea Risk

Source: Pawel Czerwinski on Unsplash

In a first-of-its-kind, scientists from the Heart Research Institute (HRI) have made the link between amounts of nicotine in the blood and their sleep apnoea risk.

Sleep apnoea occurs when a person’s throat and upper airway become partly or totally blocked during sleep, causing short periods where breathing ceases.

In a new paper published in ESC Heart Failure, Heart Research Institute (HRI) scientists found increases in nicotine levels were associated with a 2.3 minute increase in the time spent with oxygen saturations below 90%.

One of the markers of severity of sleep apnoea is time spent with an oxygen saturation less than 90%.

Lead researcher Dr John O’Sullivan, said this meant that for every cigarette a person smoked, the more they increased the risk of “dangerously low” oxygen levels.

“People who spend more time with an oxygen saturation less than 90 percent end up with more cardiovascular death than people who don’t,” Dr O’Sullivan said.

“We know smoking is bad for the heart – it’s one of the major risks for heart attacks – and although smoking is known to reduce oxygen concentration in the blood, the interaction of smoking with sleep apnoea has not been quantified. Using blood concentrations of the major nicotine metabolite, we were able for the first time to quantify the effect of smoking on oxygen concentrations at night in people with sleep apnoea.

“A standardised increase in levels of this metabolite was associated with 2.3 more minutes with an oxygen concentration less than 90 percent in people with sleep apnea. Time with an oxygen concentration less than 90% is a proven indicator of bad cardiovascular outcome.”

Sleep apnoea and congestive heart failure comorbidities are common, but their interaction is unclear. To find out more, Dr O’Sullivan’s team used hundreds metabolites to understand this interaction.

“Believe it or not, stiff heart failure – when the heart muscle can still pump blood but is stiff and cannot relax properly – is the most common form of heart failure today and we have almost no treatment options,” Dr O’Sullivan said.

“We measured molecules in the blood called metabolites and looked at the changes in these metabolites and related these to the severity of sleep apnoea.”

Metabolomics is a relatively new field of study that investigates metabolites, which are the components of your metabolism and play key roles in disease. They can provide insight into how one disease is linked to another, like in this case the consequences of sleep apnea and heart failure. Several metabolites are also key fuels for the working heart, and others form the units of energy by which the heart works.

The team studied metabolites and lipids in 3443 people from two US studies, including the landmark Framingham study.

Dr O’Sullivan said Framingham was known as the “town that changed America” because of the multi-generational study started in 1948 that subsequently identified the cardiovascular risk factors we still use today. Much research using this study is openly available internationally, enabling researchers around the world.

“Accurate measurement of disease combined with blood metabolite levels is far more accurate than self-reported questionnaires – that’s one of the strengths of this study,” he said.

While sleep apnoea is very common (up to one in four adults), its consequences and interactions with other diseases remain poorly understood. Almost no studies  have sleep study data, heart failure data, and metabolomic data in the same individuals, which is a major new feature of this study.

Source: Heart Research Institute

Why Some Drugs Have Side Effects

Photo by Myriam Zilles on Unsplash

Researchers have discovered how unwanted side effects can result from how some drugs affect various membrane-spanning proteins in addition to their intended target. The findings, published in PNAS, illuminate one of the main problems of drug discovery and point to new strategies to overcome it.

Any class of drug can have side effects, but those that interact directly with cellular membranes have been especially problematic. “Those drugs tend to affect many membrane proteins, and we suspected that there’s some kind of non-specific mechanism at work,” said first author Dr Radda Rusinova, assistant professor of research in physiology and biophysics at Weill Cornell Medicine. “We wanted to see whether it could be linked to the cell membrane.”

Dr Rusinova and her colleagues used sensitive assays that allowed them to compare how different drugs affected the activities of two channel proteins that span membranes: the gramicidin ion channel and a potassium channel called KcsA. Gramicidin was used to measure the magnitude of drugs’ effect on the membrane while KcsA reflected effects these drugs could have on typical membrane proteins.  They found that membrane-associated drugs can affect KcsA in at least three ways: by interacting directly with the proteins, by interfering with the proteins’ structural connections to the membrane, or by causing broad changes in membrane characteristics such as thickness or elasticity.

Changes in membrane characteristics have well-known effects on the gramicidin ion channel, an antibiotic isolated from bacteria that has long been used as a standard tool for studying such changes. “Gramicidin is a probe essentially for changes in bilayer and membrane properties, and will report on the magnitude of the changes,” said Dr. Rusinova.

“But we needed to go further to see how a more typical cell membrane protein would react,” Dr. Rusinova said. KcsA belongs to a class of proteins – potassium channels – that drive many aspects of cell physiology in everything from bacteria to humans, making it a good comparative probe.

The comparative assay results revealed a more nuanced process than the  straightforward model currently used to explain how membrane-binding drugs can affect membrane-spanning proteins.

“The more data that Dr Rusinova got, the more it became apparent that this simple model did not actually cover the full spectrum of effects that we saw,” said senior author Dr Olaf Andersen, professor of physiology and biophysics.

“The investigators who are looking into molecules that can move into the cell membrane need to worry about at least three mechanisms for off-target effects,” Dr Rusinova said.

However, not all is bad news: in some cases, off-target effects at the cellular level cause no trouble to the organism, and in a few instances they can even be beneficial. Dr Rusinova points to two of the drugs her team tested as an example: amiodarone, a heart medication whose membrane-mediated effects actually boost its efficacy, and troglitazone, an anti-diabetic drug whose side effects included liver toxicity, ultimately forcing regulators to pull it from the market.

The investigators hope to develop more predictive models for such off-target effects. “We would like to determine the structural characteristics of a membrane protein that would make it more or less sensitive to bilayer effects,” Dr Rusinova said.

Source: Weill Cornell Medicine

Biological Research Often Incorrectly Reports Sex Differences

Photo by Tim Mossholder on Unsplash

An analysis of published studies from a range of biological specialties shows that when data are reported by sex, critical statistical analyses are often missing and the findings are likely to be reported in misleading ways.

The analysis was published in the journal eLife.

“We found that when researchers report that males and females respond differently to a manipulation such as a drug treatment, 70% of the time the researchers have not actually compared those responses statistically at all,” said senior author Donna Maney, a professor of neuroscience in Emory’s Department of Psychology. “In other words, an alarming percentage of claims of sex differences are not backed by sufficient evidence.”

In the articles lacking the proper evidence, she added, sex-specific effects were claimed almost 90% of the time. In contrast, authors that tested statistically for sex-specific effects only reported them 63% of the time.

”Our results suggest that researchers are predisposed to finding sex differences and that sex-specific effects are likely over-reported in the literature,” Prof Maney said.

The problem is so pervasive not even her own work was safe. “Once I realised how prevalent it is, I went back and checked my own published articles and there it was,” she said. “I myself have claimed a sex difference without comparing males and females statistically.”

Prof Maney stressed that the problem should not be discounted; it is becoming increasingly serious, she said, because of mounting pressure from funding agencies and journals to study both sexes, and interest from the medical community to develop sex-specific treatments.

Better training and oversight are needed to ensure scientific rigor in research on sex differences, the authors wrote: “We call upon funding agencies, journal editors and our colleagues to raise the bar when it comes to testing for and reporting sex differences.”

Historically, biomedical research has often included just one sex, usually biased toward males. In recent decades, laws have been passed requiring US medical research to include females in clinical trials and report the sex of human participants or animal subjects.

“If you’re trying to model anything relevant to a general population, you should include both sexes,” Prof Maney explained. “There are a lot of ways that animals can vary, and sex is one of them. Leaving out half of the population makes a study less rigorous.”

As more studies consider sex-based differences, Maney adds, it is important to ensure that the methods underlying their analyses are sound.

For the analysis, Prof Maney and co-author Yesenia Garcia-Sifuentes, PhD candidate, looked at 147 studies published in 2019 to see what is used for evidence of sex differences. The studies ranged across nine different biological disciplines, including field studies on giraffes and immune responses in humans.

The studies that were analysed all included both males and females and separated the data by sex. Garcia-Sifuentes and Prof Maney found that the sexes were compared, either statistically or by assertion, in 80% of the articles. Of those articles, sex differences were reported in 70% of them and of those treated as a major finding in about half.

Statistical errors were seen in some studies, with a significant difference for one sex but not the other counted as a difference between them.  The problem with that approach is that the statistical tests conducted on each sex can’t give “yes” or “no” answers about whether the treatment had an effect.

“Comparing the outcome of two independent tests is like comparing a ‘maybe so’ with an ‘I don’t know’ or ‘too soon to tell,'” Maney explains. “You’re just guessing. To show actual evidence that the response to treatment differed between females and males, you need to show statistically that the effect of treatment depended on sex. That is, to claim a ‘sex-specific’ effect, you must demonstrate that the effect in one sex was statistically different from the effect in the other.”

Conversely, their analysis also encountered strategies that could mask sex differences, such as pooling data from males and females without testing for a difference.

“At this moment in history, the stakes are high,” Maney says. “Misreported findings may affect health care decisions in dangerous ways. Particularly in cases where sex-based differences may be used to determine what treatment someone gets for a particular condition, we need to proceed cautiously. We need to hold ourselves to a very high standard when it comes to scientific rigor.”

Source: EurekAlert!

New Type of Skin Cell Reveals Secrets of Inflammation

The surprise discovery of a new type of cell explains how distress to the skin early in life may prime a person for inflammatory skin disease later, according to a new study in Nature. This finding will likely lead to treatments for autoimmune disorders like scleroderma, and inform understanding of inflammatory disease.

“The results reinforce the idea that what you’re exposed to initially may have lasting ramifications,” said lead researcher Michael Rosenblum, MD, PhD. “It appears that early exposure to inflammation can, through these cells we discovered, imprint an ability for tissues to develop inflammatory disease later in life.”

The team came across this new type of cell while investigating the effects of certain actions known to evoke immune response in mice. One of these actions involved knocking out a group of skin cells that suppress the immune system. Without that regulation, said Dr Rosenblum, a unique cell was observed that seemed to act as a shelter for pathogenic immune cells not typically seen in skin tissues.

“We had to knock out one cell population to see that they were controlling the growth and capacity of these other, unknown cells,” he said, noting that the new cells only became apparent in the tissue exposed to inflammatory triggers. “What normally would be a deserted island on the skin was now inhabited by all these strangers,” he said.

The team dubbed these strangers ‘TIFFs’ (Th2-interacting fascial fibroblasts) after the Th2 immune cells that they help to house. The location of TIFFs in the skin suggests that they belong to a group of cells that make up the fibrous connective tissue that is fascia, said lead author Ian Boothby, a graduate student in Dr Rosenblum’s lab.

“Because most organs have fascia of some sort, what we’re learning about TIFFs in skin may well be widely applicable to the rest of the body, meaning that these cells may play a role in a huge number of inflammatory diseases,” he said.

Boothby and Dr Rosenblum when skin without regulatory cells receives inflammatory triggers, the TIFFs spread like wildfire and become a sort of holding pen for the Th2 immune cells. Later in life, when there is even a small insult to the skin, Dr Rosenblum said, the TIFFs open their floodgates, unleashing the Th2 cells.

It seems that, through these cells, early exposure to inflammalation can leave a life-long imprint.

“All you need to do is push the immune system just a little bit, with a wound or with stress, to unleash all the pathogenic cells living in these TIFFs and create an exaggerated inflammatory response,” he said.

The researchers hypothesise that the exaggerated response may manifest as the creation of fibroses in the fascia, the driving force behind inflammatory skin diseases such as scleroderma.

To confirm the presence of TIFFs in human skin, the team obtained samples from volunteers with eosinophilic fasciitis (EF), a rare inflammatory disorder in which eosinophils build up in the skin fascia, the fibrous tissue between the skin and the muscles below it.

Comparing the EF samples to those of healthy skin, the researchers found TIFFs in both, but looked completely different. In healthy skin, the fascia forms a thin, spidery network between fat cells, while in the EF skin sample, the cells had expanded to form thick bands of fibrous tissue.

Revealing the mysteries of inflammation
TIFFs appear to be present in every organ, said Dr Rosenblum, usually found in the fascia surrounding major organs and serve a role in maintaining structure. They’re also prone to interacting with immune cells. He postulates that TIFFs might have evolved as a sort of emergency brigade in case of injury, able to jump-start repair in the case of internal injury.

“In patients with scleroderma or other fibrosing diseases like EF, that repair program may be kind of co-opted, resulting in this chronic wound-healing response,” said Dr Rosenblum. “If we can understand the biology of these cells, we can come in with drugs that revert them back to what they’re supposed to be doing.”

Source: University of California San Francisco

Atmospheric Plasma Device Boosts Bone Regeneration

Photo by Zoltan Tasi on Unsplash

Scientists in Japan have developed a plasma device that promotes bone regeneration in fractures.

Unlike blood plasma, plasma here refers to the fourth state of matter, effectively a highly ionised gas, which has been long investigated as an effective surgical scalpel which cauterises tissue as it cuts. Other recent applications of plasma technology include surface sterilisation.

Now, a new type of plasma device, termed non-thermal atmospheric pressure plasma (NTAPP), was successfully tested in healing of bone fractures in animal bone defect models. It is cooler than most plasmas that are typically used. In a study published in PLOS ONE, researchers from Osaka City University detailed their findings using the technology in this world-first application.

Acceleration of cell growth
“NTAPP is considered a new therapeutic method,” said first author Akiyoshi Shimatani, “as it has been shown to accelerate cell growth when applied at low enough levels.” He explained that in an ambient atmosphere it can generate highly reactive oxygen and nitrogen species (RONS) which can be directly exposed to tissues.

Indirect treatments have shown the potential advantages of plasma in supporting the creation of stem cells that cause reactive oxygen species and in inducing osteogenic differentiation and bone formation, however, as the team points out there is no report on directly using NTAPP for bone fracture therapy. “Direct exposure of NTAPP is a key part of this study” states Jun-Seok Oh, professor at the OCU Graduate School of Engineering and advisor to the study, “It required a device specifically designed to generate and deliver RONS to areas of the bone defect ‘effectively’.”

The research group developed a pencil-like plasma device that can effectively generate and deliver RONS to an animal model with a well-established critical bone defect, allowing the team to search for the optimal exposure conditions. Comparing groups that were treated with NTAPP for 5, 10, and 15 minutes to control groups with no plasma administered, micro-CT images at eight weeks showed the 10-minute treatment time as the most successful bone regeneration with 1.51 times larger bone volume than the control group.

Since micro-CT images could not determine whether a bone defect has been filled with new bone, tissue or both, the team also ran a histological analysis and confirmed bone defects in the groups treated with plasma were in fact filled with new bone, and had no tissue or gaps like the control groups.

Precision therapy
The biological effect of plasma, like other therapies, depends on the treatment dose delivered into the targets. Although future research will be needed to clarify why the study saw the most bone regeneration during the 10-minute treatment period, surface wettability is understood to promote greater cell spreading and adhesion to biomaterials and implants. Hiroaki Nakamura, professor at the Graduate School of Medicine explained: “We wondered if something similar was occurring where we saw a strong generation of new bone. And we found that compared to the control group, bone surface of the plasma-treated group as statistically and significantly more hydrophilic.”

The research team hopes the plasma device they developed can be applied for surgical use.

Source: Osaka City University

‘Sutrodes’ Could Treat Spleen Conditions Using Electricity

Photo by Zoltan Tasi on Unsplash

Using a flexible ‘sutrode’ – a combination of suture and electrode – a group of researchers has advanced a way to treat spleen conditions by applying only electrical current.

Electroceuticals, where electrical stimulation is used to modify biological functions, could minimally invasively treat medical conditions and result in few side effects.  

The work, which appears in the Nature Journal of Communications Biology, builds on previous studies when the team introduced the sutrode to the world just over a year ago. This graphene-based electrode is an electrical stimulation device that could replace the use of pharmaceuticals to treat a range of medical conditions. The sutrode, created using a technique called fibre wet spinning, has an electrode’s electrical properties and a suture’s mechanical properties.

“The flexibility and superb sensitivity of the sutrode is allowing us to expand our understanding of how the nervous system controls main body organs, a critical step towards developing advanced therapies in bioelectronic medicines,” reported the study leader, Professor Romero-Ortega. “Our collaborative work uncovered that the spleen is controlled by different terminal nerves, and that the sutrode can be used to control them, increasing the precision in which the function of this organ can be modulated.”

Paper co-author professor Gordon Wallace said the sutrode can be integrated with delicate neural systems to monitor neural activity.

“This work has widespread implications for regulating the function of the spleen, particularly the efficient regulation of the immune response for electroceutical treatment of range of diseases,” said Prof Wallace. “We have highlighted the ongoing need to develop systems with increased fidelity and spatial resolution. This will not only bring practical applications to the forefront but will enable the unattainable exploration of the human neural system.”

The work also reveals the ability to simultaneously interrogate the four individual neural inputs into the spleen. This new technical and biological achievement will not only bring about practical applications, but also enable a previously unattainable exploration of the human neural system.

Source: University of Houston