By uncovering the subtle difference between two varieties of a protein, researchers from the Pennsylvania may have discovered how to eliminate the weight gain side effects of thiazolidinediones, which were once widely-used diabetes drugs. These findings, published in Genes & Development, could lead to more effective treatment from modified thiazolidinediones, which many likely avoid in its current form due to side effects.
“One small, undiscovered difference between the two forms of a single protein proved to be extremely significant,” said study senior author Mitchell Lazar, professor at the University of Pennsylvania. “Our findings suggest a way to improve on the mechanism of action of thiazolidinedione drugs, which holds promise for eliminating the side effect of weight gain.”
After their introduction in the 1990s, thiazolidinediones, which include rosiglitazone, soon enjoyed widespread use in diabetes. Since then, they have fallen out of favour due to their side effects. This has led some researchers to investigate whether new compounds could be developed that retain these drugs’ therapeutic effects while having fewer side effects.
In their study, Prof Lazar and his team approached this problem by studying thiazolidinediones’ target, PPARgamma (PPARγ), a protein which helps control fat cell production. The scientists examined two lines of mice: One greatly deficient in one form of the protein, PPARγ1, the other greatly deficient in PPARγ2. In the mice, the scientists showed that activating PPARγ1 or PPARγ2 with a thiazolidinedione had an anti-diabetic effect in each case, protecting mice from the metabolic harm of a high-fat diet.
However, the researchers discovered that activation of these two forms has subtly different downstream effects on gene activity. Specifically, in the PPARγ1-deficient mice (in which most of the present PPARγ takes the form of PPARγ2), the thiazolidinedione treatment caused no weight gain.
The finding therefore suggests that it may be possible to realize the benefits of thiazolidinediones without the weight gain side effect, by selectively activating PPARγ2 and not PPARγ1.
“We’re now studying in more detail how PPARγ1 and PPARγ2 work and how they differ, in the hope of finding ways to selectively activate PPARγ2,” Prof Lazar said.
Analysis of a large representative database shows that e-cigarette use is associated with an increased risk of prediabetes, posing a new concern for public health.
“Our study demonstrated a clear association of prediabetes risk with the use of e-cigarettes,” explained lead researcher Shyam Biswal, PhD, at Johns Hopkins Bloomberg School of Public Health. “With both e-cigarette use and prevalence of prediabetes dramatically on the rise in the past decade, our discovery that e-cigarettes carry a similar risk to traditional cigarettes with respect to diabetes is important for understanding and treating vulnerable individuals.”
According to the Centers for Disease Control and Prevention (CDC), traditional cigarette smokers are 30% to 40% more likely than non-smokers to develop type 2 diabetes, which increases their risk for cardiovascular diseases. e-cigarettes are sometimes promoted as a healthier option for cigarette smokers, and e-cigarettes use is rising among younger demographics.
The study analysed 2016–2018 data from the Behavioral Risk Factor Surveillance System (BRFSS), the largest annual nationally representative health survey of US adults. Among the 600 046 respondents, 9% were current e-cigarette users who self-reported prediabetes diagnoses. The data also showed that e-cigarette users have a higher prevalence of high-risk lifestyle factors and worse self-related mental and physical health status than non-smokers.
In this representative sample of US adults, e-cigarette use was associated with greater odds of prediabetes compared to those who did not use e-cigarettes or traditional cigarettes – a worrying link from a public health standpoint.
“We were surprised by the findings associating prediabetes with e-cigarettes because they are touted as a safer alternative, which we now know is not the case,” commented Dr Biswal. “In the case of cigarette smoking, nicotine has a detrimental effect on insulin action, and it appears that e-cigarettes may also have the same effect.”
Prediabetes is fortunately a reversible condition, given appropriate lifestyle management. The authors make a compelling recommendation for targeting the reduction in e-cigarette use and education of young adults to reduce diabetes risk.
“Our effort for smoking cessation has led to a decrease in smoking traditional cigarettes. With this information, it is time for us to ramp up our public health efforts to promote the cessation of e-cigarettes,” cautioned Dr Biswal.
The World Health Organization (WHO) defines prediabetes as a state of intermediate hyperglycaemia using impaired fasting glucose, defined as fasting plasma glucose of 6.1–6.9 mmol/L (110 to 125 mg/dL) and impaired glucose tolerance defined as 2h plasma glucose of 7.8–11.0mmol/L (140–200 mg/dL) after ingestion of 75g of oral glucose or a combination of the two based on a 2h oral glucose tolerance test. It is estimated that by 2030, more than 470 million people worldwide will be diagnosed with prediabetes.
Using in vitro modelling the SARS-CoV-2 infection of human pancreatic cells, researchers have found that COVID infection is likely not associated with an increased new-onset diabetes risk. At the same time, another study has suggested that in hospitalised COVID patients, it may be a temporary form of the disease resulting from the acute stress of viral infection.
The findings, which are to appear in Cell Reports, address concerns raised over the past 18 months that infection with SARS-CoV-2 may trigger new-onset diabetes. However, the supporting evidence for this has remained sparse, with at times conflicting evidence impeding with a proper risk assessment.
The team of researchers at the Icahn School of Medicine at Mount Sinai demonstrated that SARS-CoV-2 targets virtually all types of pancreatic cells, not just the insulin-producing beta cells, using the ACE2 receptor to gain access. However, the infection in the pancreas remained highly circumscribed, largely non-cytopathic and despite high viral burden in infected subsets, promoted only modest cellular perturbations and inflammatory responses.
Similar experimental outcomes were also observed after in vitro infection with endemic coronaviruses not previously associated with diabetes. Taken together, these findings challenge the notion that direct beta cell infection and destruction by SARS-CoV-2 can precipitate diabetes onset.
“Our provisional conclusions indicate that SARS-CoV-2 infection is likely not associated with an increased risk for new-onset diabetes,” said study leader Dirk Homann, MD, Professor of Medicine at Icahn Mount Sinai. “However, a history of SARS-CoV-2 infection may yet promote prolonged glycometabolic perturbations and even an increase in cumulative diabetes risk in vulnerable populations. Over the next few years, we need to pay careful attention to emerging observational and retrospective studies that determine diabetes incidence rates of previously SARS-CoV-2-infected individuals.”
To evaluate permissiveness of human pancreatic islet cells to in vitro SARS-CoV-2 infection, the team of researchers employed an in vitro infection model of primary human pancreatic islets with SARS-CoV-2 as well as endemic human coronaviruses. The team precisely delineated pancreatic infection patterns and associated cellular changes at the single-cell level. Altogether, they found that the extent and consequences of pancreatic SARS-CoV-2 infection, even under in vitro conditions of enhanced virus exposure, remained decidedly limited.
“Concerns surrounding the possibility that infection with SARS-CoV-2, the etiological agent of COVID, may cause new-onset diabetes persist amidst an evolving research landscape,” said Verena van der Heide, MD, PhD, co-first author of the study and postdoctoral research fellow at the Icahn School of Medicine at Mount Sinai. “Our findings stand in notable contrast to three recent reports that also based their speculation about the diabetogenic potential of SARS-CoV-2 on in vitro infection of human islets. As detailed in our manuscript, however, we believe that our careful experimental design and comprehensive analysis strategy make a compelling case for the considerable limits of pancreatic SARS-CoV-2 infection.”
“There are strong epidemiological associations between COVID infection in humans and diabetes, but whether the SARS-CoV-2 virus actually infects and damages the insulin-producing cells in the human pancreas, the so-called ‘beta cells,’ has been highly controversial,” said Andrew Stewart, MD, Director of the Diabetes, Obesity and Metabolism Institute at Icahn Mount Sinai. “This study by Dr. Homann and his collaborators in Mount Sinai’s Precision Immunology Institute and the Department of Microbiology provides strong evidence that SARS-CoV-2 causes little or no damage to beta cells, making it unlikely that COVID infection can predispose to development of Type 1 diabetes.”
The conclusions they came to are in line with a 2020 report by Dr Homann and his team, showing that ACE2 receptors and other entry factors are lacking among islet endocrine cells but readily detected in microvascular and ductal structures of the pancreas.
Meanwhile, a second, separate study of 594 individuals who exhibited signs of diabetes mellitus during the early pandemic showed that half of the 79 patients without a diabetes diagnosis reverted to normal blood sugar levels by one year.
“We believe that the inflammatory stress caused by COVID may be a leading contributor to ‘new-onset’ or newly diagnosed diabetes,” said Sara Cromer, MD, lead author of the second study. “Instead of directly causing diabetes, COVID may push patients with pre-existing but undiagnosed diabetes to see a physician for the first time, where their blood sugar disorder can be clinically diagnosed. Our study showed these individuals had higher inflammatory markers and more frequently required admission to hospital ICUs than COVID patients with pre-existing diabetes.”
An international team of researchers has finally cracked the puzzle of why so many patients with hypertension also have diabetes. Their discovery has shown that glucagon-like peptide-1 (GLP-1) couples the body’s control of blood glucose and blood pressure.
Senior Author Professor Julian Paton at the University of Auckland, said: “We’ve known for a long time that hypertension and diabetes are inextricably linked and have finally discovered the reason, which will now inform new treatment strategies.”
It has long been known that GLP-1 is released from the wall of the gut after eating and acts to stimulate insulin from the pancreas to control blood sugar levels. However, the researchers found that GLP-1 also stimulates the carotid body, a chemoreceptor located in the neck.
Researchers used RNA sequencing to read all the messages of the expressed genes in the carotid body in rats with and without high blood pressure. This led to the finding that the receptor that senses GLP-1 is located in the carotid body, but less so in hypertensive rats.
David Murphy, Professor of Experimental Medicine from Bristol Medical School: Translational Health Sciences (THS) and senior author, explained: “Locating the link required genetic profiling and multiple steps of validation. We never expected to see GLP-1 come up on the radar, so this is very exciting and opens many new opportunities.”
Professor Paton added: “The carotid body is the convergent point where GLP-1 acts to control both blood sugar and blood pressure simultaneously; this is coordinated by the nervous system which is instructed by the carotid body.”
Even when on medication, many patients with hypertension and/or diabetes are at high risk of life-threatening cardiovascular disease. This is because most medications only treat symptoms and not causes of high blood pressure and high sugar.
Professor Rod Jackson, an epidemiologist from the University of Auckland, said: “We’ve known that blood pressure is notoriously difficult to control in patients with high blood sugar, so these findings are really important because by giving GLP-1 we might be able to reduce both sugar and pressure together, and these two factors are major contributors to cardiovascular risk.”
Lead author Audrys Pauža, PhD student in the Bristol Medical School, added: “The prevalence of diabetes and hypertension is increasing throughout the world, and there is an urgent need to address this.
“Drugs targeting the GLP-1 receptor are already approved for use in humans and widely used to treat diabetes. Besides helping to lower blood sugar these drugs also reduce blood pressure, however, the mechanism of this effect wasn’t well understood.
“This research revealed that these drugs may actually work on the carotid bodies to enact their anti-hypertensive effect. Leading from this work, we are already planning translational studies in humans to bring this discovery into practice so that patients most at risk can receive the best treatment available.”
The research has also revealed many novel targets for ongoing functional studies that the team hope will lead to studies in human hypertensive and diabetic patients.
By combining blood glucose measurement with insulin administration in a single device, the complicated process of blood sugar management could be made easier for people with diabetes.
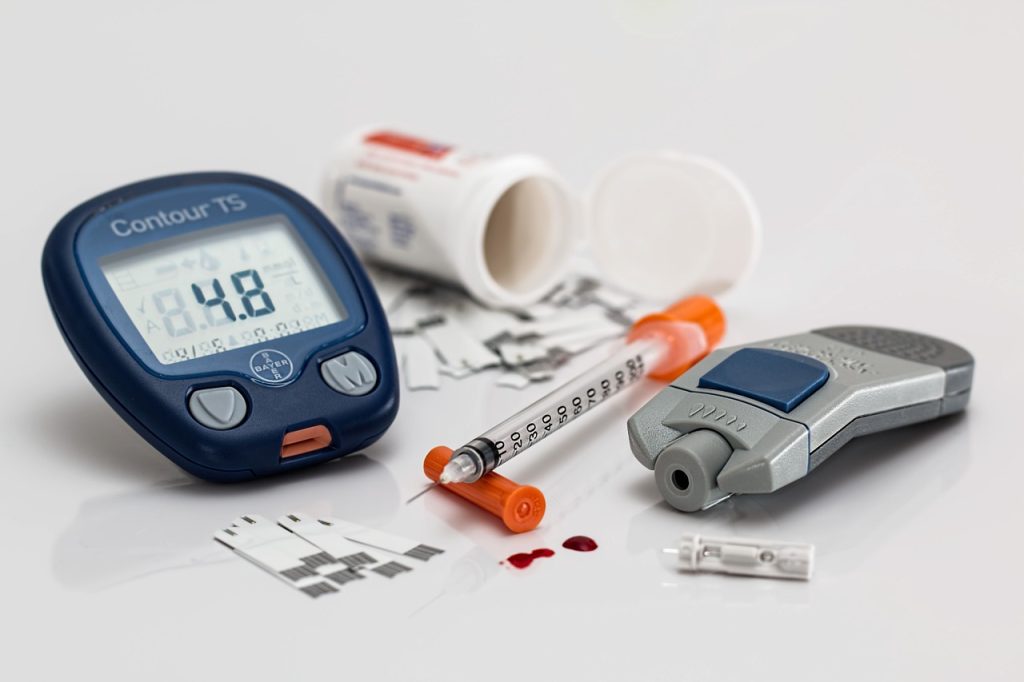
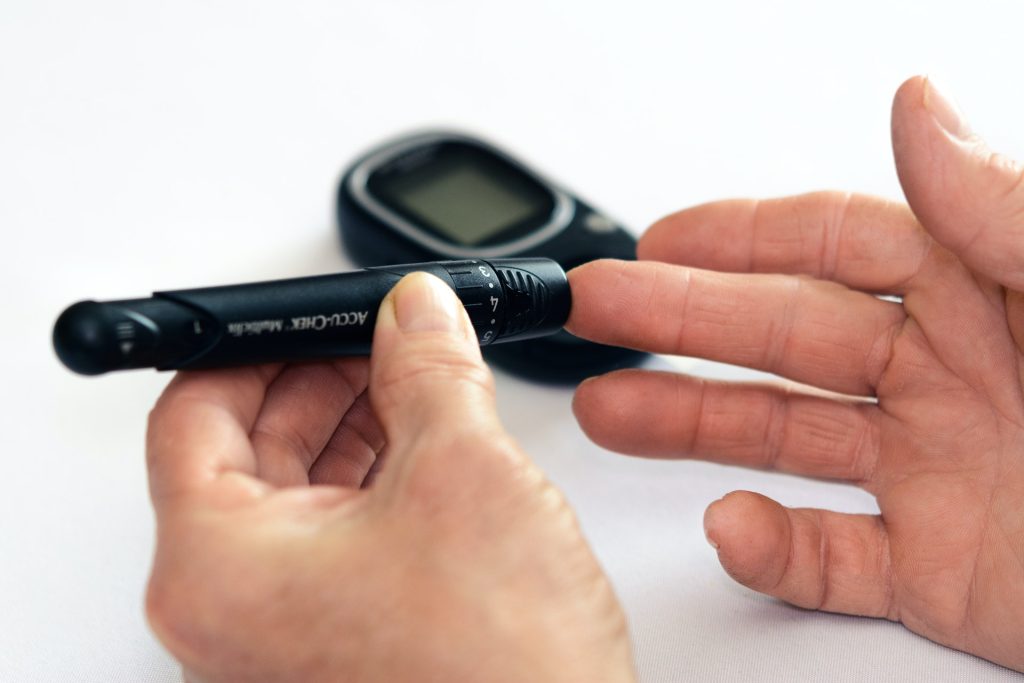
Patients with diabetes often use two types of insulin to control their blood sugar levels: long-acting insulin, which helps control glucose levels over a 24-hour period, and short-acting insulin, which is injected at mealtimes. Patients first measure their blood glucose levels with a glucose meter with a finger prick. They must also estimate how many carbohydrates are in their meal and combine this information with their blood glucose levels to calculate and inject the proper insulin dose.
Existing technologies such as continuous blood glucose monitors and insulin pumps can help with some parts of this process. However, these devices are not widely available, so most patients must rely on finger pricks and syringes. To this end, MIT researchers have developed devices to simplify the process, which they describe in the Journal of Controlled Release.
“Every day, many patients need to do this complicated procedure at least three times,” explained MIT postdoc Hen-Wi Huang. “The main goal of this project is to try to facilitate all of these complex procedures and also to eliminate the requirement for multiple devices. We also used a smartphone camera and deep learning to create an app that identifies and quantifies food content, which can aid in carbohydrate counting.”
The researchers came up with two all-in-one devices, both of which incorporate the new smartphone app. Using a photo, the app estimates the volume of food and carbohydrate content.
The first device that consolidates many of the existing tools that patients use now, including a lancet for drawing blood and glucose test strips. The device conveys blood glucose information to the smartphone app via Bluetooth, and the app works out the correct insulin dose, delivered via a needle in the same device.
“What our device is doing is automating the procedures to prick the skin, collect the blood, calculate the glucose level, and do the computation and insulin injection,” Dr Huang says. “The patient no longer needs a separate lancing device, glucose meter, and insulin pen.”
Many of the components included in this device are already FDA-approved, but the device has not been tested in human patients yet. Tests in pigs showed that the system could accurately measure glucose levels and dispense insulin.
For their second device, the researchers wanted to come up with a system that would require just one needle prick. To achieve that, they designed a novel glucose sensor that could be incorporated into the same needle that is used for insulin injection.
The researchers designed a flexible electronic sensor that can be attached to the needle and measure glucose levels in the interstitial fluid, just below the surface of the skin. Once the needle penetrates the skin, it takes between five and 10 seconds to measure the glucose levels. This information is transmitted to the smartphone app, which calculates the insulin dose and delivers it through the inserted needle.
In tests in the pigs, the researchers showed that they could accurately measure glucose levels with this system, and that glucose levels dropped after insulin injection.
Because this device uses a novel type of glucose sensor, the researchers expect that it will require further development to get to a point where it could be tested in patients.
A newly discovered hormone named fabkin helps regulate metabolism and may play an important role in the development of both type 1 and type 2 diabetes, according to a new study published in Nature.
Fabkin levels were abnormally high in mice and human patients with either type 1 or type 2 diabetes, and blocking the activity of fabkin prevented the development of both forms of diabetes in the animals. Fabkin likely plays a similar role in humans and the hormone complex could be a promising therapeutic target, according to the researchers.
“For many decades, we have been searching for the signal that communicates the status of energy reserves in adipocytes to generate appropriate endocrine responses, such as the insulin production from pancreatic beta cells,” said senior author Gökhan S. Hotamisligil. “We now have identified fabkin as a novel hormone that controls this critical function through a very unusual molecular mechanism.”
Many hormones are involved in the regulation of metabolism, such as insulin and leptin. Fabkin is different from traditional hormones in that it is not a single molecule with a single defined receptor. Instead, fabkin is composed of a functional protein complex consisting of multiple proteins, including fatty acid binding protein 4 (FABP4), adenosine kinase (ADK) and nucleoside diphosphate kinase (NDPK). Through a series of experiments, the researchers determined that fabkin regulates energy signals outside of cells. These signals then act through a family of receptors to control target cell function. In the case of diabetes, fabkin controls the function of beta cells in the pancreas that are responsible for insulin production.
Hotamisligil and colleagues previously discovered that a protein known as FABP4 is secreted from fat cells during lipolysis, the process in which lipids stored within fat cells are broken down, typically in response to starvation. Since then, many studies showed links between circulating FABP4 and metabolic diseases including obesity, diabetes, cardiovascular disease, and cancer. However, the mechanism of action was unknown.
In the new study, the researchers showed that when FABP4 is secreted from fat cells and enters the bloodstream, it binds with the enzymes NDPK and ADK to form the protein complex now identified as fabkin. In this protein complex, FABP4 modifies the activity of NDPK and ADK to regulate levels of molecules known as ATP and ADP, which are the essential units of energy in biology. The researchers discovered that surface receptors on nearby cells sense the changing ratio of ATP to ADP, triggering the cells to respond to the changing energy status. As such, fabkin is able to regulate the function of these target cells.
The pancreas’ beta cells are a target of fabkin and the hormone is a driving force behind the development of diabetes, the researchers showed. When fabkin in mice was neutralised with an antibody, the animals did not develop diabetes. When the antibody was given to obese, diabetic mice, they reverted to a healthy state.
“The discovery of fabkin required us to take a step back and reconsider our fundamental understanding of how hormones work.” said lead author Kacey Prentice. “I am extremely excited to find a new hormone, but even more so about seeing the long-term implications of this discovery.”
A new study has shown that a small molecule inhibitor drug, with the unwieldy designation of PF05175157, originally developed to treat diabetes by Pfizer, may help in the treatment of breast cancer by blocking a key enzyme.
“Our research shows the preclinical, anti-cancer activity using PF05175157 may lead us to bring this drug back into the clinic to help treat patients with breast cancer,” said lead study author Julia Foldi, MD, PhD, a clinical fellow at Yale Cancer Center and Smilow Cancer Hospital. “More studies are needed, but our initial data looks very promising.”
Cancer cells are characterised by altered metabolism. In this study, the Yale team identified new metabolic vulnerabilities in cancer cells that are based on a loss of enzyme diversity. They found that an enzyme called acetyl-CoA-carboxylase-1 (ACC1), is critical for the survival of breast cancer cells. The ACC1 enzyme is the key initial step in fatty acid synthesis. Fatty acids are building blocks of the various types of lipids and fat that are the critical ingredients of cell membranes and play an important role in energy generation in cells. The team’s analysis demonstrated that blocking ACC1 using PF05175157 can inhibit the growth of breast cancer cells grown in mice and also in patient-derived cancer models.
“We are currently testing this drug in combination with other approved breast cancer drugs to see if it could improve their activity, with the hope to bring the most promising combinations to the clinic to help patients with breast cancer,” added Lajos Pusztai, MD, DPhil, Professor of Medicine (Medical Oncology), Director of Breast Cancer Translational Research at Yale Cancer Center, and senior author of the study.
In order to find an alternative to lancets for blood glucose monitoring, researchers applied needle-free jet injection, an emerging but well-developed technique in which a drug is delivered directly with a high-speed narrow jet of fluid.
The study, led by ABI researchers Jiali Xu and James McKeage, demonstrated for the first time that a jet injector could also be used to collect blood samples from humans – that is, release enough blood for glucose sampling, sans needles. The findings appear in the Journal of Diabetes Science and Technology.
Fingertips are the preferred site for blood sampling because they have a high density of blood vessels, they are also sensitive, and pain, skin damage, bruising and risk of infection from regular ‘pricking’ has spurred increasing efforts to develop needle-free methods of blood testing for people with diabetes.
Jet injection, which does not rely on a needle, is an appealing alternative. Jiali Xu of the Auckland Bionengineering Institute (ABI) and her team demonstrated that the technology, using electric motors rather than the standard mechanical spring, could also be used to pierce the skin with a small volume of harmless saline solution, releasing enough blood for glucose concentration measurement.
The study involved 20 healthy participants, each of which received a lancet prick and jet injection on four fingertips through three differently shaped and sized nozzles. “Which were designed to mimic the wound left from a lancet prick, in the anticipation that it might release blood in a way similar to a lancet prick,” said Ms Xu.
Some nozzle shapes performing better than others – a ‘slot’ shaped nozzle released more blood than a circle-shaped nozzle, for instance.
Most of the different jet injection nozzles were generally perceived by the participants, who were unable to see the injections, as no more painful than a standard lancet, and in some cases, less so. A questionnaire was given 24 hours later to assess pain, swelling and bleeding.
People with diabetes may find jet injection more acceptable than using a needle, but the researchers caution against jumping to conclusions. “When you know there’s not a device that is pricking your skin, you could speculate that people will find jet injection more acceptable,” says Professor Andrew Taberner, head of the Bioinstrumentation Lab at the ABI, and Ms Xu’s supervisor. “But we don’t have evidence to back that up. That wasn’t part of this study. We were first trying to find out if it worked, and it did.”
He was pleased, but not surprised. “Diesel mechanics have known for years that you should never put your finger in front of a fuel injector, because it will inject fuel into your finger. They found this out the hard way. But we’re taking advantage of what diesel mechanics discovered accidentally years ago, with a very small amount of harmless liquid, to deliberately release blood.”
The team is now trying to see if they can also extract blood with this technology, allowing for the design of an even smaller nozzle.
Moreover, “our technology has the capability to both deliver and withdraw fluid. No other jet projection technology has that capacity,” said Dr Taberner.
Development and commercialisation of the technology will take time but he believes Ms Xu’s research will contribute to the ultimate aim, of the development of a single lancet-free reversible technology that will allow for both blood sampling and insulin delivery based on the glucose measurement in one device.
“I hope that this research will contribute to that, and the improvement in human healthcare, especially in the management of diabetes,” said Ms Xu.
In a study published in PLOS ONE, scientists report the identification of a new human sensory ability to detect sugars in the mouth with a kind of a molecular ‘calorie detector’. It could help explain why artificially sweetened beverages just don’t have the same appeal as ones containing sugar.
“Our mouth can identify when a sweetener has the potential to deliver calories versus a non-caloric sweetener, which cannot,” said first author Paul Breslin, PhD, a Monell investigator and a professor of Nutritional Sciences at Rutgers University.
The paper describes the first-in-human demonstration of a signaling pathway that uses the sugar glucose, a component of table sugar and high fructose corn syrup, to signal the presence of calories, in addition to the well-studied sweet-taste receptor in taste buds. Glucose is present in many foods, and has been consumed by humans in the form of honey, fruit and other sugar-rich foods.
“Humans love fruit and sugar, as do many other apes, which obtain most of their calories from sugar,” said Prof Breslin.
Recent findings from Monell showed taste bud cells in mice could identify when a sweetener has calories to burn, which prompted the researchers to see whether the ability to sense glucose in the human mouth may also involve this additional pathway. The team wanted to know if the calorie detector is functional, and if it could affect our responses to dietary sugar.
“Now that we know this calorie-detecting taste system is operating in humans, it could help explain the overall preference for sugared beverages over non-caloric sweetener beverages,” said Prof Breslin.
In a series of three human-taste experiments, the team compared oral glucose sensitivity to the ability to sense the artificial sweetener sucralose and to a special form of glucose that cannot be metabolised. “Overall, there are two sweet-sensing pathways in the mouth: one for sweet taste, and another for detecting potential energy-burning sugars,” said coauthor Linda J. Flammer, PhD, a senior research associate at Monell.
The fact that diet fizzy drinks never captured a major share of the beverage market always puzzled Prof Breslin, but he now has a hint: “Diet drinks are not as satisfying as sugared beverages. As a public health initiative, might we get beverages and foods with lower sugar levels to be more rewarding? Now that we know there is this second glucose-sensing system in the mouth, maybe we can tap into it to make healthier beverages that people enjoy drinking.”
Sugar calories are sensed in the gut and blood after swallowing, but this study shows that sugars are identified as different from non-caloric sweeteners in the mouth. “It is remarkable that we evolved a mechanism not only to taste oral sugars as sweet, but also to sense that they have a metabolic or caloric signal,” said Breslin. “This means that the mouth is much smarter than we realised and that it will be difficult to trick it by simply providing non-caloric sweeteners.”
Researchers have revealed insights into how SARS-CoV-2 attacks the insulin-producing cells of the pancreas.
There is mounting evidence of damage to the pancreas and resulting diabetes attributed to COVID, which is of great concern. The virus targets the angiotensin converting enzyme 2 (ACE2) protein on the surface of those cells, and is the subject of a special presentation at this year’s Annual Meeting of the European Association for the Study of Diabetes, given by the University of Siena’s Professor Francesco Dotta.
“The SARS-CoV-2 virus attacks specific host tissues because of the presence of viral receptors on the surface of the target cells. As such, virus binding to ACE2 protein is the key determinant for its entry, propagation and transmissibility,” explained Prof Dotta.
“Multiple studies have shown that older adults and those with chronic medical conditions like heart and lung disease and/or diabetes are at the highest risk for complications from SARS-CoV-2 infections. Moreover, impaired blood sugar control is associated with increased risk of severe COVID, suggesting a link between COVID infection and diabetes. Several reports indicate a wide, although variable, distribution of the ACE2 protein among different tissues.”
Prof Dotta and colleagues studied the ACE2 expression pattern in pancreatic tissue samples of non-diabetic multiorgan donors to better understand the molecular link between COVID and diabetes.
In the ‘normal’ pancreas, ACE2 is highly expressed in microvasculature and in ductal cells. “Importantly, we found that ACE2 was expressed in human pancreatic islets, where it is preferentially expressed in insulin producing beta-cells. We also demonstrated that ACE2 levels were increased under pro-inflammatory conditions, thus confirming the link between inflammation and ACE2 also in pancreatic islet beta cells.”
In order to isolate the mechanism involved in the upregulation of ACE2 induced by inflammation, ACE2 levels were measured in human pancreatic islets pre-treated with Jak1/2 and TYK2 inhibitors, which block inflammation in beta cells, and then exposed to pro-inflammatory conditions.
Prof Dotta said: “We showed that these drugs prevent the ACE2 increase induced by inflammation in human pancreatic islets, demonstrating that SARS-CoV-2 receptor ACE2 is regulated through specific molecular pathways and that its increased expression can be prevented.
“We studied the mechanisms of SARS-CoV-2 virus entry into insulin producing beta cells and we discovered that these cells express the SARS-CoV-2 receptor ACE2.” Other authors have independently confirmed such data.
Of note, additional published data confirmed that SARS-CoV-2 can indeed infect pancreatic insulin-producing cells causing their dysfunction or death. Moreover, during inflammation, ACE2 expression increases several times above standard values.
Prof Dotta concluded: “This means that these insulin-producing beta cells could be even more susceptible to viral infection when inflamed. This finding is also important from a clinical standpoint, since keeping inflammatory status under control in patients with COVID may reduce the expression of ACE2 receptor in beta cells with beneficial effects on blood sugar and metabolic control of patients.”