Category: Healthcare Politics and Regulations

TAC Slams Mbeki over His Views on HIV

Photo: Mohamed Nanabhay (via Flickr, CC BY 2.0)

By Mary-Anne Gontsana for GroundUp

The Treatment Action Campaign (TAC) has called on former president Thabo Mbeki to offer an apology to the public for the “dissident” views he expressed about HIV/AIDS while delivering a speech at the University of South Africa (UNISA) last week Wednesday.

In a scathing statement published by the TAC on Tuesday, the organisation said the “repetition of his scientifically erroneous views with such insensitive arrogance is an insult to the 8 million people living with HIV in SA and the families of 4 million South Africans who have died from HIV over the last three decades”.

Mbeki, who is also the Chancellor at UNISA, was speaking to students, diplomats and members of the media at an event which takes place twice each year and allows students to interact with him on pertinent issues that affect Africans.

The TAC accuses Mbeki of misleading the public when he questions the cause of AIDS. The organisation also goes on to say that they were stunned again by Mbeki’s support of the views of the late former Minister of Health, Manto Tshabalala-Msimang “who was ridiculed for promoting garlic and beetroot as the essential ingredient to manage AIDS, giving it a higher premium than antiretroviral (ARV) treatment”.

“Whilst there may be benefits in all healthy foods, the idea that these vegetables are what are most required in the management of AIDS has no basis in fact and is misleading to the public,” said the statement.

Speaking about HIV/AIDS after a question was raised in the event, Mbeki said the questions that he raised then, he would still raise today. He emphasized that AIDS was a syndrome and not a disease.

“Now this syndrome in medical terms is a group of diseases. So all of these diseases which fall under this syndrome, meningitis, TB, they’re in the syndrome.”

“Causes of Tuberculosis are known and historical, but it’s part of the syndrome. So you can’t say one virus causes all of these illnesses, what you can say is this virus impacts negatively on the immune system, it’s that weakened immune system which results in a syndrome.”

“But there’s a consequence to that kind of thinking which is when you go to test and that test says HIV positive… it does not necessarily mean you’ve got the virus. What it means is that the immune system is responding to something that is threatening the body, and therefore you need a clinical analysis in order to determine what is this thing that the immune system is rejecting. It’s in all the medical documents that go about it, and it’s correct, because then you have to go and do this clinical examination in order to determine which of these illnesses in the syndrome is the one that’s affecting this person. And then you treat the person for that particular disease,” said Mbeki.

Mentioning the views of Tshabalala-Msimang, Mbeki started off by saying as government they had to respond in an effective manner to the HIV/AIDS pandemic and various interventions were needed to do this.

“Which is why the question was raised by the then Minister of Health in a very dramatic fashion. Nutrition. Nutrition is very very critical to solving this problem and that’s why she was saying that we must take garlic and beetroot and so on. She was not saying that with those things you’re going to be cured.”

“She was raising the matter about the importance of nutrition. And those particular types of foods even today have been raised in the context of this Covid-19,” said Mbeki.

The TAC, which successfully campaigned in the 2000s for Mbeki’s government to roll out life-saving medicines, was not impressed.

“There is much ongoing stigma and denial when it comes to HIV and we call on Mr Mbeki to desist from statements about HIV that have no basis in fact,” said the TAC statement.

It said: “The former president’s statements remind us that his unscientific views led to a delay in the rollout of the ARV programme during his presidency.”

The TAC’s General Secretary, Anele Yawa, said that if Mbeki was not prepared to apologise, the organisation would make sure that his HIV denialism and the thousands of deaths that resulted, would be the only thing that he would be remembered for.

These are the facts when it comes to HIV/AIDS under Thabo Mbeki’s presidency

By Nathan Geffen, GroundUp Editor

It’s seldom clear what Thabo Mbeki means when it comes to HIV/AIDS. There is much obfuscation. But the key facts are this:

  1. HIV destroys immune system cells in infected people.
  2. Usually over a period of several years, if left untreated, the immune system collapses, causing the person to become ill with life-threatening infections. This is known as AIDS.
  3. Only antiretroviral medicines can halt this process. They have been so effective that the life-expectancy for people with HIV who take them is brought back to almost normal.
  4. HIV tests are reliable. If proper protocols are followed the odds of an incorrect result are extremely small.
  5. Mbeki’s government delayed the rollout of antiretroviral treatment in the public sector until 2004, even though an effective combination of antiretroviral medicines was available from the mid to late 1990s.
  6. It was only due to pressure from the TAC and its allies that Mbeki’s government made antiretrovirals available in the public sector.
  7. The prices of these medicines also became affordable because of the TAC’s (and its allies) campaigning against pharmaceutical companies. Mbeki’s government was largely AWOL in these efforts, despite Mbeki’s rhetoric about these companies.
  8. Two different studies have estimated that the delayed rollout of antiretrovirals resulted in well over 300 000 avoidable deaths. These estimates are conservative.
  9. These estimates also exclude those who died because they were convinced by Mbeki, Tshabalala-Msimang and their acolytes to try treatments promoted by as alternatives to antiretroviral medicines. The promotion of these nonsense remedies by Mbeki and his health minister continued long after the antiretroviral treatment rollout began.

Geffen was involved with the TAC from 2000 to 2013.

Republished from GroundUp under a Creative Commons Attribution-NoDerivatives 4.0 International License.

Views expressed are those of GroundUp and not Quicknews.

Source: GroundUp
Debunking the Myth that Africa Responded Well to COVID

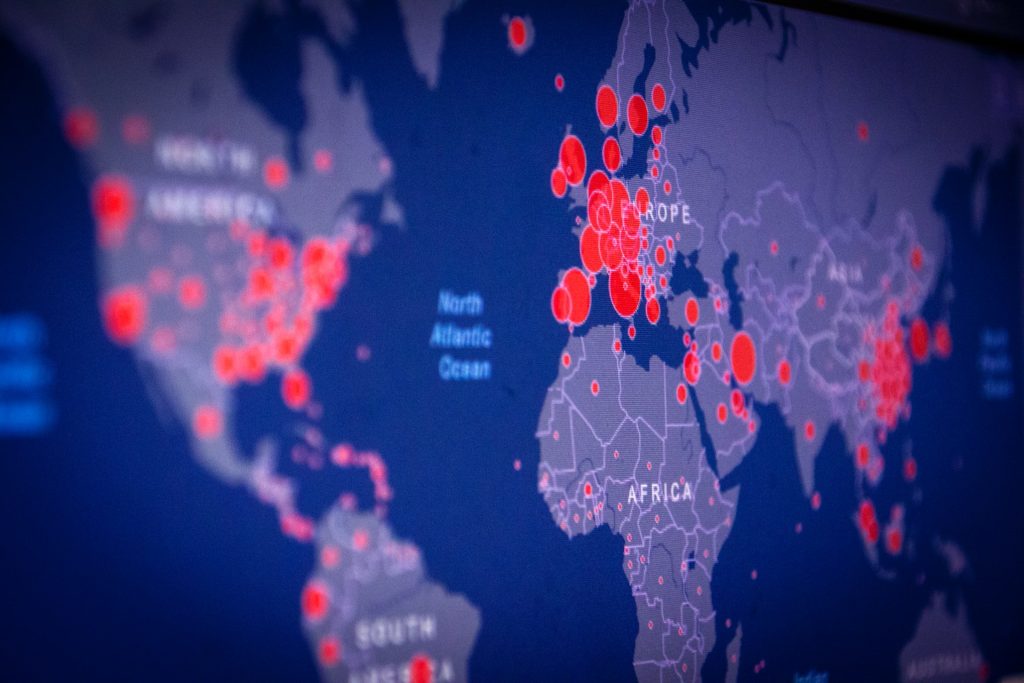
COVID heat map. Photo by Giacomo Carra on Unsplash

By Nathan Geffen and Francois Venter

There is a view being promoted that COVID didn’t hit Africa as badly as the rest of the world. The reason for this, as recently expressed in an article by Boniface Oyugi in The Conversation, was the effective and well-coordinated response of African governments.

We understand the desire to find good news on the continent. But, on balance, the very little evidence available shows that COVID has hit Africa hard. The continent is highly diverse with over 50 states, so broad generalisations should be treated cautiously but, with an exception or two, there is little evidence of an effective response to the COVID pandemic. For one thing, Africa has the lowest vaccination rate of any continent.

Oyugi uses the WHO’s official COVID infection and death statistics to claim that the continent fared better than elsewhere. These state that as of late July, less than 2% of global cases and less than 3% of global deaths occurred in Africa, which has about 17% of the world’s population. (Oyugi also cites a study which pretty much says the same thing.)

COVID test statistics and confirmed COVID deaths don’t paint an accurate picture of how seriously the pandemic has hit a country (see here). If you don’t measure something properly, you can’t conclude that it’s a small problem. COVID tests are typically only administered with any regularity to a small, predominantly better off, part of a country’s population, and countries that test more tend to find more cases. Official COVID death tolls typically count people who have died in hospital with a confirmed positive test result. But it often doesn’t happen this way, especially on a continent with large rural populations and under-resourced hospitals.

Excess deaths: a vital measure

This is why the most important measure of how hard COVID has hit a country is the excess death toll. By excess deaths, we mean the number of deaths that occurred above what you’d expect given recent historical mortality. In sub-Saharan Africa, the only country that has a system capable of reliably estimating this is South Africa. Every week since the beginning of the epidemic, the Medical Research Council (MRC), using death certificate data provided by Home Affairs, has diligently analysed excess deaths. (Many countries wealthier than South Africa do not have as good a system, so it’s something to be proud of.)

The MRC researchers calculate that there have been over 320 000 excess deaths in South Africa since May 2020 (as of July 2022). As they’ve explained, conservatively 85% of these are COVID deaths. It may be as high as 95%. We can conclude that close to 300 000 people have died of COVID in South Africa. Over the past two years about 1 in 200 people in the country have died of this new infection.

The Economist has been reporting excess deaths by country. It states: “Among developing countries that do produce regular mortality statistics, South Africa shows the grimmest picture, after recording three large spikes of fatalities.”

Official deaths are much lower than excess deaths

But if you look at South Africa’s official, and much less accurate, COVID death toll you get a very different picture: Then we’re only 65th worst in the world (source: Worldometer deaths per million people). Lesotho is in 167th place, suggesting it has had a very small epidemic. Is it plausible that an area with a porous border entirely surrounded by South Africa has a completely different epidemic? (See this set of tweets – by one of the authors of South Africa’s weekly mortality report – that explains how the little mortality data we have from Lesotho suggests it had a serious pandemic.)

What about Namibia at position 74 in the Worldometer list, Botswana at 89, Zimbabwe at position 143 and Mozambique at position 190? Is it plausible that this ordering, almost in reverse order of industrial development, accurately reflects how these countries were affected by COVID?

Depending on your bias, you can approach these statistics in two ways. You can be very optimistic and see this as evidence of a smaller epidemic in sub-Saharan Africa. Or you can be realistic and acknowledge that the official numbers are likely very badly undercounted.

We can’t know for sure though because nearly all African governments did not have the systems in place to count excess deaths.

Most African countries need much better death registration systems

Attempts to estimate excess mortality in most African countries are based on almost no data. To the extent that there is data, it supports the view that the numbers have been badly undercounted. For example, a study published in the British Medical Journal, albeit with many caveats, found death rates in developing countries were twice those of rich countries.

During the height of the AIDS pandemic in the 2000s there was much optimism that the massive influx of foreign aid in response could be used to build better health systems. Bits and pieces of evidence do suggest health on the continent has improved. But it’s very disappointing that most countries on the continent still do not have the vital registration systems in place to measure mortality with decent accuracy. This is one of the most important measures of how a population is doing.

By claiming that African governments have responded well to COVID, when there’s no proper evidence to support this, we fail to hold politicians accountable. We also create the impression that institutions like the World Health Organisation and the African Union’s African Centre for Disease Control are more successful than they’ve actually been. This is a disservice to the vast majority of people living in Africa.

Geffen is GroundUp’s editor. Professor Venter is an infectious diseases clinician and head of Ezintsha at Wits University.

This article is republished from GroundUp under a Creative Commons Attribution-NoDerivatives 4.0 International License.

Source: GroundUp

Battling to Increase Nurse Numbers, SA Looks Abroad

Image by Hush Naidoo from Unsplash

The addition of specialist nurses by the Department of Home Affairs to the critical skills list has drawn renewed attention to and criticism of the chronic shortage of nurses in South Africa.

According to a statement by Life Healthcare last year, the country would need as many 26 000 additional nurses in 2022 to meet growing demand.

“Nurses have been on the frontline of the efforts to combat COVID for over two years. They are understandably exhausted and require our support as they continue to deliver quality care to our patients,” the group said, adding that it was embarking on programme to train an additional 3000 nurses per year.

In an open letter on the situation, the Hospital Association of South Africa (HASA) said that there was considerable training capacity and willingness from private sector hospitals, while also noting that the transition to new nursing qualifications has interrupted nurse training.

Last week, following engagement with the Minister of Health, South African Nursing Council, Health Professions Council of South Africa, public hospital CEOs and other experts, the DHA published an updated critical skills list, which was expanded to include specialist nurses and medical specialists.

The registered nurse specialties are intensive/critical care, psychiatric, peri-operative, trauma and paediatric nursing, as well as midwife specialists.

What many seen as the government’s inaction over the situation has not gone without criticism.

Speaking to the the Sunday Tribune, Sibongiseni Delihlazo of the Democratic Nursing Organisation of SA said that they were “extremely angry that we have to import specialist nurses because of the government’s actions.”

He points to falling numbers of nurses being produced each year and the shutting of nursing colleges as a sign of government neglect. World Health Organization studies showed a worldwide nursing shortage of 10 million positions by 2030, which needed an 8% annual increase in new nurses.

“Our country has not adhered to the warning, but has done the opposite,” he said.

Delihlazo said that most nursing students received government funding which was drying up, yet the population growth continued as did public healthcare system demand.

Public healthcare was not releasing nurses for specialist training, as doing so would cause the system to crumbled, Delihlazo said. In addition, local nurses are being effectively poached by first world nations.

“We could have produced our own nurses in a country with serious unemployment issues. The government doesn’t have a strategy to keep our nurses,” he said.

Despite Disagreement, WHO Sounds Highest Alert for Monkeypox

Source: Pixabay CC0

On 22 July, World Health Organisation (WHO) director general Dr Tedros Adhanom Ghebreyesus declared the global spread of monkeypox a Public Health Emergency of International Concern (PHEIC) – a move which went against the recommendation of a special committee. This was the first time since the PHEIC’s inception in 2005 that it had done so. The special committee’s reluctance to recommend a PHEIC has previously drawn criticism from public health experts.

The 21 July meeting of WHO’s Emergency Committee, did not reach a consensus on whether to declare the growing monkeypox outbreak a PHEIC; a narrow majority voting against doing so. But Dr Tedros invoked a PHEIC at a press conference the next day in Geneva. “We have an outbreak that has spread around the world rapidly, through new modes of transmission, about which we understand too little and which meets the criteria in the International Health Regulations,” he said.

Data presented during the meeting including modelling which showed the basic reproduction number (R0) to be above 1 among gay or bisexual men, and below 1 in other groups. For example, in Spain, the estimated R0 is 1.8, in the United Kingdom 1.6, and in Portugal 1.4.

In June, the committee first recommended against declaring a PHEIC , which was roundly criticised by epidemiologists and global health experts. Dr Tedros reconvened the group this week and asked it to reconsider the question. Nine members were against declaring a PHEIC and six in favour, Dr Tedros said at the press conference.

According to Science, the Thursday meeting of the expert panel was followed by tense exchanges via email and text messages between its participants.

One of the objections to a PHEIC was that few deaths had been caused by the disease so far and was not spreading in the general population. Another was that a PHEIC could possibly lead to further stigmatisation of men who have sex with men (MSM), the group primarily affected.

Many gay rights and sexual health advocates were for the PHEIC, as it would help raise awareness and help protect the most at-risk group of MSM.

“Although I’m declaring a public health emergency of international concern, for the moment, this is an outbreak that’s concentrated among men who have sex with men, especially those with multiple sexual partners,” Dr Tedros said. “That means that this is an outbreak that can be stopped with the right strategies in the right groups.”

Those who push for declaring a PHEIC also cited the rising number of monkeypox cases (over 15 000) and the countries affected (70), and that many cases are likely still not being picked up. The virus could also potentially establish itself permanently worldwide – indeed, the CDC reported that two children in the US had been infected.

Sources familiar with the deliberations of the committee said the votes for a PHEIC were driven by those with expertise in monkeypox and LGBT health, and those against by more generalist global heath voices.

According to Science, sources familiar with the committee’s deliberation said that those in favour of a PHEIC had monkeypox and LGBT health expertise, and those against were from a global health standpoint.

While a PHEIC can give the WHO some extra powers, it is the loudest level of alert it can sound. Since its creation in 2005, PHEIC has been declared six times: for outbreaks of H1N1 influenza, polio, Zika, COVID (ongoing), and twice for Ebola outbreaks (one ongoing).

Source: Science.org

Employees’ Rights: What Does The Law Say about COVID Vaccination?

Photo by Gustavo Fring on Pexels

In the past year, the Commission for Conciliation, Mediation and Arbitration (CCMA) has delivered several arbitration awards which have upheld the dismissals of employees who refused to get vaccinated against COVID.

But a recent award has created some confusion about whether this is still allowed and under what circumstances.

On 22 June, CCMA Commissioner Richard Byrne found that it was unfair and unconstitutional for Baroque Medical, which supplies and sells medical equipment, to retrench Kgomotso Tshatshu for refusing to get a Covid vaccination. The company was ordered to pay her 12 months’ salary as compensation (the maximum allowed).

But this contradicts an earlier CCMA award by Commissioner Piet van Staden, delivered in May, who found that Baroque Medical was within its rights to retrench another employee, Cecilia Bessick, who had also refused to get a COVID vaccine.

These conflicting decisions may be understandable, because CCMA arbitration awards do not create binding legal precedent in the same way as court judgments. The most recent CCMA ruling therefore does not set a binding legal precedent that employees cannot be dismissed for refusing to get a COVID vaccine.

The Labour Court has also not yet delivered any binding judgment about whether an employer can fairly dismiss an employee who refuses to get a Covid vaccination. Until this occurs, it is likely the CCMA will continue to give conflicting decisions about whether employers can fairly dismiss employees who refuse to get a vaccine.

Below, we explain what the law currently says about whether an employee can be dismissed for refusing to get a COVID vaccine and under what circumstances.

Labour Relations Act

The Labour Relations Act (LRA) says that an employee can only be dismissed for these reasons: when they are guilty of misconduct; suffer from an incapacity, such as ill health or injury, which prevents them from performing their duties; have to be retrenched because of the economic, structural, technological or similar needs of their employer.

The LRA also requires an employer to follow a fair procedure before dismissing an employee. Usually, this would involve explaining to an employee why they could be dismissed if they refuse to get a Covid vaccine and give the employee an opportunity to explain why they should not be dismissed.

The LRA, however, does not explain whether an employee who refuses to get vaccinated can be dismissed for misconduct or incapacity. The LRA also does not explain whether an employee who refuses to get a Covid vaccine can be retrenched.

Occupational Health and Safety Act

But the Occupational Health and Safety Act does require employers to take all reasonable steps to provide their employees with a safe and healthy working environment. The act also requires employers to take reasonable steps to ensure other people who may be affected by their business activities (such as customers or suppliers) are not exposed to a hazard to their health or safety – such as Covid.

During March, the Minister of Labour issued a Code of Good Practice which explains the steps that an employer should take to manage Covid in their workplace and to comply with their legal duties to provide a safe and healthy working environment.

This code was enacted after a previous directive on managing Covid in the workplace was repealed after the State of Disaster came to an end.

Code of Good Practice

According to the new Code of Good Practice, every employer with at least 20 employees must conduct a “risk assessment” and must develop a COVID plan with the measures it will implement regarding vaccination of employees and when they should be fully vaccinated. When developing the plan, the employer must consult with any representative trade union in its workplace or an employee representative.

The risk assessment and plan, among other things, should identify employees who must be vaccinated and must notify them of their duty to get a vaccination.

The code also states employers can require employees to disclose their vaccination status and to produce a vaccine certificate in order to give effect to the code.

The code further states that employees can lawfully refuse work when there exists a serious risk that they may imminently be exposed to COVID in the workplace. Should this occur, the employer cannot take any action against that employee for refusing to work, such as later dismissing or suspending them from work.

There may be situations where a refusal by employees to work because other employees refuse to get vaccinated, could justify the dismissal of the employees who refuse to get a COVID vaccine. This is because the refusal of many employees to work could affect the ability of a company or business to operate. This could potentially justify retrenchment of employees who refuse to get a COVID vaccine.

However, should an employee refuse to get vaccinated, the code also says that the employer should take steps to reasonably accommodate them in a position that does not require them to be vaccinated. Should an employee produce a valid medical certificate, which provides legitimate reasons why they cannot be vaccinated, the employer can send that employee to another doctor at their own expense.

The code does recognise that it would be unfair to dismiss employees who cannot be vaccinated on valid medical grounds. But, the duty to accommodate employees who refuse to get vaccinated on other grounds would depend on whether an employer has another position available which does not require that employee to be vaccinated. Should the employer not have an alternative position which does not require the employee to be vaccinated, this could be a fair reason to dismiss them.

It is important to note that the code does state that it reflects the policy position of the Department of Labour and that it should be applied until any of its provisions are reversed by a court judgment. Until the Labour Court delivers a binding judgment on when employees can be dismissed for refusing to get a COVID vaccination, it would seem it would be best to follow the provisions of the code.

By Geoffrey Allsop

Republished from GroundUp under a Creative Commons Attribution-NoDerivatives 4.0 International License.

Source: GroundUp

Court Action to Stop Immigrants Being Denied Life-saving Healthcare

Gavel
Photo by Bill Oxford on Unsplash

The rights of immigrant and undocumented women and children to access free healthcare in South Africa will be put to the test in a court challenge launched by SECTION27 in the Gauteng High Court in Johannesburg.

In December 2019, two-year-old Sibusiso Ncube died of poisoning after he was refused treatment at Charlotte Maxeke Hospital because his Zimbabwean mother could not instantly produce his birth certificate or pay R5000, says an affidavit in the court case.

This was not an isolated incident according to Umunyana Rugege, executive director of SECTION27.

“Since 2013, SECTION27 has been repeatedly approached by pregnant migrant women and children under six, who have been denied access to free health services. This is perpetuated through discriminatory subordinate laws and practices,” Rugege says in her affidavit.

“They have routinely been denied access to the health care services, or they are pressured into signing acknowledgements of debt and undertakings to pay for services.”

SECTION27 wants all the relevant ordinances and regulations scrapped. It also seeks an an order that the Minister of Health issue a circular to all provincial health departments recording that all pregnant or lactating women, and children under six, who are not members of medical aid schemes and who have not come to South Africa to obtain health care, be entitled to free health services at any public health establishment, irrespective of their nationality and documentation status.

Rugege says that while the National Health Act does not place any limitation on the right to free health services, there are a range of subordinate laws and practices implemented at hospitals that impose conditions requiring proof of nationality and financial means.

“These laws and practices are unlawful,” she says.

Rugege cited other examples, such as a pregnant asylum seeker who was denied treatment after she was injured in a robbery. She was told she had to pay R2000 before a “file could be opened” at Steve Biko Academic Hospital.

Two months later, when she was eight months pregnant and went to Charlotte Maxeke, she was told she had to pay R20 000 if she wanted treatment and give birth at the hospital. Only after SECTION27 intervened, was she given an appointment, but the night before it she lost her baby.

Another Zimbabwean woman whose child needed emergency surgery was forced to sign an admission of debt for more than R34 000 at the same hospital. Then when he needed further surgery, it was denied because of the outstanding debt. The woman was further told that she would have to pay R5000 for admission and R50 000 for the second surgery.

Again SECTION27 intervened. But in March, when the mother took him back for a checkup, a nurse addressed everyone in the queue and told them that foreign nationals would not be attended to if they did not have money to pay. The mother, and others, left without being seen.

The application is supported by the Jesuit Refugee Service, The Southern African HIV Clinicians Society, and Doctors Without Borders; all are expected to file affidavits soon. Rugege says these will highlight discriminatory institutional policies and systematic xenophobic practices and attitudes that have “detrimental and sometimes fatal consequences”.

“There is simply no coherent approach at different public health establishments … even within a single establishment, different officials treat patients differently,” she said. Access to health care depends on who is on duty that day. On “lucky days” people will gain access without any trouble.

The respondents – the MEC and Gauteng health department head, the Minister and Director-General of Health – have 15 days to file notices of opposition.

By Tania Broughton

This article is republished from GroundUp under a Creative Commons Attribution-NoDerivatives 4.0 International License.

Source: GroundUp

Will NHI Mean the End of Medical Aid in South Africa?

Once again, concerns are being raised over the implementation of the proposed National Health Insurance (NHI) scheme. This time, it is over the future of private healthcare and medical aid under the contentious Section 33 of the Bill.

Many previous discussions have focused on the NHI’s affordability, accountability, the potential mass flight of healthcare professionals from the country, and even whether NHI is even possible to achieve given South Africa’s challenges.

In a new healthcare stakeholder opinion report [PDF] published by Section 27 and the Concentric Alliance on Monday, 20 June, it is noted that private healthcare is a major contributor to the economy. May public and private sector respondents believe it could play a significant role in achieving health reform thanks to its resources and capacity.

However, Section 33 of the NHI Bill states that medical schemes may only provide “cover that constitutes complementary or top-up cover and that does not overlap with the personal health care service benefits purchased by the National Health Insurance Fund on behalf of users”.

This basically means medical schemes which are not gap cover will no longer operate – something which does not sit well with the private sector respondents in the report, who argue that even in countries with the best developed public health systems, private healthcare funders still exist.

A carrot vs stick approach

An academic respondent suggested incentivising people into switching to a public healthcare funder, rather than removing private healthcare funding. A private sector respondent also suggested the idea of competition with private funders as a means to improve the NHI’s efficiency. Indeed, it may even be necessary the NHI to function well.

The report makes note of Section 33 of the NHI Bill becoming “something of a hill to die on”. The report says that “During the six-a-side engagements between Business Unity and the National Department of Health, urgent discussions on NHI were nearly derailed by demands that Section 33 be re-opened for discussion and one respondent in the NDOH stating that the Bill was now before parliament. This respondent stated that they would rather see this point litigated, than back down. The current approach to this draft provision has the potential to undermine the implementation of the NHI and delay urgent reform to the health system.”

Up in Smoke: The Tobacco Wars and Lessons for Vaccination Efforts

Tobacco companies waged a massive disinformation campaign to keep people consuming their products. There are parallels with today’s antivaxx movement. Even before the 1964 US Surgeon General’s report on tobacco, the tobacco industry was deflecting health concerns by featuring doctors in their advertising and actively courting the medical industry. This advert is from 1930.

In a perspective piece published in the New England Journal of Medicine, authors find a parallel between the tactics used in the ‘tobacco wars’ and vaccination efforts. In a seeming repeat of history, anti-vaccination groups are using the same tactics the tobacco industry used to defend their products and undermine trust in science, but the successful anti-tobacco campaign holds important lessons for turning the tide against misinformation and normalising vaccination.

In late 2020 when the first COVID vaccines became available, the authors note that surveys indicated that about a third of US adults were keen to be vaccinated, 15% expressed strong resistance to vaccination (a proportion that has stayed fairly constant), and the remainder didn’t harbour strong ideological resistance. Now, about 27% of US adults now remain unvaccinated – and reaching this remainder is an important public health challenge.

The authors believe that the ‘tobacco wars’ can provide perspective. The tobacco industry fuelled preventable deaths by glamourising smoking, with almost 50% of US adults smoking cigarettes in the 1960s.

The current rate of about 12.5% is the result of decades of public health efforts to make tobacco use less socially acceptable. The first US Surgeon General’s report on smoking and health in 1964 was attacked by the tobacco industry. It was only until C. Everett Koop’s overwhelming report in 1986 that cemented tobacco use as a major preventable cause of cancer and death and highlighted the dangers of second-hand smoking.

Koop and others were vilified by the tobacco industry, which mounted a sustained campaign that cast doubts on the science, publicised misinformation, emphasised tobacco’s economic importance, and warned against restricting individual freedom. Industry leaders directly lied about knowing that nicotine was addictive and the lethal dangers of tobacco use. Indeed, from the 1920s to 1950s, in response to growing health concerns, the tobacco industry had actively courted doctors and influenced medical journals, widely reporting positive findings of studies that were deeply flawed. This may have only played into the hands of antivaxxers, creating a historical example of distrust in the medical system.

A 1940s advert showing how ‘doctors’ (probably actors) enjoyed Camel brand cigarettes. With the 1950 publication of studies showing the connection between cancer and tobacco, the public began to be suspicious and such campaigns featuring doctors ended by 1954.

While the focus of the debate was initially on smoking as an individual choice, two 1981 studies on nonsmoking wives of smokers vs nonsmokers revealed the dangers of secondhand smoke and shifted the discourse.

The US Congress has never enacted a federal smoking ban, but did grant the FDA limited authority to regulate tobacco in 2009, enabling restrictions on youth sales.

However, the broad-based effort from all levels of society that were important, discouraging smoking in public settings. This was supplemented by messaging from celebrities, taxation, and even a 1998 legal battle against the tobacco industry.

Efforts undertaken by the antivaccination movement, which is hardly new but is thriving during the COVID pandemic, bear many similarities to strategies used during the tobacco wars. Although not driven by a single industry but a collection of celebrities and social media groups, it sows mistrust in science and promotes conspiracy theories. Misinformation tactics are used that are strikingly similar to the tobacco industry’s, and this time Dr Antony Fauci is vilified instead of Koop.

There are big differences between tobacco control and vaccination; such as taking a long time for smoking interventions to reduce chronic diseases, whereas vaccinations usually reduce hospitalisations and severe illness within days or weeks.

The authors believe that success against antivaccination movement can draw on the tobacco wars’ lessons, illustrating COVID’s harm and the power of vaccines. Getting vaccinated and boosted should be the accepted social norm during a pandemic, they stress.

Drawing on similar efforts for anti-tobacco campaigns, vaccination campaigns using real patients in ICU who express regret over not being vaccinated. Unvaccinated people often assume they can be cared for if they get sick, so messages could also be included from healthcare works talking about the strain of the pandemic.

“There is an opportunity to mount a serious effort to provide accurate vaccination information using the same media channels on which people currently consume misinformation,” they wrote.

They also consider vaccine mandates which make being vaccinated a social norm such as wearing a seatbelt, and other regulations at the community and business level may be more effective.

They note that personal physicians play a key role, being the best way to transmit health information. But many people at risk of remaining unvaccinated have had negative experiences with health care, compounded by doctors spreading misinformation.

The authors note that the dangers of tobacco use were known to public health practitioners for years, but it took a well-funded concerted effort that emphasised the impact on others to achieve a change in behaviour. This is something that needs to be repeated for vaccinations.

“Freedom of choice remains; people can still smoke cigarettes and decline vaccinations. But the roadmap drawn by tobacco-control efforts shows that the public mindset can be tilted toward public health and social good. With vaccination, this work shouldn’t take decades; it needs to begin immediately.”

Source: New England Journal of Medicine

South African Medical-legal Reform: Modernising the System or a Knee-jerk Reaction?

By Dr Hlombe Makuluma, Clinical Risk Management at EthiQal and JP Ellis, Senior Legal and Claims Manager at EthiQal Medical Risk Protection, a division of Constantia Insurance.

South Africa’s medicolegal problems are well documented. Our healthcare system is vulnerable, with many healthcare workers working under stressful conditions, not to mention the uncertainty in relation to the implementation of National Health Insurance and the adverse consequences of the pandemic.

A public healthcare system which is overburdened and under-resourced finds itself confronted with litigation daily with the result that it has accumulated contingent liabilities (ie, the projected cost of payments for medical litigation claims) in the billions. Whereas in the private sector the burden of professional indemnity insurance cover for certain high-risk specialities has resulted in many private practitioners limiting their scope of practice or reconsidering the viability of continuing to practise. Since many private hospitals are self-insured for medico-legal claims up to a certain level, the price for their litigation defence is ultimately brought back to the consumer. To make matters worse, the South African civil justice system is renowned for its delays, inefficiencies, and the unnecessarily high cost of litigation. All these things make up the perfect recipe for a very lucrative industry which rewards many role-players, who have no hesitation in taking advantage of a vulnerable medicolegal system.

The South African Law Reform Commission (SALRC) was requested by the Ministers of Health and Justice to review the current system and to offer proposals. The SALRC has published their discussion paper 154 in November 2021 on their recommendations based on preliminary research, five years after the publication of their initial working paper on Project 141: Medico-legal Claims. While we should all be happy that progress has been made the real question is whether there is real appetite to improve our system or whether this is all a knee-jerk reaction?

There is an urgent need for meaningful reform. Patients who suffer harm because of negligence by healthcare providers require reasonable compensation quickly, and healthcare providers should be sufficiently protected from abuse and unmeritorious claims. Sadly, our medicolegal system does not adequately provide for this.

The burden of clinical negligence litigation is great as it often takes many years to finalise cases – whether in the form of a resolution or judgment – and the cost of litigation is exorbitant. Overall, the SALRC has taken great care in considering the rights of claimants and the burden of compensation on the State by thoroughly researching the medico-legal landscape in South Africa. Reform is generally classified into three areas, namely reforms that limit access to our courts, reforms that influence court processes, and reforms that limit the amount of compensation awarded.

They have offered recommendations which they believe will make the most difference. Most notably:

Reforms that limit access to our courts

  • Mediation has been encouraged as a first step to deal with medico-legal disputes before litigation. Most stakeholders appear to have no serious objections to mediation, especially because Uniform Rule 41A was introduced a few years ago, which requires a plaintiff or applicant who initiates litigation proceedings to file a certificate indicating whether they agree to the referral of the matter to mediation and, if not, to state the reasons for that refusal.
  • A certificate of merit affidavit should be filed on behalf of an accredited and suitably qualified medical practitioner to avoid frivolous, meritless, fraudulent or abandoned claims. This essentially opens the door for a successful defendant to claim the costs of litigation against those parties, and possibly their attorneys, who engage in irresponsible litigation.
  • A plaintiff is barred from proceeding with a claim after a period of inaction after issuing summons, with the possibility of having the period extended by the court but only on good cause shown. Either our Court rules or Practice manuals should be amended to ensure that once legal action is taken the matter must be finalised within a specified period, depending on the nature and extent of the litigation.  
  • Adopting an administrative compensation system for smaller medical negligence claims.
  • Introducing a pre-action protocol system for larger medical negligence claims.

Reforms that influence court processes

  • There seems to be a consensus in the legal fraternity that the rules relating to the way in which experts are used should be reconsidered. The recommendation from the SALRC is that opposing parties to litigation should use joint expert witnesses, and when necessary, a panel of three joint expert witnesses from the discipline concerned, for technical medical evidence. The use of joint experts should be encouraged but naturally there will be situations where it is inappropriate, and a panel of three experts will only increase the costs unnecessarily. Rather the two main areas of concern which ought to be addressed is the accreditation and accountability of expert witnesses for the purposes of court proceedings and the desirability of sanctions for inappropriate or unethical conduct by expert witnesses. 
  • The Superior Courts Act and the Uniform Rules of Court should be amended to provide for the appointment of specialist assessors to assist judges in complex medical negligence matters, rather than the establishment of specialist medical courts. Although the use of specialist assessors will be helpful this won’t necessarily address the issue that a generalist court will misapply the law, confuse rather than clarify the issues, and inadvertently encourage additional litigation rather than a specialist court.
  • Civil procedures be amended to substantially improve pre-trial procedures, as well as case management to expedite and simplify the finalisation of litigation.

Reforms that limit the amount of compensation awarded

  • Compensation to be awarded in the form of a structured settlement, with part of the compensation paid in a lump sum, part of the compensation paid as periodic payments, and part of the compensation provided as ‘payments in kind’ by means of the delivery of services – allowing a combination of these methods and determining the ratio of one aspect in comparison to another aspect by considering the circumstances of each case. This ‘payment in kind’ element is arguably the most controversial, given the parlous state of much of South Africa’s public healthcare system.
  • Periodic payments in the nature of an annuity be awarded for future maintenance, loss of earnings and the portion of future medical care, treatment, rehabilitation and therapy that the state cannot provide.
  • The underlying principle for the calculation of future loss of income be changed to a structured method based on the average national income or the average income of the area where the claimant lives.
  • It may be necessary to cap any damages other than special damages such as constitutional damages and general damages (non-pecuniary damages).
  • It should be possible to adjust periodic payments in exceptional circumstances.

Except for a few controversial recommendations, most will probably carry widespread support from various stakeholders. But the reality is that this is not enough. As the saying goes ‘the proof is in the pudding’. How exactly these recommendations will translate into independent pieces of legislation, amendments to existing legislation, adjustments to Court rules and practices are largely uncertain.

Whether their recommendations will carry through into positive and meaningful change is dependent on the ‘Powers that Be’. At this stage, there are indications that tend to suggest that the SALRC is under political pressure to now finalise this investigation and are more concerned with adopting recommendations which will relieve the most burden on the public sector rather than taking this opportunity to adopt a holistic approach to strengthening the entire South African medico-legal system, which is obviously preferable.

For example, there has been much criticism levelled at the SALRC for their exclusive focus on reform to the public sector. In their own words “(t)he proposals focus mainly on measures to alleviate the financial burden of medico-legal claims against the state on the fiscus, and to provide for alternative procedures for the speedy resolution of medical negligence claims against the state”. What is clear from the proposals offered in chapter 9 of Discussion Paper 154 is that efforts to reform the system can only realistically be done through a process of collaboration between the private and public healthcare system. According to them this was deliberate since the request for the current investigation was initiated at the insistence of the Ministries of Health and Justice. It would be preferable if law reform was not a knee-jerk reaction to the financial burden medical malpractice claims present for the State. Although the public sector exposure is, for various reasons, much greater financially: if not similar, the same risks exist for the private healthcare industry. Many medical malpractice claims and significant awards continue to plague the private sector. Therefore, it would be ideal if law reform was universally applied because there is no reason why the SALRC’s investigation should not include specific law reform initiatives that are helpful to the challenges presented to the private sector. Patients, health establishments and medical practitioners, whether in the private or public sector, are equally deserving of the constitutional imperative of equality before the law and “the right to equal protection and benefit of the law”.

What remains to be seen is how the recommendations in the final report will be implemented. The state has an exceptionally poor track record in following the corrective measures contained in the Public Protector reports, the South African Human Rights Commission reports, the Auditor-General audit reports, the Office of Health Standards Compliance reports, the Presidential Health Summit 2018 Compact and other existing government-initiated reports, plans and studies.

So whereto from here? Only time will tell. The investigative work of the SALRC is ongoing and it will no doubt take some time before we receive a final report. The real issue confronted by the SALRC is that there are a variety of different competing interests in the healthcare ecosystem, and it will be difficult to provide a holistic set of recommendations that will please everyone.

Acknowledging the good work done by SALRC the final report should adopt a balanced approach, one which prioritises interests of the state versus the poor and most vulnerable. Deciding how to compensate someone for harm suffered due to medical negligence is a thorny and complicated question. There is a difficult balancing act here. On the one hand, people have a right to be given fair compensation. On the other hand, the state has only limited funds and there is an understandable impulse to limit how much of those funds go toward compensation payments.

Of course, those mechanisms of compensation must not be unfair and punitive. The work of the SALRC is difficult, necessary, and very important to the sustainability of our healthcare system. The SALRC has noted the contribution of an ailing healthcare system to the significant medicolegal burden the country is facing. Factors contributing to poor healthcare service delivery by the State include maladministration, mismanagement and fraud, number of qualified healthcare workers and access to drugs, technologies and emergency transport.

Unfortunately, legislation and other reforms cannot fix the healthcare system or improve the standards of healthcare. But, overall, care must be taken to ensure that the final recommendations are well balanced and will pass constitutional muster. 

Renewed Political Will Needed for the Complexities of African Healthcare

Delegates at the 21st Annual Board of Healthcare Funders (BHF) Conference currently being held in Cape Town.

19 May 2022: Healthcare – Cape Town, South Africa: The healthcare system in South Africa and on the continent is beset with structural challenges and skewed political priorities that hamper the attainment of universal healthcare coverage, therefore a fundamental overhaul of the healthcare system and renewed political will is required to improve citizen’s access to quality healthcare services.

These sentiments kicked off the first day of the 21st Annual Board of Healthcare Funders (BHF) Conference currently being held in Cape Town under the theme: Leading change in strengthening our healthcare ecosystem.

Connected virtually, South Africa’s Minister of Health, Dr Joe Phaahla invited the private sector to submit recommended solutions to strengthen the country’s healthcare systems, emphasising the need for a collaborative approach to transform healthcare.

Dr Phaahla conceded that the health system in the country was already weak before the outbreak of COVID and inequality in access to reliable health services is inextricably linked to the economic and social inequality that our country is facing.

The Minister added, “The country’s healthcare system should be restructured to focus more on preventative services rather than the current curative approach.”

“The socio-economic inequality is perpetuated further by our own health services, which are highly heavily commodified. Our two-tiered healthcare system with one being driven by the private sector for a few who can afford it and the other by the public sector being provided for the majority of the population does not bode well for the future prospects of the country. This system is unsustainable and if we are going to talk about a change in strengthening the health system, we cannot avoid talking about the need to accelerate the creation of a more equitable health system.” 

He acknowledged that the passing of the NHI Bill will not in itself be a silver bullet in the transformation of our health system, however, will lay a good foundation for the country to timely start to fundamentally transform our health system towards equity.

Speaking about the relationship between politics and healthcare, Professor Patrick Lumumba, former Director of the Kenya Anti-Corruption Commission, said, “Politics is at the very heart of the provision of sound healthcare systems.”

He challenged some of the perceptions around the delivery of national healthcare insurance across Africa, asking governments and the private sector to closely examine suitable healthcare solutions that will consider the continent’s current different types of conflicts.

He highlighted that considerations should be made in the best interest of the continent’s populations when making the decision on an approach to be taken for the continent’s healthcare needs, bearing in mind what is affordable to the different countries across the continent, especially given that the continent’s entire GDP is less than that of Italy, which has just under 60 million people.

“The continent is currently under different types of conflict at various intensities, and these conflicts are in turn undermining the provision of healthcare,” said Prof Lumumba.

He noted that in Africa, there is a lack of political will to spend more on healthcare despite the commitments made at Abuja, Nigeria, in 2001 to invest a minimum of 15% of their national budget in healthcare.

“Politicians are rich in making promises. The evidence we have in different countries is that universal health care as promised by politicians and as desired by the population is not easily achievable,” he said.

He cautioned against the temptation to compare the healthcare system in Africa with that of developed countries, citing a lower tax base and GDP in Africa to fund a healthcare system that services a substantially larger population.

“The entire GDP of Africa is slightly over two trillion US dollars, which is smaller than the GDP of Spain, which has a population of no more than 50 million people, it is critical that the private and public sectors; and politicians work together to come up with a system that is going to be beneficial to the majority of Africa’s people,” said Professor Lumumba.

He said the envisaged economic revival of Africa cannot be sustained if the continent’s healthcare needs are not adequately addressed.

“If the continent of Africa is to enjoy the perceived economic growth that is expected, then the population must be healthy. Healthcare is about creating healthcare systems that are also able to retain the skills that are required for Africa’s emerging or growing economies. There is also a clear need for collaboration in the delivery of health services,” said Lumumba.

Dr Millicent Hlatshwayo Chairperson of the Government Employees Medical Scheme (GEMS) reiterated the need for the private healthcare sector to play a meaningful role towards shaping the proposed healthcare funding model to ensure its sustainability.

She acknowledged that the healthcare sector is faced with several systemic challenges, and this is reflected in our international rankings; where South Africa ranks 49th out of 89 countries on the 2022 Global Healthcare Index. Though South Africa is the highest-ranked African country in this index, it has been rated below its peers in BRICS such as China and India, which are rated 40th and 44th respectively.

Dr Hlatshwayo said, “Proposed reforms such as the implementation of the NHI can help to facilitate better cooperation between the public and private sectors. We cannot afford to be passive observers in these deliberations, because our failure to act on these opportunities will be an indictment on the industry.”

Dr Hlatshwayo said from its inception, GEMS has been aligned with the transformation of the healthcare industry and supportive of the principles of universal health coverage.

She said universal health coverage can only be achieved if we get the basics in place, namely qualified staff, equipment and technology, infrastructure and working systems.