Credit: Darryl Leja / National-Human-Genome Research Institute / National Institutes of Health
Men undergoing MRI-guided radiotherapy for localised prostate cancer, had fewer toxicities and better quality of life, according to new research published in JAMA Oncology. This was the first randomised phase III clinical trial to directly compare MRI-guided stereotactic body radiotherapy (SBRT) with the same therapy guided by CT.
“MRI guidance offers several advantages over standard CT guidance, most notably the ability to dramatically reduce planning margins, providing more focused treatment with less injury to nearby normal tissues and organs,” said lead author Amar Kishan, MD, a radiation oncologist. “MRI technology is more costly than CT, both in terms of upfront equipment expenses and longer treatment times, which is one reason our study set out to determine if MRI-guided technology offers tangible benefits for patients.”
SBRT for prostate cancer usually delivers radiation in five or fewer precisely targeted doses. It is an established and generally well tolerated form of treatment, but it can cause toxicities resulting in urinary, bowel and sexual dysfunction. This UCLA-led clinical trial included 154 analysable patients with prostate cancer who were randomised to either a CT-guidance arm (76 patients) or an MRI-guidance arm (78 patients).
This study included assessment by both physicians and patients. From both perspectives, MRI-guided therapy was associated with fewer side effects and better quality of life over at least three months of follow-up.
“In this trial, we demonstrated that the reduction in treatment volumes facilitated by MRI guidance leads to a significant reduction in moderate physician-scored toxicity and to a reduction in the proportion of patients noting significant decrements in patient-reported outcome metrics in the near term,” said Dr Kishan. “Although additional studies will need to confirm these benefits over time, we’re hopeful that these results will lead to better outcomes for men with prostate cancer.”
The 2mm margin used with MRI-guidance in the trial is narrower than has been used in any previous large study. Unlike CT, MRI technology can monitor prostate motion directly, and it offers improved soft tissue contrast, improving the accuracy of alignment prior to radiation.
A new way to significantly increase the potency of almost any vaccine has been developed by researchers from the International Institute for Nanotechnology (IIN) at Northwestern University, which they describe in Nature.
The scientists used chemistry and nanotechnology to change the structural location of adjuvants and antigens on and within a nanoscale vaccine, greatly increasing vaccine performance. The antigen targets the immune system, and the adjuvant is a stimulator that increases the effectiveness of the antigen.
“The work shows that vaccine structure and not just the components is a critical factor in determining vaccine efficacy,” said lead investigator Chad A. Mirkin, director of the IIN. “Where and how we position the antigens and adjuvant within a single architecture markedly changes how the immune system recognises and processes it.”
This new heightened emphasis on structure has the potential to improve the effectiveness of conventional cancer vaccines, which historically have not worked well, Mirkin said.
Mirkin’s team has studied the effect of vaccine structure in the context of seven different types of cancer to date, including triple-negative breast cancer, papillomavirus-induced cervical cancer, melanoma, colon cancer and prostate cancer to determine the most effective architecture to treat each disease.
Conventional vaccines take a blender approach
With most conventional vaccines, the antigen and the adjuvant are simply blended and injected into a patient, giving no control over the vaccine structure, and, consequently, limited control over trafficking and processing of the vaccine components. Thus, there is no control over how well the vaccine works.
“A challenge with conventional vaccines is that out of that blended mish mosh, an immune cell might pick up 50 antigens and one adjuvant or one antigen and 50 adjuvants,” said study author and former Northwestern postdoctoral associate Michelle Teplensky, who is now an assistant professor at Boston University. “But there must be an optimum ratio of each that would maximise the vaccine’s effectiveness.”
Enter SNAs (spherical nucleic acids), which are the structural platform, invented and developed by Mirkin, used in this new class of modular vaccines. SNAs allow scientists to pinpoint exactly how many antigens and adjuvants are being delivered to cells. SNAs also enable scientists to tailor how these vaccine components are presented, and the rate at which they are processed. Such structural considerations, which greatly impact vaccine effectiveness, are largely ignored in conventional approaches.
Vaccines developed through ‘rational vaccinology’ offer precise dosing for maximum effectiveness
Mirkin came up with this approach to systematically control antigen and adjuvant locations within modular vaccine architectures, and called it ‘rational vaccinology’. It is based on the concept that the structural presentation of vaccine components matters as much as the components themselves in driving efficacy.
“Vaccines developed through rational vaccinology deliver the precise dose of antigen and adjuvant to every immune cell, so they are all equally primed to attack cancer cells,” said Mirkin. “If your immune cells are soldiers, a traditional vaccine leaves some unarmed; our vaccine arms them all with a powerful weapon with which to kill cancer. Which immune cell ‘soldiers’ do you want to attack your cancer cells?”
Building an (even) better vaccine
The team developed a cancer vaccine that reduced tumour growth by more than four times compared to checkpoint inhibitor monotherapy, and led to a 40% extension in median survival.
By reconfiguring the architecture of a vaccine containing multiple targets, the SNA enables the immune system to find tumour cells. The team investigated differences in how well two antigens were recognised by the immune system depending on their placement, on the core or perimeter, of the SNA structure. For an SNA with optimum placement, they could increase the immune response and how quickly the nanovaccine triggered cytokine (an immune cell protein) production to boost T cells attacking the cancer cells. The scientists also studied how the different placements affected the immune system’s ability to remember the invader, and whether the memory was long-term.
“Where and how we position the antigens and adjuvant within a single architecture markedly changes how the immune system recognises and processes it,” Mirkin said.
The most powerful structure throws two punches to outsmart the tumour
The study data show that attaching two different antigens to an SNA comprising a shell of adjuvant was the most potent approach for a cancer vaccine structure. These engineered SNA nanostructures stalled tumour growth in multiple animal models.
“It is remarkable,” Mirkin said. “When altering the placement of antigens in two vaccines that are nearly identical from a compositional standpoint, the treatment benefit against tumours is dramatically changed. One vaccine is potent and useful, while the other is much less effective.”
Many current cancer vaccines are designed to primarily activate cytotoxic T cells, only one defence against a cancer cell. Because tumour cells are always mutating, they can easily escape this immune cell surveillance, quickly rendering the vaccine ineffective. The odds are higher that the T cell will recognise a mutating cancer cell if it has more antigens to recognise it.
“You need more than one type of T cell activated, so you can more easily attack a tumour cell,” Teplensky said. “The more types of cells the immune system has to go after tumours, the better. Vaccines consisting of multiple antigens targeting multiple immune cell types are necessary to induce enhanced and long-lasting tumour remission.”
Another advantage of the rational vaccinology approach, especially when used with a nanostructure like an SNA, is that it’s easy to alter the structure of a vaccine to go after a different type of disease. Mirkin said they simply switch out a peptide, a snippet of a cancer protein with a chemical handle that “clips” onto the structure, not unlike adding a new charm to a bracelet.
Towards the most effective vaccine for any cancer type
“The collective importance of this work is that it lays the foundation for developing the most effective forms of vaccine for almost any type of cancer,” Teplensky said. “It is about redefining how we develop vaccines across the board, including ones for infectious diseases.”
In a previously published paper, Mirkin, Teplensky and colleagues demonstrated the importance of vaccine structure for SARS-CoV-2 by creating vaccines that exhibited protective immunity in 100% of animals against a lethal viral infection.
“Small changes in antigen placement on a vaccine significantly elevate cell-to-cell communication, cross-talk and cell synergy,” Mirkin said. “The developments made in this work provide a path forward to rethinking the design of vaccines for cancer and other diseases as a whole.”
A new MIT study explains why dendritic cells (green) in lymph nodes that drain from the lungs fail to stimulate killer T cells (white) to attack lung tumours. Credits: MIT/ Courtesy of the researchers
Immunotherapy works well against some types of cancer, but it has shown mixed success against lung cancer. A new study from MIT helps to shed light on why the immune system mounts such a lacklustre response to lung cancer, even after treatment with immunotherapy drugs. In a study of mice, the researchers found that bacteria naturally found in the lungs help to create an environment that suppresses T-cell activation in the lymph nodes near the lungs.
The researchers did not find that kind of immune-suppressive environment in lymph nodes near tumours growing near the skin of mice. They hope that their findings could help lead to the development of new ways to rev up the immune response to lung tumours.
“There is a functional difference between the T-cell responses that are mounted in the different lymph nodes. We’re hoping to identify a way to counteract that suppressive response, so that we can reactivate the lung-tumour-targeting T cells,” says Stefani Spranger, the Howard S. and Linda B. Stern Career Development Assistant Professor of Biology, a member of MIT’s Koch Institute for Integrative Cancer Research, and the senior author of the new study.
MIT graduate student Maria Zagorulya is the lead author of the paper, which appears today in the journal Immunity.
Failure to attack
For many years, scientists have known that cancer cells can send out immunosuppressive signals, which leads to a phenomenon known as T cell exhaustion. The goal of cancer immunotherapy is to rejuvenate those T cells so they can begin attacking tumours again.
One type of drug commonly used for immunotherapy involves checkpoint inhibitors, which remove the brakes on exhausted T cells and help reactivate them. This approach has worked well with cancers such as melanoma, but not as well with lung cancer.
Spranger’s recent work has offered one possible explanation for this: She found that some T cells stop working even before they reach a tumour, because of a failure to become activated early in their development. In a 2021 paper, she identified populations of dysfunctional T cells that can be distinguished from normal T cells by a pattern of gene expression that prevents them from attacking cancer cells when they enter a tumour.
“Despite the fact that these T cells are proliferating, and they’re infiltrating the tumour, they were never licensed to kill,” Spranger says.
In the new study, her team delved further into this activation failure, which occurs in the lymph nodes, which filter fluids that drain from nearby tissues. The lymph nodes are where ‘killer T cells’ encounter dendritic cells, which present antigens (tumour proteins) and help to activate the T cells.
To explore why some killer T cells fail to be properly activated, Spranger’s team studied mice that had tumours implanted either in the lungs or in the flank. All of the tumours were genetically identical.
The researchers found that T cells in lymph nodes that drain from the lung tumours did encounter dendritic cells and recognise the tumour antigens displayed by those cells. However, these T cells failed to become fully activated, as a result of inhibition by another population of T cells called regulatory T cells.
These regulatory T cells became strongly activated in lymph nodes that drain from the lungs, but not in lymph nodes near tumours located in the flank, the researchers found. Regulatory T cells are normally responsible for making sure that the immune system doesn’t attack the body’s own cells. However, the researchers found that these T cells also interfere with dendritic cells’ ability to activate killer T cells that target lung tumours.
The researchers also discovered how these regulatory T cells suppress dendritic cells: by removing stimulatory proteins from the surface of dendritic cells, which prevents them from being able to turn on killer T cell activity.
Microbial influence
Further studies revealed that the activation of regulatory T cells is driven by high levels of interferon gamma in the lymph nodes that drain from the lungs. This signalling molecule is produced in response to the presence of commensal bacterial – bacteria that normally live in the lungs without causing infection.
The researchers have not yet identified the types of bacteria that induce this response or the cells that produce the interferon gamma, but they showed that when they treated mice with an antibody that blocks interferon gamma, they could restore killer T cells’ activity.
Interferon gamma has a variety of effects on immune signalling, and blocking it can dampen the overall immune response against a tumour, so using it to stimulate killer T cells would not be a good strategy to use in patients, Spranger says. Her lab is now exploring other ways to help stimulate the killer T cell response, such as inhibiting the regulatory T cells that suppress the killer T cell response or blocking the signals from the commensal bacteria, once the researchers identify them.
Experts led by researchers from the Murdoch Children’s Research Institute have created the world’s first international clinical guidelines to help prevent and treat heart complications in children undergoing cancer treatment.
Published in JACC:Advances, the guidelines cover cardiovascular disease assessment, screening and follow-up, for paediatric patients receiving cancer treatment with new molecular therapies, immunotherapy, chemotherapy and radiotherapy.
The expert consensus has defined the high-risk group of cancer patients who should undergo a heart check-up, standardised an approach to screening and surveillance during treatment and provided recommendations to protect vulnerable young hearts.
Murdoch Children’s Associate Professor Rachel Conyers said while international guidelines to monitor poor heart side effects during therapy exist for adult patients, none were specific to children.
Associate Professor Conyers said the success of new cancer drugs had increased the chances of cardiac side effects that occur early on during therapy, sometimes within days, which warranted closer heart health surveillance and earlier monitoring.
“Recent advances in treating childhood cancer have resulted in survival rates of more than 80 percent. However, improving serious health outcomes in survivors remains an important and essential focus and prevention is key,” she said.
“Heart complications are a leading cause of death for childhood cancer survivors, second only to cancer relapse. Modern treatments including precision medicine have broadened the agents that can cause heart problems.”
Childhood cancer survivors are 15 times more likely to have heart failure and eight times more likely to have heart disease than the general population.
Associate Professor Conyers said the guidelines would be an indispensable tool for clinicians to significantly reduce the harmful impact of cancer drugs on children’s hearts.
“The guidelines are a major advance for the cardio-oncology field as before this there was no defined approach for surveillance or follow up of pediatric patients during treatment despite new therapeutics having early heart complications such as high blood pressure, abnormal heart beats and heart failure,” she said.
The Australian and New Zealand expert group consisted of pediatric and adult cardiologists and pediatric oncologists who undertook a Delphi consensus approach across 11 areas of cardio-oncology care. The Australian New Zealand Children’s Oncology Group endorsed the study with the guidelines useful for any tertiary institutes treating pediatric oncology patients or initiating cardio-oncology clinics.
Lung cancer cells in the process of metastasising. Source: National Cancer Institute on Unsplash
When cancer cells metastasise, they have to break connections with neighbouring cells and migrate to other tissues. Both processes are promoted by signalling molecules released by the cancer cells, which thereby increase the malignancy of tumours. Researchers found that the release of these ‘prometastatic’ factors is influenced by the cellular skeleton – specifically, actin filaments. The study was published in Advanced Science.
Actin’s multiple role functions in cancer propagation
Actin filaments are part of the cell skeleton and essential for stability and motility. They form a network that dynamically builds up and gets broken down by the addition or detachment of building blocks at the filaments’ ends. These processes are precisely regulated by other molecules, such as formins. The dynamics of the actin network enable the movement of cells, for example during development or wound closure, but also that of spreading cancer cells. Actin also plays a role in the transport of substances within the cell. However, this is less well understood than that of other intracellular transport mechanisms.
The research team led by Prof Dr Robert Grosse and Dr Carsten Schwan from the University of Freiburg, now found that the actin network also enables the release of prometastatic factors, such as ANGPTL4 which is an important prometastatic factor that promotes the formation of metastases in various types of cancer. For their study, they used high-resolution microscopy to track the movement of individual transport vesicles within living cancer cells.
“We observed that ANGPTL4-loaded vesicles are conveyed to the periphery of the cell by means of dynamic and localised polymerisation of actin filaments,” says Grosse, who is a member of the Cluster of Excellence CIBSS – Centre for Integrative Biological Signalling Studies at the University of Freiburg.
Transportation along actin filaments
Based on microscopic observations and genetic analyses, the scientists conclude that the vesicles’ movement is controlled by the formin-like molecule FMNL2 by initiating polymerisation (ie elongation) of actin filaments directly at the vesicle. “We already knew that increased FMNL2 activity has prometastatic effects in many types of tumours,” says Grosse. “In our current work we could now demonstrate an important underlying process and a connection to the TGFbeta signalling pathway.” According to the scientist, this knowledge could be used for tumour diagnostics or therapy. for example, by developing an antibody that indicates the presence of active FMNL2 or pharmacologically targets active, phosphorylated FMNL2.
A Phase III trial testing the targeted therapy momelotinib showed that patients with myelofibrosis had clinically significant improvement in disease-related symptoms, including anaemia and spleen enlargement.
The findings, published in The Lancet, support the use of momelotinib over the standard therapy (danazol) in treating myelofibrosis patients that were resistant, refractory or intolerant to firstline therapy, especially symptomatic patients and those with anemia.
“Current options for managing anaemia in our myelofibrosis patients provide only modest and temporary benefits, so we are excited about these findings,” said study lead Srdan Verstovsek, MD, PhD, professor of Leukemia at University of Texas. “The trial results suggest that momelotinib is safe, well-tolerated and can improve one of the most common and debilitating clinical problems for this patient population.”
Myelofibrosis is an uncommon bone marrow cancer that is part of a group of diseases known as myeloproliferative neoplasms. A hallmark of the disease is dysregulated JAK signalling, which disrupts blood cell production and leads to symptoms including an enlarged spleen and anaemia. Chronic anaemia in these patients is associated with poor prognoses.
Currently approved JAK inhibitors can improve spleen responses and other disease-related symptoms, but they also can worsen anaemia. In this trial, momelotinib improved anaemia and reduced transfusion dependency in myelofibrosis patients previously treated with a JAK inhibitor. Momelotinib, a potent ACVR1/ALK2 and JAK1/2 inhibitor, can be administered and maintained at full dose because it does not suppress bone marrow activity like other JAK inhibitors.
The randomised Phase III MOMENTUM trial was designed to compare the clinical benefits of momelotinib to danazol, a synthetic androgen currently used to treat anaemia in symptomatic myelofibrosis patients.
The trial enrolled 195 adult patients (63% male, 37% female) from 107 research sites across 21 countries. Trial participants were randomised (2:1) to receive momelotinib plus placebo or danazol plus placebo. A significantly greater proportion of patients who received momelotinib saw benefits in their disease symptoms (25%) compared to those receiving danazol (9%).
Patients treated with momelotinib also experienced a significant reduction in their spleen size, with 25% responding after 24 weeks of therapy. Additionally, these patients required fewer blood transfusions compared to those receiving danazol.
The safety profile of momelotinib was comparable to previous clinical trials. The most common non-haematological side effects experienced by trial participants in the momelotinib group included diarrhoea, nausea, weakness and itching or irritated skin.
“If approved, momelotinib could offer an effective option for patients with myelofibrosis to improve anemia, splenomegaly and other disease-related symptoms over other approved medications so far,” Verstovsek said. “Momelotinib may also be an ideal partner for combinations with other investigational agents in development to further control myelofibrosis symptoms.”
Patient follow-up is ongoing and long-term survival continues to be monitored.
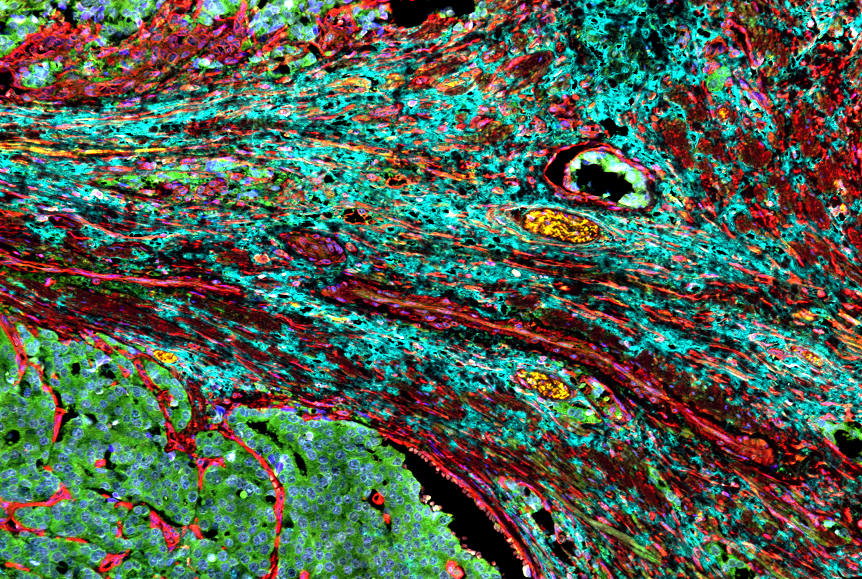
Cancer-associated fibroplasts surrounding a prostate tumour. Credit: Moscat and Diaz Meco labs
Prostate cancer is the second most common cancer and the second leading cause of cancer death among American men. Now, researchers have discovered key molecular players that drive prostate cancer to progress into a highly aggressive form of the disease called neuroendocrine prostate cancer that currently has no effective treatment. The finding, published in in the journal Scientific Reports, opens new avenues to therapeutics to treat neuroendocrine prostate cancer.
“We have found novel pathways that promote neuroendocrine prostate cancer,” says senior author Lucia R. Languino, PhD, a professor in the department of Pharmacology, Physiology and Cancer Biology and director of the Genetics, Genomics, and Cancer Biology PhD Program at Thomas Jefferson University.
Most prostate cancers are a type of disease called prostate adenocarcinoma. Other types of prostate cancer, including neuroendocrine tumours, are rare. However, unlike prostate adenocarcinoma, neuroendocrine prostate cancer is very aggressive and can quickly spread to other parts of the body. Treatments that are effective for adenocarcinomas in the prostate do not work against neuroendocrine prostate cancers.
Adenocarcinoma prostate cancers can progress into neuroendocrine prostate cancer. Until now, how this transition occurs has been a mystery.
To better understand how neuroendocrine prostate cancer develops, Dr Languino and colleagues looked for biomarkers of the disease. In previous work, they discovered that a molecule known as aVb3 integrin is abundant in mice and humans with neuroendocrine prostate cancer, but missing in prostate adenocarcinoma.
To look for molecules unique to neuroendocrine prostate cancer, the researchers found that aVb3 integrin expression in prostate cancer cells bumped up the expression of a known marker of neuroendocrine prostate cancer and significantly increased the expression of a molecule called Nogo receptor 2 (NgR2).
The finding “was a big discovery,” Dr Languino says. That’s because NgR2 is a protein found in nerve cells, where it contributes to neuronal functions. It has never before been studied in cancer, of any kind.
Dr Languino and her colleagues wanted to find out what this molecule, a neuronal protein, is doing in cancer.
An initial experiment revealed that NgR2 binds the aVb3 integrin. The scientists also saw that in mice with neuroendocrine prostate tumors, aVb3 integrin and NgR2 were both present in the primary tumor and in cancerous lesions that had formed in the lungs of the animals. A follow-up experiment made it clear that both aVb3 integrin and NgR2 are necessary for neuroendocrine prostate cancers.
When Dr Languino and her team lowered the amount of NgR2 in neuroendocrine prostate cancer cells, neuroendocrine markers also decreased. The results suggest that NgR2 plays a role in the development of neuroendocrine prostate cancer. Lowering the amount of NgR2 also reduced the ability of cancer cells to grow and move, indicating that NgR2 may have a hand in cancer spreading to other parts of the body, in a process known as metastasis. Metastases are often what makes cancers fatal.
“These two molecules, aVb3 integrin and NgR2, seem to create a combination that is lethal,” Dr Languino says.
She and her colleagues are now looking for a molecule or antibody that would block the effect of NgR2, or the aVb3 integrin/NgR2 complex, to inhibit their ability to promote neuroendocrine prostate cancer growth and development, and make the cancer more susceptible to therapy.
While chemotherapy is highly effective at killing cancer cells, it also kills healthy cells, something which medical research is trying minimise. Recently, ‘chronochemotherapy’ has garnered growing attention in the research community. As the name suggests, the aim is timing the delivery of the drug when the body is least vulnerable to the harmful effects of the drug, while the cancer cells are at their most vulnerable.
Chronochemotherapy exploits the fact that human physiological processes, including cell proliferation and differentiation, are regulated by the circadian clock. However, it is not yet widely exploited in real-world clinical settings because there at present is no systematic method to find the optimal chemotherapy delivery time.
This problem was tackled by an interdisciplinary team of researchers from the Institute for Basic Science (IBS), South Korea. They were led by the principal investigators, mathematician Kim Jae Kyoung at IBS and oncologist Koh Youngil at Seoul National University Hospital. The researchers studied a group of patients suffering from diffuse large B-cell lymphoma (DLBCL), which accounts for about 30 to 40% of non-Hodgkin’s lymphoma. Their findings are published in the journal JCI Insights.
The research team noticed that DLBCL patients at Seoul National University Hospital received chemotherapy at two different schedules, with some patients receiving morning treatment (8:30), while others taking the drugs in the afternoon (14:30). All patients received R-CHOP, which is a combination of targeted therapy and chemotherapy, 4 to 6 times in the morning or afternoon at intervals of about 3 weeks.
Figure 1. Chemotherapy in the afternoon can improve treatment outcomes The daily fluctuation of proliferative activity of bone marrow is larger in females than in males, and it becomes higher in the morning (left). Thus, chemotherapy in the morning strongly inhibits proliferative activity in female lymphoma patients, resulting in a higher incidence of adverse events such as neutropenia and infections. This forces the clinicians to reduce the dose intensity (center). Consequently, female patients undergoing the morning treatment show a lower survival probability than those undergoing the afternoon treatment (right). Specifically, only ~13% of female patients treated in the afternoon had a worse outcome and ~2% of them died while ~37% of female patients treated in the morning had a worse outcome and ~25% of them died. Male patients did not show any difference in treatment outcomes depending on the chemotherapy delivery time.
They analysed 210 patients to investigate differences between morning and afternoon treatment. They found that female patients who received afternoon treatment had 12.5 times reduced mortality rate (25% to 2%), while the cancer recurrence after 60 months was decreased by 2.8 times (37% to 13%). In addition, chemotherapy side effects such as neutropenia were more common in female patients who received morning treatment.
Surprisingly, there was no difference in treatment efficiency depending on the treatment schedule in the case of male patients.
To understand the cause of gender differences, the research team analysed ~14 000 blood samples from the Seoul National University Hospital Health Examination Center. It was found that in females, white blood cell count tends to decrease in the morning and increase in the afternoon. This indicates that the bone marrow proliferation rate is higher in the morning than in the afternoon because there is a ~12hr delay between the bone marrow proliferation and blood cell production.
This means that if a female patient receives chemotherapy in the morning when bone marrow is actively producing blood cells, the possibility of adverse side effects becomes greater. These results are consistent with the findings from recent randomised clinical trials that showed female colorectal cancer patients treated with irinotecan in the morning suffered from higher drug toxicities.
One confounding variable was the drug dose. Since the morning female patients suffered from greater adverse side effects, oftentimes the dose had to be reduced in these patients. On average, the drug dose was reduced by ~10% compared to the dose intensity given to female patients receiving the afternoon treatment.
Unlike female patients, it was found that male patients did not show a significant difference in white blood cell count and bone marrow cell proliferation activity throughout the day, which is the reason why the timing of the treatment had no impact.
Professor Koh Young-il said, “We plan to verify the conclusions of this study again with a large-scale follow-up study that completely controls confounding variables, and to confirm whether chemotherapy has similar effects in other cancers.”
Ci Kim Jae Kyung said, “Because the time of the internal circadian clock can vary greatly depending on the individual’s sleep-wake patterns, we are currently developing a technology to estimate the time of the circadian clock from the patient’s sleep pattern. We hope that it can be used to develop an individualised anti-cancer chronotherapy.”
New research published in Dermatologic Surgery indicates that simple laser treatments to the skin may help to prevent the development of basal cell carcinoma and squamous cell carcinoma, collectively known as keratinocyte carcinoma.
Conducted by a team of researchers from Massachusetts General Hospital, a founding member of Mass General Brigham, the work describes an easy-to-implement strategy to protect skin health.
Nonablative fractional lasers (NAFL) deliver heat in a fractional manner that leaves it fully intact after treatment, unlike ablative fractional lasers that remove the top layer of skin. Currently they are used to treat things such as scars, sun-damaged skin and age spots, but their effectiveness for preventing skin damage is unknown.
To investigate, Mathew Avram, MD, JD, director of the Mass General Dermatology Laser & Cosmetic Center, and his colleagues studied patients who had been successfully treated for facial keratinocyte carcinoma in the past. Such patients have a 35% risk of experiencing a subsequent keratinocyte carcinoma within 3 years and a 50% risk within 5 years.
In the study, 43 patients received NAFL therapy and 52 served as controls and did not receive NAFL therapy.
The rate of subsequent facial keratinocyte carcinoma development over an average follow-up of more than 6 years was 20.9% in NAFL-treated patients and 40.4% in controls, indicating that patients treated with NAFL had about half the risk.
Controlling for age, gender, and skin type, control patients were 2.65-times more likely to develop a new facial keratinocyte carcinoma than NAFL-treated patients.
Also, among patients who developed a facial keratinocyte carcinoma, the time to development was significantly longer in patients treated with NAFL compared with untreated patients.
“These findings suggest that NAFL treatment may have an important role in protecting against subsequent keratinocyte carcinomas,” says Avram.
“While the mechanism of NAFL’s protective effect is not completely understood, it is suspected that NAFL treatment reduces the overall burden of photo damaged keratinocytes and may promote a wound healing response, which gives healthy skin cells a selective advantage.”
Avram noted that additional studies are warranted to more critically assess the role of NAFL in skin cancer prevention, to reveal the duration of its protective effects, and to determine optimal treatment parameters.
“Based on this research, it’s encouraged for patients to have nonablative laser treatments to help prevent skin cancer if they are at risk or notice abnormalities,” says Avram.
The evolutionary secrets that enable the traditional Chinese medicinal herb known as barbed skullcap to produce cancer fighting compounds have been unlocked by a collaboration of UK and Chinese researchers, who published their research in the journal Molecular Plant.
The researchers used DNA sequencing technology to assemble the genomic sequence of skullcap (Scutellaria barbata) known in China as banzhilian. This gave researchers the genetic information, a microevolutionary history, required to identify how the plant produces the compound scutebarbatine A, which acts against a range of cancer cells.
Professor Cathie Martin, Group Leader at the John Innes Centre, and one of the authors of the study said, “We have found that the primary metabolite has activity against cancer cells but not non-cancer cells which is especially important for an anti-cancer metabolite. Now we are looking to develop synthetic methods for producing more of the lead compound.”
In Traditional Chinese Medicine (TCM), to isolate medicinal chemistry from the plant, the herb is boiled in water for two hours and extract is dried to produce a powder and taken as a decoction (concentrated liquid). Now, with the knowledge of the genes that make up the biochemical pathway behind the anti-cancer activity of the herb, researchers are close to being able to synthesise larger quantities of compounds more rapidly and sustainably by using a host such as yeast.
The research is led by CEPAMS, a partnership between the John Innes Centre and the Chinese Academy of Science and supported by The Royal Society.
“This is a fantastic collaboration about developing interesting drug leads from natural resources and shows the practical value of focusing on the microevolution of a species” said Professor Martin.
The Skullcap genus has been used for centuries in TCM for treatment of different medical conditions. Clinical work has shown that preparations based on Scutellaria barbata during chemotherapy can reduce the risk of metastatic tumours.
CEPAMS Group Leader based at Shanghai Dr Evangelos Tatsis said, “Natural products have long been the lead compounds for the discovery of new drugs. By following the trail of the traditional Chinese plants, we can develop new anti-cancer medicines and this research marks a crucial step in that direction.”
Plant-based traditional medicines have long been used to provide leads for the new drug discovery, leading to drugs such as vinblastine and taxol which are now used clinically as anticancer drugs.
TCM is one of the best catalogued systems with empirical information about the therapeutic properties of herbal remedies.
Anti-cancer drugs obtained from traditional Chinese medicine have higher efficacy than chemical synthetic drugs and with less toxic side effects. The genomes of medicinal skullcaps reveal the polyphyletic origins of clerodane diterpene biosynthesis in the family Laminiaceae, is published in Molecular Plant