

Tag: testosterone

Women are Turning to Testosterone, but What does the Science Actually Say?
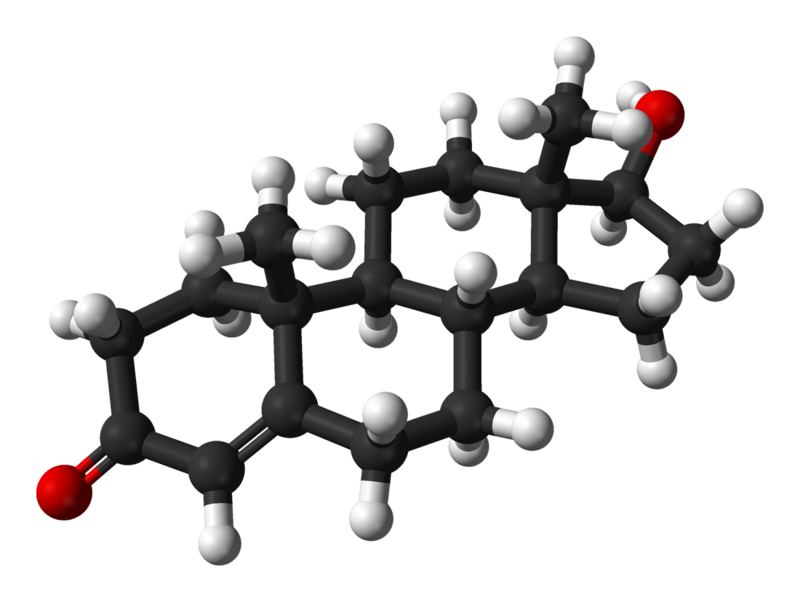
Ball and stick 3D model of testosterone. Source: Wikimedia CC0

Daniel Kelly, Sheffield Hallam University

A recent BBC report described women posing as men to get hold of testosterone gel, hoping to improve their menopause symptoms, because female testosterone products are not easily available to them. But why is the appetite for this predominantly male hormone exploding and are there risks involved?

Testosterone is usually thought of as the defining male hormone. It is linked to puberty, muscle development and reproductive function. But this overlooks an important biological reality. Women also produce testosterone, and it plays important roles throughout the body.

Although blood concentrations are typically about ten to 15 times lower than in men, testosterone remains biologically active in women.

Women make testosterone in their ovaries and adrenal glands, and the body also makes it by changing other hormones in fat, skin and muscle. Some of this testosterone is then used to make oestradiol, the main form of oestrogen in women of reproductive age.

But testosterone is not simply an oestrogen reservoir. It also acts directly on tissues throughout the body, including the bones, muscles, heart and blood vessels, and the brain. This has led researchers to look more closely at how testosterone may affect women’s health.

Similar to men, testosterone declines gradually across the reproductive lifespan, although patterns vary between individuals. This fall begins well before menopause, and unlike oestrogen, it doesn’t fall sharply at menopause as the ovaries decline.

Measuring how far it’s fallen is its own problem. Female levels are so low that routine blood tests have historically struggled to measure them reliably, making it hard to precisely define “normal” concentrations.

So why are increasing numbers of women interested in testosterone therapy after menopause?

What the evidence says

Because testosterone is known to influence sexual desire, one of its most studied uses in women is for hypoactive sexual desire disorder (HSDD) – persistent low sexual desire that causes distress.

A 2019 meta-analysis of 36 randomised trials found that carefully dosed testosterone can improve sexual desire and satisfaction in some postmenopausal women. International clinical guidelines recognise testosterone therapy as an evidence-based treatment for HSDD, the only condition in women for which there is enough clinical evidence to recommend testosterone therapy.

Sexual desire is shaped by relationships, stress, fatigue and mental health as much as by any single hormone. Testosterone is one input among several rather than a master switch.

Beyond sexual desire, high-quality clinical trial evidence in women is largely absent. But this does not necessarily mean testosterone has no broader influence on women’s health.

Randomised trials are the best way to establish whether a treatment causes a particular effect, but they cannot capture everything that happens in everyday medical practice. Patients may have other health problems or take several medicines, making it harder to know whether an improvement is due to testosterone or something else.

Testosterone is not a replacement for standard menopause hormone therapy. When it is prescribed, it is usually alongside oestrogen – and sometimes progesterone. Some women report that even after their conventional HRT (hormone replacement therapy) has been optimised, they still do not feel that their symptoms are fully addressed, and that adding testosterone makes a noticeable difference.

Women and doctors using testosterone in routine menopause care report improvements beyond sexual function. A recent UK study of 510 women at a specialist menopause clinic found that after four months on testosterone gel, women reported improvements in mood, cognitive symptoms and libido. These findings are interesting, but do not prove that the testosterone treatment caused these changes.

Real-world evidence should not replace randomised trials, but neither should the absence of large trials mean that these observations be simply dismissed. Instead, they can help identify effects worth testing in the clinical trials that are still needed.

A market that’s only just catching up

The evidence for using testosterone in women is strongest for sexual desire, but products made specifically for women have been much slower to arrive. In the US, for example, there’s still no approved testosterone product for women.

Of the three major sex hormones produced by the ovaries, oestrogen and progesterone have widely licensed products for women. Testosterone has been much slower to follow, with female-specific products still limited in many countries. This is despite evidence that testosterone can be used safely in women when given at doses designed to keep levels within the physiological female range.

International guidelines have recognised the lack of suitable products for women and called for testosterone treatments designed specifically for them. The issue is now receiving attention from regulators. In September 2026, the US Food and Drug Administration held a public workshop examining evidence gaps and the need for future drug development in this area.

Australia has led the way with Androfeme, a testosterone cream, being formally registered in 2020, specifically for female use. The UK granted it a marketing authorisation in July 2025, but it is not yet routinely available through the NHS.

The workaround has been men’s gel, measuring out a tenth of a sachet by eye. This is a less precise way to deliver a hormone for which the therapeutic dose is so small. If too much is applied, testosterone can rise above the desired range, increasing the likelihood of side-effects, such as acne and increased facial or body hair.

More importantly, evidence on the long-term safety of testosterone in women remains limited, particularly for heart disease, stroke and breast cancer, because trials have generally been short and often excluded women at higher risk of these conditions.

Demand continues to climb despite these uncertainties. NHS prescriptions to women in England rose roughly tenfold between 2015 and 2022, and in the US, testosterone prescribing has almost tripled over the past decade. The need for licensed female-specific testosterone products cannot be ignored, not just to improve access but to allow testosterone in women to be studied with the same scientific rigour it deserves.

Daniel Kelly, Senior Lecturer in Biochemistry, Sheffield Hallam University

This article is republished from The Conversation under a Creative Commons license. Read the original article.


Coffee’s Biological Benefits Linked to Metabolic Health and Sex Hormones

Photo by Porapak Apichodilok on Pexels

Coffee is one of the world’s most widely consumed beverages, and previous research has linked its consumption to a lower risk of conditions such as type 2 diabetes and cardiovascular disease. However, the biological mechanisms behind these benefits remain unclear. A new Finnish study links habitual coffee consumption to healthier body composition and metabolic markers, while revealing distinct associations with sex hormones in men and women.

The study, conducted at the University of Oulu, analysed data from 2264 participants aged 46 in the Northern Finland Birth Cohort 1966. Researchers examined how habitual coffee consumption was associated with circulating metabolites, cardiometabolic risk markers and sex hormones.

Despite having a similar body mass index (BMI), individuals with higher coffee consumption had lower total and visceral fat and greater skeletal muscle mass than those who consumed less coffee.

In both men and women, higher coffee consumption was correlated with lower circulating levels of branched-chain amino acids, biomarkers that have previously been linked to insulin resistance and an increased risk of type 2 diabetes when chronically elevated.

The strongest sex-specific associations were observed in men. Higher coffee consumption was linked to a more favourable glucose–insulin profile, higher concentrations of total and bioavailable testosterone, and increased levels of sex hormone-binding globulin (SHBG). At the same time, free testosterone and the free androgen index were modestly lower. In women, hormonal associations were more limited and were primarily characterised by higher SHBG and lower measures of free androgens.

“Coffee is consumed by millions of people every day, yet we still know surprisingly little about how it relates to our metabolism and hormones. What stood out in our findings was a distinct hormonal signature that didn’t disappear even after we took into account BMI and lifestyle factors, with several of these associations differing between men and women,” says Luca Verroest, lead author of the study and Doctoral Researcher at the University of Oulu.

The results suggest that hormonal pathways may partly explain the relationship between coffee consumption and metabolic health. However, as this was an observational study, the findings demonstrate associations rather than cause-and-effect relationships.

The study is particularly relevant in Finland, one of the world’s highest coffee-consuming countries, where annual consumption averages around 11.8 kilograms per person.

The researchers say the findings provide a foundation for future studies aimed at determining whether coffee itself drives these biological changes and identifying the compounds responsible. These questions are currently being investigated in animal models, with the long-term goal of progressing to human intervention studies. Further research will be needed before the findings could inform dietary recommendations.

The study, Associations of habitual coffee intake with testosterone and cardiometabolic markers: the Northern Finland Birth Cohort 1966 study, has been published in the European Journal of Nutrition on 16 July 2026.

Source: University of Oulu

Scientists Figure out Paradoxical Effect of Testosterone in Prostate Cancer

Ball and stick 3D model of testosterone. Source: Wikimedia CC0

A treatment paradox has recently come to light in prostate cancer: Blocking testosterone production halts tumour growth in early disease, while elevating the hormone can delay disease progression in patients whose disease has advanced.

The inability to understand how different levels of the same hormone can drive different effects in prostate tumours has been an impediment to the development of new therapeutics that exploit this biology.

Now, a Duke Cancer Institute-led study appearing in Nature Communications, provides the needed answers to this puzzle.

The researchers found that prostate cancer cells are hardwired with a system that allows them to proliferate when the levels of testosterone are very low. But when hormone levels are elevated to resemble those present in the normal prostate, the cancer cells differentiate.

“For decades, the goal of endocrine therapy in prostate cancer has been to achieve absolute inhibition of androgen receptor function, the protein that senses testosterone levels,” said lead investigator Rachid Safi, PhD, research assistant professor in the Department of Pharmacology and Cancer Biology, at Duke University School of Medicine.

“It’s been a highly effective strategy, leading to substantial improvements in overall survival,” he said. “Unfortunately, most patients with advanced, metastatic disease who are treated with drugs to inhibit androgen signaling will progress to an aggressive form of the disease for which there are limited therapeutic options.”

Using a combination of genetic, biochemical, and chemical approaches, the research team defined the mechanisms that enable prostate cancer cells to recognise and respond differently to varying levels of testosterone, the most common androgenic hormone.

It turned out to be rather simple. When androgen levels are low, the androgen receptor is encouraged to “go solo” in the cell. In doing so, it activates the pathways that cause cancer cells to grow and spread. However, as androgens rise, the androgen receptors are forced to “hang out as a couple,” creating a form of the receptor that halts tumour growth.

“Nature has designed a system where low doses of hormones stimulate cancer cell proliferation and high doses cause differentiation and suppress growth, enabling the same hormone to perform diverse functions,” McDonnell said.

In recent years, clinicians have begun treating patients with late-stage, therapy resistant prostate cancers using a monthly, high-dose injection of testosterone in a technique called bi-polar androgen therapy, or BAT. The inability to understand how this intervention works has hindered its widespread adoption as a mainstream therapeutic approach for prostate cancer patients.

“Our study describes how BAT and like approaches work and could help physicians select patients who are most likely to respond to this intervention,” McDonnell said. “We have already developed new drugs that exploit this new mechanism and are bringing these to the clinic for evaluation as prostate cancer therapeutics.”

Source: Duke University

A Mechanism that Links Anxiety to Testosterone

Photo by Inzmam Khan

A groundbreaking study has unveiled a significant link between anxiety disorders and a brain receptor known as TACR3, as well as testosterone. published last month in the journal Molecular Psychiatry.

Anxiety is a common response to stress, but for those dealing with anxiety disorders, it can significantly impact daily life.

Clinical evidence has hinted at a close connection between low testosterone levels and anxiety, particularly in men with hypogonadism, a condition characterised by reduced sexual function.

However, the precise nature of this relationship has remained unclear until now.

Prof Shira Knafo, head of the Molecular Cognitive Lab at Ben-Gurion University, led this new study which discovered male rodents exhibiting exceedingly high anxiety levels had notably lower levels of a specific receptor called TACR3 in their hippocampus.

The hippocampus is a brain region closely associated with learning and memory processes. TACR3 is part of the tachykinin receptor family and responds to a substance known as neurokinin.

This observation is what prompted the researchers to investigate the link between TACR3 deficiency, sex hormones, anxiety, and synaptic plasticity.

The rodents were classified based on their behavior in a standard elevated plus maze test measuring anxiety levels.

Subsequently, their hippocampi were isolated and underwent gene expression analysis to identify genes with varying expressions between rodents with extremely low anxiety and those with severe anxiety.

One gene that stood out was TACR3. Previous research had revealed that mutations in genes associated with TACR3 led to a condition known as “congenital hypogonadism,” resulting in reduced sex hormone production, including testosterone.

Notably, young men with low testosterone often experienced delayed sexual development, accompanied by depression and heightened anxiety.

This pairing led researchers to investigate the role of TACR3 further.

Prof. Knafo and her team were aided in their research by two innovative tools they crafted themselves.

The first, known as FORTIS, detects changes in receptors critical for neuronal communication within living neurons.

By utilizing FORTIS, they demonstrated that inhibiting TACR3 resulted in a sharp increase in these receptors on the cell surface, blocking the parallel process of long-term synaptic strengthening, known as LTP.

The second pioneering tool employed was a novel application of cross-correlation to measure neuronal connectivity within a multi-electrode array system.

This tool played a pivotal role in uncovering the profound impact of TACR3 manipulations on synaptic plasticity.

Synaptic plasticity refers to the ability of synapses, the connections between brain cells, to change their strength and efficiency.

This dynamic process is fundamental for the brain’s adaptation to the environment.

Through synaptic plasticity, the brain can reorganize its neural circuitry in response to new experiences.

This flexibility allows for the modification of synaptic connections, enabling neurons to strengthen or weaken their communication over time.

Essentially, synaptic plasticity is a key mechanism by which the brain encodes and stores information, adapting continuously to the ever-changing external stimuli and internal states.

Importantly, it revealed that deficiencies stemming from TACR3 inactivity could be efficiently rectified through testosterone administration, offering hope for novel approaches to address challenges related to anxiety associated with testosterone deficiency.

TACR3 is seemingly a central player in bridging anxiety and testosterone.

The researchers have unravelled the complex mechanisms behind anxiety and opened avenues for novel therapies, including testosterone treatments, that could improve the quality of life for individuals grappling with sexual development disorders and associated anxiety and depression.

Source: Ben-Gurion University of the Negev

A Keto Diet may Improve Fertility in Women with PCOS

Photo by Sora Shimazaki on Pexels

The ketogenic (keto) diet may lower testosterone levels in women with polycystic ovary syndrome (PCOS), according to a new paper published in the Journal of the Endocrine Society. The diet also appeared to lower follicle-stimulating hormone (FSH) levels, which may thereby improve the chances of ovulating. These improvements in hormonal balance could help alleviate fertility problems.

PCOS is the most common hormone disorder in women, affecting 7–10% of women of childbearing age. It can cause infertility and raises the risk of developing diabetes, obesity and other metabolic health problems.

Women with PCOS have at least two of these signs:

  • Elevated levels of testosterone and other androgen hormones associated with male reproduction,
  • Irregular periods, and
  • Large ovaries with many small follicles.

The keto diet is a high fat, low carbohydrate diet that has shown promising effects in women with PCOS. Studies have shown that it may help women lose weight and maintain weight loss, improve their fertility, optimise their cholesterol levels and normalise their menstrual cycles.

“We found an association between the ketogenic diet and an improvement in reproductive hormone levels, which influence fertility, in women with PCOS,” said study author Karniza Khalid, MBBS, MMedSc, of the Ministry of Health Malaysia in Kuala Lumpur, Malaysia. “These findings have important clinical implications, especially for endocrinologists, gynaecologists and dieticians who, in addition to medical treatment, should carefully plan and customise individual diet recommendations for women with PCOS.”

The researchers conducted a meta-analysis of clinical trials in women with PCOS on the keto diet and examined the diet’s effects on their reproductive hormones (FSH, testosterone and progesterone) and weight change.

They found women with PCOS who were on the keto diet for at least 45 days saw significant weight loss and an improvement in their reproductive hormone levels. Their FSH ratio was lower, which means they may have a better chance of ovulating. The women also had lower testosterone levels, which could help with excess hair growth and other symptoms of excess male sex hormones.

Source: The Endocrine Society

Study Reveals How Androgen Receptor Functions are Affected by Mutations

Testosterone molecule
Model of a testosterone molecule. Source: Wikimedia CC0

The androgen receptor is a key transcriptional factor for proper sex development, especially in males and the physiological balance of all the tissues that express this receptor. The androgen receptor is involved in several pathologies and syndromes, such as spinal and bulbar muscular atrophy or androgen insensitivity syndrome, for which there is no specific treatment. Regarded as the main initial and progression factor in prostate cancer, this receptor has been the main therapeutic target for the treatment against this disease for decades.

Now, a study published in Science Advances describes the structural and functional effects of mutations on the androgen receptor, as well as how these changes lead to the development of prostate cancer.

Point mutations in the androgen receptor

The human androgen receptor is a key protein in the development and functioning of the prostate in response to male hormones, such as testosterone. Point mutations in the androgen receptor – specifically, one amino acid swapped for another – are one of the main mechanisms than can lead to structural and functional alterations in the receptor, which result in the development of diseases.

The results of the University of Barcelona-led study show that the analysed mutations affect several functional regions of the union domain of the androgen receptor to testosterone. In particular, these are mutations that alter a region of the receptor which is the target for posttranscriptional modifications (that is, modifications in the protein once this is produced).

This type of chemical alterations affect specific amino acids of the androgen receptor and are executed by regulating proteins which are critical for the proper functioning of the receptor. If this receptor’s regulation pathway is altered, such as the case of the presence of mutations described by the team, its function is deregulated and it can be dysfunctional and cause pathologies.

“In our study, we experimentally checked that these mutations deregulate a specific mutation, known as arginine methylation, which is one of the posttranscriptional modifications, due to the structural changes these alterations produce in a functional area of the receptor. Also, we could observe that the deregulation of the androgen receptor methylation involves relevant changes in its function within the cell,” the team concludes.

Source: University of Barcelona

Hormone Discovery could Predict Longevity of Men

Old man jogging
Photo by Barbra Olsen on Pexels

Researchers have discovered that a certain hormone, that develops in males during puberty, could be predictive of the risk of developing age-related disease in later life.

The novel insulin-like peptide hormone, called INSL3, was found by researchers to be consistent over long periods of time and is an important early biomarker for prediction of age-linked disease. Their latest findings have been published today in Frontiers in Endocrinology.

INSL3 is produced in the testes by Leydig cells, which also make testosterone, but unlike testosterone which fluctuates over a man’s life, INSL3 remains consistent, with the level at puberty staying about the same throughout life, decreasing only slightly into old age. This makes it the first clear and reliable predictive biomarker of age-related morbidity as compared to any other measurable parameters.

Blood levels of INSL3 were associated with a range of age-related illnesses, such as bone weakness, sexual dysfunction, diabetes, and cardiovascular disease.

Since the hormone is so consistent, a young man with high INSL3 would still have high INSL3 when he is older. But low levels of INSL3 when young will stay low when older, making a man more likely to acquire typical age-related illnesses. This opens up exciting possibilities for predicting age-related illnesses and finding ways to prevent the onset of these diseases with early intervention.

This study from University of Nottingham was led by Professors Ravinder Anand-Ivell and Richard Ivell and is the latest of three recent studies into this hormone. Prof Anand-Ivell explains: “The holy grail of ageing research is to reduce the fitness gap that appears as people age. Understanding why some people are more likely to develop disability and disease as they age is vital so that interventions can be found to ensure people not only live a long life but also a healthy life as they age. Our hormone discovery is an important step in understanding this and will pave the way for not only helping people individually but also helping to ease the care crisis we face as a society.”

The team analysed blood samples from 3000 men, with two samples taken four years apart and found that unlike testosterone, INSL3 remains at consistent.

The study also showed that there is an almost 10-fold variation in INSL3 levels in the normal male population, even among the young and healthy.

Prof Ivell adds: “Now we know the important role this hormone plays in predicting disease and how it varies amongst men we are turning our attention to finding out what factors have the most influence on the level of INSL3 in the blood. Preliminary work suggests early life nutrition may play a role, but many other factors such as genetics or exposure to some environmental endocrine disruptors may play a part.”

Source: University of Nottingham

Low Testosterone may be a Risk Factor for Severe COVID

Testosterone molecule
Model of a testosterone molecule. Source: Wikimedia CC0

Among men with COVID, those with low testosterone levels are more likely to become seriously ill and be hospitalised than men with normal levels of the hormone, according to a study which appears in JAMA Network Open.

Analysis of data for 723 men who tested positive for COVID, mostly in 2020 before vaccines were available, indicated that low testosterone is an independent risk factor for COVID hospitalisation, similar to diabetes, heart disease and chronic lung disease.

They found that men with low testosterone who developed COVID were 2.4 times more likely to require hospitalisation than men with hormone levels in the normal range. Further, men who were once diagnosed with low testosterone but successfully treated with hormone replacement therapy were no more likely to be hospitalised for COVID than men whose testosterone levels had always tested in the normal range.

The findings, by researchers from the Washington University School of Medicine in St. Louis and Saint Louis University School of Medicine, suggest that treating men with low testosterone may help protect them against severe disease and reduce the burden on hospitals during COVID waves.

“It is very likely that COVID is here to stay,” said co-senior author Abhinav Diwan, MD, a professor of medicine at Washington University. “Hospitalizations with COVID are still a problem and will continue to be a problem because the virus keeps evolving new variants that escape immunization-based immunity. Low testosterone is very common; up to a third of men over 30 have it. Our study draws attention to this important risk factor and the need to address it as a strategy to lower hospitalisations.”

Prof Diwan and co-senior author Sandeep Dhindsa, MD, an endocrinologist at Saint Louis University, had previously shown that men hospitalised with COVID have abnormally low testosterone levels. However, severe illness or traumatic injury can cause a temporary drop in hormone levels, so causation cannot be proved in data from men already hospitalised with COVID. Data were needed for men with chronically low testosterone before COVID infection.

Profs Diwan, Dhindsa and colleagues identified 723 men whose testosterone levels had been measured between Jan. 1, 2017, and Dec. 31, 2021, and who had documented cases of COVID in 2020 or 2021. In some cases, testosterone levels were measured after the patient recovered from COVID. Since low testosterone is a chronic condition, men who tested low a few months after recovering from COVID probably had low levels before as well, Prof Dhindsa said.

The researchers identified 427 men with normal testosterone levels, 116 with low levels, and 180 who previously had low levels but were being successfully treated, meaning that they were on hormone replacement therapy and their testosterone levels were in the normal range at the time they developed COVID.

“Low testosterone turned out to be a risk factor for hospitalisation from COVID, and treatment of low testosterone helped to negate that risk,” Prof Dhindsa said. “The risk really takes off below a level of 200 nanograms per decilitre, with the normal range being 300 to 1000 nanograms per decilitre. This is independent of all other risk factors that we looked at: age, obesity or other health conditions. But those people who were on therapy, their risk was normal.”

Men with low testosterone levels can experience sexual dysfunction, depressed mood, irritability, difficulty with concentration and memory, fatigue, loss of muscular strength and a reduced sense of well-being overall. When a man’s quality of life is clearly diminished, he is typically treated with testosterone replacement therapy. When the symptoms are mild, though, doctors and patients may hesitate to treat.

The two main concerns related to testosterone therapy are an increased risk of prostate cancer and heart disease. Testosterone is well known to boost prostate cancer, but for heart disease, the evidence for risk is more ambiguous. A large clinical trial on the relationship between heart health and testosterone supplementation is expected to be completed soon.

“In the meantime, our study would suggest that it would be prudent to look at testosterone levels, especially in people who have symptoms of low testosterone, and then individualise care,” said Prof Diwan, whose specialty is cardiology. “If they are at really high risk of cardiovascular events, then the doctor could engage the patient in a discussion of the pros and cons of hormone replacement therapy, and perhaps lowering the risk of COVID hospitalisation could be on the list of potential benefits.”

Since this study is observational, it only suggests that boosting testosterone levels may help men avoid severe COVID, Diwan cautioned. A clinical trial would be needed to demonstrate conclusively whether such a strategy works.

Source: Washington University School of Medicine

Low Sex Hormone Levels Linked to Rotator Cuff Tears

Photo by Harlie Raethel on Unsplash

Patients with lower levels of sex hormones are more likely to need to undergo surgery for rotator cuff tears, suggests a study in The Journal of Bone & Joint Surgery. 

Sex hormone deficiencies “was associated with a significantly increased incidence of RCR within [two] independent databases,” according to the new research by Peter N. Chalmers, MD, and colleagues at University of Utah. These findings add to previous evidence that hormone levels may be a systemic factor contributing to the development of rotator cuff tears, a common condition that is a major cause of shoulder pain.

The study used health insurance data for nearly 230 000 adults under age 65 who underwent surgery to repair a torn rotator cuff from 2008 through 2017. Patients were matched for age, sex, and type of insurance to patients who did not undergo rotator cuff surgery.

Patients undergoing rotator cuff repair had an average age of 54 years, and 58% were men. Most patient characteristics were similar between those who underwent rotator cuff repair and those who did not, except tobacco use, which was more common in the surgical cohort.

Dr Chalmers and colleagues found that 27% of women and 7% of men undergoing rotator cuff surgery had diagnosed sex hormone deficiency, compared with 20% and 4% respectively in the control group. Controlling for other factors, rotator cuff repair likelihood was 48% higher in women with oestrogen deficiency and 89% higher in men with testosterone deficiency.

To confirm their findings, the researchers then accessed the Veterans Administration Genealogy database which has data on millions of individuals. Here, they found that rotator cuff repair was about 2.5 times more likely for women with oestrogen deficiency and three times more likely for men with testosterone deficiency.

This study builds on a prior study by the same research group, which demonstrated that women with mutations in an oestrogen receptor gene were more likely to develop rotator cuff disease, with higher rates of failed rotator cuff surgery.

Despite limitations such as not accounting for hormone replacement therapy, the observed association between sex hormone deficiency and rotator cuff repair strongly supports the theory that low oestrogen and testosterone levels may contribute to the development of rotator cuff tears. The researchers concluded that “Future prospective studies will be necessary to understand the relationship of sex hormones to the pathophysiology of rotator cuff disease.”

Source: EurekAlert!

Study Implicates High Leptin Levels in Androgen Deficiencies

Source: National Cancer Institute on Unsplash

Researchers have uncovered new clues about the cellular processes that can lead to androgen deficiencies, in which high leptin levels appear to play a role. The findings are published in the journal Cell Death & Disease.

Symptoms of testosterone deficiency include low sex drive, erectile dysfunction, depression, and fatigue. TD afflicts approximately 30% of men aged 40-79 years, with an increase in prevalence strongly associated with ageing and common medical conditions including obesity, diabetes, and hypertension.

“Although testosterone deficiency may be present in one in five men 40 years or older, the driving factors remain largely unknown,” said Himanshu Arora, PhD, assistant professor of urology.

Dr Arora’s lab examined the effect of different concentrations of leptin on the microenvironment of the testes. The research builds on prior studies of how Sertoli and peritubular myoid cells (PMC) in the testicular microenvironment help drive Leydig stem cell differentiation via the cellular desert hedgehog signalling pathway, which transmits information to embryonic cells that guides proper cell differentiation.

The researchers extracted cellular samples from men undergoing testes biopsies for sperm retrieval. When the testes microenvironment secreted leptin in low doses, they found that Leydig stem cells differentiated into adult Leydig cells producing normal levels of testosterone. Higher doses of leptin were observed to depress testosterone levels.

“Our findings identify leptin as a key factor within the testes microenvironment,” said Dr Arora, adding that the insight “holds important implications for androgen deficiency and could have further application in prostate cancer research.”

Noting that leptin is already used in treating patients for obesity, “Preclinical studies could indicate whether adjusting levels of this hormone would be helpful in patients with testosterone deficiency,” said Ranjith Ramasamy, MD, study co-author and associate professor and director of the Miller School’s Reproductive Urology Program.

Source: University of Miami Health System, Miller School of Medicine

