

Tag: postmenopausal

The Ovary Doesn’t Retire After Menopause

Postmenopausal human ovaries show progressive molecular remodelling and inflammatory shifts
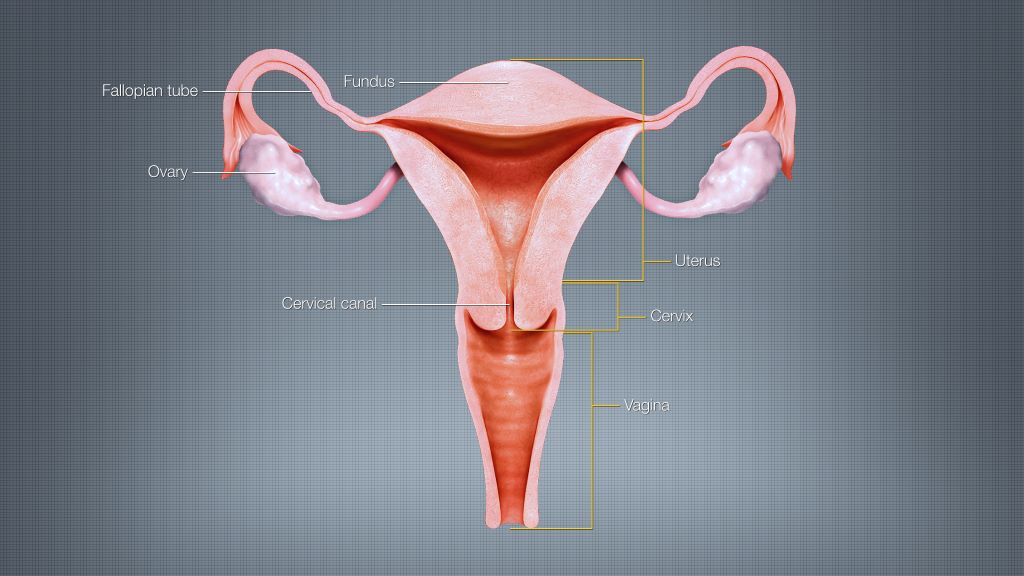
Female reproductive system. Credit: Scientific Animations CC4.0 BY-SA

Contrary to popular belief, the postmenopausal ovary is not defunct.

In a new, paradigm-shifting study of ovaries from 28 women, scientists at Northwestern University and the Buck Institute for Research on Aging found that in the decades after menopause the ovary remains biologically active and continues to remodel with age, showing increased inflammation and changes in tissue structure. The study also identified a molecular link between ovarian ageing and cancer.

The study was published on 14 October in Aging Cell.

“In the ovary, we reach a point of no return with respect to fertility in which it’s no longer producing eggs, and I would venture to say most people assume those ovaries are just sitting there doing nothing, similar to the appendix,” said co-corresponding author Francesca Duncan (associate professor of reproductive science in medicine, Northwestern University Feinberg School of Medicine; associate professor in residence, Buck Institute). “But that’s what makes this study very different.”

The findings challenge the notion that the ovary is an innocent bystander after reproduction ends, raising questions about whether it could play a more active role in ageing and chronic disease in women.

“The ovary is not just a reproductive organ,” said co-corresponding author Birgit Schilling (professor and director of the Mass Spectrometry Center, Buck Institute). “It really influences how somebody ages because it speaks to all these other organs, such as the brain, and also to the bone, and women after menopause experience often a lot of bone problems. So, we think there is a connection between all these organs.”

Women now routinely live for decades after menopause, making it increasingly important to understand what the ovary is doing during this long post-reproductive period, Duncan said.

“Is the ovary the canary in the coal mine in women?” said Duncan. “Could ageing in the ovary set off a cascade of changes that continues throughout the body as women get older?”

Duncan’s group previously found similar evidence of continued remodelling in postmenopausal ovaries of mice. When she embarked on that research and the current study in humans, she expected to see very little activity in the postmenopausal ovary.

“I was predicting that if we took a 50-year-old ovary, a 60-year-old ovary, a 70-year-old, an 80-year-old ovary, they would all look exactly the same, have no eggs, and basically be non-functional,” Duncan said. “The fact that across species we’re seeing this gives us confidence that this isn’t just some random event, but something truly meaningful is happening in the biology.”

What remains unknown is exactly what the ovary is doing after menopause and whether those changes are beneficial or harmful, Duncan said.

“Our data points to progressive ageing features in which the ovary appears to lose its original identity and ends up doing something different,” Duncan said. “We do not yet know if there’s ever a point in a woman’s life when this organ is no longer beneficial and it’s actually harmful. These results really point to the need to ask this question.”

To characterise the changes, Schilling’s team – spearheaded by Buck Institute staff scientist Mark Watson – used advanced proteomic technologies to analyse 5,812 protein groups in normal ovarian tissue from postmenopausal women aged 50 to 75.

Human ovarian tissue is difficult to obtain, making the 28 ovaries an unusually valuable collection. By focusing exclusively on women within a relatively narrow 25-year age range after menopause, the researchers examined molecular changes that continue during the postmenopausal years. The technology allowed examination of thousands of proteins across every sample and identification of patterns using multiple statistical approaches.

Those analyses showed that the ovary continues to change well after its reproductive life ends.

Ovaries from younger postmenopausal women had more proteins involved in maintaining cells and tissue structure, while older ovaries had more proteins associated with inflammation, immune activity and the ongoing breakdown and rebuilding of the extracellular matrix. The differences were most pronounced between ovaries from women in their 50s and those from women 70 and older.

“When we analysed the data in multiple different statistical ways, what became clear across all these methodologies is that the ovary was not stagnant,” Schilling said. “In fact, over the decades, there were quite dramatic differences in terms of some proteins’ levels would go up with age and some proteins’ levels would go down, which tells us this organ is quite dynamic.”

The ageing ovaries also showed some of the same molecular patterns seen in cellular senescence.

The findings build on a discovery Duncan’s lab made a decade ago. In 2016, the lab was the first to report that as ovaries age they become increasingly inflamed, fibrotic and stiff. Because cancer cells can thrive in collagen-rich, stiff environments, the scientists have been investigating whether these age-related changes could make the ovary more hospitable to cancer cells.

The new study provides a molecular view of that remodelling process later in life. As postmenopausal ovaries aged, proteins involved in maintaining tissue structure declined, while proteins involved in inflammation and reshaping the tissue environment became more prominent.

Although all the ovarian tissue in the study appeared normal and cancer-free, some proteins previously associated with ovarian cancer were more abundant in ageing ovaries, with the strongest signal among women in their 60s. The finding does not mean the ovaries were cancerous or precancerous, but suggests healthy ovarian ageing and ovarian cancer share some biological processes.

“It’s not that all postmenopausal women get ovarian cancer, but we know that that fibrotic inflammatory environment is certainly an environment that cancer cells prefer to home in on,” Duncan said. “This is all consistent with the idea that the ageing ovary is a potential third hit for ovarian cancer, with the first hit being genetic and the second hit being environmental. So can we target the ageing ovary therapeutically to lower the risk of ovarian cancer, or can we develop novel biomarkers of ovarian cancer?”

The findings do not answer whether healthy ovaries should ever be removed after menopause. Rather, they raise new questions about how the biological activity of the postmenopausal ovary might influence women’s health systemically and whether the observed changes contribute to disease or are features of normal ageing.

Source: Northwestern University

‘Wait and See’: Three Words Costing Postmenopausal Women Their Hair

More than half of postmenopausal women have clinically measurable hair loss. The most common response is to tell them to do nothing

Photo by Kateryna Hliznitsova on Unsplash

52% of postmenopausal women experience female-pattern hair loss, according to peer-reviewed research published in Menopause, the journal of the North American Menopause Society. Hot flushes – one of the symptoms that owns many public conversations about menopause – affect a larger proportion of women, but the disparity is not in the data. It is in how medicine responds to them. At more than one in two women, female-pattern hair loss is routinely absent from clinical consultations, rarely investigated at first presentation, and almost universally met with the same advice: give it time.

Why timing matters

During and after menopause, declining oestrogen levels and shifts in androgen balance cause susceptible hair follicles to gradually shrink. Each hair grows finer and shorter, with a briefer growth period per cycle. Left long enough without intervention, some follicles reach a point of no return, and the damage becomes irreversible.

“When we say irreversible, we mean that the follicle has become so damaged or inactive that it can no longer reliably regenerate a healthy terminal hair on its own,” says Dr Kashmal Kalan, Medical Director at Alvi Armani South Africa. “Medical therapies may help stabilise surrounding hair at that stage, but they may not recover what has already been lost,” says Dr Kalan.

For many women, that window closes not because they made an informed decision, but because nobody told them they had options. The advice they received – that gradual thinning is normal, that stress is a likely factor, that it may settle with time – sounded measured.

The cost of being dismissed

When the condition is classified as cosmetic, clinical urgency disappears. The patient is reassured rather than assessed, even though menopausal thinning is frequently a visible signal of systemic change. Hormonal shifts, nutritional deficiencies, thyroid dysfunction, and inflammatory or metabolic factors are all documented contributors, and none of them are cosmetic.

The consequences reach well beyond the scalp. Research published in the British Journal of Dermatology found that over 60% of women with hair loss actively avoided social interactions because of it. A separate study in the Journal of Cosmetic Dermatology found that affected women reported significantly higher social anxiety, lower self-esteem, and reduced life satisfaction compared to men experiencing the same condition. What begins on the scalp moves into how a woman presents professionally, how she engages socially, and how she sees herself.

A clinical framework built for men, applied to women

The protocols widely used to assess and treat this condition were largely developed around male patients. Defined hairline recession, concentrated donor areas, and linear progression are all considered male presentations. As a result, women have largely been assessed within a framework built for someone else.

“Applying male-based protocols to women can absolutely compromise outcomes. Female hair restoration requires an understanding of female-specific patterns of loss, progression risk, and the long-term hormonal picture. Preservation of softness, natural density gradients, and age-appropriate framing are considerations with no real equivalent in the male framework. In experienced hands, those distinctions are built into every stage of assessment and planning – not treated as secondary.”

What rigorous care looks like

At Alvi Armani, the first step is not a treatment recommendation – it is a diagnosis. A comprehensive workup, including blood investigations, is conducted before any intervention is discussed, because in menopausal women the drivers are rarely singular and what is visible on the scalp is seldom the whole picture.

“Not every patient is an immediate candidate for surgical restoration and recognising this is itself part of responsible practice. Medical stabilisation, non-surgical therapies, and hormonal management in collaboration with relevant specialists all form part of the treatment landscape – guided by individual diagnosis, not assumption,” Dr Kalan concludes.

“If any of this sounds familiar – the gradual changes, the concerns dismissed, the years of quietly adapting – it is worth knowing that the window is not necessarily closed. But it is also not standing still. Hair loss during menopause is extremely common – but common does not mean insignificant, and it does not mean inevitable.”

Higher Oestrogen Levels Protect Older Women Against Severe COVID

Photo by Ravi Patel on Unsplash

An older woman’s oestrogen levels may be linked to her chances of dying from COVID, with higher levels of the hormone seemingly protective against severe infection, according to a study published in BMJ Open.

Supplemental hormone treatment to curb the severity of COVID infection in post-menopausal women could be investigated, the researchers suggested.

Even after accounting for other factors, women seem to have a lower risk of severe COVID infection than men. This holds true for other serious recent viral infections, such as MERS (Middle East Respiratory Syndrome).

Oestrogen may have a role in this gender discrepancy, so to invesitgate the researchers compared the potential effects of boosting and reducing oestrogen levels on COVID infection severity.

They drew on Swedish national data, and the study sample included 14 685 women in total: 227 (2%) had been previously diagnosed with breast cancer and were on oestrogen blocker drugs (adjuvant therapy) to curb the risk of cancer recurrence; and 2535 (17%) were taking hormone replacement therapy (HRT) to boost their oestrogen levels in a bid to relieve menopausal symptoms.

Some 11,923 (81%) women acted as the comparison group as they weren’t on any type of treatment, either to enhance or reduce their systemic oestrogen levels.

Analysis of all the data showed that compared with no oestrogen treatment, the crude odds of dying from COVID were twice as high among women on oestrogen blockers but 54% lower among women on HRT.

After accounting for potentially influential factors, COVID mortality risk remained significantly lower (53%) for women on HRT.

Unsurprisingly, age was significantly associated with COVID mortality risk, with each extra year associated with 15% greater odds, while every additional coexisting condition increased the odds of death by 13%.

And those with the lowest household incomes were nearly 3 times as likely to die as those with the highest.

As an observational study, it cannot establish cause. There were no data on the precise doses of HRT or oestrogen blocker drugs, or their duration, nor on weight or smoking, while the number of women on adjuvant therapy was relatively small.

These factors may have been influential. But the researchers conclude: “This study shows an association between oestrogen levels and COVID death. Consequently, drugs increasing oestrogen levels may have a role in therapeutic efforts to alleviate COVID severity in postmenopausal women and could be studied in randomised control trials.”

Source: EurekAlert!

Reduced Heart Failure Risk in Postmenopausal Women Who Walk Faster

Photo by Teona Swift from Pexels

A study of postmenopausal women, published in the Journal of the American Geriatrics Society, found that those who reported a faster walking pace had a lower risk of developing heart failure. 

Among 25 183 women aged 50 to 79 years, there were 1455 cases of hospitalisation for heart failure during a median follow-up of 16.9 years. Compared with women who walked at a casual pace, those who walked at an average pace or fast pace had 27% and 34% lower risks of heart failure, respectively.

Fast walking for less than 1 hour per week was associated with the same risk reduction of heart failure as average or casual walking for more than 2 hours per week.

“This study confirms other studies demonstrating the importance of walking speed on mortality and other cardiovascular outcomes,” said senior author Charles B. Eaton, MD, MS, of the Warren Alpert Medical School of Brown University. “Given that limited time for exercise is frequently given as a barrier to regular physical activity, walking faster but for less time might provide similar health benefits as the recommended 150 minutes per week of moderate physical activity.”

Further study is warranted to determine whether interventions to increase the walking pace in older adults will reduce heart failure risk and whether fast pace will compensate for the short duration of walking.

Source: Wiley

