Category: Cardiovascular Disease

Cardiovascular Disease Deaths Worldwide Linked to Widely Used Phthalates

Phthalates are commonly used in plastic medical equipment
Photo by Marcelo Leal on Unsplash

Daily exposure to certain chemicals used to make plastic household items could be linked to the more than 356 000 global deaths from cardiovascular disease that occurred in 2018 alone, a new analysis of population surveys shows.

Although the chemicals, called phthalates, are in widespread use globally, the Middle East, South Asia, East Asia, and the Pacific bore a much larger share of the death toll than others – about three-fourths of the total.

For decades, experts have connected health problems to exposure to certain phthalates found in cosmetics, detergents, solvents, plastic pipes, bug repellents, and other products. These chemicals break down into microscopic particles and are ingested, and studies have linked such exposure to an increased risk of conditions ranging from obesity and diabetes to fertility issues and cancer.

Led by researchers at NYU Langone Health and published in eBioMedicine, the current study focused on a kind of phthalate called di-2-ethylhexyl phthalate (DEHP). This chemical is used to increase the flexibility and softness of food containers, medical equipment, and other plastic items. Exposure has been shown in other studies to prompt inflammation in the heart’s arteries, which over time is associated with increased risk of heart attack or stroke. In their new analysis, the authors estimated that DEHP exposure contributed to 356 238 deaths, or more than 13% of all global mortality from heart disease in 2018 among men and women ages 55 through 64.

“By highlighting the connection between phthalates and a leading cause of death across the world, our findings add to the vast body of evidence that these chemicals present a tremendous danger to human health,” said study lead author Sara Hyman, BS, an associate research scientist at NYU Grossman School of Medicine.

In a past study from 2021, the research team tied phthalates to more than 50 000 premature deaths each year, mostly from heart disease, among older Americans. Their latest investigation is believed to be the first global estimate to date of cardiovascular mortality, or indeed any health outcome, resulting from exposure to the chemicals, said Hyman, who is also a graduate student at NYU School of Global Public Health.

For the research, the team used health and environmental data from dozens of population surveys to estimate DEHP exposure across 200 countries and territories. The information included urine samples containing chemical breakdown products left by the plastic additive. Mortality data was obtained from the Institute for Health Metrics and Evaluation, a research group in the United States that collects medical information worldwide to identify trends in public health.

Among the key findings, the study showed that losses in the combined region of East Asia and the Middle East and the combined region of East Asia and the Pacific accounted, respectively, for about 42% and 32% of the mortality from ardiovascular disease linked to DEHP. Specifically, India had the highest death count, at 103 587 deaths, followed by China and Indonesia. The larger heart death risks in these populations held true even after the researchers adjusted their statistical analysis to take into account population size within the studied age group.

A possible explanation, the authors say, is that these countries face higher rates of exposure to the chemicals, possibly because they are undergoing a boom in plastic production but with fewer manufacturing restrictions than other regions.

“There is a clear disparity in which parts of the world bear the brunt of heightened heart risks from phthalates,” said study senior author Leonardo Trasande, MD, MPP. “Our results underscore the urgent need for global regulations to reduce exposure to these toxins, especially in areas most affected by rapid industrialisation and plastic consumption,” added Dr Trasande, Professor of Pediatrics at NYU Grossman School of Medicine.

Dr Trasande, who is also a professor in the Department of Population Health, cautions that the analysis was not designed to establish that DEHP directly or alone caused heart disease and that higher death risks did not take into account other types of phthalates. Nor did it include mortality among those in other age groups. As a result, the overall death toll from heart disease connected to these chemicals is likely much higher, he says.

Dr Trasande says that the researchers next plan to track how reductions in phthalate exposure may, over time, affect global mortality rates, as well as to expand the study to other health concerns posed by the chemicals, such as preterm birth.

Source: NYU Langone Health / NYU Grossman School of Medicine

A New Way of Visualising BP Data to Better Manage Hypertension

Photo by National Cancer Institute on Unsplash

If a picture is worth a thousand words, how much is a graph worth? For doctors trying to determine whether a patient’s blood pressure is within normal range, the answer may depend on the type of graph they’re looking at.

A new study from the University of Missouri highlights how different graph formats can affect clinical decision-making. Because blood pressure fluctuates moment to moment, day to day, it can be tricky for doctors to accurately assess it.

“Sometimes a patient’s blood pressure is high at the doctor’s office but normal at home, a condition called white coat hypertension,” said Victoria Shaffer, a psychology professor in the College of Arts and Science and lead author of the study published in the Journal of General Internal Medicine. “There are some estimates that 10% to 20% of the high blood pressure that gets diagnosed in the clinic is actually controlled – it’s just white coat hypertension – and if you take those same people’s blood pressure at home, it is really controlled.”

In the study, Shaffer and the team showed 57 doctors how a hypothetical patient’s blood pressure data would change over time using two different types of graphs. One raw graph showed the actual numbers, which displayed peaks and valleys, while the other graph was a new visual tool they created: a smoothed graph that averages out fluctuations in data.  

When the blood pressure of the patient was under control but had a lot of fluctuation, the doctors were more likely to accurately assess the patient’s health using the new smoothed graph compared to the raw graph.

“Raw data can be visually noisy and hard to interpret because it is easy to get distracted by outliers in the data,” Shaffer said. “At the end of the day, patients and their doctors just want to know if blood pressure is under control, and this new smoothed graph can be an additional tool to make it easier and faster for busy doctors to accurately assess that.”

This proof-of-concept study is the foundation for Shaffer’s ongoing research with Richelle Koopman, a professor in the School of Medicine, which includes working with Vanderbilt University and Oregon Health & Science University to determine whether the new smoothed graph can one day be shown to patients taking their own blood pressure at home. The research team is working to get the technology integrated with HIPAA-compliant electronic health records that patients and their care team have access to.

This could alleviate pressure on the health care system by potentially reducing the need for in-person visits when blood pressure is under control, reducing the risk for false positives that may lead to over-treatment.

 “There are some people who are being over-treated with unnecessary blood pressure medication that can make them dizzy and lower their heart rate,” Shaffer said. “This is particularly risky for older adults who are more at risk for falling. Hopefully, this work can help identify those who are being over-treated.”

The findings were not particularly surprising to Shaffer.

“As a psychologist, I know that, as humans, we have these biases that underlie a lot of our judgments and decisions,” Shaffer said. “We tend to be visually drawn to extreme cases and perceive extreme cases as threats. It’s hard to ignore, whether you’re a patient or a provider. We are all humans.”

Given the increasing popularity of health informatics and smart wearable devices that track vital signs, the smoothed graphs could one day be applied to interpreting other health metrics.

“We have access to all this data now like never before, but how do we make use of it in a meaningful way, so we are not constantly overwhelming people?” Shaffer said. “With better visualisation tools, we can give people better context for their health information and help them take action when needed.”

Source: EurekAlert!

This Injected Polymer Boosts Healing after a Heart Attack

Human heart. Credit: Scientific Animations CC4.0

Researchers have developed a new therapy that can be injected intravenously right after a heart attack to promote healing and prevent heart failure. The therapy both prompts the immune system to encourage tissue repair and promotes survival of heart muscle cells after a heart attack. Researchers tested the therapy in rats and showed that it is effective up to five weeks after injection.

The research team, led by bioengineers at the University of California San Diego and chemists at Northwestern University, published their findings in Advanced Materials.

“Preventing heart failure after a heart attack is still a major unmet clinical need,” said Karen Christman, one of the study’s corresponding authors and a professor of bioengineering at UC San Diego. “The goal of this therapy is to intervene very soon after someone suffers a heart attack to keep them from ultimately going into heart failure.”

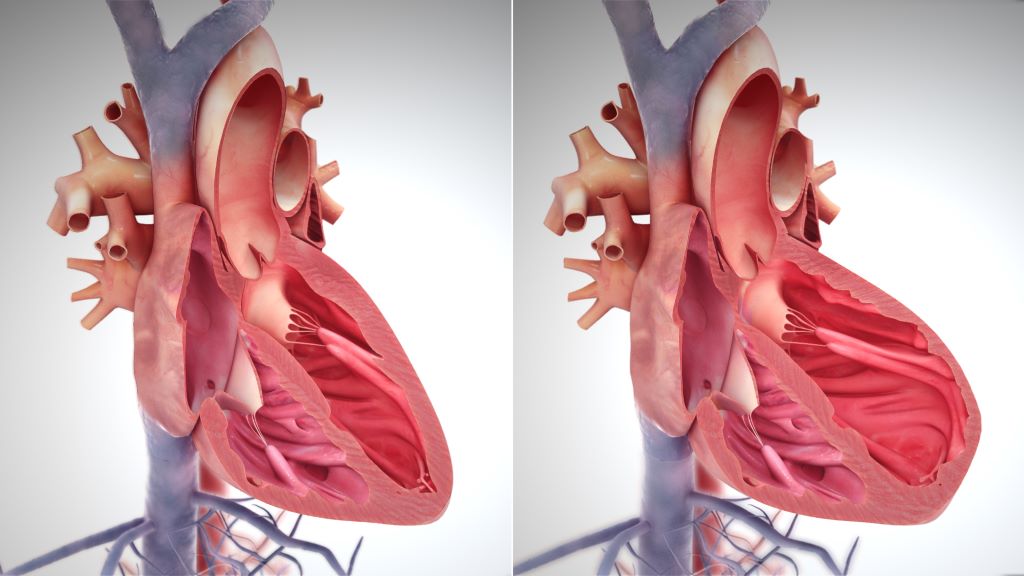
Side by side comparison of heart muscle cells with and without treatment. Damage to the cells is shown in blue. On the left, tissue has been injected with saline and the damaged area is considerably larger. On the right, the issue was treated with the PLP platform and the damaged area is significantly smaller.

The therapy could have broader applications, said Nathan Gianneschi, the paper’s other corresponding author and a professor in the Department of Chemistry at Northwestern.

“This therapeutic platform has tremendous potential for several diseases, including everything from macular degeneration to multiple sclerosis and kidney disease,” Gianneschi said.

The platform aims to block the interaction of two key proteins that intervene in the body’s response to stress and inflammation. When the protein Nrf2 is activated, cells resist the degradation brought on by inflammation. But KEAP1 binds with Nrf2 to degrade it in turn. After a heart attack, this process of degradation has to be stopped so that tissues can health better.

The protein-like polymer, or PLP, platform is made from a polymer that mimics Nrf2. Once injected intravenously, it finds KEAP1 and binds to it, preventing it from binding to the actual Nrf2 protein and degrading it.

Researchers injected rat models after a heart attack with either the PLP platform or a saline solution. The team was blinded to which animals received the polymer or saline. After five weeks, the rodents underwent MRIs while sedated. The animals injected with the polymer showed better cardiac function and significantly more healing in their heart muscle tissue. Other tests also showed that genes that promote healing of tissues were expressed more.

Researchers describe the study as a proof of concept. Before moving on to tests in larger mammals, they want to optimize the design and dosage, and conduct further analysis.

“Proteins are the molecular machines that drive all essential cellular function, and dysregulated intracellular protein-protein interactions are the cause of many human diseases,” Gianneschi said. “Existing drug modalities are either unable to penetrate cells or cannot effectively engage these large disease target domains. We are looking at these challenges through a new lens.”

The therapy method was developed by Gianneschi, while he was a faculty member at UC San Diego, where he is now an adjunct faculty. He continued working on the technology at Northwestern.

Source: University of California – San Diego

Statin Use May Improve Survival in Patients for Some Blood Cancers

Photo by Towfiqu Barbhuiya on Unsplash

Patients with chronic lymphocytic leukaemia (CLL) or small lymphocytic lymphoma (SLL) who were taking cholesterol-lowering statin medications at the start of their cancer treatment had a 61% lower risk of dying from their cancer compared to similar patients who were not taking statins, according to a study published today in the journal Blood Advances.

“This is the first systematic evaluation of the association of statin use with survival outcomes in patients with CLL or SLL who have been treated with contemporary targeted agents such as ibrutinib,” said the study’s principal investigator, Ahmad Abuhelwa, PhD, an assistant professor of pharmacy practice and pharmacotherapeutics at the University of Sharjah in the United Arab Emirates. “Our results highlight a strong link between statin use and improved survival in this patient population.”

CLL is a slow-growing cancer that starts in the blood-forming cells of the bone marrow and is the most common form of leukaemia in adults in the United States. SLL, also a slow-growing cancer, affects the same type of cells as CLL but starts in lymphoid tissues such as the spleen instead of in the blood-forming cells.

Statins are among the most widely prescribed medications. It’s estimated that over 90 million adults in the United States take a statin drug to reduce their cholesterol levels and lower their risk for heart disease, which can lead to heart attacks or strokes. Previous studies have linked statin use to reduced death rates from several cancers, including CLL, said Dr Abuhelwa. However, those studies did not evaluate the effects of statin use in patients who were treated with newer cancer therapies such as the targeted drug ibrutinib, he said.

In the current study, Dr Abuhelwa and his colleagues analysed data from 1467 patients with CLL or SLL who participated in four international clinical trials conducted between 2012 and 2019. In these trials, patients were randomly assigned to treatment with ibrutinib either alone or in combination with other anti-cancer drugs, or to a drug regimen that did not include ibrutinib. A total of 424 patients (29%) were taking a statin at the time they started treatment across the four clinical trials. The median patient age was 65, and 66% were men; 92% had CLL, which was either newly diagnosed, had come back, or had not responded to prior treatment.

The study’s primary endpoints were cancer-specific survival (how long patients lived after starting treatment before dying specifically from their cancer), overall survival (how long patients lived after starting treatment, regardless of the cause of death), and progression-free survival (how long patients lived after starting treatment before their cancer worsened or they died from any cause). The secondary endpoint was the proportion of patients who experienced severe or life-threatening adverse events. The median follow-up time for all patients enrolled in the four trials was five years for overall survival and 22 months for progression-free survival.

To account for potential confounding factors, the investigators adjusted their analysis for variables including each patient’s diagnosis, age, sex, weight, physical functioning (as assessed by doctors), disease severity, length of time since their diagnosis, number of co-existing illnesses, use of other medications for heart conditions or high blood pressure, and the specific anti-cancer treatment regimen received.

Results showed that, regardless of any of these factors, patients who took a statin had, on average, a 61% reduced risk of dying from their cancer, a 38% reduced risk of death from any cause, and a 26% reduced risk of disease progression. Importantly, statin use did not increase the likelihood of severe or life-threatening adverse events.

“These findings don’t allow us to say for certain that statins directly improve cancer outcomes,” said Dr. Abuhelwa. “However, the fact that this association remained strong even after accounting for multiple factors makes it an important area for future research.” As next steps, he recommended conducting laboratory studies to better understand how statins may influence cancer biology, as well as prospective clinical trials in which patients with CLL or SLL are randomly assigned to take a statin or not.

The study has several limitations given its observational nature. For example, patients enrolled in clinical trials tend to be monitored more closely than those who receive treatment outside of a clinical trial, so the study findings may not be generalizable to patients treated in non-clinical trial settings. Additionally, because patients used various statins at different doses, the study could not determine the effects of specific statin types, doses, or duration of use on patients’ survival.

“While our results are very promising, we can’t recommend starting statins for CLL/SLL treatment based on this study alone,” Dr Abuhelwa said. “Future clinical trials are needed to determine definitively whether statins have a direct benefit on cancer survival.”

Source: American Society of Hematology

Urinary Incontinence may Be Associated with Cardiovascular Disease

Photo by Jan Antonin Kolar on Unsplash

A University of Iowa-led research team has found that urinary incontinence may be associated with a greater risk for cardiovascular disease in women.

Urinary incontinence is a common condition, especially in older adults. Previous studies have stated that it can affect between 38% and 60% of women. The researchers aimed to find out whether urinary incontinence was linked to a decline in physical activity, which can lead to a host of health issues, including greater risk for cardiovascular disease.

The findings were published in Preventive Medicine.

In the study, the researchers – led by Lisa VanWiel, assistant professor at the University of Wisconsin-La Crosse who in April earned her doctorate in health and human physiology from Iowa – analysed medical records over two years from more than 20 000 female patients in the Hartford Healthcare system in Connecticut. Of those patients, 5.4% reported through a questionnaire to have urinary incontinence. All patients were asked to rate their level of physical activity in the questionnaire.

The researchers found that the respondents with urinary incontinence did not report engaging in less physical activity than those who did not have the condition. But the team did find an association between patients with urinary incontinence and cardiovascular disease risk factors or events, such as dyslipidemia, type 2 diabetes, and stroke.

“There is an association between incontinence and cardiovascular disease (CVD) risk,” the study authors write. “Women should be screened for incontinence regularly as it may contribute to CVD risk, and women with CVD risk factors should be screened for undiagnosed incontinence.” 

Source: University of Iowa

Preventing Onset and Development of Heart Failure with Preserved Ejection Fraction

Right side heart failure. Credit: Scientific Animations CC4.0

There is a natural mechanism that protects the heart from heart failure with preserved ejection fraction (HFpEF), according to findings published in Circulation. An international team of researchers at the University of Manchester, Baylor College of Medicine and collaborating institutions discovered that when the cardioprotective mechanism fails, it promotes the development of HFpEF. Restoring the mechanism prevents progression, and presents a promising therapeutic target to prevent and treat this life-threatening disease.

“HFpEF is a complex, multifactorial disease associated with metabolic stress. One of the factors involved is the toxic accumulation of lipids in heart cells,” said co-author Dr Tamer M. A. Mohamed, associate professor of surgery and director of the Laboratory for Cardiac Regeneration Baylor.

The team began by assessing gene changes in hearts from people diagnosed with metabolic stress along with various cardiovascular complications and found alterations in the expression of 488 genes. “We found particularly relevant the simultaneous reduction of the expression of genes XBP1 and EDEM2 in human HFpEF hearts,” Mohamed said.

The link between EDEM2 and other conditions has been studied, but its role in the heart remains unexplored.

“We discovered that the XBP1 protein regulates the Edem2 gene in animal models and that EDEM2 was downregulated in hearts from individuals with metabolic disorders and in mouse models,” Mohamed said. “Further evidence supported the involvement of EDEM2 and XBP1 in cardiovascular diseases and lipid regulation.”

To investigate whether XBP1 and EDEM2 were directly involved in lipid toxicity and HFpEF, the researchers removed the Xbp1 or the Edem2 gene in mice. Consequently, these mice became more vulnerable to metabolic stress-induced heart lipid toxicity and cardiac dysfunction. “It was exciting to see that restoring Xbp1 or Edem2 alleviated lipid overload in the heart and reversed HFpEF,” Mohamed said.

This comprehensive study uncovered that XBP1 and EDEM2 work together to maintain a healthy lipid balance in heart cells.

“Our findings support further study of the XBP1s and EDEM2 pathway as a promising therapeutic target for mitigating cardiac lipotoxicity and progression of HFpEF,” Mohamed said.

Source: Baylor College of Medicine

Daytime-only Meals Could Protect People from the Heart Risks of Shift Work

Photo by Malvestida on Unsplash

A new study from Mass General Brigham suggests that eating only during the daytime could help people avoid the health risks associated with shift work. Results are published in Nature Communications.

“Our prior research has shown that circadian misalignment – the mistiming of our behavioral cycle relative to our internal body clock – increases cardiovascular risk factors,” said senior author Frank A.J.L. Scheer, PhD, a professor of Medicine at Brigham and Women’s Hospital. “We wanted to understand what can be done to lower this risk, and our new research suggests food timing could be that target.”

Animal studies have shown that aligning food timing with the internal body clock could mitigate the health risks of staying awake during the typical rest time, which prompted Scheer and his colleagues to test this concept in humans.

For the study, researchers enlisted 20 healthy young participants to a two-week in-patient study at the Brigham and Women’s Center for Clinical Investigation. They had no access to windows, watches, or electronics that would clue their body clocks into the time. The effect of circadian misalignment could be determined by comparing how their body functions changed from before to after simulated night work.

Study participants followed a “constant routine protocol,” a controlled laboratory setup that can tease apart the effects of circadian rhythms from those of the environment and behaviours (eg, sleep/wake, light/dark patterns). During this protocol, participants stayed awake for 32 hours in a dimly lit environment, maintaining constant body posture and eating identical snacks every hour. After that, they participated in simulated night work and were assigned to either eating during the nighttime (as most night workers do) or only during the daytime. Finally, participants followed another constant routine protocol to test the aftereffects of the simulated night work. Importantly, both groups had an identical schedule of naps, and, thus, any differences between the groups were not due to differences in sleep schedule.

The investigators examined the aftereffects of the food timing on participants’ cardiovascular risk factors and how these changed after the simulated night work. Researchers measured various cardiovascular risk factors, including autonomic nervous system markers, plasminogen activator inhibitor-1 (which increases the risk of blood clots), and blood pressure.

Remarkably, these cardiovascular risk factors increased after simulated night work compared to the baseline in the participants who were scheduled to eat during the day and night. However, the risk factors stayed the same in the study participants who only ate during the daytime, even though how much and what they ate was not different between the groups—only when they ate.

Limitations of the study include that the sample size was small, although of a typical size for such highly controlled and intensive randomised controlled trials. Moreover, because the study lasted two weeks, it may not reflect the chronic risks of nighttime versus daytime eating.

A strength is that the study participants’ sleep, eating, light exposure, body posture, and activity schedule were so tightly controlled.

“Our study controlled for every factor that you could imagine that could affect the results, so we can say that it’s the food timing effect that is driving these changes in the cardiovascular risk factors,” said Sarah Chellappa, MD, MPH, PhD, an associate professor at the University of Southampton, and lead author for the paper.

While further research is necessary to show the long-term health effects of daytime versus nighttime eating, Scheer and Chellappa said the results are “promising” and suggest that people could improve their health by adjusting food timing. They add that avoiding or limiting eating during nighttime hours may benefit night workers, those who experience insomnia or sleep-wake disorders, individuals with variable sleep/wake cycles, and people who travel frequently across time zones.

Source: Mass General Brigham

Add-on for Statins Greatly Reduces Recurrence of Heart Attacks

Photo by Mikhail Nilov: https://www.pexels.com/photo/paramedics-using-a-defibrillator-on-a-patient-8942635/

Patients who receive an add-on medication soon after a heart attack have a significantly better prognosis than those who receive it later, or not at all. These are the findings of a new study from researchers at Lund University in Sweden and Imperial College London.

Their analysis suggests that treating patients earlier with a combination of statins and the cholesterol-lowering drug ezetimibe could prevent thousands of new heart attacks in the UK over a decade.

Cardiovascular disease is by far the most common cause of death worldwide, with heart attack (‘myocardial infarction’) being the most common acute event.

For those who survive a heart attack, the risk of a new heart attack is greatest in the first year after the initial event because the blood vessels are more sensitive, making it easier for blood clots to develop.

Our findings suggest that a simple change in treatment guidelines could have a huge impact on patients and reduce the demand on the NHS.

Professor Kausik Ray, School of Public Health

Reducing LDL or “bad” cholesterol in the blood can stabilise changes in the vessels, decreasing the risk for new events.

The current treatment guidelines for patients are high-potency statins immediately after a heart attack, to lower their cholesterol levels.

However, the majority of patients do not reach recommended cholesterol levels using only statins, and so need an add-on treatment, such as ezetimibe.

“Today’s guidelines recommend stepwise addition of lipid-lowering treatment. But it’s often the case that this escalation takes too long, it’s ineffective and patients are lost to follow-up,” says Margrét Leósdóttir, Associate Professor at Lund University and senior cardiology consultant at Skåne University Hospital in Malmö, Sweden. “By giving patients a combination treatment earlier, we could help to prevent many more heart attacks.”

Co-investigator Professor Kausik Ray, from Imperial College London’s School of Public Health, said: “This study shows that we could save lives and reduce further heart attacks by giving patients a combination of two low-cost drugs.

“But at the moment patients across the world aren’t receiving these drugs together. That’s causing unnecessary and avoidable heart attacks and deaths – and also places unnecessary costs on healthcare systems.

“Our study shows the way forward; care pathways must now change for patients after this type of heart event.”

Reducing heart attacks

In the latest study, the international team examined outcomes for heart attack patients if they received a combination of statins with the add-on therapy ezetimibe (within 12 weeks after a heart attack), statins with ezetimibe added later (between 13 weeks and 16 months), or just statins with no ezetimibe at all.

Based on Swedish registry data from 36 000 patients who had a heart attack between 2015 and 2022, the researchers used advanced statistical models to emulate a clinical trial.

The results show that patients who received a combination treatment of statins and ezetimibe within 12 weeks of a heart attack and were able to lower cholesterol to the target level early, had a better prognosis and less risk of new cardiovascular events and death than those who received the add-on treatment later, or not at all.

From the analysis, the researchers believe many new heart attacks, strokes and deaths could be prevented every year internationally if the treatment strategy were to be changed.

Under a scenario in which 100% of patients would receive ezetimibe early, they estimate 133 heart attacks could be avoided in a population of 10 000 patients in 3 years.

The researchers suggest that in the UK, which records an estimated 100 000 hospital admissions from heart attacks a year,[1] this would equate to an estimated 5000 heart attacks being prevented over a ten year period.[2]

Improving guidance

Dr Leósdóttir said: “Combination therapy is not applied up-front for two main reasons. General recommendations are not included in today’s guidelines and a precautionary principle is applied to avoid side effects and overmedication.

However, there are positive effects from applying both medicines as soon after the infarction as possible. Not doing this entails an increased risk. In addition, the drug we have examined in the study causes few side effects and is readily available and inexpensive in many countries.”

Margrét Leósdóttir hopes that the research results will in time provide support for changes in the recommendations. A treatment algorithm has already been introduced at her hospital in Sweden to help doctors to prescribe appropriate lipid-lowering treatment for patients who have had a myocardial infarction.

It has been noted that patients achieve their treatment goals earlier and two months after the infarction twice as many patients have reduced their bad cholesterol to the target level, compared with previously.

“Several other hospitals in Sweden have also adopted the algorithm and there are similar examples from other countries that have produced as good results. My hope is that even more will review their procedures, so that more patients will get the right treatment in time, and we can thereby prevent unnecessary suffering and save lives.”

Source: Imperial College London

CVD and Obesity: When Protective Lipids Decline, Health Risks Increase

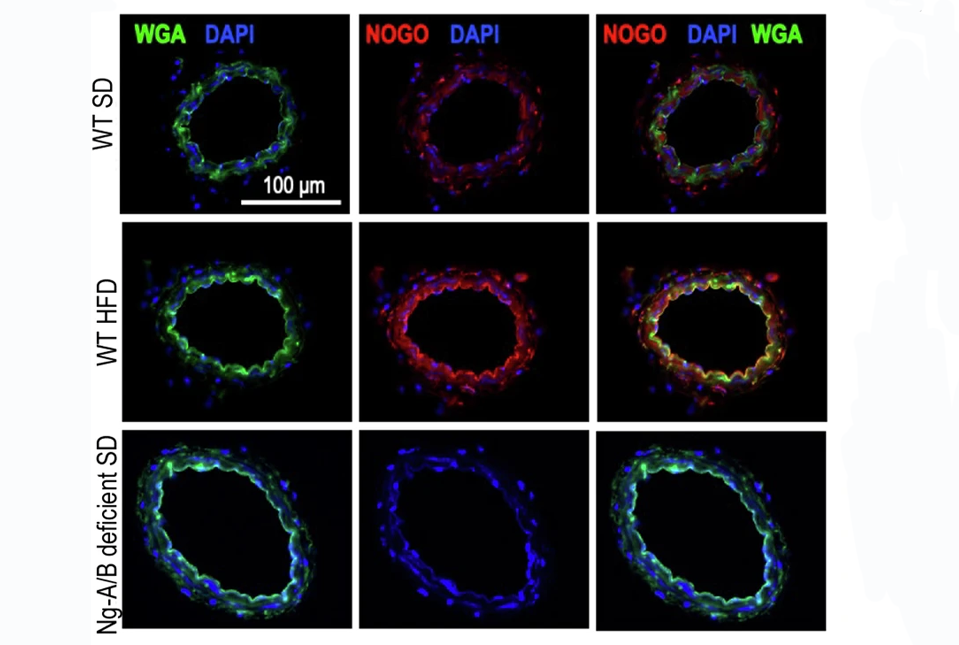
The mesenteric arteries from obese and lean mice, pictured above, supply oxygen and nutrients to the intestines. Immunofluorescence staining revealed that the NOGO-B protein increases in the vascular walls of mice fed a high fat diet compared to mice fed a standard diet. As a result, ceramides decrease in the mesenteric arteries of the obese mice, damaging endothelial cells lining blood vessels. Credit: Annarita Di Lorenzo/Weill Cornell Medicine

New research from Weill Cornell Medicine has uncovered a surprising culprit underlying cardiovascular diseases in obesity and diabetes—not the presence of certain fats, but their suppression. The study, published in Nature Communications, challenges the conventional belief that a type of fat called ceramides accumulates in blood vessels causing inflammation and health risks. Instead, their findings reveal that when ceramides decrease in endothelial cells lining blood vessels, it can be damaging and cause chronic illnesses. Ironically, the findings could ultimately lead to therapies that maintain high levels of these protective lipids in patients with obesity.

Ceramides are found throughout the body and in the endothelium, the thin lining inside blood vessels. These waxy lipids regulate blood vessel tone, dilating or contracting vessels to modulate blood pressure. They also help prevent blood clots, keeping blood flowing easily through the body’s extensive highway of arteries and veins.

“The common assumption in the field was that high levels of ceramides in the endothelium of blood vessels contributed to cardiovascular disease, but this conclusion was extrapolated from in vitro data in cells,” said Dr Annarita Di Lorenzo, professor of pathology and laboratory medicine at Weill Cornell Medicine. “Ours is the first in vivo study that measures the levels of the lipids in the endothelial cells of an animal model. In obese mice fed a high-fat diet, ceramides do not build up—they decrease compared to lean mice.” Also working on this research are co-first authors Dr Onorina L. Manzo, postdoctoral associate and Luisa Rubinelli, both in Dr Di Lorenzo’s lab.

Ceramide to the Rescue

Dr Di Lorenzo and her team discovered the importance of ceramides in blood vessels two years ago. Together with Dr Giuseppe Faraco, assistant professor of neuroscience at Weill Cornell Medicine, they found that decreased levels of ceramides in otherwise healthy mice causes severe blood vessel inflammation in the brain, clot formation and death. Last year, the team reported that ceramide production increases as a protective response in a mouse model of coronary artery disease. Ultimately, when ceramide is broken down by the body it produces a compound called sphingosine-1-phosphate (S1P), which builds up and protects mice against cardiovascular disease. But when this process doesn’t work the mice are left vulnerable.

The researchers also found that two proteins, Nogo-B and ORMDL, decreased the production of ceramides and S1P in obesity. This decrease leads to increased blood pressure, impaired vascular regulation and higher glucose levels—all of which contribute to cardiometabolic conditions that affect the heart (cardiovascular system) and energy processing (metabolism), like diabetes like diabetes, hypertension, coronary artery disease and stroke.

Maintaining Balance

To understand how these different molecules interact, the researchers tested what happens in animal models. Mice with obesity fed a high-fat diet had low levels of ceramides and S1P, but high levels of Nogo-B. These mice showed signs of inflammation, diabetes and high blood pressure.

But what happens if the Nogo-B inhibitor wasn’t present? The researchers knocked out Nogo-B only in the endothelium of blood vessels in a mouse model to find out. “These mice have the same body weight and diabetes as controls, but their blood vessel health is much better,” said Dr. Di Lorenzo. “By knocking out this inhibitor, we preserved vascular health. This also showed that the regulation of ceramide metabolism causes vascular dysfunction and inflammation in obesity.”

The paper suggests that targeting this metabolic pathway could have multiple beneficial effects in the treatment of cardiometabolic diseases related to obesity. “Nogo suppresses biosynthesis of ceramides, so if we can identify a drug that can block Nogo-B, we could restore ceramide levels to a healthy balance and this would fight not only obesity and diabetes, but would directly keep blood vessels functioning properly,” she said.

Source: Weill Cornell Medicine

New Study Investigates Effects of ADHD Medications on the Heart

Photo by Annie Spratt on Unsplash

A new study led by the University of Southampton has found that medications for ADHD have overall small effects on blood pressure and heart rate after weeks or a few months of use.

There have been concerns about the side effects of ADHD medications but the new findings, coupled with other studies, suggest that the benefits of taking these medications outweigh the risks, while highlighting the need for careful monitoring.

The study, published in The Lancet Psychiatry, conducted the largest and most comprehensive analysis of the cardiovascular effects of ADHD medications based on the results of randomised controlled trials – the most rigorous type of clinical study to assess medication effects.

Professor Samuele Cortese, senior lead author of the study from the University of Southampton said: “When it comes to taking any medication, risks and benefits should always be assessed together. We found an overall small increase in blood pressure and pulse for the majority of children taking ADHD medications.

“Other studies show clear benefits in terms of reductions in mortality risk and improvement in academic functions, as well as a small increased risk of hypertension, but not other cardiovascular diseases. Overall, the risk-benefit ratio is reassuring for people taking ADHD medications.”

The study was funded by the National Institute for Health and Care Research (NIHR), within the framework of the NIHR Research Professorships scheme to Professor Samuele Cortese, with Dr Luis Farhat (University of São Paulo, Brazil) as first author and Professor Alexis Revet (University of Toulouse, France) as co-senior author.

It is estimated that attention-deficit/hyperactivity disorder (ADHD) affects around 4 per cent of children in the UK. Of these, around 45 per cent are treated with medication.

The international team of investigators analysed data from 102 randomized controlled trials, including a total of 22,702 participants with ADHD. They used an advanced statistical approach – network meta-analysis – that allowed them to compare the effects of several medications, even when the medications were not directly compared in the trials included in the analysis.

They found that all ADHD medications were generally associated with overall small effects on blood pressure, heart rate, and ECG parameters. With the exception of guanfacine (which leads to decreased blood pressure and heart rate), other medications led to increases in the values of these parameters.

No significant differences were found between stimulants (including methylphenidate and amphetamine) and non-stimulants (atomoxetine and viloxazine) with regard to their effects on blood pressure and heart rate.

“Our findings should inform future clinical guidelines, stressing the need to systematically monitor blood pressure and heart rate, both for stimulants and non-stimulants. This should be particularly relevant for practitioners who might assume that only stimulants have a negative effect on the cardiovascular system,” said Dr Farhat.

The researchers say that those with existing heart conditions should discuss the side effects of ADHD medications with a specialist cardiologist before starting treatment.

Professor Revet added: “Our findings, based on randomised controlled trials that tend to be of short duration due to ethical issues, should be complemented by results from real-world, longer-term studies.”

The research team will now look to see if some groups might be more vulnerable to cardiovascular side effects than others.

NIHR Research Professor Cortese concluded: “While our findings are informative at the group level, that is, on average, we cannot exclude that a subgroup of individuals may have a higher risk of more substantial cardiovascular alterations.

“While it is currently not possible to identify those individuals at higher risk, efforts based on precision medicine approaches will hopefully provide important insights in the future.”

Source: University of Southampton