

Category: Cancer

Most Glucose Consumption in Non-cancer Cells, Upending Century-old View

A study has found that cancer cells are not the main consumers of glucose in tumours, challenging an observation held for over a century.

“The field of cancer metabolism has really exploded over the last 20 years, but it has been based on this observation that Otto Warburg published in 1922—that cancer cells can consume glucose at a very high rate,” said Jeffrey Rathmell, PhD, Cornelius Vanderbilt Professor of Immunobiology and director of the Vanderbilt Center for Immunobiology. “We now know that tumors include many types of cells, and it’s surprising that non-cancer cells are actually the major glucose consumers in the tumor.”

One application of the Warburg effect is where cancer cells are picked out based on their glucose metabolism in positron emission tomography (PET), a radioactive tracer of glucose (FDG). However, this doesn’t always yield the results expected by clinicians.

“I had been curious about why PET scans are ‘hot’ or ‘not hot’ for many years because the kidney cancer type that I study, from what we understand about the biology, should light up hot on PET and often doesn’t,” said W. Kimryn Rathmell, MD, PhD, Hugh J Morgan Professor and Chair of the Department of Medicine. “Jeff and I have had many conversations about which cells are using the glucose: is it the cancer cells; is it the immune cells; how does it all fit together? You can just imagine our dinner table.”

A pair of MD-PhD students from their labs, Bradley Reinfeld and Matthew Madden, decided to resolve this conundrum. They administered two different PET tracers (one for glucose, one for glutamine) to mice with tumours, isolated the tumors and separated them into various cell types and then measure the radioactivity in the cells. Six different tumour models were used, including colorectal, kidney and breast cancer. The results showed that, in each case, myeloid immune cells (primarily macrophages) had the highest uptake of glucose, followed by T cells and cancer cells. Cancer cells, in contrast, had the highest glutamine uptake.

“We think this is a general phenomenon that extends across cancer types,” Madden said.

The researchers showed that, instead of limiting nutrients, certain cellular signaling pathways drove the differences in glucose and glutamine uptake. The prevailing view is rather of metabolic competition taking place in the tumour microenvironment, where the cancer cells “win” to deplete nutrients and suppress immune cells.

“The idea has been that the cancer cells are gobbling up all of the glucose, and consequently, immune cells can’t get enough glucose and can’t do their job,” Madden said. “Our data suggest that nutrients aren’t limiting. Instead, cells are programmed to consume certain nutrients, and there is partitioning of nutrients between cells: cancer cells pick up glutamine and fatty acids; immune cells pick up glucose.”

Knowing that cells in the tumour microenvironment use different nutrients “may allow for specifically targeting particular cell types—for new therapies or for imaging people’s tumors,” Reinfeld said.

Kimryn Rathmell added, “We’re in a good place now to be able to have more sophisticated PET radiotracers. It’s time to think about testing fluoridated glutamine or other nutrient probes in patients.”

The study’s findings also have implications for interpreting FDG-PET imaging results, she said. “We order FDG-PET scans all the time, and we need to have a good sense of what that information is providing us. We use it to judge tumor response, but it may be telling us about inflammatory response and not tumor response.”

Source: Medical Xpress

Journal information: Cell-programmed nutrient partitioning in the tumour microenvironment, Nature (2021). DOI: 10.1038/s41586-021-03442-1
A Cellular Communication Network Allows Tumour Regrowth

Scientists at the University of Missouri and Yale University have discovered that one of the mutations in the RAS family of genes, which impede treatment options, is also responsible for allowing tumour regrowth following genotoxic therapy.

Genotoxic therapies cause DNA damage inside cancer cells in order to destroy them . To avoid being eliminated, cells will stop replicating and try to repair the damage, but if they fail to do so, they will trigger cell death, relying on a protein called “p53”.  

While RAS gene mutations have been studied for over three decades, scientists today have a better understanding of how they work. However, many of them still consider these mutations to be “undruggable” or resistant to therapeutic treatment, according to the National Cancer Institute.

“Most of our knowledge of how cells respond to DNA damage is mainly derived from studies looking at the single cell level,” said Yves Chabu, an assistant professor in the MU College of Arts and Science. “Therefore, we don’t know much about how tumour cells respond to DNA damage in the broader context of the tissue level, and what possible implications these responses might have on a tumor’s relapse following genotoxic therapies. To address this, we looked at how tissues containing patches of cells carrying oncogenic RAS mutations respond to DNA damage. We focused on oncogenic RAS because it is associated with cancers relapse and resistance to genotoxic therapies in humans. This approach has allowed us to identify novel cell-to-cell communication within the tissue that instructs tumour cells in tissues to regrow. It’s something we would not have identified if we were only looking at the single cell level.”

“We found that in oncogenic RAS tissues, cells elevate the levels of the p53 protein to varying degrees in response to DNA damage,” said Prof Chabu, whose appointment is in the Division of Biological Sciences. “Further analyses revealed that cells with high p53 protein levels, or more extensive DNA damage, do not simply die in response to the DNA damage. Instead, they release a growth signal called interlukin-6 into the tumor environment. Interlinkin-6 instructs cells with low p53 levels, or cells with less DNA damage, to activate JAK/STAT, a growth-amplifying signal, and drive tumor regrowth after treatment. We essentially have a situation where cells that are vulnerable to the treatment are instructing the more robust cells to take over and grow.”

Prof Chabu, who has been studying oncogenic RAS mutations for more than a decade, said that this further suggests that adding JAK/STAT inhibitors to genotoxic therapies inhibit the regrowth ability of RAS tumours. He said another interesting aspect of their findings is that p53 is traditionally considered as a tumour suppressor protein.

“A loss of p53 activity, due to genetic mutation, causes cells to grow uncontrollably while accumulating even more DNA mutations,” said Prof Chabu. “So, naturally one would think that having more p53 activity is a good thing because it prevents pre-cancerous cells from growing and forming cancers. Yet, here we find that too much of a normal, not mutated, p53 can signal the surrounding RAS tissues to overgrow.”

Source: Medical Xpress

Journal information: Yong-Li Dong et al, Cooperation between oncogenic Ras and wild-type p53 stimulates STAT non-cell autonomously to promote tumor radioresistance, Communications Biology (2021). DOI: 10.1038/s42003-021-01898-5

Antihypertensive Drugs Not Linked to Cancer Risk

A review of 33 clinical studies  showed that antihypertensive drugs did not have a consistent association with cancer risk.

Patients treated with any of five different classes of antihypertensive drugs had essentially the same cancer risk as those receiving placebo. Comparisons of each antihypertensive class against all the others showed no association with an increased risk of cancer, save for calcium channel blockers (CCBs), which had only a modestly higher risk versus the other drug classes (HR 1.06, 95% CI 1.01-1.11).

The data do not conclude the issue, since some comparisons had insufficient data to exclude the possibility of excess cancer risk, reported Kazem Rahimi, DM, of the University of Oxford in England, and colleagues in Lancet Oncology.

“Our study has addressed an ongoing controversy about the safety of blood pressure-lowering medication with respect to cancer risk, using the largest sample of individual-level randomized evidence on blood pressure-lowering treatment to date, to our knowledge,” they wrote. “The main implication of our study is that patients using antihypertensive medication should continue to take their medications because concerns about increased cancer risk seem to be unfounded.”

The author of an accompanying commentary noted that the findings could have been due to chance. The number of trials per drug class varied greatly, and small sample sizes were used in analyses by type of cancer.

“Taken together, these limitations raise a more fundamental question about how the findings of randomised controlled trials should be interpreted,” wrote Laurent Azoulay, PhD, of McGill University in Montreal.

Randomised trials are the “gold standard” for assessing drug efficacy, but are not typically designed to assess safety, he continued. This is especially important for outcomes like cancer, which have a delayed onset. Since the median follow-up was only 4.2 years , “a potential association between cancer and the long-term use of antihypertensive drugs cannot be ruled out.”

“Such analyses are necessary to understand the short-term effects of these drugs on cancer incidence,” Azoulay concluded. “However, moving forward, these studies will need to be complemented with well-designed, real-world studies in heterogeneous patient populations who are followed up for extended periods of time to fully understand their carcinogenic potential.”

Several meta-analyses have yielded conflicting evidence, Rahimi and colleagues stated. The Blood Pressure Lowering Treatment Trialists’ Collaboration (BPLTTC) is the world’s largest individual patient-level data on blood pressure-lowering trials, and data from this formed the basis for the meta-analysis.

The authors identified 33 trials for inclusion in the meta-analysis, which comprised 260 447 patients with available data on cancer outcomes. CCBs were the antihypertensive class most commonly represented in the trials (n=19), followed by ACE inhibitors (15), angiotensin-receptor blockers (ARBs, 11), thiazide diuretics (six), and beta-blockers (five). Median follow-up ranged from 4 to 5 years across the trials, grouped by drug class.

Patient age ranged between 64 and 68 by drug class, and pretreatment systolic blood pressure ranged from 147mm Hg (ACE inhibitors) to 166mm Hg (beta-blockers).

Across the five classes of antihypertensive drugs, individual comparisons for cancer risk versus the other drug classes yielded only a maximum hazard ratio of 1.06 for CCBs.

“We found no consistent evidence that antihypertensive medication use had any effect on cancer risk,” the authors stated.

Source: MedPage Today

Journal information 1: Copland E, et al “Antihypertensive treatment and risk of cancer: An individual participant data meta-analysis” Lancet Oncol 2021; DOI: 10.1016/S1470-2045(21)00033-4.

Journal information 2: Azoulay L “Elucidating the association between antihypertensive drugs and cancer: A need for real-world studies” Lancet Oncol 2021; DOI: 10.1016/S1470-2045(21)00085-1.

Blood Mutation Explains High Leukaemia Rates in Children with Down’s

According to a new study by researchers at the Linda Crnic Institute for Down Syndrome, the reason that children with Down syndrome have a drastically elevated risk of leukaemia is due to a more prevalent condition increasing blood stem cell mutation.

Children with Down syndrome are 20-times more likely to develop acute lymphocytic leukaemia (ALL) and 150-times more likely to develop acute myeloid leukaemia (AML) compared to their typical peers. The researchers found that the reason for this is that they are more likely to present with clonal haematopoiesis (CH), a process in which a blood stem cell acquires a genetic mutation that promotes replication.  

The findings add to a growing body of evidence linking immune dysregulation to a very different disease spectrum, whereby people with Down syndrome are highly predisposed to certain diseases such as leukaemia and autoimmune disorders, while being highly protected from others, such as solid tumours.

“We found a higher-than expected rate of CH in individuals with Down syndrome between the age of one to 20 years old,” said study author Dr Alexander Liggett, who as a doctoral candidate led the study in the lab of Dr James DeGregori, Professor of Biochemistry and Molecular Genetics. “It is a surprising finding, as the phenomenon is typically only observed in elderly people.”

The researchers used an advanced sequencing technique that they had developed, called FERMI, to blood samples from the Crnic Institute Human Trisome Project Biobank. Mutations were more likely to be detected in Down’s syndrome and also more likely to be oncogenic. In elderly people, oncogenic mutations are commonly found in the genes DNMT3A, TET2, ASXL1, TP53, and JAK2. In people with Down’s syndrome, oncogenic CH was found to be dominated by mutations of the TET2 gene.

“Given the increased risk of leukaemia that accompanies clonal expansion of blood cells carrying oncogenic mutations, these expansions may become an important biomarker of cancer risk in the future,” said Dr Liggett.

The study also found that CH in Down syndrome is associated with immune dysregulation biosignatures linked to diseases co-occurring with Down’s syndrome, including thyroiditis, Alzheimer’s disease, and leukaemia. This discovery opens new avenues in understanding the way CH impacts an array of health outcomes in Down syndrome and how to potentially counteract its effects.

“This is truly transformative. This team has identified a new trait of Down syndrome that has strong implications for understanding the appearance of comorbidities more common in this population, such as leukaemia and premature ageing,” said Dr. Joaquin Espinosa, Executive Director of the Crnic Institute. “The next step is to define the long-term impacts of this precocious clonal hematopoiesis and how to prevent its harmful effects.”

Source: News-Medical.Net

Journal information: Liggett, L.A., et al. (2021) Precocious clonal hematopoiesis in Down syndrome is accompanied by immune dysregulation. Gut. doi.org/10.1182/bloodadvances.2020003858.

The Effect of Hypoxia on Cancer Cells is a Matter of Timing

A new study from the University of Colorado School of Medicine shows that the effect of hypoxia on cancer cells varies in the short term versus the long term, opening new possibilities for cancer treatment.

How cancer cells adapt to hypoxia, where insufficient oxygen reaches cells, is a key aspect of cancer biology.

“Most tumours cannot grow unless they figure out a way to induce formation of new blood vessels to supply them with oxygen and other nutrients,” explained Matthew Galbraith, PhD. “So, what happens inside of solid tumours is they undergo intermittent periods of low oxygen between rounds of new blood vessel formation.”

Previous research focussed on hypoxia in the long term, characterising it as oncogenic, or cancer promoting. However some studies showed that hypoxia-sensing factors, known as hypoxia inducible factors, or HIFs, can in some situations suppress tumour growth. To solve this, senior researcher Joaquin Espinosa, PhD and colleagues studied the immediate acute response to hypoxia.

“We employed a cutting-edge genomics technology that nobody had employed in this field before that allowed us to see what happens to cancer cells within minutes of depriving them of oxygen,” Dr Espinosa said.

Employing this technology, they identified hundreds of hypoxia-inducible genes activated shortly upon oxygen deprivation. Using computational biology approaches on large, publicly available datasets, they inferred the function of these genes on hundreds of lab-grown cancer cell lines and hundreds of tumour samples from cancer patients.

They found that when a cell is hypoxic, it reacts by ceasing growth to preserve its existing nutrients and oxygen. Thus, hypoxia causes a tumour-suppressive reaction at this point, mostly by preventing protein synthesis. Only after prolonged periods of hypoxia do cells metastasise and spread out in search of oxygen.

“There’s been a lot of debate about whether these hypoxia-inducible factors promote tumour growth or prevent tumour growth,” Dr Espinosa said. “The conclusion we came to is that everyone was right to a degree. Hypoxia-inducible factors can suppress tumour growth by preventing protein synthesis early on, but they can also advance tumour growth at later stages by promoting the ability of cancer cells to invade neighboring tissues. It depends on when you’re looking at it.”

The tumour suppression and promotion mechanisms elicited by HIFs can be exploited as drug targets. Tumour suppression is mediated by inhibition of an enzyme known as mTOR, which in turn can be inhibited by available drugs often used in cancer therapies. “mTOR inhibitors could mimic the tumour suppressive effects of HIFs,” Dr Galbraith explained.

When deprived of oxygen for a longer amount of time, the HIFs switch on a set of enzymes that can degrade the extracellular matrix that holds them in place, allowing the cancer cells to escape the oxygen-deprived tumour. The cancer cells can then enter the bloodstream and invade nearby tissues.

“These results emphasise the importance of developing inhibitors of hypoxia-inducible enzymes that degrade collagen and other components of the extracellular matrix,” Espinosa said.

Dr Espinosa and his team hope that their research will help new cancer treatments to be developed, which also target the cancer at the right times. 

“People have been trying to target the hypoxia-inducible factors with different therapeutics, but this research would suggest that you may want to exercise some caution about when you apply those therapeutics, given that the HIFs can be tumour suppressive in the early stages of hypoxia,” Dr Galbraith said.

“Since the hypoxic response can be tumour suppressive in some contexts and oncogenic in other contexts, it’s not a good idea to issue a blanket statement that we should always try to shut it down,” Dr Espinosa added. “Instead, we should be thinking about what aspect of the hypoxic response to target, and that’s the aspect where hypoxia drives invasion and metastasis.”

Hoping that other researchers would make use of the map his team developed, Dr Espinosa said, “I would say this is a definitive improvement in the mapping of the early events of hypoxia. And the beauty of that is that once you have a good map of the land, a lot of people can use it.”

Source:  Medical Xpress

Journal information: Zdenek Andrysik et al, Multi-omics analysis reveals contextual tumor suppressive and oncogenic gene modules within the acute hypoxic response, Nature Communications (2021). DOI: 10.1038/s41467-021-21687-2

Duo of Existing Drugs Punishes Ravenous Cancer Cells

Preclinical research from VCU Massey Cancer Center published recently in the Proceedings of the National Academy of Sciences shows that the combination of two existing drugs can kill aggressive neuroblastoma cancer cells by exploiting their metabolic ‘hunger’.

A cancer of the nervous system, neuroblastomas are one of the deadliest childhood cancers, and if the MYCN gene is overexpressed, the prognosis is even worse. Although paediatric blood cancers are more treatable thanks to medical advancements, it has been much harder to treat neuroblastomas mostly due to the difficulty of targeting MYCN.

“MYCN is a transcription factor, and it’s very difficult to drug transcription factors,” said study senior author Anthony Faber, PhD, co-leader of the Developmental Therapeutics research programme and Natalie N and John R.Congdon, Sr. Endowed Chair of Cancer Research at VCU Massey Cancer Center and associate professor in the Philips Institute for Oral Health Research at the VCU School of Dentistry. “So, the next best thing is to target what MYCN does in the cell. One thing it does is to crank up metabolic activity – what it’s doing to keep the cell alive – and we can work that against itself.”

Since these ravenous cells burn cellular energy stores as quickly as they can be replenished Prof Faber’s team looked for a method to kick their metabolism over the edge without harming normal cells.

Screening 20 metabolic drug combinations in cancer cells originating from nearly 1000 different patients, the researchers found that neuroblastoma with high MYCN expression was particularly sensitive to a cocktail containing two drugs: phenformin and AZD3965..

Phenformin was developed in 1957 to treat diabetes. It blocks complex I on the surface of mitochondria, the organelle where energy production occurs.

Although phenformin was taken off the US market in the 1970s after a number of deaths, it’s still in use elsewhere in the world and is finding new application in the US as a cancer drug. Right now, phenformin is being tested in phase I clinical trial for melanoma.

Meanwhile, AZD3965 is a much newer type of drug under phase I clinical investigation. It works by blocking MCT1 rectors on the surface of cells, in this case as a cancer treatment. MCT1 receptors ferry lactate, another energy source, out of the cell. Blocking MCT1 causes lactate to accumulate, causing the cell to stop using it to make energy.

Simultaneously targeting energy production with the two different pathways used by the drugs should result in disruption of the cellular power supply, stressing and finally killing the cells.

This idea was put to the test by using mice seeded with MYCN-amplified neuroblastoma patient cells. Greater tumour reduction was seen from the cocktail than either drug given alone, with the cocktail being well tolerated.

“The data we got with AZD3965 in combination with phenformin might get people to reconsider phenformin,” said study lead author Krista Dalton, MEng, PhD Student, Virginia Commonwealth University Philips Institute for Oral Health Research. “In combination, where we can use lower doses, phenformin might have better tolerability than it previously did on its own.”

Source: News-Medical.Net

Journal information: Dalton, K. M., et al. (2021) Catastrophic ATP loss underlies a metabolic combination therapy tailored for MYCN-amplified neuroblastoma. Proceedings of the National Academy of Sciences. doi.org/10.1073/pnas.2009620118.

Insights into How CAR T Cancer Treatment Works

Researchers have uncovered why some patients respond strongly to chimeric antigen receptor T-cell therapy (CAR T), 

CAR T is a new development in cancer therapy, a treatment approved to treat many types of aggressive B cell leukaemias and lymphomas. Moffitt Cancer Center researchers use mathematical modeling to help explain why CAR T cells work in some patients and not in others, with the response instead tapering off and the disease continuing its progression.

CAR T is a type of personalised immunotherapy that uses a patient’s own T cells to target cancer cells. Many patients have strong responses to CAR T; however, some have only a short response and develop disease progression quickly. The procedure involves T cells from a patient being genetically modified to include a specific receptor targeting cancer cells. 

hemotherapy then lowers some of the patient’s existing normal immune cells to help deal with the influx of CAR T cells that are infused back into the patient, where they can get to work and attack the tumour.

“Treatment success critically depends on the ability of the CAR T cells to multiply in the patient, and this is directly dependent upon the effectiveness of lymphodepletion that reduces the normal T cells before CAR T infusion,” explained co-lead author Frederick Locke, MD, Vice Chair, Blood and Marrow Transplant and Cellular Immunotherapy Department, Moffitt.

In their model, the researchers discovered that tumour eradication is effectively random, but can happen with high probability. The researchers showed that differences in the timing and probability of cures are determined largely by variability among patient and disease factors. The model confirmed that cures tends to happen 20 to 80 days before the CAR T cells decline, while disease tends to progress over a wider time range between 200 to 500 days after treatment.

“Our model confirms the hypothesis that sufficient lymphodepletion is an important factor in determining durable response. Improving the adaptation of CAR T cells to expand more and survive longer in vivo could result in increased likelihood and duration of response,” explained lead author Philipp Altrock, PhD, and assistant member of the Integrated Mathematical Oncology Department at Moffitt.

Source: News-Medical.Net

Journal information: Kimmel, G.J., et al. (2021) The roles of T cell competition and stochastic extinction events in chimeric antigen receptor T cell therapy. Proceedings of the Royal Society B: Biological Sciences. doi.org/10.1098/rspb.2021.0229.

Despite COVID, Cancer Screenings in the US Picked Up

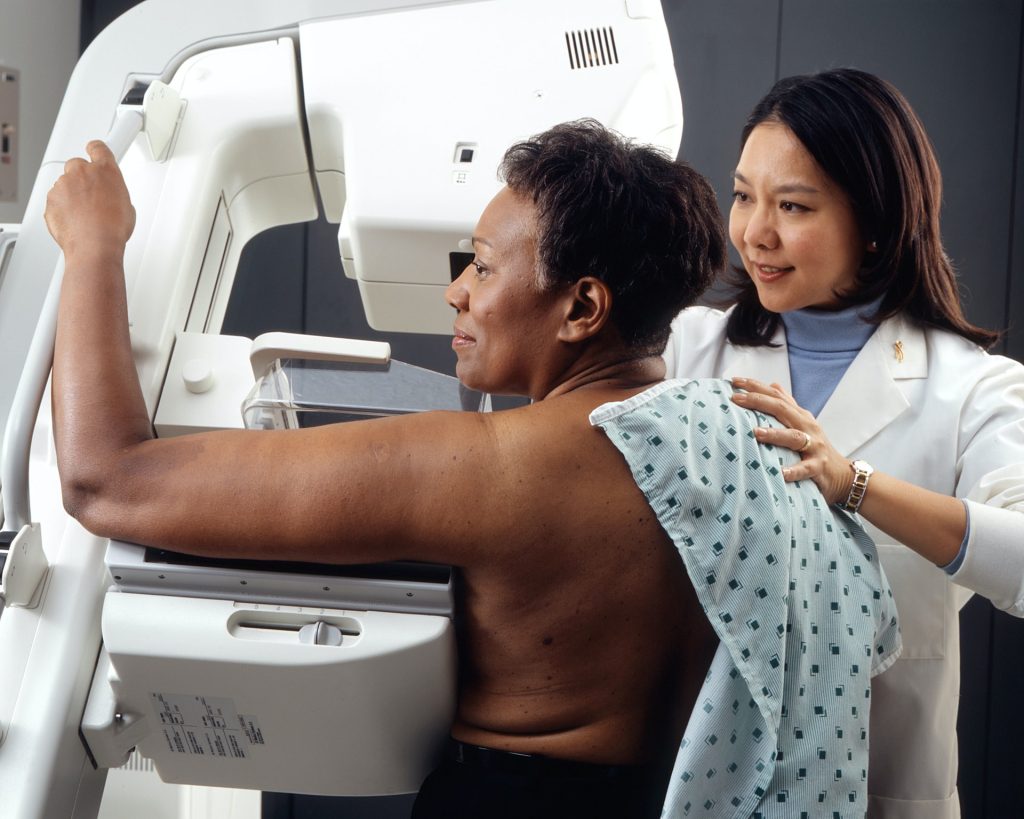
Woman Receives Mammogram. An Asian female technician positions an African-American woman at an imaging machine to receive a mammogram. Creator: Rhoda Baer

In an encouraging sign, the RAND corporation reports that despite COVID, cancer screenings in the United States rebounded in the wake of the first wave.

There has been concern since the COVID pandemic was keeping people from going in for routine cancer screening, resulting in more undetected cancers to progress unchecked and an increase in cancer deaths. As some 600 000 Americans were expected to die of cancer in 2020, any impact on screening is a considerable health concern.

In a statement, Ryan McBain, PhD, of the RAND Corp. in Santa Monica, California, said: “These are the first findings to show that, despite real fears about the consequences of drop off in cancer screens, health facilities figured out how to pick this back up after the initial pandemic restrictions. Our study shows that health systems were able to recalibrate resources and protocols in a relatively short interval to deliver these important services.”

In Spain, cancer diagnoses were down 38% in the first half of 2020, according to one study. The pandemic’s impact on cancer screening that required in-person examinations, such as mammography and colonoscopy, were a particular concern, McBain and co-authors noted. Moreover, little was known about the magnitude of the decline in screening rates or longer-term trends in screen.

Using data on Castlight Health beneficiaries from January 15 to July 31, 2020, the researchers calculated weekly screening rates per 10 000 eligible beneficiaries. Before the declaration of national emergency in the US on March 13, screening mammography weekly rate was 87.8 per 10 000, falling to a low of 6.9 per 10 000 in April. Thereafter, screening rates began a steady recovery, to 88.2 per 10 000 at the end of July.

Over the same time period, weekly colonoscopy screenings fell from 15.1 to 0.9 per 10 000, before rebounding to a weekly median of 12.6 per 10 000 by July 31, 2020.

Multivariable regression analyses confirmed the significant declines in screening mammography and colonoscopy. A larger decline in colonoscopy was observed in high-income counties. Otherwise, the analyses showed no significant demographic variations.

Laura Makaroff, DO, of the American Cancer Society in Atlanta, said that the pandemic’s ultimate impact on cancer screening and cancer care is still largely unknown.

“We have seen similar data showing some rebound in cancer screening rates last summer and fall, but even those turnarounds show an approximate 30% decrease in cancer screening compared with pre-pandemic rates,” she said to MedPage Today in an email. “We also don’t yet know the full impact of the late fall and winter surges on disruptions in cancer screening and diagnosis.”

“The COVID-19 pandemic has had numerous consequences secondary to the disease itself, including reduced access to care for other illnesses,” Dr Makaroff added. “While these measures were necessary, delays in cancer screening, diagnosis, and treatment due to reduced healthcare access will likely result in a short-term drop in cancer diagnoses followed by increases in late-stage diagnoses and preventable cancer deaths.

“The full impact of the COVID-19 pandemic on cancer prevention and early detection will not be known until population-based nationwide data become available in the years to come,” she said.

Source: MedPage Today

Journal information: McBain RK, et al “Decline and rebound in routine cancer screening rates during the COVID-19 pandemic” J Intern Med 2021; DOI: 10.1007/s11606-021-06660-5.

Low-dose Radiation May be Beneficial to Humans

A study has found that cancer rates go down and life expectancy increases in areas of the US with high natural background radiation, flying in the face of decades of accepted theory that low-dose radiation is still harmful.

Natural background radiation exists from sources in the environment. This is the first large-scale study looking at terrestrial radiation (coming from radioactive elements in rocks, which vary across regions) and cosmic radiation (which increases with altitude). The Ben-Gurion University of the Negev (BGU) researchers found that life expectancy is approximately 2.5 years longer for those who live in areas of naturally high background radiation vs those who live in areas of low radiation.

The linear no-threshold (LNT) hypothesis has guided radiation protection policy in the US since the 1960s. This assumes that health risk from radiation is linear and incremental, meaning that there is no safe minimum dose – all ionising radiation is assumed to be harmful. However, numerous studies have contended that radiation at low doses initiates a protective hormesis effect.

Reduced levels of a number of types of cancers were found when in areas of high background radiation levels as opposed to lower. In both sexes, there was a significant decrease in lung, pancreatic, colon and rectal cancers. Among men, there were additional decreases in brain and bladder cancers. However, no decreases in cervix, breast or prostate cancers or leukaemia were observed.

“Decades of scientific theory are potentially being disproven by the remarkable researchers at BGU. These findings might even provide a sense of relief for those who reside in areas in the U.S. with higher-than-average background radiation,” said Doug Seserman, Chief Executive Officer, American Associates, BGU.

Using the United States Environmental Protection Agency’s radiation dose calculator, the researchers retrieved data background radiation on all 3,29 US counties. Cancer rate data were retrieved from the United States Cancer Statistics, while life expectancy data were retrieved from the Institute for Health Metrics and Evaluation at the University of Washington Medical Center.

“It is reasonable to suggest that a radiation threshold does exist, yet it is higher than the upper limit of the natural background radiation levels in the US (227 mrem/year),” the researchers wrote. “These findings provide clear indications for re-considering the linear no-threshold paradigm, at least within the natural range of low-dose radiation.”

Source: News-Medical.Net

Journal information: David, E., et al. (2021) Background radiation impacts human longevity and cancer mortality: reconsidering the linear no-threshold paradigm. Biogerontology. doi.org/10.1007/s10522-020-09909-4.

Positive Safety News for Important Diabetes Drugs

A systematic review and meta-analysis showed that GLP-1 receptor agonists weren’t associated with increased risk for incident breast cancer.

Giovana Fagundes Piccoli, MD, of the Hospital de Clínicas de Porto Alegre in Brazil presented the findings at the Endocrine Society’s virtual ENDO 2021 meeting.

Out of 48 267 patients treated with a GLP-1 receptor agonist there were 130 cases of incident breast cancer among versus 107 cases out of 40 755 controls. Control participants received either placebo or active treatment with a non-GLP-1 receptor agonist. 
There was also no difference in risk of benign breast neoplasms for patients on GLP-1 receptor agonists versus other drug types (RR 0.99).

No difference was seen among individual GLP-1 receptor agonists, including each of the four major drugs in the class — liraglutide, dulaglutide, semaglutide, and albiglutide  — with exendin-4 mimetic agents including exenatide and lixisenatide.

No difference in incident breast cancer risk was seen when comparing trials with an open-label design versus double-blinded trials.

Dr Piccoli explained that her team wanted to investigate the issue further following the 2015 SCALE Obesity and Prediabetes trial, which found more breast neoplasms in patients receiving liraglutide than with placebo (4.36 vs 1.80 per 1000 person years). In that study, most of those neoplasms developed in the first year of treatment with GLP-1 receptor agonist, and were more common in participants with greater weight loss on the agent.

“I think that the results of our meta-analysis adds more security and safety information about this treatment,” said Dr Piccoli during a press conference. “Patients, doctors, and other health professionals can be more secure of the safety of these drugs.”

For this analysis, her team searched a variety of medical journal databases for randomised trials assessing GLP-1 receptor agonists in adults with overweight, obesity, prediabetes, or type 2 diabetes that also reported breast cancer or benign breast neoplasm incidence.

Participant ages ranged from 45 to 70 years old and follow-up lasted between 24 weeks to 7.5 years.

Piccoli emphasised that these findings only apply to patients treated with a GLP-1 receptor agonist for diabetes control or weight loss in the absence of pre-existing breast cancer. She added that patients with a history of breast or any other cancer were usually excluded from the trials in this meta-analysis.

“We can say in a general population with type 2 diabetes and obesity, [GLP-1 receptor agonists] are safe,” Piccoli said. But the class’s safety in patients with a history of breast cancer is less certain, she added.

Source: MedPage Today

Presentation information: Piccoli G, et al “Do GLP-1 receptor agonists increase the risk of breast cancer? A systematic review and meta- analysis” ENDO 2021.