

Day: September 16, 2026

Making Medical AI Smarter and Safer

A conversation with Qingyu Chen, PhD, about what medical artificial intelligence learns, what it memorises, and what it takes to use it responsibly.

Qingyu Chen, PhD, and his team set out to study how artificial intelligence language models are adapted for medicine and found that what these models memorise can be both useful and risky. A model may retain valuable medical knowledge, but in a controlled study using real hospital records, the same fine-tuning – the added training that adapts a model to a specific task – that improved diagnostic performance also made it more likely to reproduce material it had seen during training, including sensitive patient information.

The study, published recently in Nature Communications, reflects a question at the center of Chen’s research: How can medical AI become not only more capable but also more reliable and safer? The study was led by its first author, Anran Li, PhD, who conducted the research as a postdoctoral researcher in Yale’s Department of Biomedical Informatics and Data Science.

Chen is an assistant professor of biomedical informatics and data science at Yale School of Medicine, with a secondary appointment in ophthalmology. He leads research on the accuracy and reasoning of medical language models and on multimodal AI-assisted disease diagnosis, which draws on both text and medical images.

The following conversation with Chen discusses what medical AI learns, what it memorises, and what it takes to use it responsibly.

What is your lab’s research focus?

Our lab does two things that are usually treated as separate: We build medical AI, and we study where it fails.

On the building side, we work with two main kinds of information medicine runs on. We develop models that read clinical records and the medical literature, models that analyse medical images to help diagnose disease and predict its course, and systems that combine both, so an AI can weigh a patient’s written history alongside their scans, the way a physician would.

But a model that performs well on a test is not the same as a model you can trust with a patient. So, we also study how these systems fail. They can state falsehoods with complete confidence. They can reach a right answer through faulty reasoning. And, as our recent work shows, they can memorise sensitive information from the data they were trained on.

Our goal is to develop medical AI that is genuinely useful, understand where it breaks down, and produce the evidence needed to know when it can – and cannot – be trusted.

Why work across both text and images?

Because medicine is inherently multimodal. A patient cannot be understood through a single paragraph or a single image. Clinical decisions often require bringing together a patient’s history, laboratory results, medical notes and imaging findings.

Our work spans both sides of that. On the language side, we develop methods to help computers understand clinical records and biomedical literature. On the imaging side, much of our research focuses on medical images and specialties that depend heavily on them—ophthalmology in particular, where we work on diagnosing eye disease and predicting how it will progress. This is also why I hold a secondary appointment in ophthalmology.

What excites us most is bringing these areas together: systems that can integrate text, images and other clinical information to form a more complete picture of a patient and better support medical decision-making.

Progress here requires more than developing new models. One of the biggest barriers is the limited availability of medical data that is large enough, reliable enough and free for researchers to share.

To help address this, we recently developed MedPMC, a system that has assembled 11 million medical images paired with their accompanying text, drawn from research literature that is openly licensed for reuse—and that is designed to keep growing as new research is published. We’ve made the data, the tools used to assemble it, the tests for measuring performance and the resulting models publicly available so that other institutions can develop, evaluate, reproduce and adapt these systems rather than starting from scratch.

Your team recently published a study in Nature Communications on how AI models ‘memorise’ medical data. What does memorisation mean here?

Memorisation means that a model can recall or reproduce content it encountered during training. If a model has been trained on clinical guidelines, it may reproduce part of a guideline when you give it the opening of that passage. If it has had additional training on a set of medical exam questions, it may produce an answer choice that appeared in that training data – even after we removed that choice from the question.

That is different from simply saying that a model performs well. When a model answers a question correctly, there are several possible explanations. It may have acquired genuine medical knowledge. It may have learned a pattern of reasoning it can apply to problems it hasn’t seen before. Or it may simply recognise the question and reproduce something it previously saw during training. If all we check is whether the final answer is correct, we cannot tell these apart.

So, our goal was to look beyond accuracy and ask a different set of questions: How often does memorisation occur? What types of content get memorised? How much can a model reproduce? Does what it memorised earlier survive further training? And what does all of this mean for using these systems in medicine?

What did you find?

We looked at the main stages a general-purpose model goes through on its way to becoming a medical one.

First, we examined models that had already undergone continued pretraining, in which a general-purpose model is trained further on large collections of medical text, including biomedical literature, clinical guidelines and clinical notes. Second, we evaluated models that had been fine-tuned on the standard question-and-answer datasets that the field uses to test medical models. Third, we conducted a privacy-protected, HIPAA-compliant study using more than 13 000 medical records to fine-tune models for disease diagnosis.

This was done in an isolated and secure computing environment. These records had already been collected in the course of care; the study did not recruit patients or change anyone’s treatment.

Across those settings, we examined both general-purpose models and models trained on medical data, 10 different datasets containing hundreds of thousands of records and thousands of model responses that we manually reviewed.

The patterns differed depending on the training stage. Continued pretraining was more likely to produce long, word-for-word matches to source documents. Fine-tuning produced less long-form copying in some settings, but more memorisation tied to the specific task the model was trained on. For example, after fine-tuning on medical question-and-answer datasets, models reproduced roughly 14% to 21% of the answer choices that had been removed from the question the model was shown.

We also found that memorisation was persistent. Depending on the setting, as much as 87% of what a model memorised during continued pretraining was still present after it had been fine-tuned on a new medical task. Fine-tuning does not necessarily erase what a model previously memorised. It may preserve that content while adding new memorisation specific to the task it was just trained on.

What did the clinical case study show?

The clinical case study showed both the potential benefit and the risk of adapting these models to real-world medical data. Fine-tuning improved diagnostic performance; for one model, the correct diagnosis came up as its first choice 54.8% of the time, up from 48.6%. In some specialties, the gains were larger than that – more than 10 percentage points in areas such as cardiology and nephrology, which deal with heart and kidney conditions.

At the same time, the study showed a real privacy risk. In a controlled test conducted in a secure research setting, we found that the model could sometimes reproduce sensitive information from the records used to train it. This was not something that would happen during patient care, but it shows that privacy risks should be evaluated before models trained on clinical data are shared or deployed.

Is memorisation always harmful?

No. One of the central findings of our study is that memorisation in medicine is not a single behaviour.

We identified three broad types. The first is beneficial memorisation. A model may accurately retain biomedical concepts, clinical guidelines, the medical literature it has read or specific medical knowledge tied to its task. That kind of memory may support factual accuracy and help the model perform medical tasks more effectively.

The second is uninformative memorisation. Models sometimes reproduce document disclaimers, section headings, formatting instructions or other boilerplate language. This adds little medical value and may indicate that the model is learning surface-level patterns rather than deeper medical understanding.

The third is harmful memorisation. This includes reproducing quirks specific to a particular dataset, word-for-word passages from patient notes, protected health information or other sensitive patient content. This form of memorisation may create privacy risks and may also indicate that the model is leaning too heavily on its training data rather than generalising to new cases.

The important question, then, is not simply whether a model memorises; it is what the model memorises, why it memorises it, and whether that memory supports or undermines the medical use it is intended for.

Did anything about the way memorisation develops surprise you?

One thing that stood out: Memorisation did not only show up late, after a model had been trained too long. It began early.

As we trained the models, we tracked their progress and compared three things: how much they were memorising, how well they were learning by the usual measure, and how accurate their diagnoses were. Memorisation began increasing relatively early, even while the standard measures still showed the model improving, and before its diagnoses had reached their peak accuracy.

That means traditional indicators researchers watch during training – such as whether the model keeps improving on held-out data, or the point at which they would normally stop training – are useful but may not be sufficient on their own. A model can appear to be learning effectively according to standard performance measures while simultaneously increasing its retention of training-specific content.

We also found two other patterns. Larger models and longer inputs were generally associated with more memorisation. By contrast, changing common generation settings such as temperature – which controls how varied the model’s answers are – had relatively limited effects. This suggests that memorisation is fundamentally connected to how a model is trained and what data it is exposed to, rather than being something that can simply be solved by adjusting how the model generates its answers after training.

What do you most want readers to take away from this work?

Adapting an AI model to medicine does not simply make it “more medical.” It changes what the model knows, what it remembers and what it may reproduce.

Some of that memory is valuable. We want models to retain accurate medical knowledge and clinical guidance. But we do not want them to rely on meaningless repetition, echo back the answers to test questions or expose sensitive information from patient records.

Trustworthy medical AI therefore requires more than measuring whether a model gets the answer right. We need to understand how it got there, what it retained from training, and whether it will stay safe and reliable when used in a new setting.

Source: Yale School of Medicine
Scientists Target Periodontitis with Viruses

Scientists have shown that a naturally occurring virus can dismantle complex bacterial communities responsible for severe gum disease, offering a potential alternative to traditional antibiotics.

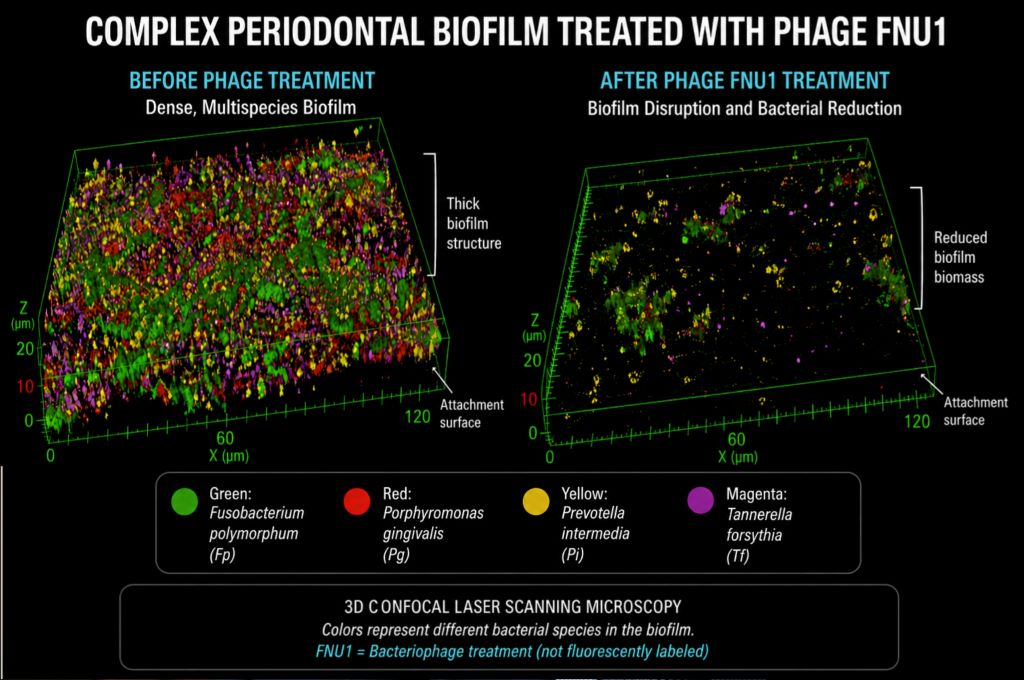
In the first study to demonstrate this effect, La Trobe University researchers found the FNU1 virus selectively attacked Fusobacterium polymorphum, a bacterial species that helps other disease-causing bacteria to stick together and thrive.

The virus reduced total bacterial levels by 94 per cent, leaving only about six per cent of the original disease-causing plaque intact.

Despite targeting just one bacterial species, the treatment dramatically reduced the size and density of the plaque, with levels of three other bacteria linked to gum disease falling by more than 85 per cent.

Dr Mwila Kabwe, lead author and Post Doctoral Research Fellow at La Trobe’s Holsworth Biomedical Research Centre, said the findings were important given gum disease affects more than half the world’s population and remains a leading cause of tooth loss.

The research focused on bacteriophages or phages, viruses that infect bacteria but are harmless to humans.

“Current treatments for gum disease don’t directly target the bacterial imbalance that drives the disease, and the dense layers of bacteria that form around teeth can be resistant to antibiotics,” Dr Kabwe said.

“By targeting one of the key bacteria that holds these disease-causing communities together, we were able to destabilise the entire plaque community.

“The findings suggest phages could offer a more precise way to treat gum disease while preserving healthy bacteria.”

While the laboratory findings are promising, further research is needed before phage-based treatments could be used in dental practice.

The study forms part of Dr Kabwe’s early career-research investigating how phages could be used to target harmful bacteria linked to oral disease and other chronic health conditions.

Source: La Trobe University

Healthy Eating Associated with Slower Biological Aging – But No One Diet is Best

Photo by Gustavo Fring

A study by DZNE finds that healthy eating is associated with slower biological aging – and that there is more than one way to eat healthily. The researchers examined ten dietary patterns considered healthy, including the Mediterranean, Nordic, and a plant-based diet, as well as the DASH diet, which is designed to help lower blood pressure. All were linked with slower biological aging, with age-related changes in the DNA serving as markers. These results, based on data from DZNE’s Rhineland Study and confirmed with data from an independent study, are published in the journal Nature Communications. 

“Our study suggests that healthy eating goes hand in hand with slower biological aging. The effects are not massive, but they are measurable and relevant for prevention. By slowing the aging process, the risk of age-related diseases such as dementia or cardiovascular disorders can be reduced. Thus, healthy eating contributes to healthy aging,” says Prof. Monique Breteler, Director of Population Health Sciences at DZNE and head of the Rhineland Study. “Importantly, there is probably no single ‘correct’ diet. According to our data, various dietary patterns are associated with slower aging, some more, some less. That is an encouraging finding, because it leaves room to tailor healthy eating to personal and cultural preferences, budget and taste.” 

Molecular Aging Measures 

For their analysis, the researchers evaluated blood samples and dietary habits from about 7500 women and men: This included 6470 participants of DZNE’s Rhineland Study in Bonn – where the findings were initially made – and 1034 participants of the EPIC-Potsdam Study of the German Institute of Human Nutrition Potsdam-Rehbrücke (DIfE), where the key results were independently confirmed.  

From blood, the team determined chemical modifications in the DNA, known as “DNA methylation patterns”, which influence gene activity and thus biological mechanisms. Since these molecular markers change systematically over the course of life, they are considered indicators of biological aging. 

“We applied three different approaches, so-called epigenetic clocks, to read biological aging from DNA methylation,” explains Juliana Tavares, a doctoral researcher at DZNE and lead author of the current publication. “To this end, we leveraged state-of-the-art technology, which allowed us to cover about 850 000 sites in the DNA. This is roughly twice as many as in most previous studies.” 

Healthy Eating: Different for Everyone 

The researchers also matched every participant’s eating habits against the recommendations of each of the ten diets studied. Adherence was quantified and graded using a scoring system based on how closely individuals followed each dietary pattern. “One and the same person could therefore rank high on one diet score and low on another. In other words: People who ate healthily by one standard were often not the same people who ate healthily by another. According to our data, hardly anyone counts as a healthy eater by every standard at once,” says Tavares. 

However, across the board, higher diet quality was associated with slower biological aging. This applied to all of the ten diets examined. “While there are measurably differences between the diets, they are modest in absolute terms. It’s the big picture what matters,” says Tavares. “In summary: When it comes to slowing down the aging process, there isn’t just one healthy diet, but indeed a whole repertoire of possible diets with a positive effect.”  

One result was particularly noteworthy: the association between diet quality and slower biological aging was most pronounced in smokers, even though smokers were by no means eating healthier than non-smokers. The biological explanation is still open. “Smoking is very harmful to health,” says Tavares, “One explanation for our findings might be that there is just more health benefit to gain for smokers by eating healthy because of the enormous detrimental effects of smoking.” 

Shared Biological Pathways 

Although each dietary pattern was associated with its own distinct set of DNA methylation sites, the biological mechanisms involved showed substantial overlap. “More than 70 percent of the affected biological pathways were shared across all diets. These involve cell structure, cell signalling and metabolism – processes central to aging and chronic disease. Therefore, it is understandable that the dietary patterns we examined were all linked with a slowing of biological aging,” says Tavares. “A few pathways were diet-specific, and they matched each diet’s main objectives: heart-related pathways were unique to the DASH diet, and pathways related to cognition and memory were unique to the so-called MIND diet, which aims to support brain health. You don’t need a perfect diet – that may be the most practical message here. But moving forward, the diet-specific pathways point to future research on targeted dietary interventions. This could be helpful in designing targeted health recommendations.” 

Source: DZNE

Researchers Discover How Epstein-Barr Virus Triggers Multiple Sclerosis Attacks

Study found distinct immune changes preceding multiple sclerosis relapse, providing new insight into how Epstein-Barr virus reactivation may trigger an MS attack in people with genetic risk factors

An electron micrograph showing three Epstein-Barr virus (EBV) particles colourised red-orange. Credit: NIAID

A new study illuminates the connection between the Epstein Barr virus (EBV) and multiple sclerosis (MS), pointing to a causal role for reactivation of the virus in triggering MS attacks in people with certain genetic risk factors. In a study of blood samples from more than 100 participants with MS, Mass General Brigham researchers detected increased EBV lytic activity in immune cells up to three months before MS relapse and discovered that these cells also showed elevated expression of genes linked to MS risk. The finding helps explain how a common virus and genetic risk may work together to trigger MS attacks. The work is published in Nature Medicine.

“These findings open a whole new avenue for targeted therapeutics,” said senior author Tanuja Chitnis, MD, director of the Translational Neuroimmunology Research Center and Chief of the Division of Neuroimmunology at Mass General Brigham. “Currently, most MS treatments work by broadly suppressing the immune system. Our results suggest there’s an opportunity to be more precise and develop approaches that target EBV or the immune cells involved in relapse.”

Researchers analysed blood samples from 114 patients with MS and 21 healthy participants in the Comprehensive Longitudinal Investigation of Multiple Sclerosis (CLIMB) study, a decades-long MS cohort based at Brigham and Women’s Hospital, to track immune changes before relapse. The study included samples collected up to 90 days before participants experienced a relapse, allowing researchers to compare the pre-relapse immune state with periods of remission in the same patients.

To identify which immune cells changed the most before a relapse, researchers used single-cell RNA sequencing and other molecular techniques to analyse hundreds of thousands of immune cells. They found that B cells (immune cells that can house dormant EBV) showed some of the strongest changes, activating genes associated with antiviral responses, inflammation and EBV activity. The researchers also observed an increase of ABC-like B cells, a subset of cells linked to viral infections and autoimmune disease. They found that EBV proteins (derived from EBV genes) triggered MS risk genes to be expressed in immune cells prior to relapse, but not during remission or in healthy controls.

If these findings are validated in larger, prospective studies, blood biomarkers of EBV activity could help identify patients at increased risk of relapse, complementing MRI scans and existing blood biomarkers that typically detect disease activity only after inflammation is already underway. The authors note that future studies are needed to determine whether these findings extend to early-stage and progressive forms of MS.

“We believe this work provides foundational insights into the cause of multiple sclerosis,” said Chitnis. “This study puts all the pieces together, showing a timeline of how the reactivated virus interacts with risk genes to unleash inflammation before relapse

Source: Mass General Brigham

Autistic Kids Showed Improved Social Skills After Summer Programme

Photo by Peter Burdon on Unsplash

A summer intervention programme for autistic children ages 4-6 with no intellectual disability significantly improved their social performance, according to a study by researchers at the Institute for Autism Research (IAR) at the University at Buffalo. It was published in Advances in Neurodevelopmental Disorders.

“Completion of our 5-week summerMAXyc programme was associated with significant social, behavioral and autism symptom benefits for the children,” says Christopher J. Lopata, PsyD, co-author on the study and co-founder/co-director of the IAR with Marcus L. Thomeer, PhD; both are professors of pediatrics in the Jacobs School of Medicine and Biomedical Sciences at UB. “Developing such foundational skills early in development sets the stage for development of more advanced skills later in childhood, adolescence and adulthood, thus leading to better long-term outcomes.”

Thomeer notes that while programmes for autistic children with no intellectual disability ages 4-6 do exist, few provide intensive social programming. This population also tends to engage in significantly fewer group recreational activities in general than their peers without autism, further limiting social development opportunities.

“This constitutes a significant gap in social intervention development and service provision, which prompted our interest in developing such a programme for this population,” he says. 

Five weeks, five days a week

The intensive summerMAXyc programme was conducted five-days-a-week over five weeks in the summer. The programme follows a similar model to that of the IAR’s successful, evidence-based summerMAX programme for older children, which has helped improve the social skills of hundreds of children since it began 23 years ago.

In the summerMAXyc programme, each 6-hour day included 8 cycles of 30 minutes each, which began with 10 minutes of instruction in particular skills, such as having a conversation or accepting consequences, followed by a 20-minute cooperative activity.

According to the study, the children found that the programme was fun and helped them learn skills and make new friends. Average child satisfaction was 14.9 out of a possible 15 with parent satisfaction at 69.8 out of a possible 70. Parents reported significant improvement in the children’s social skills, behaviors and autism symptoms.

There is broad consensus that earlier intervention is associated with better outcomes for autistic children. And parents are often the first to recognize the need.

“Parents reach out to us because their child has difficulty navigating the social world,” says Thomeer. “They describe their autistic children as wanting to have friends but not knowing what to do in social situations.”

Families noticed the difference

Over the course of their child’s participation in summerMAXyc, Thomeer says, parents reported that other family members began to notice the child playing with others, not just playing alone. They also noticed that the child now makes eye contact, asks about others, plays games without getting upset and can recognise and understand different emotions.

According to Thomeer, a mother of one of the participants reported that her child not only noticed that she was frustrated about something, but also told her to “squeeze the orange,” a technique the children are taught where they squeeze an imaginary orange and take a deep breath in order to calm themselves down.

One of the study’s major strengths involved the use of objective observers to assess the children’s social performance. According to Lopata, parents are a critical source of information, however there is a risk of bias because they know that their children are in the intervention. Most social skills intervention studies for autistic children rely on parent ratings alone and therefore suffer from this limitation, he adds.

 “Our use of masked observers – trained individuals – eliminated that risk because they were unaware that the children received an intervention,” says Lopata.

The authors also note that the intervention was similarly successful in improving the children’s social performance and autism features regardless of the child’s age, IQ level, communication ability or level of diagnostic symptoms.

“There is widespread recognition in the field that no intervention will be effective for all autistic children and there is a significant need to determine which children are most likely to benefit from a specific intervention,” says Lopata. “Answering this question can help ensure that scarce resources are efficiently allocated and that children receiving a given intervention are most likely to benefit.”

The next step is to test the intervention in a large-scale randomised clinical trial with a control group, which would be a first for such a social intervention in this population. 

Original written by Ellen Goldbaum

Source: University at Buffalo

