Tag: antifungal

Cryptococcal Meningitis Claims Many Lives in SA – Stopping it won’t be Easy

Cryptococcal meningitis is a serious fungal infection causing inflammation of the lining of the brain. (Photo: Pixabay)

By Elri Voigt for Spotlight

One of the top killers of people living with HIV in South Africa is a fungal infection. In this Spotlight special briefing, we unpack what we know about this dangerous disease called cryptococcal meningitis, why it remains so deadly, and what we can do about it.

Someone who is diagnosed with HIV today could live a relatively healthy and normal life. That is providing that they are consistently taking the antiretroviral treatment that successfully suppresses the virus in their bodies.

Roughly four out of every five people living with HIV in South Africa are on treatment. The remaining one in five, or 20%, represents around 1.6 million people who could potentially get very ill from a virus that is attacking their immune system, leaving them at risk of complications and opportunistic infections.

The best-known HIV-related opportunistic infection is tuberculosis, comfortably the top killer of people with HIV in South Africa. The second top killer of people with HIV, at least according to most estimates, originates from the environment around us. Around 19% of HIV-related deaths were attributed to this illness in a 2022 modelling study. Despite the many lives this illness has claimed, it has lurked chronically under the radar, much more so than TB, which itself has been somewhat in the shadows.

A fungus that is all around us

“Cryptococcal meningitis is a serious fungal infection causing inflammation of the lining of the brain (meninges),” explains Dr Richard Lessells. He is an infectious diseases clinical researcher at the KwaZulu-Natal Research Innovation and Sequencing Platform (KRISP) at the University of KwaZulu-Natal (UKZN).

Cryptococcal meningitis is caused by one of two fungi – Cryptococcus neoformans or Cryptococcus gattii. The former is responsible for most infections in people. The fungus is found all around us, particularly in rotting trees and wood, the soil and bird droppings. The tiny fungal spores are routinely inhaled by humans.

In most people, the immune system takes care of the spores and eventually controls it, explains Lessells. The fungus only starts causing problems when the immune system is weakened and not able to contain it. When that happens, the fungus spreads to the bloodstream, from where it can spread all over the body. While it can cause disease in other places, like in the lungs or on the skin, the most common place the fungus heads to is the brain and its lining. This lining, which consists of three membrane layers that cover and protect the brain and spinal cord, is called the meninges.

Classic symptoms of cryptococcal meningitis include headache, stiff neck, light sensitivity, fever, confusion, and nausea and vomiting. The symptoms can eventually be debilitating, with one patient quoted in literature saying that a previous gunshot wound hurt less than his headache. The inflammation in the meninges causes a dangerous build-up of pressure in the skull – called raised intracranial pressure – which explains the severity of the headaches.

Two disease states

When the fungus spreads from the lungs to the rest of the body, it doesn’t immediately cause inflammation in the brain or lead to severe illness. At this early stage, it is possible to stop the infection from spreading to the central nervous system, if it is detected and treated.

The key is a blood test, explains Professor Graeme Meintjes, an infectious diseases specialist based at the University of Cape Town and Clinical Professor of Infectious Diseases at Queen Mary University of London. The test, called a cryptococcal antigen test (CrAg), looks for a complex sugar molecule found in the cell wall of the fungus. When the test detects the sugar molecule in the blood, that person has what is called cryptococcus antigenemia – meaning the antigen is present in the body.

“They would then be treated pre-emptively with antifungal medication, essentially to prevent them from progressing from the antigenemia to the meningitis,” Meintjes says. Fluconazole, the drug used for this early treatment, is cheap, widely available, and works well.

If someone is not treated in time, the fungus spreads to the central nervous system – specifically the brain – and causes dangerous inflammation in the lining of the brain. When it gets to this stage, the infection is called cryptococcal meningitis. It is diagnosed by doing a CrAG test on spinal fluid obtained through a lumbar puncture, explains Lessells.

The key difference between the two disease states is that symptoms only manifest once cryptococcus antigenaemia has progressed to cryptococcal meningitis.
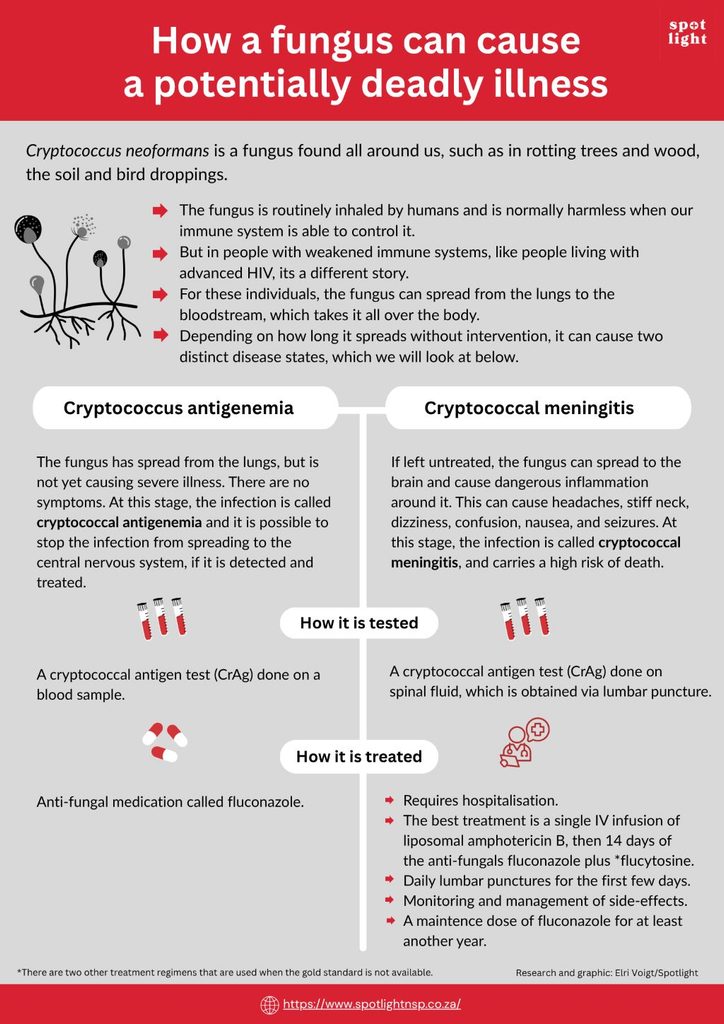
Someone who has cryptococcal meningitis needs to be admitted to hospital. This is because the drugs used to treat it will only start helping to control the dangerous inflammation after a few days. In the meantime, the build-up of intracranial pressure needs to be reduced through daily lumbar punctures during the first few days in hospital, says Lessells. The drugs themselves can also cause some dangerous side effects that need to be monitored closely and managed.

“Cryptococcal meningitis is associated with very high early mortality. GERMS-SA surveillance in South Africa has shown in-hospital mortality in routine care to be between 30-40% for the past 20 years,” points out Lessells. GERMS-SA is a national, population-based laboratory surveillance programme led by the National Institute for Communicable Diseases (NICD). It monitors bacterial, fungal, and parasitic infections across South Africa through a network of laboratories and sentinel hospital sites.

Screening the right people

Since waiting for cryptococcal meningitis symptoms to appear is a losing strategy, the focus has been on proactively identifying and offering CrAg screening to people at high risk of the condition.

In South Africa, says Lessells, cryptococcal meningitis most commonly affects people living with HIV, especially those with advanced HIV disease. This is a state where the virus is not under control in the body and the number of important immune cells called CD4 cells are dangerously low, at less than 200 cells/mm3. CD4 cells are a type of white blood cell important for a well-functioning immune system. A CD4 count above 500 is generally considered to be healthy.

But cryptococcal meningitis can also affect organ transplant recipients, people undergoing cancer treatment or those taking steroids. “Very occasionally, it can affect people with no apparent immunocompromising condition,” adds Lessells.

Either way, people with advanced HIV are the most obvious group to target with screening efforts. In 2025, there were about 7.8 million people living with HIV in South Africa, according to estimates from Thembisa, the leading mathematical model of HIV in the country. Of those, roughly 530 000 had advanced HIV, with a CD4 count of less than 200. This group of around half-a-million people are at highest risk of cryptococcal meningitis.

The National HIV treatment guidelines recommend that people living with HIV should be offered CrAg screening if they present with a blood test showing a CD4 count of less than 200. But the catch is that often people with advanced HIV disease are not accessing healthcare services or only accessing services once they are already very ill. In 2025, around 42 000 of the adults living with HIV who started taking treatment that year had a CD4 count of less than 200, according to Thembisa. This is over 20% of the total number of people who started taking treatment that year.

“Cryptococcal meningitis is essentially a marker for the gaps in our HIV programme,” says Liliwe Shuping, an epidemiologist at the NICD.

“If a patient gets cryptococcal meningitis, it usually means they fell through the cracks of the healthcare system; either they were never tested for HIV, they were lost to follow-up, or their treatment failed without being caught,” she says.

She describes cryptococcal meningitis as “almost exclusively a disease of advanced HIV, untreated HIV, or failed HIV care”.

There are thus two layers to the problem: First, too many people with HIV are not in care and end up developing advanced HIV, and second, even when people are visiting health facilities, they are not always screened in time.

“At the primary healthcare level, there are still challenges with implementation of the CrAg screening programme,” says Lessells. The laboratory component works well, but then he says there are the usual problems of a healthcare worker seeing the result, acting on the result, being able to contact the patient to recall them to the facility, and then referral to a higher level of care for lumbar puncture.

Unfortunately, people do fall through the cracks. Similarly, he suggests there are sometimes avoidable delays at hospital level when it comes to doing lumbar puncture. For example, some doctors might wait for a CT scan of the brain, which is not always necessary and can lead to delays.

At least some of these challenges should be reduced with the latest National HIV treatment guidelines, which address these issues with more information and clarified referral pathways, Lessells says. For example, the guidelines include a chapter on managing advanced HIV, among others covering how to screen for, diagnose and manage cryptococcal meningitis. It also spells out the requirement for automatic CrAg testing for people with CD4 counts below 200.

The big picture – what the data tells us

Some good news from the GERMS-SA report is that there has been a decline of about 11% in reported cryptococcal meningitis cases from 2023 to 2024. There has also been a drop in cryptococcal meningitis incidence over the last six years, says Shuping.

The annual number of recorded cases dropped from about 6 000 in 2018 to 4 000 in 2023, decreasing by about one third overall, says Shuping. This is based on the Public Health Bulletin study on data from 2018 to 2023. The authors caution that the decline in cases could be due to the potential impact of strengthening public health interventions or may reflect an under-detection of cases. Either way, these numbers reflect only confirmed cases. Modelling suggests real cryptococcal meningitis incidence may be several times what is being reported.

Shuping cautions that despite the reduction in reported cases, cryptococcal meningitis is still killing many people living with HIV.

The in-hospital mortality rate for cryptococcal meningitis “has not meaningfully improved,” she points out. Despite treating fewer cases over time, she says that a patient who develops cryptococcal meningitis today has roughly the same high risk of dying in hospital as they did six years ago.

In general, Meintjes explains that brain infections have a high mortality. Even with the best treatment options and under clinical trial settings, around a quarter of patients die despite treatment.

Quality of care matters. Lessells says that while drug treatment generally receives the most attention, it is only one component of the clinical management of cryptococcal meningitis. Monitoring and reducing intracranial pressure and preventing and monitoring side effects from the drugs are vital. In a setting where resources are stretched thin, healthcare workers are overwhelmed and facilities don’t always follow the best practises, he says quality of care can fall, contributing to “stubbornly high mortality rates”.

High mortality despite new drug

Given the serious side effects associated with some medicines used to treat cryptococcal meningitis, there was great optimism in 2022 when an old anti-fungal medicine called flucytosine was approved for use in the country to the treat the illness.

This followed the AMBITION trial, where researchers found that combining flucytosine with two other powerful drugs (liposomal amphotericin B – an IV infusion and fluconazole – an oral medication) improved patient treatment. Meintjes explains that the combination of the three drugs was not “better” than the previous regimen as there were similar mortality rates between the two arms, but it was safer and had far fewer side effects.

Meintjes says that today the first choice for the treatment of cryptococcal meningitis is a single infusion of liposomal amphotericin B, then 14 days of fluconazole plus flucytosine.

The second choice, that has similar mortality outcomes to the first but has more side effects, is seven days of another form of amphotericin B plus flucytosine and fluconazole.

The third-choice regimen is 14 days of amphotericin B plus fluconazole. Meintjes says that the outcomes for this regimen are not as good as with the first two.

After the initial treatment, regardless of which regimen was used, patients then have to take a maintenance dose of fluconazole for at least another year to completely eradicate the fungus. If the fungus is not entirely gone from the body, it can cause disease again in the future. Patients living with HIV also need to be started on antiretroviral therapy around four weeks after the meningitis diagnosis, which helps prevent a relapse.

Best drugs not always in stock

One reason the approval of flucytosine, and the improved treatment regimens it enables together with liposomal amphotericin B, hasn’t yet resulted in better outcomes is that patients simply aren’t always getting the drugs.

“[O]ften we’re in a situation where we have to use the third choice because neither liposomal amphotericin B nor flucytosine are available and that’s associated with worse outcomes,” says Meintjes.

Jessica Burry, a pharmacist and technical officer working on advanced HIV with Unitaid, concurs. “I think what it comes down to is if you don’t have access to liposomal amphotericin B and flucytosine, then you don’t have the gold standard of treatment…and it’s shown quite clearly that mortality rates are much higher in those groups [that don’t have access to these drugs],” she says.

There are several reasons why a drug might not be in stock at the clinic or hospital where it is needed. Often in South Africa, medicines have been in stock in central depots, but not available at all health facilities. A further challenge with medicines for cryptococcal meningitis is that the volumes are comparatively low, and pharmacies may thus be reluctant to hold onto too much stock for fear it might expire.

While such distribution problems have no doubt played a role in limiting access to cryptococcal meningitis medicines, sourcing a reliable supply from manufacturers appears to have been a greater stumbling block in recent years. In this regard, public health imperatives are up against some tough economic realities.

Lessells says that, because flucytosine is an anti-fungal mainly used to treat cryptococcal meningitis, there isn’t much demand for the drug across the world, since many countries very rarely deal with the illness. This, he says, ties into the systemic problem with global drug supplies for rare diseases or rare conditions, where you’ve got a small number of manufacturers and problems in the manufacturing process that then lead to global supply chain problems.

How such dynamics have played out with flucytosine and liposomal amphotericin B is worth a closer look. As often is the case with such questions of medicines access, the picture gets fuzzier before it becomes clearer.

Flucytosine shortages

“During 2026, the availability of flucytosine has been constrained, requiring available stock to be carefully managed and distributed to facilities based on clinical need,” Foster Mohale, spokesperson for the National Department of Health tells Spotlight. He says that there was a global supply problem and that the stockouts were not due to procurement issues at the department. A shortage of flucytosine has also affected several other countries.

Flucytosine is on the Essential Medicines List (EML), which is a list of medicines that are considered vital for the health of the country, like antiretrovirals or insulin. The health department undertakes to supply medicines on the EML to the public health sector, normally via tenders.

Two pharmaceutical companies, Viatris and Macleods, have registered flucytosine with the South African Health Products Regulatory Authority (SAHPRA) for use in South Africa.

Flucytosine was previously procured by the state in terms of a tender awarded to Viatris in 2023. According to Mohale, uptake from provincial health departments was poor, and in July 2024 some expired stock had to be written off. A few months later, the department issued a notice to confirm there was stock and that healthcare facilities should place orders based on their needs.

A new tender was advertised in 2025, but according to Mohale, no “responsive bids” were received. The health department then approached Viatris to supply flucytosine via a Request for Quotation (RFQ). The RFQ process is when the state obtains a quotation on a price when an essential medicine is not available from a contracted tenderer, either because no tender was awarded or the product is out of stock, explains UKZN pharmaceutical sciences expert Dr Andy Gray. This form of procurement, he says, is not unusual.

Viatris initially accepted the RFQ but then informed the department in March 2026 that it was “unable to supply due to manufacturing and global supply constraints”. Macleods was then approached by the health department and is now supplying the drug in terms of a new RFQ. The plan is to issue a new tender when it makes sense to do so. (You can read the health department’s full response here).

Price fluctuations

There have also been challenges with access to another important cryptococcal meningitis medicine. Historically, many low-and-middle income countries have struggled to access liposomal amphotericin B because of the price, says Burry.

Gilead Sciences, the pharmaceutical company that owned the patent for liposomal amphotericin B (which it acquired when purchasing a company called NeXstar Pharmaceuticals) had made it available at an access price for some low-and-middle income countries starting in 2018. It has also taken steps to make the drug more widely available to treat another infection called leishmaniasis through a long-standing partnership with the World Health Organization (WHO).

Initially, it appeared that South Africa was exempt from this access price due to an exclusive distributor agreement Gilead had with some companies. In South Africa, the distributor was Key Oncologics, which at the time had priced the drug for sale in the private healthcare sector at just under $200 a vial (about R2 880 at the time) – a price the health department could not afford when Spotlight first reported on the issue in 2022.

When asked about access to the drug and this agreement, both Gilead and Key Oncologics provided short statements which you can read here and here.

Key Oncologics then did end up supplying the health department with the drug in 2023, through the Gilead Access Programme, explains Mohale, when it was contracted to supply an estimated 5 860 vials at around R600 per vial over two years. That R600 price tag was used to support the inclusion of the drug on the EML and Adult Hospital Level Standard guidelines. There were initially some supply issues as demand for the drug increased, but Mohale says that was resolved when production and supply volumes were adjusted.

Under the current three-year tender, Key Oncologics is contracted to supply an estimated 166 056 vials at R1 167.48 per vial. Although, Mohale adds that following engagements with Gilead and Key Oncologics, the price has been reduced to R1 035 per vial. This is still substantially higher than the previous price of R600. Mohale says the department’s understanding is that South Africa is no longer eligible for the lower access price since a generic alternative has been registered in the country. (You can read the health department’s full response here.)

How outcomes can be improved

As we’ve seen in this Spotlight special briefing, South Africa has made substantial progress against cryptococcal meningitis, but the fungal infection nevertheless continues to cause suffering and death. The reasons for the disease’s continued toll on people living with HIV are varied and complex, but three issues stand out.

First, there is the fact that far too many people living with HIV in South Africa are not on antiretroviral treatment and are thus at increased risk of developing cryptococcal meningitis. As with our HIV response more generally, the priority here must simply be to help more people with HIV to start and stay on antiretroviral treatment. Special attention needs to be paid to finding and supporting the subset of people who don’t go to the clinic or the hospital until they are very ill.

Second, we need to get better at diagnosing infection early, ideally before the development of full-on cryptococcal meningitis. Automatic CrAg testing for people with low CD4 counts is the right move – it needs to be backed up with a push for greater healthcare worker awareness to respond quickly to a positive test.

And third, there is the question of having the best treatments available where they are needed. There was much optimism a few years ago over the introduction of new safer treatments with fewer side effects, but issues with drug supply has dampened the mood considerably since then. The good news, for now at least, is that the national supply of the most important medicines seems to have stabilised. As we know from experience, however, having the medicines in the country does not always mean they are available in the right health facilities when needed.

Ultimately, in all three of these areas much will depend on how well our public healthcare system is, or is not, functioning. As Lessells puts it: “We have the right approach to prevention, diagnosis and management of cryptococcal meningitis. Our guidelines are informed by the best evidence (including clinical trial evidence generated in Africa by African research teams). It’s really about broader health systems strengthening so that we can realise the benefits of this.”

*Reviewed by Professor Graeme Meintjes and Dr Richard Lessells. Spotlight takes full responsibility for any errors.

This special briefing is part of a series by Spotlight – health journalism in the public interest. Sign up to the Spotlight newsletter.

Ignore Antifungal Resistance at Your Peril, Scientists Warn

Candida Auris

Without immediate action, humanity will potentially face further escalation in resistance in fungal disease, a renowned group of scientists from the across the world has warned. The commentary – published in ‘The Lancet’ this week – was coordinated by scientists at The University of Manchester, the Westerdijk Institute and the University of Amsterdam. According to the scientists most fungal pathogens identified by the World Health Organization – accounting for around 3.8 million deaths a year – are either already resistant or rapidly acquiring resistance to antifungal drugs.

The authors argue that the currently narrow focus on bacteria will not fully combat antimicrobial resistance (AMR). September’s United Nations meeting on antimicrobial resistance (AMR) must, they demand, include resistance developed in many fungal pathogens.

Devastating health impacts

Resistance is nowadays the rule rather than the exception for the four currently available antifungal classes, making it difficult – if not impossible – to treat many invasive fungal infections. Fungicide resistant infections include Aspergillus, Candida, Nakaseomyces glabratus, and Trichophyton indotineae, all of which can have devastating health impacts on older or immunocompromised people.

Dr Norman van Rhijn from The University of Manchester coordinated the comment with Professor Ferry Hagen from the University of Amsterdam and the Westerdijk Institute in the Netherlands.

Dr van Rhijn said: “Most people agree that resistant bacterial infections constitute a significant part of the AMR problem. However many drug resistance problems over the past decades have also been the result of invasive fungal diseases largely underrecognized by scientists, governments, clinicians and pharmaceutical companies. The threat of fungal pathogens and antifungal resistance, even though it is a growing global issue, is being left out of the debate.”

Unlike bacteria, the close similarities between fungal and human cells which, say the experts, means it is hard to find treatments that selectively inhibit fungi with minimal toxicity to patients.

Back to square one

Professor Ferry Hagen added: “Despite the huge difficulties in developing them, several promising new agents including entirely new classes of molecules, have entered clinical trials in recent years. But even before they reach the market after years of development, fungicides with similar modes of action are developed by the agrochemical industry resulting in cross-resistance. That sets us back to square one again. It is true many essential crops are affected by fungi, so antifungal protection is required for food security. But the question is, at what price?”

The scientists recommend:

  • Worldwide agreement on restricting the use of certain classes of antifungal molecules for specific applications.
  • Collaboration on solutions and regulations that ensure food security and universal health for animals, plants, and humans.
  • Adding priority to AMR to fungal infections at the UN’s meeting in September.

Source: Universiteit van Amsterdam

Rise in Global Fungal Drug-resistant Infections

In a recent study published in Pathogens and Immunity, researchers issue a call to action over how rising antifungal resistance is worsening the problem of invasive fungal infections.

Fungal infections have become more than just Epidemiological data published in Microbial Cell indicates that a rise in severe fungal infections has resulted in over 150 million cases annually and almost 1.7 million fatalities globally.

Skin contact with microorganisms found in soil or on hard surfaces, such as common shower facilities, or exposure to infected pets, can result in fungal infections known as dermatomycoses. Rashes, itching, burning and skin irritation are among the symptoms of fungal infection.

Thomas McCormick and Mahmoud Ghannoum, professors of dermatology at the Case Western Reserve University School of Medicine and affiliated with University Hospitals Cleveland Medical Center, explained extent of the problem. “This is not just an issue that affects individual patients,” McCormick said.

“The World Health Organization has recognised it as a widespread threat that has the potential to impact entire healthcare systems if left unchecked.”

Based on their findings, the researchers issued precautions and a “call to action” for the medical community to help protect people from multidrug-resistant fungi, starting with awareness and education.

“Healthcare providers must prioritise the use of diagnostic tests when faced with an unknown fungal infection,” Ghannoum said.

“Early detection can make all the difference in improving patient outcomes.”

Patients treated with medications to protect the immune system after cancer and transplant procedures are more vulnerable to fungal infections – making them especially more vulnerable to infections from drug-resistant fungi, the researchers said.

The emergence of multidrug-resistant fungal species, such as Candida auris and Trichophyton indotineae, is especially troubling and requires urgent attention, they reported.

In a study recently published in Emerging Infectious Diseases, Ghannoum’s research team and the Centers for Disease Control and Prevention (CDC), detailed a case that demonstrated Trichophyton indotineae, in addition to becoming drug-resistant, was also sexually transmissible.

To address the growing health concern, McCormick and Ghannoum suggest several measures:

  • Increased awareness and education: Raising awareness in the general healthcare setting to obtain a more accurate understanding of the rise of antifungal-resistant infections.
  • Diagnostic Testing: Routine use of diagnostic tests can guide appropriate treatment strategies.
  • Antifungal Susceptibility Testing (AST): Improving insurance reimbursement rates for AST and increasing the number of qualified laboratories with the capacity to perform these tests.
  • Call to Action: Addressing the emerging challenge of antifungal resistance involves concerted efforts from healthcare professionals, researchers, policymakers and the pharmaceutical industry to develop and implement strategies for managing and preventing antifungal resistance.

“The ultimate goal of these measures,” Ghannoum said, “is to improve the quality of patient care by ensuring effective treatment and preventing further escalation of the problem.”

Source: Case Western Reserve University

Plant Compound could Prove to be a Potent Tool against Candida

Photo by CDC on Unsplash

A new study published in the journal ACS Infectious Diseases has found that a natural compound found in many plants inhibits the growth of drug-resistant Candida fungi – including its most virulent species, Candida auris, an emerging global health threat.

Led by Emory University researchers, the study used in vitro experiments that showed that the natural compound, a water-soluble tannin known as PGG, blocks 90% of the growth in four different species of Candida fungi. The researchers also discovered the mechanism by which PGG inhibits the growth: It grabs up iron molecules, essentially starving the fungi of an essential nutrient.

By starving the fungi rather than attacking it, the PGG mechanism does not promote the development of further drug resistance, unlike existing antifungal medications. In vitro testing also showed minimal toxicity of PGG to human cells.

“Drug-resistant fungal infections are a growing healthcare problem but there are few new antifungals in the drug-development pipeline,” says Cassandra Quave, senior author of the study and assistant professor at Emory University. “Our findings open a new potential approach to deal with these infections, including those caused by deadly Candida auris.”

C. auris is often multidrug-resistant and has a high mortality rate, leading the Centers for Disease Control and Prevention (CDC) to label it a serious global health threat.

“It’s a really bad bug,” says Lewis Marquez, first author of the study and a graduate student in Emory’s molecular systems and pharmacology programme. “Between 30 to 60% of the people who get infected with C. auris end up dying.”

An emerging threat

Some species of Candida, a yeast commonly found on the skin or in the digestive tract, can cause infection, which can be invasive and life-threatening. Immunocompromised people, including many hospital patients, are most at risk for invasive Candida infections, which are rapidly evolving drug resistance.

In 2007, the new Candida species, C. auris, emerged in a hospital patient in Japan. Since then, C. auris has caused health care-associated outbreaks in more than a dozen countries around the world with more than 3000 clinical cases reported in the United States alone.

A ‘natural’ approach to drug discovery

Quave is an ethnobotanist, studying how traditional people have used plants for medicine to search for promising new candidates for modern-day drugs. Her lab curates the Quave Natural Product Library, which contains 2500 botanical and fungal natural products extracted from 750 species collected at sites around the world.

“We’re not taking a random approach to identify potential new antimicrobials,” Quave says. “Focusing on plants used in traditional medicines allows us to hone in quickly on bioactive molecules.”

Previously, the Quave lab had found that the berries of the Brazilian peppertree, a plant used by traditional healers in the Amazon for centuries to treat skin infections and some other ailments, contains a flavone-rich compound that disarms drug-resistant staph bacteria. They had also found that the leaves of the Brazilian peppertree contain PGG, a compound that has shown antibacterial, anticancer and antiviral activities in previous research.

A 2020 study by the Quave lab, for instance, found that PGG inhibited growth of Carbapenem-resistant Acinetobacter baumannii, a bacterium that infects humans and is categorised as one of five urgent threats by the CDC.

The Brazilian peppertree is a member of the poison ivy family. “PGG has popped up repeatedly in our laboratory screens of plant compounds from members of this plant family,” Quave says. “It makes sense that these plants, which thrive in really wet environments, would contain molecules to fight a range of pathogens.”

Experimental results

The Quave lab decided to test whether PGG would show antifungal activity against Candida.

In vitro experiments demonstrated that PGG blocked around 90% of the growth in 12 strains from four species of CandidaC. albicans, multidrug-resistant C. auris and two other multidrug-resistant non-albicans Candida species.

PGG is a large molecule known for its iron-binding properties. The researchers tested the role of this characteristic in the antifungal activity.

“Each PGG molecule can bind up to five iron molecules,” Marquez explains. “When we added more iron to a dish, beyond the sequestering capacity of the PGG molecules, the fungi once again grew normally.”

Dish experiments also showed that PGG was well-tolerated by human kidney, liver and epithelial cells.

“Iron in human cells is generally not free iron,” Marquez says. “It is usually bound to a protein or is sequestered inside enzymes.”

A potential topical treatment

Previous animal studies on PGG have found that the molecule is metabolised quickly and removed from the body. Instead of an internal therapy, the researchers are investigating its potential efficacy as a topical antifungal.

“If a Candida infection breaks out on the skin of a patient where a catheter or other medical instrument is implanted, a topical antifungal might prevent the infection from spreading and entering into the body,” Marquez says.

The researchers will bext test PGG as a topical treatment for fungal skin infections in mice.

Meanwhile, Quave and Marquez have applied for a provisional patent for the use of PGG for the mitigation of fungal infections.

“These are still early days in the research, but another idea that we’re interested in pursuing is the potential use of PGG as a broad-spectrum microbial,” Quave says. “Many infections from acute injuries, such as battlefield wounds, tend to be polymicrobial so PGG could perhaps make a useful topical treatment in these cases.”

Source: Emory University

An Unexpected Ally: Pathogen Enhances Antifungal Drug

Scanning Electron Micrograph of Pseudomonas aeruginosa.
Credit: CDC/Janice Carr

While pathogens usually work against drug treatments, sometimes, they can actually strengthen them, according to a new University of Maine study published in the journal Infection and Immunity.

Polymicrobial infections, which are a combination of bacteria, viruses, fungi and parasites, are challenging to treat because it is not well understood how pathogens interact during infection and how these interactions affect the drugs treating them.

In a study published in Infection and Immunity, University of Maine researchers examined two common pathogens that often occur at similar sites, particularly in cystic fibrosis and mechanically ventilated patients: Candida albicans and Pseudomonas aeruginosa.

Candida is the fourth most common hospital-acquired pathogen, and many antifungal agents only slow it rather than kill it outright. Meanwhile, P. aeruginosa infects 90% of all adult cystic fibrosis patients. Combined, C. albicans and P. aeruginosa cause more serious disease in cystic fibrosis and ventilated patients.

The researchers investigated the effectiveness of the antifungal drug fluconazole in vitro and then during infection of the zebrafish with both pathogens. Fluconazole slows fungal growth, but Candida can become tolerant to the drug and not only survive, but also evolve tolerance that leads to therapy failure and, potentially, death.

The results showed that P. aeruginosa in fact works with fluconazole to eliminate drug tolerance and clear the C. albicans infection in the culture and the zebrafish.

“Polymicrobial infections are challenging to treat not only because of the lack of understanding of how invading microorganisms interact but also because we don’t know how these interactions affect treatment efficacy. Our work demonstrates that polymicrobial interactions can indeed affect treatment efficacy and, most importantly, it highlights the importance of nutrient availability in the environment -; such as iron in our study -; and how it modulates treatment efficacy,” explained Siham Hattab, lead author of the study.

What’s more, the bacteria also enhance the drug’s ability against a second pathogenic Candida species that tends to be more resistant to the drug.

The increased effectiveness of the drug suggests to the researchers that there is still much more to learn about how current drugs work when targeting these dangerous and complex polymicrobial infections.

Senior study author, Robert Wheeler, associate professor of microbiology said: “We are really excited to have revealed that sometimes drugs against fungal infection can work even better in a more ‘real-world’ situation than in the test tube. There is still a lot to learn about how pathogens interact during infection, and it will be interesting to see how the bacteria manage to work with the drugs to target Candida.”

Source: University of Maine

Candida Glabrata Genome Yields Secrets of Virulence and Drug Resistance

Genetics
Source: Pixabay

A project sequencing the Candida glabrata genome has revealed insights into the pathogenic fungus’s virulence and resistance, which researchers found to have been enhanced by transmission through humans as they travel between continents. The project’s findings appear in Genetics

C. glabrata is an opportunistic human fungal pathogen that causes superficial mucosal and life-threatening bloodstream infections in individuals with a compromised immune system. It most commonly affects the urinary tract, genitals, mouth, and the bloodstream. If it is not caught, these infections can become deadly.  It is also very resistant to certain antifungal drugs, so understanding why resistance occurs is key to knowing how to treat it effectively. 

Using samples from eight hospitals in Scotland to sequence the genome of C. glabrata, new insights on the species were made. This includes information on how it reproduces and its genetic diversity. Genes increasing its infectivity also confer an advantage for survival, and the drug-resistance genes often evolve within patients.

These findings provide scientists with an advantage in treating fungus, allowing research to focus in ways that were not possible before. It also helps aid understanding on how the pathogen spreads, which is important to identifying infections.

Dr Rhys Farrer, one of the Principal Investigators at the MRC Centre for Medical Mycology at the University of Exeter, said: “Our study sheds new light on the genetic diversity of Candida glabrata. We have demonstrated that this deadly human fungal pathogen is being spread between continents, probably by humans, and recombining to form new populations, which is likely contributing to its high virulence and increasing drug resistance.”

Source: University of Exeter

The Emerging Treatment-resistant Fungus Threat

Professor Rodney E. Rohde, a public health and clinical microbiology expert at Texas State University, warned in article for The Conversation of the growing threat of fungal resistance — a problem drawing much less attention than antibiotic resistance. 

 Athlete’s foot, thrush, ringworm and other ailments are caused by fungi, and some are serious risks to health and life. Among these is Candida auris, a pathogenic fungus. Fungi generally have not caused major disease, so there is a lack of funding in this area and there are limited antifungal agents that can treat C. auris.

Most fungal infections around the world are caused by the genus Candida, particularly the species called Candida albicans. But there are others, including Candida auris, which gets its name ‘auris’, Latin for ear, because it was first identified from an external ear canal discharge in 2009.

Candida normally lives on the skin and inside the body, such as in the mouth, throat, gut and vagina, without causing any problems. It exists as a yeast and is thought of as normal flora, harmless microbes. However when the body is immuno-compromised, these fungi become opportunistic pathogens, something happening around the world with multidrug-resistant C. auris.

The threat of Candida auris

C. auris infections, or fungaemia, have been reported in 30 or more countries. They are often found in the blood, urine, sputum, ear discharge, cerebrospinal fluid and soft tissue, and occur in people of all ages. According to the US Centers for Disease Control, the mortality rate in the US has been reported to be between 30% to 60% in many patients who had other serious illnesses. In a 2018 review of research on the global spread of the fungus, researchers estimated mortality rates of 30% to 70% in C. auris outbreaks among critically ill patients in intensive care.

Recent surgery, diabetes and broad-spectrum antibiotic and antifungal use are risk factors. Furthermore, immuno-compromised patients are at greater risk than those with healthy immune systems.

C. auris can be difficult to identify with conventional microbiological culture techniques, which leads to frequent mis-identification and under recognition. This yeast is also known for its tenacity to easily colonise the human body and environment — including medical devices. People in nursing homes and patients with catheters, on ventilation etc seem to be at highest risk.

The CDC has set C. auris infections at an “urgent” threat level because 90% are resistant to at least one antifungal, 30% to two antifungals, and there are some resistant to all three available classes of antifungals. This multidrug resistance has led to outbreaks in health care settings, especially hospitals and nursing homes, that are extremely difficult to control.

The double threat of COVID and C. auris

For hospitalised COVID patients, antimicrobial-resistant infections may be a particularly devastating risk. The mechanical ventilators often used to treat serious COVID are breeding grounds and highways for entry of environmental microbes like C. auris. Further, according to a September 2020 paper, hospitals in India treating COVID have detected C. auris on surfaces including “bed rails, IV poles, beds, air conditioner ducts, windows and hospital floors.” The researchers termed the fungus a “lurking scourge” amid the COVID pandemic. Termed ‘white fungus’, these fungal infections typically arise a week to 10 days after being in the ICU.

The same authors reported in a November 2020 CDC article that of 596 COVID-confirmed patients in a New Delhi ICU from April 2020 to July 2020, 420 patients required mechanical ventilation. Of these, 15 were infected with candidemia fungal disease and eight of those infected (53%) died. Ten of the 15 patients were infected with C. auris; six of them died (60%).

How to deal with this?

With fewer and fewer antifungal options,  CDC is recommending a focus on preventing C. auris infections. This involves better hand hygiene and improving infection prevention and control in medical care settings, judicious and thoughtful use of antimicrobial medications, and stronger regulation limiting the over-the-counter availability of antibiotics.

Source: The Conversation

Journal information: Anuradha Chowdhary et al, The lurking scourge of multidrug resistant Candida auris in times of COVID-19 pandemic, Journal of Global Antimicrobial Resistance (2020). DOI: 10.1016/j.jgar.2020.06.003

Antifungal Compound Discovered in Ant Farms

Researchers in Brazil have discovered an antifungal compound by bacteria living in ant farms, which may have medical applications.

In the fungal farms where attine ants tend as their food source, Pseudonocardia and Streptomyces bacteria produce metabolites which shield the crop against pathogens. Curiously, these metabolites vary across geographic locations.

Attine ants are a type of ant which grow and harvest fungus for food, and are only found in the Western Hemisphere. They first evolved from a common Amazonian ancestor some 50 million years ago, giving rise to some 200 species of ants spread across South and Central America, which share common farming practices. The bacteria at these farms have a symbiotic relationship where they defend against fungi such as Escovopsis in exchange for food.

These metabolites vary considerably, suggesting a fragmented history. Searching a number of ant nests spread across a large geographical area, the researchers discovered that two thirds of the Pseudonocardia strains were producing the same metabolite. They named this newly discovered metabolite attinimicin.The study was the first one where a common, specialised metabolite produced by ant-associated bacteria was found across geographic locations.

Attinimicin inhibited fungal parasites while not harming the fungal crop, but only in the presence of iron. It proved as effective in treating Candida albicans infections in mice as a clinically used azole-containing antifungal. This means that the metabolite could have clinical applications. Attinimicin was shown to have a similar structure to two other metabolites produced by Streptomyces, suggesting the responsible genes have a common evolutionary origin.

Source: News-Medical.Net

Journal information: Fukuda, T.T.H., et al. (2021) Specialized Metabolites Reveal Evolutionary History and Geographic Dispersion of a Multilateral Symbiosis. ACS Central Science. doi.org/10.1021/acscentsci.0c00978.