Category: Mental Health

‘We Cannot Ban Our Way out of a Youth Mental Health Crisis’

Social media bans for teenagers lack evidence and pose risks, scientists say

Photo by Vlad Patana on Unsplash

Bans on teenagers’ social media use are gathering pace worldwide. Their proponents claim that social media bans will improve young people’s mental health, but what evidence supports these claims? In their new Frontiers in Developmental Psychology article, Dr Monika Neff Lind and her co-authors argue that there is no solid scientific evidence behind these bans, and reason to believe they could backfire. In this guest editorial, Neff Lind explains why she and her colleagues doubt that social media bans will work, and how bans should be evaluated to determine whether they have any positive effects.

By Monika Neff Lind, PhD

In December 2025, Australia banned young people under 16 from having social media accounts. France, Greece, Spain, Denmark, Malaysia, Norway, India, Egypt, Canada, Türkiye, and the United Kingdom are hot on their heels. French president Emmanuel Macron said, “Banning social media for those under 15: this is what scientists recommend.” American senator Brian Schatz, author of the Kids Off Social Media Act, said, “Studies have revealed that when children and teens reduce or eliminate exposure to social media for longer than a month, their mental health benefits.” Proponents of youth social media bans claim that we have strong scientific evidence showing that bans will improve teenagers’ wellbeing.

As a clinical psychologist and parent, I would be thrilled if this were true, but it is not. We do not know how social media bans will affect youth because we have never studied that question. Let me explain.

Searching for evidence

When we want to test claims like ‘banning social media improves youth wellbeing’, scientific experiments are one of our most powerful tools to figure out what is causing something to happen. In experiments testing the effects of social media restriction on wellbeing, we randomly assign people to at least two groups: one quits using social media for a period of time and the other is the control or comparison group, which continues to use social media as usual. Given the strength of ban proponents’ claims, my co-authors and I were curious to know how strong the experimental evidence supporting their position was. In our new study, we collected and reviewed all of the experiments that have tested whether social media restriction improves wellbeing, and we were shocked by what we found.

Not a single social media restriction experiment has included people under the age of 16. We do not know how social media bans will affect the young people being targeted by them because we have never tested this with them!

To be fair, sometimes strong evidence in adults warrants making the leap to apply the same conclusions to teenagers. But even that leap is not justified here. The experiments with adults show weak, null, and mixed effects, with 40% of experimental studies showing harmful effects (eg, decreased life satisfaction and increased loneliness) or no effects of social media restriction. So even when adults are told repeatedly that social media is bad for their mental health and that giving it up will help, we find, on average, few to no benefits.


Read and download the original article


Unintended consequences?

There is also good reason to believe that bans may backfire. First, enforcing a youth social media ban raises major ethical concerns. Enforcement efforts invade people’s privacy and are likely to hurt marginalized people more. For example, the technology that determines age based on selfie uploads makes more mistakes with young faces and people of color. Banned youth may also miss out on important resources and communications provided via social media, as schools, clubs, and most other youth-serving organizations use social media as a main form of communication.

What happens when enforcement efforts fail? Many young people will circumvent bans by creating fraudulent ‘adult’ accounts or lurking anonymously. They will retain access to social media without any of the benefits of parental controls or content filters enabled by youth accounts. The vast majority of young people oppose youth social media bans, and teens are well known for their defiance of top-down edicts that disregard their needs. Expect more conflict between teens and caregivers, not less.

To recap, we don’t know how social media bans will affect teens, and the bans may backfire. Yet the bans are still happening! Like other policies that consume resources, political capital, and time, it is imperative for governments to evaluate these actions by funding comprehensive assessments of the bans’ impacts.

What next?

The first step in measuring the impact of these bans is to determine if the bans actually change teenagers’ social media habits. Three months in, Australian authorities reported that close to 70% of social media accounts owned by people under 16 remained active.

Second, we need a careful and well-resourced plan to measure both positive well-being and mental health problems from multiple sources, including self-report, caregiver report, and objective behavioral data, to get a full picture of whether and how altered social media use affects youth.

Third, we need creative approaches to capture the real-world impacts of the bans, since true experiments are not possible and effects may be at the community as well as the individual level. For example, we could randomly assign a subset of youth (eg within a certain region) to delayed enactment of the ban. Whatever approach is taken, governments must collaborate with diverse stakeholders – including young people – to rigorously and openly evaluate potential impacts. Rushed or improvised assessment will leave room for politicization and motivated reasoning.

Big Tech has become infamous for ‘moving fast and breaking things’. Policymakers rushing to enact these bans risk repeating Big Tech’s mistakes and compounding the problems the bans are trying to solve. We cannot ban our way out of a youth mental health crisis. Rather than take things away, we should make things better.

About the author

Dr Monika Neff Lind is a clinical psychologist, science communicator, and researcher in digital mental health based at the University of California Irvine. See more of her work here.

Source: Frontiers

Postpartum Psychosis Found to Have a Substantial Genetic Component

Study finds postpartum psychosis is strongly influenced by genetics and reveals links to cholesterol metabolism, immune biology, and psychiatric disorders

Photo by Alina Matveycheva

Researchers at the Icahn School of Medicine at Mount Sinai have uncovered a substantial genetic component to postpartum psychosis, a rare but severe psychiatric illness that occurs in the days to weeks after childbirth. The findings, published May 14 in Molecular Psychiatry, provide new evidence that the condition has a substantial biological and genetic basis and may help guide future research into prediction, prevention, and treatment. 

The study, which combined whole genome sequencing with population-level family data, identified rare damaging mutations in the gene HMGCR as associated with increased risk for postpartum psychosis. The researchers also found significant genetic overlap between postpartum psychosis and bipolar disorder, schizophrenia, and several autoimmune diseases, including rheumatoid arthritis, Sjögren’s syndrome, myasthenia gravis, and Crohn’s disease. 

Postpartum psychosis affects approximately 1 in 1000 mothers and is considered a psychiatric emergency because of the elevated risk of suicide and infanticide. Symptoms can include delusions, hallucinations, severe mood changes, confusion, and disorganised behaviour. 

“Our findings show that postpartum psychosis is a biological illness with a substantial genetic basis,” said Behrang Mahjani, PhD, Assistant Professor in the Departments of Psychiatry, Genetics and Genomic Sciences and Artificial Intelligence and Human Health at the Icahn School of Medicine and senior author of the paper. “It is not a parenting failure or a personal weakness, and women affected by it deserve the same medical seriousness afforded to other severe illnesses.”  

This condition has historically been understudied, particularly at the genetic level, and we hope these results help move the field toward a more mechanistic understanding of why some women become vulnerable during the postpartum period.” 

The study estimated that approximately 55 percent of risk for postpartum psychosis is attributable to inherited genetic factors based on family data, while whole genome sequencing analyses estimated heritability from common genetic variants at approximately 46 percent. 

Researchers were particularly surprised by the identification of HMGCR, which encodes the rate-limiting enzyme in cholesterol biosynthesis. The study also revealed broader-than-expected overlap between postpartum psychosis and immune-related conditions. Researchers say the findings are consistent with longstanding clinical observations that autoimmune disease activity often changes during the postpartum period and suggest that immune biology may play a role in the illness. 

“Cholesterol biosynthesis was not a pathway we had anticipated, but once HMGCR emerged, the biology became highly coherent in light of the changing dynamics of cholesterol during and after pregnancy, because cholesterol serves as the precursor for steroid hormone synthesis and prior reports linking low serum cholesterol to first episode psychosis and suicidal behaviour,” said Dr Mahjani. “The postpartum period is marked by dramatic hormonal and metabolic shifts, and this gene sits directly within pathways affected during that transition.” 

The research, with analyses performed by Seulgi Jung, PhD, a postdoctoral fellow in the Mahjani Lab at Mount Sinai, is the first study to apply whole genome sequencing to postpartum psychosis, allowing investigators to examine rare damaging mutations across the genome rather than focusing solely on common genetic risk variants. The team combined data from Swedish national health registers with genomic information from the National Institutes of Health’s All of Us Research Program, enabling researchers to study one of psychiatry’s rarest and least understood conditions at an unprecedented scale. 

“It is important to understand that multiple genes are involved in postpartum psychosis and that HMGCR can be used as a research tool for further scientific discovery,” said Veerle Bergink, MD, PhD, Director of the Women’s Mental Health Research Center at Mount Sinai and an author of the paper.  

Future work will focus on expanding sample sizes and improving ancestral diversity. The team is now pursuing functional studies of HMGCR and other candidate genes in neuronal and immune cell models relevant to pregnancy and the postpartum period. Researchers also plan to integrate genetic findings with hormonal and immunological changes associated with childbirth to better understand why the illness emerges during such a tightly defined window. 

“In the long term, our goal is to understand postpartum psychosis well enough to predict it, prevent it where possible, and develop treatments that target the underlying biology rather than symptoms alone,” said Dr Bergink. 

The investigators also emphasized the importance of large-scale collaborative research infrastructure in enabling discoveries for rare conditions. 

“This work would not have been possible without the NIH’s All of Us Research Program and the participants who contributed their data,” said Dr. Mahjani.  “For rare and historically neglected illnesses such as postpartum psychosis, equitable access to large genomic datasets is essential for scientific progress.” 

Source: Mount Sinai

Why Lithium is Still the Gold Standard in Treating Bipolar Disorder

Angel Soler Gollonet/Shutterstock

Julia E. Marquez Arrico, Universitat de Barcelona

According to recent data from the Global Bipolar Cohort, only 29% of people with bipolar disorder are prescribed lithium. Despite being the “gold standard” for treating this mental health condition, we often prioritise perceptions over scientific reality, and neglect the best available treatment.

Lithium is not some complex molecule synthesised in a state-of-the-art laboratory. It is just an element, the third in the periodic table, and ever since the Australian psychiatrist John Cade discovered its therapeutic properties in 1949, it has maintained a relevance that no other psychotropic drug has been able to match.

This longevity is not a relic of the past, but a reflection of its clinical robustness. Despite decades of research and the constant emergence of new drugs, no alternative has shown comparable efficacy in the long-term prevention of manic and depressive episodes in bipolar disorder.

According to a review published in 2024, lithium is still “the mainstay treatment of mood disorders in general and in bipolar disorder specifically”. It is also the benchmark against which all other treatment options are compared, both for stabilising mood and reducing the risk of relapse.

It is the only mood stabiliser with proven efficacy in treating mania and depression, as well as in preventing relapses. Furthermore, recent studies confirm that it may also have neuroprotective properties, from the modulation of cellular pathways involved in neural plasticity to potential effects in preventing mild cognitive impairment and dementia.

These characteristics explain why international guidelines still rank it as the first-line treatment for bipolar disorder. A consensus published in 2025 stated that it should be prescribed more frequently, contrary to the unfounded reservations that still persist in clinical practice.

Suicide reduction

Above all, there is one aspect that sets lithium apart from other psychopharmaceutical drugs: its ability to reduce the risk of suicide. No other medication has demonstrated such a consistently protective effect.

A 2024 review highlighted that, despite the methodological difficulties in studying this statistically rare event, the body of evidence from clinical trials, observational studies and meta-analyses all points in the same direction: lithium reduces mortality and suicide attempts.

This is likely due to its ability to reduce impulsivity, stabilise extreme mood swings and prevent depressive relapses, all of which create the moments of greatest risk.

Beyond episodic treatment

Current research is also looking into lithium’s ability to alter the course of bipolar disorder. Not only does it stop episodes, but it also protects the brain, and evidence suggests that, unlike some antipsychotics, it improves brain connectivity and preserves verbal fluency.

In fact, there is very interesting data suggesting that it could reduce the risk of dementia by up to 50%. Even residual levels in drinking water appear to have a protective effect at a population level. Lithium is, in short, a molecule with exceptional neuroprotective potential.

But the neuroprotective effects do not stop there. Recent studies also suggest that lithium stimulates the production of brain-derived neurotrophic factor, a protein essential for neuronal survival and growth that is often reduced in patients with bipolar disorder.

In other words, it doesn’t just prevent the brain from deteriorating – it actively helps it to heal.

Blood monitoring and ‘precision medicine’

It is often argued that the need for blood tests to monitor lithium levels (the optimal therapeutic range is 0.6-0.8 millimoles per litre) is an inconvenience. However, from a rigorous clinical perspective, this monitoring is a safeguard, not a risk. It is what allows the dose to be adjusted to the exact biology of each patient, a form of “precision medicine” that we were already practising long before the term became fashionable.

We should also remember that many commonly used medicines – from anticoagulants to immunosuppressants – require the same kind of laboratory monitoring, yet they are not considered dangerous for that reason.

What lithium management requires is not fear, but rigour. So why is it prescribed less often? The answer is complex. It is partly due to pressure from the pharmaceutical industry to promote new, patentable molecules – lithium, being a natural element, cannot be patented. There is also a degree of clinical reluctance due to its narrow therapeutic window – it needs to be carefully controlled to ensure a safe yet effective dose.

However, international guidelines are clear: lithium should be the first choice. We cannot overlook it in favour of less effective alternatives simply because they appear more modern. This kind of mistake should not influence clinical practice.

Newer is not always better

Good psychopharmacology is not a question of chasing the latest developments, but of using the most appropriate treatment for each individual at every stage of their illness.

Lithium has a proven track record that spans decades, across areas that no other mood stabiliser can address simultaneously. It controls manic and depressive episodes, prevents suicide, and provides active neuroprotection. Three areas, in one single drug.

This does not mean it is right for absolutely everyone. Good psychopharmacology should always push back against fads and dogma alike, but discarding lithium’s use without ever seriously considering it deprives patients of an option that is, according to the evidence, categorically the best therapeutic option.

Our challenge today is not to reinvent the wheel, but to understand how best to use the therapeutic tools we already have. A drug doesn’t become outdated just because time has passed; it becomes outdated when new evidence emerges and supersedes it. In the case of lithium, new evidence only confirms its value.

Julia E. Marquez Arrico, Professora Lectora, Universitat de Barcelona

This article is republished from The Conversation under a Creative Commons license. Read the original article.

Widely Used Food Preservative Implicated in Recent Uptick in UK Suicide Deaths

Disproportionately high number of cases among Gen Z, Millennials, and males

Photo by Andrew Neel on Unsplash

A chemical widely used in food preservation is implicated in an uptick in recent UK deaths by suicide, with a disproportionately high number of cases among young people and boys/men, finds a comprehensive analysis of available data for the period 2019-24, published in the open access journal BMJ Public Health.

There’s now an urgent public health need to review unrestricted access to this source, to avoid further preventable deaths, say the researchers.

Rates of death by suicide have been falling across the UK since the early 1990s. But there is some evidence of a recent uptick in the numbers, coinciding with increasing reports of suicide associated with sodium nitrite poisoning around the world, they explain. 

To find out if this form of poisoning is implicated in deaths by suicide in the UK, the researchers retrospectively analysed the details of cases submitted by coroners, forensic pathologists, and police forces between March 2019 and August 2024 to the primary UK laboratory that assesses nitrite and its oxidised metabolite, nitrate, in postmortem samples.

During this period, the laboratory received 274 samples from 201 cases of suspected deliberate or unintentional poisoning from across the UK, Ireland, and Gibraltar. 

Most of these cases came from Greater London, South East England, Ireland, and the Midlands, although these figures may reflect coroner awareness rather than true incidence, caution the researchers.

The number of cases rose substantially after 2019, the first year samples were received for nitrite/nitrate assessment.

The final analysis included only the data for which coroners granted permission for use – 82% (164) of the cases received between 2019 and 2024. 

The average age of these cases was 28, but ranged from 14–74 for males and 17–82 for females. Nearly three quarters (71%) of all the cases were among younger generations: Gen Z (33%; born 1981-96); and Millennials (38%; born 1997-2012, but listed up to 2005 to account for a separate category of minors, as 4% of cases were among those under the age of 18). 

Overall, there were more men (109) than women (52) among the cases. And more than half of the cases in each generation were men, except for the oldest classified generation (Silent, born 1928-45), where the only case was that of a woman.

Levels of nitrite and nitrate found in the blood samples were 100 times higher than would be expected physiologically in 87% of cases, suggesting that swallowing the chemical was intentional, say the researchers.

The researchers highlight some caveats to their findings, including that because nitrite and nitrate analysis isn’t routinely mandated for all suspected suicides, it’s not clear exactly how many such deaths are caused by this chemical. 

“It is therefore likely that the cases included here represent a substantial underestimate of the actual incidence. Secondly, the interval between death and sample receipt varied considerably, introducing the possibility that delays may have affected the accuracy of the biochemical measurements,” they say.

Nevertheless, the observed rise in cases among predominantly young people, who tend to be tech savvy, is concerning, they suggest. 

“Intentional poisoning has contributed to these recent increases, and at least in the USA, this
rise has been partly attributed to the use (and availability) of sodium nitrite,” they point out.

“This trend has emerged alongside freely accessible online information detailing how sodium nitrite can be obtained and used, disseminated both under the guise of providing mental health support and for more explicitly harmful purposes,” they explain.

Their findings warrant urgent action, they suggest. “Collectively, these findings establish unequivocally that use of sodium nitrite in the UK as a method of suicide is both substantial and concerning,” they write.

“Our data provide strong support for the suggestion that the improved digital literacy of younger people enables access to illicit online material promoting suicide practices and lends further support for calls for tighter legislation to prevent availability of such information in online forums,” they add.

In the meantime, steps to mitigate the effects of this type of poisoning, such as the provision of an antidote (methylthioninium chloride kits) in ambulances would be “a simple and cost effective timely method to prevent the devastating consequences of ingestion,” they point out.

*Lead researcher, Professor Amrita Ahluwalia, comments: “This is an extremely difficult subject to talk about, and we appreciate the impact that this might have on all those affected by suicide. 

“What our research shows is deeply upsetting. But it makes clear why urgent steps are needed to regulate access to this chemical and to reduce the spread of harmful information about it online.”

For anyone struggling, in South Africa SADAG’s 24 hour hotline can be contacted on 0800 567 567. In the UK and Ireland, Samaritans can be contacted on tel 116 123. In the US, call or text the National Suicide Prevention Lifeline on 988, chat on 988lifeline.org, or text HOME to 741741 to connect with a crisis counsellor. In Australia, the crisis support service Lifeline is 13 11 14. Other international helplines can be found at www.befrienders.org

Source: The BMJ Group

Sedatives in Pregnancy Not Linked to Psychiatric Disorders in Children

Findings offer reassurance to clinicians and pregnant women, say researchers 

Photo by SHVETS production

A large South Korean study published by The BMJ finds no increased risk of psychiatric or neurodevelopmental disorders, such as ADHD and autism, in children whose mothers used sedative drugs (benzodiazepines or Z-hypnotics) during pregnancy.

Benzodiazepines and Z-hypnotics are used to alleviate anxiety and insomnia, which are among the most common conditions during pregnancy.

Previous studies have examined the short term safety of benzodiazepine and Z-hypnotic use in pregnancy, but evidence on their psychiatric and neurodevelopment effects in children remains scarce.

To fill this evidence gap, researchers used South Korea’s National Health Information Database to track nearly 3.8 million children born between 2010 and 2022.

Pregnancies exposed to benzodiazepines or Z-hypnotics were compared with unexposed pregnancies and with women who had used these drugs before but not during pregnancy (past users).

Twelve specific neurodevelopmental and general psychiatric disorders were assessed, including substance use disorder, schizophrenia, personality disorder, intellectual disability, autism, ADHD, and behavioural disorder.

Factors, such as mother’s age, income, underlying conditions and other medication use were also taken into account.

Among the 3 809 949 children, 94,482 (2.5%) were exposed to benzodiazepines or Z-hypnotics during pregnancy, 3 715 467 were unexposed, and 147 307 were born to past users.

During the tracking period of up to 14 years, a total of 10 060, 311 997, and 15 645 events occurred in the exposed, unexposed, and past user groups, respectively.

Overall, rates of psychiatric disorders were slightly higher (19.2%) in exposed children compared with 13.8% in unexposed children and 16.5% in the past user group.

However, these associations were no longer significant when the researchers used sibling analysis to disentangle drug effects from shared family, genetic, and environmental factors, and no increased risk was found for individual psychiatric disorders.

Further analyses were generally consistent with the main findings, although some estimates, such as exposure in early and late pregnancy, and longer durations of Z-hypnotic use specifically, remained modestly elevated in certain groups.

This is an observational study, so can’t establish cause and effect, and the researchers acknowledge that a prescription may not always reflect actual ingestion and their follow-up period may be insufficient to capture late onset conditions such as schizophrenia or personality disorders. What’s more, this study was not designed to assess the overall safety of these drugs but specific psychiatric outcomes in children.

However, use of a large, nationally representative database and rigorous methods to overcome confounding suggest the results withstand scrutiny.

As such, they say this study suggests “no substantial evidence that prenatal exposure to benzodiazepines or Z-hypnotics increases the risk of psychiatric disorders in children.”

Although these findings provide reassurance about neuropsychiatric safety, further research is needed to clarify the modest elevations seen in some analyses and help inform discussions when considering sedative therapy in pregnancy, they add.

In a linked editorial, researchers agree that this evidence is reassuring, but this does not mean that sedatives should be prescribed without caution.

Clinicians should be mindful of signals around prolonged use and late pregnancy exposure, while also balancing the risks of untreated maternal psychiatric illness, they write.

However, they conclude that this study “offers a compelling example of how observational research can generate reliable estimates of prenatal drug safety.

Source: The BMJ Group

Research Identifies the ‘Sweet Spot’ for ADHD Dosage

Photo by Towfiqu barbhuiya

Researchers have identified the best dosage for each ADHD medication using data from thousands of people with the condition.

A new study published 14 May in the Lancet Psychiatry provides the most comprehensive view of dosage effects for five commonly used medications for ADHD.

To help patients and clinicians choose the right dosage, the international research team led by Professor Samuele Cortese from the University of Southampton has also developed a free online tool based on the findings.

The research was funded by the National Institute for Health and Care Research (NIHR).

Attention Deficit Hyperactivity Disorder (ADHD) is one of the most common neurodevelopmental conditions, affecting about five per cent of school-age children and two to three per cent of adults.

Medication is a key part of treatment, and prescriptions have increased substantially in recent years. However, most clinical guidelines provide limited guidance on the most effective dosages.

Finding the right dose is important to avoid dosages that are too low to be effective or too high, causing unwanted side effects. To identify this dosage ‘sweet spot’, the research team analysed data from 113 clinical trials, including more than 25 000 participants.

They used an advanced method called dose–effects network meta-analysis, which allowed them to estimate how different doses of each medication affect both effectiveness and side effects.

The results show that patterns differ between medications and age groups.

Dr Mikail Nourredine from the University of Lyon, first author of the study, said: “Overall, our findings suggest that clinicians should avoid using doses that are too low to be effective. If symptoms are not well controlled, the dosage may need to be increased.

“We also found no evidence that going beyond the licensed maximum doses improves average effectiveness, and higher doses are usually linked to more side effects. However, our results derive from group averages. Specific individuals with ADHD may benefit from and tolerate well unlicensed doses.”

Evidence from other studies shows that a substantial proportion of children and adolescents are prescribed low dosages without appropriate increases. That’s despite timely and adequate dose adjustments being associated with better adherence to treatment.

Professor Cortese, an NIHR Research Professor at the University of Southampton, commented: “Our study and the tool have the potential to support shared decision-making between clinicians, patients, and families when choosing the best dose. It is not only a clinician’s decision – patients and caregivers should be involved.

“The tool helps show what can be expected from each dose so that the patient knows why that particular dose has been chosen. We are continuing research to further personalise these recommendations based on individual patient characteristics.”

The study Pharmacological interventions for ADHD: a systematic review and dose-effect network meta-analysis is published in The Lancet Psychiatry and is available online.

Source: University of Southampton

Cannabis and Tobacco Co-use Increases Psychosis Chances in High-risk Cohorts

Results highlight concern about co-use, a growing trend that has been understudied until now

Photo by Thought Catalog on Unsplash

A new multisite study published May 12 in Nature Mental Health found that using cannabis and tobacco together increases the risk of developing psychotic disorders like schizophrenia among those considered high risk.  

Researchers led by Heather Ward, MD, assistant professor of Psychiatry and Behavioral Sciences and director of Neuromodulation Research at Vanderbilt Health, analysed data from more than 1,000 participants in the North American Prodrome Longitudinal Study, which tracks individuals at “clinical high risk” for psychosis. These individuals often experience mild or early symptoms but have not yet developed a full psychotic disorder.  

“The prevalence of cannabis and tobacco use, known as ‘co-use,’ has been rising in the general population for the past several decades, while exclusive tobacco use has declined and exclusive cannabis use has been on the rise,” Ward said. “However, little is known about cannabis and tobacco co-use in adolescents at risk for psychosis.”  

Substance use patterns – tobacco only, cannabis only, co-use, other substances and no substance use – were assessed over a two-year period in 734 individuals at clinical high risk for psychosis and 278 healthy controls.   

“People with psychosis are much more likely to use cannabis and tobacco than the general population. Because of their heavy cannabis and tobacco use, people with psychosis are also disproportionately affected by the negative consequences of cannabis and tobacco use,” said Ward, who recently presented study findings at the Society of Biological Psychiatry Annual Meeting in an oral session titled, “High Stakes: Consequences of Cannabis Use in Vulnerable Populations.”  

According to Ward, in people with psychosis, tobacco use is associated with a 20-year decreased life expectancy compared to the general population, that is attributable to the medical consequences of tobacco use, such as cardiovascular disease, heart attack, stroke and lung cancer.  

“In people in their first episode of psychosis, it is estimated that 25%–50% use cannabis. Cannabis use is associated with more severe psychosis symptoms, poor response to treatment and psychiatric hospitalisations. There is even evidence that cannabis use may cause psychosis in people who are already at risk,” Ward said.  

“Tobacco and cannabis use in isolation have devastating consequences for people with psychosis, so we wanted to see if people who co-use cannabis and tobacco had more severe psychiatric symptoms and if they were at greater risk for developing psychosis in the first place.”  

The study found that regular use of either cannabis or tobacco was linked to anxiety, depression and early psychotic experiences. However, people who used cannabis and tobacco together did not show worse short-term symptoms than those using just one.  

However, the biggest difference appeared over time. Those who used cannabis heavily and tobacco lightly were almost three times more likely to develop psychosis compared to those who used neither substance.  

The results highlight concern about co-use, a growing trend that has been understudied until now. Researchers defined co-use in the study as “using substances at the same time, on the same occasion, or within a defined time frame where their effects may overlap.”  

“We found that cannabis and tobacco co-use was associated with a nearly threefold increased risk of developing psychosis in people who were already at risk,” Ward said. “There is evidence to suggest that using tobacco and cannabis together may have synergistic effects on the brain.  

“Smoking tobacco and cannabis together increases absorption of THC, the psychoactive component of cannabis. It is possible that co-use itself is contributing to the development of psychosis. However, it is also possible that the people who are going to develop psychosis anyway have an underlying predisposition to using both cannabis and tobacco.”  

Ward said it is important for both patients and clinicians to know that cannabis and tobacco co-use is a risk factor for psychosis. Stopping use of cannabis and tobacco may improve mental health symptoms, and it is possible that stopping cannabis and tobacco co-use could reduce risk of developing psychosis in the first place.  

The next step is to replicate this finding in other groups of people at risk for psychosis, and “we need to test if stopping cannabis and tobacco use reduces risk of developing a psychotic disorder,” Ward said.  

Source: Vanderbilt University Medical Center

Does 432Hz Tuning Improve your Wellbeing? A Music Psychologist Unpacks the Evidence

Photo by morefun_boy on Unsplash

Sandra Garrido, University of Sydney

If you scroll through social media for long enough, you’ll probably find videos claiming that listening to songs tuned to “A 432Hz” can provide an amazing sense of calmness or healing.

It’s even claimed that listening to music tuned to this frequency can align your internal frequencies to those of the universe. It’s an alluring idea – that simply listening to music tuned in a specific way could improve your health.

But does it have any scientific basis?

An ancient idea

Firstly, what does it even mean if songs are tuned to A 432Hz?

Hertz (or Hz) is a measurement of frequency, or the number of times sound waves vibrate per second. Sounds are transmitted as waves through the air which hit our eardrums to create the sensation of hearing. The more quickly those sound waves are vibrating, the higher the pitch of the note.

In standard concert tuning, the note A above middle C is tuned to 440Hz. A 432Hz tuning simply means the pitch of that A and all the other notes in the music are tuned a little lower than normal.

Some argue 432Hz is closer to natural harmonic frequencies than 440Hz and that using this tuning is therefore better for wellbeing.

The idea that sounds or music can heal or even align us with the cosmos is not new. Long before social media, the ancient Greeks linked sound to the frequencies of the universe. Pythagoras proposed musical notes were governed by simple numerical ratios, the same ratios he believed underpinned the cosmos itself.

Later, medieval and Renaissance thinkers built on these ideas with the concept of “music of the spheres” – the idea that sound could be used to align us with the vibrations of the planets in a kind of cosmic harmony that influenced human emotions and wellbeing.

No magical effect

Although the concept of cosmic alignment is intriguing, there’s little scientific support for the idea that specific frequencies have any magical effect on wellbeing.

In one study from 2019, researchers played movie soundtracks tuned to 440 Hz to participants on one day and to 432 Hz on another day, finding that after listening to the 432 Hz tunings participants had slightly decreased heart rate and blood pressure. However, the study was limited by a very small sample and non-randomisation of participants, making it difficult to separate true frequency effects from expectancy or general relaxation responses.

Modern research suggests the effects of sound or music on wellbeing are less about any single special frequency, and more about how we perceive and interpret sound.

Some have theorised the use of frequencies that correspond to specific brainwave patterns such as delta waves (0.5–4Hz, associated with deep sleep), or alpha waves (8–12Hz, associated with relaxed wakefulness), can make the brain synchronise to those frequencies and achieve a relaxed state.

However, research in support of this theory is inconclusive. One study from 2017 found no changes in electrical activity in the brain after hearing such frequencies presented as binaural beats.

Binaural beats themselves are another form of sound that many claim can have miraculous effects on wellbeing. When two slightly different frequencies are played separately into each ear, the brain perceives a rhythmic pulse at a rate equal to the difference between the two frequencies. This is called a binaural beat.

There is some evidence that our physiological systems (such as breathing and heart rate) synchronise to any beat that we hear. This can help lower our levels of arousal or alertness.

That’s why most of us tend to be attracted to slower, calmer sounding music when we want to relax, for example, since the slower beat helps slow our breathing and heart rate and make us feel sleepier or calmer.

Focusing on your own response

Does that mean binaural beats have any special therapeutic effect? Not really.

A recent study found binaural beats can increase relaxation and alter brain activity. But crucially, similar effects were also observed with other types of moving or spatialised sounds. The authors concluded the benefits were likely driven by general auditory features rather than the binaural beats themselves.

It all comes down to individual preferences and perceptions. For example, binaural beats are frequently associated with meditation or mantras. And it could be this association which enhances the supposed wellbeing effects of binaural beats for some people.

Similarly with music tuned to A 432Hz.

Our brains tend to interpret sounds as expressions of emotional states. When humans are relaxed, our voices are usually lower in pitch than when we are excited or agitated.

Thus, notes of a lower pitch are sometimes perceived as more relaxing than notes that are higher pitched. Again, this doesn’t mean there is anything special or magical about 432Hz tunings – just that for many people, lower pitched notes seem calmer. The same effect could be achieved by listening to other music or frequencies with a lower pitch.

So while 432Hz might sound soothing to some ears, it’s not a shortcut to cosmic alignment. Rather than thinking about the numbers, focus on really becoming aware of your own response. Notice how different sounds make you feel, what slows your breathing, eases your body, or lifts your mood.

When it comes to wellbeing, what works is what works for you.

Sandra Garrido, Senior Research Fellow, School of Psychology, University of Sydney

This article is republished from The Conversation under a Creative Commons license. Read the original article.

Is It Anxiety or OCD? 2 Psychology Experts Explain the Difference

Photo by Joice Kelly on Unsplash

Emily Upton, UNSW Sydney; Black Dog Institute and Kayla Steele, UNSW Sydney

Anxiety itself is not a mental illness. It’s a normal, adaptive emotion that helps us respond to perceived threats.

Anxiety is the automatic reaction that makes you jump back when you think you’ve seen a snake while bushwalking – before realising it’s a stick.

It’s also (inconveniently) the sweaty palms and shaky voice you notice before a presentation or a first date, or the circling thoughts that keep you awake at 3am.

Most of us have ways to cope with anxious thoughts and feelings that can give us more of a sense of control. This could be checking and double-checking we’ve got the room right for our presentation, or seeking reassurance from someone we love.

But when might these behaviours fit a diagnosis of an anxiety disorder? And when could they actually be a sign of obsessive compulsive disorder (OCD)?

As clinical psychologists, we find these questions come up a lot, perhaps spurred by a recent surge of interest in OCD on social media. So what’s the difference between anxiety and OCD? And how are they treated?

Social media is full of content ‘diagnosing’ OCD and explaining how it’s different to anxiety. TikTok

When is anxiety something more serious?

“Normal” anxiety can become an anxiety disorder when fears or worry are persistent, intense and start interfering with everyday life.

About one in three people will experience an anxiety disorder at some point in their lifetime.

Among the most common are social anxiety disorder (fear in social situations), panic disorder (frequent panic attacks, and fears you’ll have another) and generalised anxiety disorder (persistent and excessive worry).

These disorders have slightly different symptoms. But all share excessive and persistent fear or worry that causes distress or leads people to avoid important parts of life including work, study or social activities.

So, what about OCD?

Although OCD involves anxiety, it is actually considered a separate disorder in the diagnostic manual used by mental health professionals.

It is possible to have both – around half to three-quarters of individuals with OCD also meet criteria for one or more anxiety disorders as well.

OCD involves obsessions, compulsions, or both. These cause significant distress or interfere with daily functioning.

Obsessions are intrusive, unwanted thoughts, images or urges. This could mean an intense fear your food is contaminated, suddenly visualising hurting someone, or a feeling that keeps entering your mind that you’ve made a serious mistake.

Compulsions are the repetitive behaviours (or mental rituals) people feel driven to perform to ease that distress, such as checking, repeating phrases, excessive hand-washing or seeking reassurance.

Many of us will occasionally experience unwanted thoughts or go back to check the oven is actually off. Keeping things tidy or being particular about routines can simply be habits that don’t cause distress.

But what makes OCD different is its severity and impact.

If obsessions or compulsions take up large amounts of time, cause you significant distress, or interfere with daily life, it may be a sign of OCD.

You can’t “spot” OCD from behaviour alone. OCD can also be invisible because many compulsions happen mentally, such as repeating phrases or counting. People with OCD may also try to hide their symptoms out of shame.

Are OCD and anxiety treated differently?

While anxiety disorders and OCD share some similarities, including repetitive distressing thoughts, the patterns and beliefs driving them are different. This means the way they’re treated will also differ.

Cognitive behavioural therapy (CBT) is one of the most effective treatments for both anxiety disorders and OCD.

For OCD, treatment often involves a specialised form of CBT called exposure and response prevention (ERP). It involves gradually facing situations that trigger distressing thoughts while resisting the urge to perform compulsions.

For example, someone with contamination fears might gradually reduce the number of times they wash their hands before eating. Over time, people learn the feared outcome does not occur, that they can tolerate their discomfort without the ritual, and that the anxiety passes on its own.

Treatment for anxiety disorders focuses on the specific fear. For generalised anxiety, for example, it involves understanding patterns of worry, challenging beliefs that keep worries going, and developing more helpful ways to respond to problems, such as brainstorming solutions and taking small actions.

Antidepressant medication (particularly selective serotonin re-uptake inhibitors, or SSRIs) can be an effective component of treatment for both anxiety disorders and OCD. A combined treatment approach of medication (SSRIs) and therapy (CBT) often leads to the best treatment outcomes, especially for severe OCD.

A final note

While it’s great mental health is being discussed more openly online and stigma is reducing, social media can also blur the line between personal experience and evidence-based information.

If something you’ve seen online has sparked curiosity about your mental health, the best next step is to talk with a qualified professional who can help you understand what you’re experiencing and what support might help.

For more information and resources about anxiety and OCD, visit the Black Dog Institute or Beyond Blue, and ReachOut or Headspace for young people.

There are lots of evidence-based online treatment programs for anxiety disorders and OCD you can access for free or low-cost, such as This Way Up, MyNewWay or Mindspot.

There are also online treatments for kids and teens with OCD and anxiety.

You can also ask your GP about a Mental Health Care Plan for Medicare-rebated psychology sessions.

Emily Upton, PhD Candidate in Psychology, UNSW Sydney; Black Dog Institute and Kayla Steele, Postdoctoral Research Fellow and Clinical Psychologist, UNSW Sydney

This article is republished from The Conversation under a Creative Commons license. Read the original article.

People with Poor Mental Health Have Worse Healthcare Experiences

Poorer mental health was associated with worse reported care and less trust in the healthcare system

Photo by Alex Green on Pexels

People with self-reported poorer mental health also report worse quality of care and lower confidence in healthcare systems, according to a study published May 5th in the open-access journal PLOS Medicine by Margaret E. Kruk from Washington University in St. Louis, U.S., and colleagues.

Rates of depression and anxiety have increased worldwide since the COVID-19 pandemic, and more people are pursuing mental health treatment as a result. However, there is limited up-to-date data describing how these individuals seek out and receive care. Detailed, population-level information can help healthcare systems meet this growing population’s needs.

To make a start on gathering this data, Kruk and her colleagues surveyed 32 419 adults in 18 high-, low-, and medium-income countries. More than 1000 people from each country responded. Participants self-reported data via the People’s Voice Survey in 2022 and 2023.

First, survey respondents self-assessed their physical and mental health (the latter including “poor,” “fair,” “good,” “very good,” and “excellent”). Then, they quantified their overall confidence in the healthcare system, their own use of healthcare services, the typical quality of care received, and their ability to manage their own mental health (a metric called patient activation).

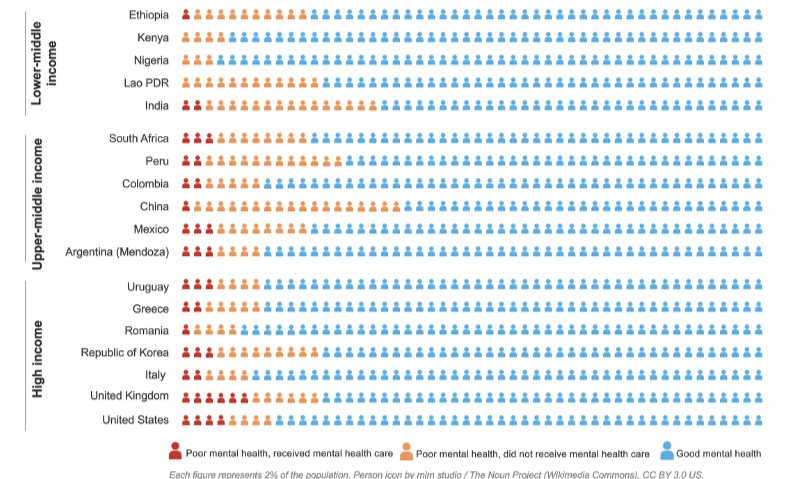
Mental healthcare receipt among people with poor mental health. Infographic displaying the weighted distribution of mental health status and care receipt. Each figure icon represents 2% of the population. Dark orange = respondents with poor/fair mental health who received mental healthcare in the past 12 months; light orange = those with poor/fair mental health who did not receive care; blue = those with good/very good/excellent mental health.

Image credit: Kruk ME, et al., 2026, PLOS Medicine, CC-BY 4.0 (https://creativecommons.org/licenses/by/4.0/)

Across all countries, respondents reporting poor mental health were more likely to report chronic illness, poorer overall health, lower patient activation, worse care quality and lower confidence in the healthcare system. Between 0.9% (Lao PDR) and 52.4% (UK) of these respondents reported receiving mental health care in the last year. Respondents in Nigeria reported the best overall mental health (4.7% people reported the lowest proportion of “poor” or “fair” mental health (4.7%), while respondents in China had the highest proportion (39.6%).

The researchers hope these results can help the countries in question – and individual healthcare systems – better serve the needs of those with poor mental health. While this is a descriptive study, the researchers posit patient activation as a potential target for elevating overall health and wellness.

The authors acknowledge that big-picture data doesn’t describe individuals’ specific experiences within the healthcare system. They suggest comparison across similar health systems and tracking system performance over time to continuously improve health services.

The authors add, “What stands out from this study is that poor mental health doesn’t exist in isolation. People reporting poor mental health were nearly twice as likely to have a chronic illness and far less likely to feel empowered to manage their own health. Health systems need to stop treating mental health in a silo and recognise that these patients are showing up across all areas of care – and often with more complex needs.”

Kruk adds, “As a research consortium working across very different health systems, we expected to find variation, and we did, in treatment access. But the experience gap was remarkably consistent: people with poor mental health had worse care, more unmet needs, and less trust in the system, regardless of where they lived. Health systems globally need to rethink how they serve this growing group, not just whether they can reach them.”

Provided by PLOS