A recent study found that factors such as a person’s birthweight, sex, ethnicity, and father’s age may affect the risk of being diagnosed with colorectal cancer at a young age. The findings are published by Wiley online in CANCER, a peer-reviewed journal of the American Cancer Society.
In the study of 1,221 people born and diagnosed with early-onset colorectal cancer – defined as being diagnosed before age 50 – in California in 1988–2021 and 61 050 matched individuals without cancer, men had a 34% higher risk of early-onset colorectal cancer compared with women. Also, Hispanic ethnicity was linked with a 43% higher risk compared with white ethnicity. Having a foreign-born mother was associated with a 15% lower risk of early-onset colorectal cancer. Among females, every 500g increase in birthweight was associated with a 10% increase in early-onset colorectal cancer risk and having a father aged 35 years or older was associated with a 56% higher risk. Investigators did not observe any links between early-onset colorectal cancer risk and other demographic, birth, and parental characteristics.
Additional research is needed to uncover potential mechanisms behind these associations.
“Evaluating demographic, birth, and parental characteristics is important in understanding what’s causing the rising incidence of early-onset colorectal cancer,” said lead author Sunny Siddique, MPH, PhD, of the Yale School of Public Health. “Our findings warrant future studies aimed to understand the mechanisms through which factors such as male sex, Hispanic ethnicity, birthweight, maternal birthplace, and paternal age may influence risk of early onset colorectal cancer.”
With colorectal cancer a growing concern among younger people, the American Cancer Society has endorsed two new types of stool tests to encourage people to get screened while also recommending a limited role for new blood tests many patients find appealing.
The recommendations are an update to the ACS’s screening guidelines – an update led by Andrew Wolf, MD, a cancer-prevention expert at UVA Health. He and a blue-ribbon panel of cancer experts conducted a systemic review of the available colorectal cancer tests to determine which are most effective. In addition to recommending a next-generation DNA stool test and a new type of RNA stool test, the group is advising doctors to recommend blood tests only to patients who decline all other options.
The recommendations come with a dose of pragmatism: “The most effective screening test,” the panel concludes, “is the one that the patient completes.”
“The new guidance adds a stool RNA test and an updated stool DNA test to the menu of preferred options for colorectal cancer screening, which currently include colonoscopy and stool tests that detect tiny amounts of blood, among other options,” said Wolf, a professor emeritus at the University of Virginia School of Medicine. “Although the idea of a blood test for colorectal cancer sounds very attractive, they aren’t yet as good as the other tests at detecting precancerous growths and early-stage cancer, so we don’t believe they are as effective as a screening test. That said, we’re very hopeful that broadening the array of options will get more folks screened and reduce the burden of suffering from colorectal cancer.”
About Colorectal Cancer
Colorectal cancer is the second-leading cause of cancer deaths in the United States, killing 55 000 people in 2026. Improvements in detection, screening and treatment have contributed to declining colorectal cancer death rates over the last several decades, but that decline has been accompanied since 2013 by an alarming increase in the cancer among people under the age of 50. Among that age group, colorectal cancer is now the leading cause of cancer death for men and the second-leading cause for women.
In response, the American Cancer Society in 2018 lowered the recommended age for initial colorectal cancer screening from 50 to 45 for people at average risk. It also affirmed the importance of screening tools such as stool-based tests as well as visual exams such as colonoscopies. Since then, however, new, multi-target stool tests and blood-based screening tests have become available. The new blood tests proved popular in a patient survey, with 53% of respondents saying they would prefer blood testing every three years to taking a stool test every year or receiving a colonoscopy every 10.
For the latest guideline update, Wolf and his colleagues examined the effectiveness of the new tests to provide doctors with guidance on if, how and when they should be used. The experts conclude that the DNA and RNA tests had high sensitivity for detecting colorectal cancer and moderate sensitivity for detecting advanced precancerous lesions that are about to turn into cancer. The blood tests, on the other hand, showed lower sensitivity for both advanced precancerous lesions and stage 1 cancers.
“While colorectal screening blood tests may not be as effective as other options, they are certainly better than not screening,” Wolf said. “So if a patient declines a stool test or a visual exam like a colonoscopy, a blood test would be the way to go, as long as the patient understands it is not as effective, and, if it is positive, they will still need to have a colonoscopy.”
Based on their results, the experts endorse the stool tests for patients at average risk but urge doctors to reserve the blood tests for patients who refuse other screening options. And they recommend that anyone who tests positive on any stool or blood test should receive a colonoscopy promptly.
It’s important, they note, that doctors explain to patients the strengths and weaknesses of the available tests so that patients can make informed decisions.
“Currently, almost a third of adults are not up to date with colorectal cancer screening, and among those ages 45 to 49, it’s twice that number,” Wolf said. “We hope these new options will help to close this gap. The most important message is that colorectal cancer is a disease you don’t have to die from, and there’s a screening test out there that’s right for you.”
Better preventing, detecting and treating cancer is the core mission of UVA Comprehensive Cancer Center, one of only 57 cancer centers in the nation to earn the prestigious “comprehensive” designation from the National Cancer Institute. That designation is awarded only to elite cancer centers with the most outstanding cancer care and research programs in the country.
Daily aspirin use does not offer a quick or reliable way to prevent colorectal cancer in the general population and carries immediate risks of serious bleeding, a new Cochrane review finds.
Colorectal cancer is one of the most common types of cancer worldwide. Prevention typically involves following a healthy lifestyle and periodically undergoing routine screening tests. In recent years, researchers have also explored the role of off-the-shelf medications, such as nonsteroidal anti-inflammatory drugs (NSAIDs), in reducing the incidence of colorectal cancer.
NSAIDs, which include ibuprofen and aspirin, are commonly used to reduce inflammation, fever, and pain. However, their role in the primary prevention of colorectal cancer remains uncertain and controversial.
Researchers from West China Hospital of Sichuan University in China analysed 10 randomised controlled trials including 124 837 participants, assessing whether aspirin or other NSAIDs could prevent colorectal cancer or precancerous polyps (adenomas) in people at average risk. The team found no suitable trials for non-aspirin NSAIDs, so their conclusions focus exclusively on aspirin.
Little to no short-term benefit and uncertain long-term effects
The review found that aspirin probably does not reduce the risk of colorectal cancer in the first 5 to 15 years of use. Possible protective effects after more than 10–15 years of follow-up were observed in some studies, but the certainty of this evidence is very low.
These potential long-term benefits come from observational follow-up phases of trials, in which participants may have stopped aspirin, started it independently, or begun other treatments, making the findings vulnerable to bias.
“While the idea of aspirin preventing bowel cancer in the long run is intriguing, our analysis shows that this benefit is not guaranteed and comes with immediate risks.”
— Dr Zhaolun Cai, lead author
Immediate and well-established risks
The findings also show clear evidence that daily use of aspirin increases the risk of serious extracranial haemorrhage and probably increases the risk of haemorrhagic stroke.
Although higher doses carry the greatest risk, low-dose (“baby”) aspirin also raises bleeding risk. Older adults and those with a history of ulcers or bleeding disorders may be particularly vulnerable.
The authors therefore caution that any potential long-term benefit must be weighed against the immediate and well-established risk of bleeding.
“My biggest worry is that people might assume that taking an aspirin today will protect them from cancer tomorrow. In reality, any potential preventive effect takes over a decade to appear, if it appears at all, while the bleeding risk begins immediately.”
— Dr Bo Zhang, senior author
Not a ‘one-size-fits-all’ solution
Previous evidence has shown potential benefits for people at high genetic risk of colorectal cancer, such as those with Lynch syndrome. However, this review focuses strictly on people at average risk, and the long-term evidence for them proved highly uncertain.
The authors urge that patients should not start taking aspirin for cancer prevention without a careful conversation with their healthcare professional about their personal risk of bleeding.
“This review reinforces that we must move away from a one-size-fits-all approach. Widespread aspirin use in the general population simply isn’t supported by the evidence. The future lies in precision prevention – using molecular markers and individual risk profiles to identify who might benefit most and who is most at risk.”
— Dr Dan Cao, senior author
The research team concludes that the story of aspirin for cancer prevention is far more complex than previously believed and that the balance of benefits and harms changes over time.
Dr Zhang adds:
“As scientists, we must follow the evidence where it leads. Our rigorous analysis of the highest-quality trials reveals that the ‘aspirin for cancer prevention’ story is more complex than a simple ‘yes or no.’ The current evidence does not support a blanket recommendation for aspirin use purely to prevent bowel cancer.”
Results from a cancer screening trial indicate that consistent heavy alcohol intake and higher average lifetime drinking are associated with increased risk.
Photo by Apolo Photographer on Unsplash
Studies have demonstrated a link between alcohol consumption and an elevated risk of colorectal cancer. New research now reveals that higher lifetime alcohol consumption is also associated with a higher risk, especially for rectal cancer, and that quitting drinking can lower a person’s risk. The findings are published by Wiley online in CANCER, a peer-reviewed journal of the American Cancer Society.
When investigators analysed data on US adults enrolled in the National Cancer Institute (NCI) Prostate, Long, Colorectal, and Ovarian (PLCO) Cancer Screening Trial who did not have cancer at baseline, they observed that 1679 colorectal cancer cases occurred among 88 092 participants over 20 years of follow-up.
Current drinkers with an average lifetime alcohol intake of ≥ 14 drinks per week (heavy drinkers) had a 25% higher risk of developing colorectal cancer and a 95% higher risk of developing rectal cancer compared with those with an average lifetime alcohol intake of < 1 drink per week (light drinkers).
When further considering drinking consistency, heavy drinking throughout adulthood was linked to a 91% higher risk of colorectal cancer compared with consistent light drinking. In contrast, no evidence of increased colorectal cancer risk was observed among former drinkers, and former drinkers had lower odds of developing noncancerous colorectal tumours, or adenomas (which may go on to become cancerous) than current drinkers averaging < 1 drink per week, suggesting that alcohol cessation may lower individuals’ risks. These data were limited, however.
The association between alcohol consumption and increased risks observed in this and other studies might be explained by carcinogens produced from alcohol metabolism or alcohol’s effects on gut microbes. Additional studies are needed to test whether these mechanisms are involved.
“Our study is one of the first to explore how drinking alcohol over the life course relates to both colorectal adenoma and colorectal cancer risk. While the data on former drinkers were sparse, we were encouraged to see that their risk may return to that of the light drinkers,” said co–senior author Erikka Loftfield, PhD, MPH, of the NCI, part of the National Institutes of Health.
A new study from researchers at The University of Texas MD Anderson Cancer Center shows that the glucose-fructose mix found in sugary drinks directly fuels metastasis in preclinical models of advanced colorectal cancer. The study was published in Nature Metabolism.
A research team led by Jihye Yun, PhD, assistant professor of Genetics, studied how sugary drinks may affect late-stage colorectal cancer. Using laboratory cancer models, they compared the effects of the glucose-fructose mix found in most sugary drinks with those of glucose or fructose alone. Only the sugar mix made cancer cells more mobile, leading to faster spread to the liver – the most common site of colorectal cancer metastasis.
The sugar mix activated an enzyme called sorbitol dehydrogenase (SORD), which boosts glucose metabolism and triggers the cholesterol pathway, ultimately driving metastasis. This is the same pathway targeted by statins, common heart drugs that inhibit cholesterol production. Blocking SORD slowed metastasis, even with the sugar mix present. These findings suggest that targeting SORD could also offer an opportunity to block metastasis.
“Our findings highlight that daily diet matters not only for cancer risk but also for how the disease progresses once it has developed,” Yun said. “While these findings need further investigation, they suggest that reducing sugary drinks, targeting SORD or repurposing statins may benefit patients with colorectal cancer.”
The Yun Laboratory is interested in studying how diet affects the intestine and cancer development, and they have made important discoveries on the impacts of sugary drinks on colorectal cancer.
Sugar has long been indirectly linked to an increase in cancer risk through obesity. However, a previous study by Yun’s lab challenged that view, showing that even moderate intake of sugary drinks directly fuelled tumour growth in early-stage colorectal cancer, independent of obesity. The current study was done to determine how sugary drinks may impact later-stage disease.
While this study needs further clinical investigation, the results suggest that reducing sugary drinks and targeting the SORD enzyme may offer opportunities to reduce colorectal cancer metastasis. Additional studies are warranted to confirm these results outside of preclinical models.
Further, Yun explained it may be worthwhile to consider revisions to current dietary recommendations to reduce sugary drink consumption in this patient population. To meet nutritional needs, many patients with cancer are encouraged to have nutritional supplement drinks and concentrated juices that contain high glucose and fructose content.
A Swedish-led research team at Karolinska Institutet and Karolinska University Hospital has shown in a new randomised clinical trial that a low dose of the well-known medicine aspirin halves the risk of recurrence after surgery in patients with colon and rectal cancer with a certain type of genetic alteration in the tumour.
Every year, nearly two million people worldwide are diagnosed with colorectal cancer, and 20–40% develop metastases.
Previous observational studies have suggested that aspirin may reduce the risk of certain cancers and possibly also the risk of recurrence after surgery in patients with colorectal cancer harbouring mutations in genes within the PIK3 signaling pathway. These genes regulate key cellular processes such as growth and division. When mutated, these processes can become dysregulated, leading to uncontrolled cell proliferation and cancer development.
Randomised clinical trials were lacking
Prior findings have been inconsistent and no randomised clinical trials had previously confirmed the association. To address this gap, the ALASCCA trial was initiated, with the results now been published in The New England Journal of Medicine.
The current study included more than 3500 patients with colon and rectal cancer from 33 hospitals in Sweden, Norway, Denmark, and Finland. Patients whose tumours showed a specific genetic mutation in the PIK3 signalling pathway – a mutation found in approximately 40% of patients – were randomised to receive either 160mg of aspirin daily or a placebo for three years after surgery.
For patients with the genetic mutation in PIK3, the risk of recurrence was reduced by 55% in those who received aspirin compared with the placebo group.
“Aspirin is being tested here in a completely new context as a precision medicine treatment. This is a clear example of how we can use genetic information to personalise treatment and at the same time save both resources and suffering,” says first author Anna Martling, professor at the Department of Molecular Medicine and Surgery, Karolinska Institutet, and senior consultant surgeon at Karolinska University Hospital.
Less favourable environment for cancer
So how does aspirin reduce the risk of recurrence of colon and rectal cancer? The researchers believe that the effect is likely due to aspirin acting through several parallel mechanisms – it reduces inflammation, inhibits platelet function and tumour growth. This combination makes the environment less favourable for cancer.
“Although we do not yet fully understand all the molecular links, the findings strongly support the biological rationale and suggest that the treatment may be particularly effective in genetically defined subgroups of patients,” says Anna Martling.
The researchers believe that the results could have global significance and influence treatment guidelines for colon and rectal cancer worldwide. Anna Martling sees the fact that the drug is well established as a major advantage.
“Aspirin is a drug that is readily available globally and extremely inexpensive compared to many modern cancer drugs, which is very positive,” says Anna Martling.
The potential role of vitamin D in preventing and treating colorectal cancer (CRC) has attracted growing research interest – especially as CRC rates are rising, particularly among younger adults. This isn’t a new area of study. Low vitamin D levels have long been linked to a higher risk of developing colorectal cancer.
One large study involving over 12 000 participants found that people with low blood levels of vitamin D had a 31% greater risk of developing CRC compared to those with higher levels. Similarly, another study reported a 25% lower CRC risk among individuals with high dietary vitamin D intake.
Data from the Nurses’ Health Study – a long-term investigation of American nurses – showed that women with the highest vitamin D intake had a 58% lower risk of developing colorectal cancer compared to those with the lowest intake.
Now, a review highlights vitamin D’s promise in colorectal cancer prevention and treatment – but also underscores the complexity and contradictions in current research.
While observational data, which follow people’s use of vitamin D, and mechanistic studies, to investigate how vitamin D works in the laboratory, suggest protective effects, this isn’t confirmed by larger trials.
In fact, randomised controlled trials (RCTs), in which some people receive vitamin D and others don’t, the gold standard by which treatments are judged, reveal inconsistent outcomes. This highlights the need for a balanced approach to its integration into public health strategies.
Vitamin D is synthesised in the skin in response to sunlight and exerts its biological effects through vitamin D receptors (VDRs) found throughout the body, including in colon tissue. When activated, these receptors help regulate gene activity related to inflammation, immune response and cell growth – processes central to cancer development and progression.
Preclinical studies have shown that the active form of vitamin D (calcitriol) can suppress inflammation, boost immune surveillance (the immune system’s ability to detect abnormal cells), inhibit tumour blood vessel growth and regulate cell division – a key factor in cancer development, as demonstrated in my recent research.
Epidemiological studies, which track health outcomes across large populations over time, consistently find that people with higher blood levels of vitamin D have a lower risk of developing CRC. This paints a hopeful picture, suggesting that something as simple as getting more vitamin D – via sun exposure, diet, or supplements – could lower cancer risk.
But the story gets more complicated.
Mixed results
When it comes to medical decision-making, randomised controlled trials (RCTs) are the gold standard. These studies randomly assign participants to receive either a treatment (like vitamin D) or a placebo, helping eliminate bias and isolate cause-and-effect relationships.
Unfortunately, RCTs on vitamin D and CRC have produced mixed results.
For example, the VITAL trial – a major RCT involving over 25 000 participants – found no significant reduction in overall colorectal cancer incidence with 2000 IU/day of vitamin D supplementation over several years.
However, a meta-analysis of seven RCTs did show a 30% improvement in CRC survival rates with vitamin D supplements, suggesting potential benefits later in the disease course rather than for prevention.
On the other hand, the Vitamin D/Calcium Polyp Prevention Trial found no reduction in the recurrence of adenomas (pre-cancerous growths) with supplementation, raising questions about who benefits most, and at what dosage.
Adding to the uncertainty is the question of causation. Does low vitamin D contribute to cancer development? Or does the onset of cancer reduce vitamin D levels in the body? It’s also possible that the observed benefits are partly due to increased sunlight exposure, which itself may have independent protective effects.
The big picture
These discrepancies highlight the importance of considering the “totality of evidence” – treating each study as one piece of a larger puzzle.
The biologic plausibility is there. Observational and mechanistic studies suggest a meaningful link between vitamin D and lower CRC risk. But the clinical evidence isn’t yet strong enough to recommend vitamin D as a standalone prevention or treatment strategy.
That said, maintaining sufficient vitamin D levels – at least 30ng/mL – is a low-risk, cost-effective health measure. And when combined with other strategies like regular screening, a healthy diet, physical activity, and personalised care, vitamin D could still play a valuable role in overall cancer prevention.
Vitamin D is not a miracle cure – but it is part of a much broader picture. Its role in colorectal cancer is promising but still being defined. While it’s not time to rely on supplements alone, ensuring adequate vitamin D levels – through sun exposure, diet, or supplements – remains a smart choice for your health.
Colorectal cancer is a complex disease, and tackling it requires an equally nuanced approach. For now, that means focusing on evidence-based lifestyle changes, regular screenings, and staying informed as new research unfolds.
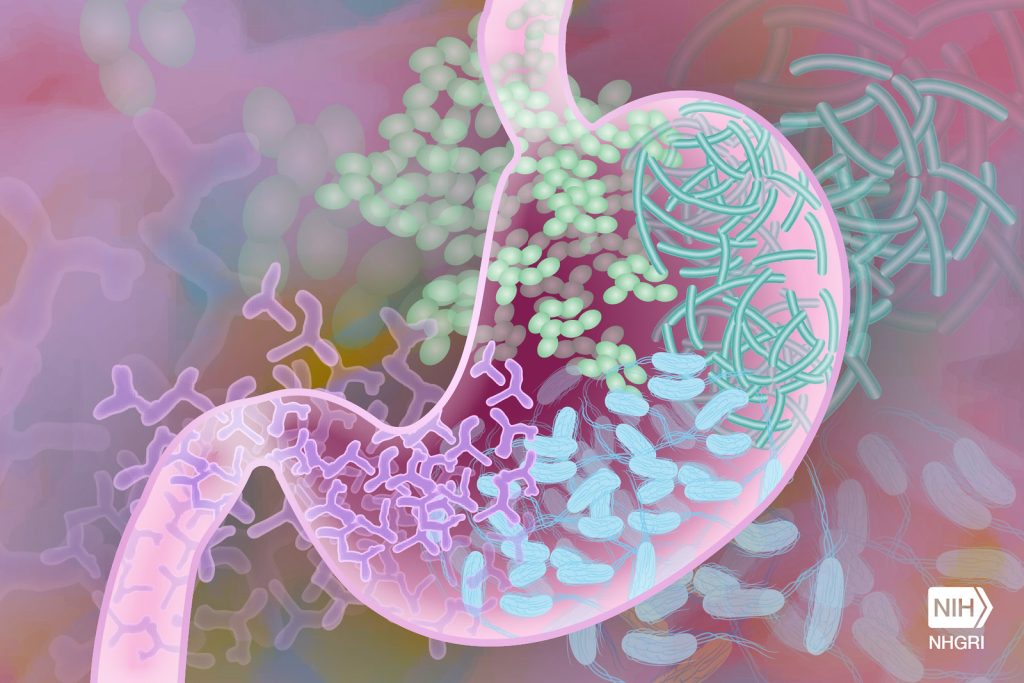
Gut Microbiome. Credit Darryl Leja National Human Genome Research Institute National Institutes Of Health
Researchers from the University of Toronto have shown how a low-carbohydrate diet can worsen the DNA-damaging effects of some gut microbes to cause colorectal cancer.
The study, published in the journal Nature Microbiology, compared the effects of three different diets: normal, low-carb, or Western-style with high fat and high sugar, each in combination with specific gut bacteria on colorectal cancer development in mice.
They found that a unique strain of E. coli bacteria, when paired with a diet low in carbs and soluble fibre, drives the growth of polyps in the colon, which can be a precursor to cancer.
“Colorectal cancer has always been thought of as being caused by a number of different factors including diet, gut microbiome, environment and genetics,” says senior author Alberto Martin, a professor of immunology at U of T’.
“Our question was, does diet influence the ability of specific bacteria to cause cancer?”
To answer this question, the researchers, led by postdoctoral fellow Bhupesh Thakur, examined mice that were colonized with one of three bacterial species that had been previously linked to colorectal cancer and fed either a normal, low-carb or Western-style diet.
Only one combination, a low-carb diet paired with a strain of E. coli that produces the DNA-damaging compound colibactin, led to the development of colorectal cancer.
The researchers found that a diet deficient in fibre increased inflammation in the gut and altered the community of microbes that typically reside there, creating an environment that allowed the colibactin-producing E. coli to thrive.
They also showed that the mice fed a low-carb diet had a thinner layer of mucus separating the gut microbes from the colon epithelial cells. The mucus layer acts as a protective shield between the bacteria in the gut and the cells underneath. With a weakened barrier, more colibactin could reach the colon cells to cause genetic damage and drive tumour growth. These effects were especially strong in mice with genetic mutations in the mismatch repair pathway that hindered their ability to fix damaged DNA.
While both Thakur and Martin emphasize the need to confirm these findings in humans, they are also excited about the numerous ways in which their research can be applied to prevent cancer.
Defects in DNA mismatch repair are frequently found in colorectal cancer, which is the fourth most commonly diagnosed cancer in Canada. An estimated 15 per cent of these tumours having mutations in mismatch repair genes. Mutations in these genes also underlie Lynch syndrome, a genetic condition that significantly increases a person’s risk of developing certain cancers, including colorectal cancer.
“Can we identify which Lynch syndrome patients harbour these colibactin-producing microbes?” asks Martin. He notes that for these individuals, their findings suggest that avoiding a low-carb diet or taking a specific antibiotic treatment to get rid of the colibactin-producing bacteria could help reduce their risk of colorectal cancer.
Martin points out that a strain of E. coli called Nissle, which is commonly found in probiotics, also produces colibactin. Ongoing work in his lab is exploring whether long-term use of this probiotic is safe for people with Lynch syndrome or those who are on a low-carb diet.
Thakur is keen to follow up on an interesting result from their study showing that the addition of soluble fibre to the low-carb diet led to lower levels of the cancer-causing E. coli, less DNA damage and fewer tumours.
“We supplemented fibre and saw that it reduced the effects of the low-carb diet,” he says. “Now we are trying to find out which fibre sources are more beneficial, and which are less beneficial.”
To do this, Thakur and Martin are teaming up with Heather Armstrong, a researcher at the University of Alberta, to test whether supplementation with a soluble fibre called inulin can reduce colibactin-producing E. coli and improve gut health in high-risk individuals, like people with inflammatory bowel disease.
“Our study highlights the potential dangers associated with long-term use of a low-carb, low-fibre diet, which is a common weight-reducing diet,” says Martin.
“More work is needed but we hope that it at least raises awareness.”
Researchers at Karolinska Institutet have found a molecule that can both help the intestines to heal after damage and suppress tumour growth in colorectal cancer. The discovery could lead to new treatments for inflammatory bowel disease (IBD) and cancer. The results are published in the journal Nature.
Many patients with inflammatory bowel disease (IBD) such as Crohn’s disease or ulcerative colitis do not respond to available treatments, highlighting the need to identify novel therapeutic strategies. In this study, researchers propose that promoting mucosal healing through tissue regeneration could be a valid alternative to immunosuppressive drugs.
“However, it’s virtually impossible to promote tissue regeneration without the risk of inducing tumour growth, as cancer cells can hijack the body’s natural healing processes and start to grow uncontrollably,” says lead author Srustidhar Das, research specialist in Eduardo Villablanca’s research group at Karolinska Institutet. “We’ve now identified a molecule that can help the intestines to heal after damage while suppressing tumour growth in colorectal cancer.”
New drug candidates
In their search for new ways to treat IBD, the researchers have identified a handful of molecules with drug-candidate potential. They found that activation of a protein called the Liver X receptor (LXR) can promote regeneration and suppress tumour growth in colorectal cancer.
“The discovery of both these functions was astonishing,” says last author Eduardo J. Villablanca, docent at Karolinska Institutet. “We now need to study how LXR controls tumour formation more closely.”
The researchers used a collection of advanced technologies to conduct their study, which included mapping the transcriptome of intestinal cells. The researchers also cultivated what are known as 3D organoids: small, three-dimensional cell structures that mimic the function and structure of the body’s own organs, albeit in miniature format.
They then used spatial transcriptomics to map the gene expression in the different tissues, a technique that has been developed at SciLifeLab by scientists from the Royal Institute of Technology (KTH) and Karolinska Institutet in Sweden.
Third most common cancer
Patients, the third most common type in Sweden, are often treated with chemotherapy and radiotherapy, but this can cause irritation and swelling of the bowel mucosa with subsequent chronic intestinal inflammation.
“Thus, this new therapeutic molecule has the potential to treat not only IBD patients but also cancer patients to prevent chronic bowel disorders after radiotherapy and/or chemotherapy,” says Eduardo J. Villablanca.
Plant fungus provides new drug with a new cellular target
Human colon cancer cells. Credit: National Cancer Institute
Novel chemical compounds from a fungus could provide new perspectives for treating colorectal cancer, one of the most common and deadliest cancers worldwide. The fungus, Bipolaris victoriae, is otherwise known as a fungal plant pathogen which in the 1940s caused the “Victoria blight”, decimating oats and similar grains in the US.
In the journal Angewandte Chemie, researchers reported on the isolation and characterisation of a previously unknown class of metabolites (terpene-nonadride heterodimers). One of these compounds effectively kills colorectal cancer cells by attacking the enzyme DCTPP1, which thus may serve as a potential biomarker for colorectal cancer and a therapeutic target.
Rather than using conventional cytostatic drugs, which have many side effects, modern cancer treatment frequently involves targeted tumour therapies directed at specific target molecules in the tumour cells. The prognosis for colorectal cancer patients remains grim however, demanding new targets and novel drugs.
Targeted tumour therapies are mostly based on small molecules from plants, fungi, bacteria, and marine organisms. About half of current cancer medications were developed from natural substances. A team led by Ninghua Tan, Yi Ma, and Zhe Wang at the China Pharmaceutical University (Nanjing, China) chose to use Bipolaris victoriae S27, a fungus that lives on plants, as the starting point in their search for new drugs.
The team first analysed metabolic products by cultivating the fungus under many different conditions (OSMAC method, one strain, many compounds). They discovered twelve unusual chemical structures belonging to a previously unknown class of compounds: terpene-nonadride heterodimers, molecules made from one terpene and one nonadride unit. Widely found in nature, terpenes are a large group of compounds with very varied carbon frameworks based on isoprene units. Nonadrides are nine-membered carbon rings with maleic anhydride groups. The monomers making up this class of dimers termed “bipoterprides” were also identified and were found to contain additional structural novelties (bicyclic 5/6-nonadrides with carbon rearrangements).
Nine of the bipoterprides were effective against colorectal cancer cells. The most effective was bipoterpride No. 2, which killed tumour cells as effectively as the classic cytostatic drug Cisplatin. In mouse models, it caused tumours to shrink with no toxic side effects.
The team used a variety of methods to analyse the drug’s mechanism: bipoterpride 2 inhibits dCTP-pyrophosphatase 1 (DCTPP1), an enzyme that regulates the cellular nucleotide pool. The heterodimer binds significantly more tightly than each of its individual monomers. The activity of DCTPP1 is elevated in certain types of tumours, promoting the invasion, migration, and proliferation of the cancer cells while also inhibiting programmed cell death. It can also help cancer cells to resist treatment. Bipoterpride 2 inhibits this enzymatic activity and disrupts the now pathologically altered amino acid metabolism in the tumour cells.
The team was thus able to identify DCTPP1 as a new target for the treatment of colorectal cancer and bipoterprides as new potential drug candidates.