Exploited and Exhausted, SA’s Ghost Doctors Start to Rattle Their Chains
By Joan van Dyk for Spotlight

For years, hospitals have relied on the unpaid, unprotected labour of trainee-specialists to fill their rosters, but these doctors are reaching a breaking point.

Across South Africa’s public sector hospitals, a growing number of aspiring specialists are choosing to work for free — sometimes for years at a time — in pursuit of the coveted title.

Nearly every step of the 12 to 15 years of training required to specialise or sub-specialise can only happen in the public sector, but provincial health departments, bruised by more than a decade of austerity and graft, have few paid posts to offer.

As a result, hundreds of local doctors and hopeful specialists are stuck in a nightmarish competition to be the most impressive candidate. There are waiting lists for both paid and unpaid positions.

Once the paid positions are filled, doctors from poorer backgrounds who did not get placed are at a dead end, perpetuating historical injustices and undercutting transformation targets. “A new apartheid,” several doctors call it.

The volunteer specialists Spotlight interviewed knew they were lucky to have the option to specialise, but their stories suggest it’s a dubious privilege.

They endure the financial and emotional stress of specialising without pay for a number of reasons, passion, to take over the family practise, or, most commonly, to secure a ticket out of the public healthcare sector.

But to reach the predictable hours and high income of specialist private practise, they must first navigate a clinical wasteland left behind by years of budget cuts and mismanagement by provincial health departments.

The gruelling unpaid route to specialisation they describe crosses a financial abyss with toll gates guarded by sometimes powerful bullies and dotted with legal and professional traps that could cast a long shadow over the futures they’re working to build.

How to spot a clinical spectre

South Africa’s phantom doctors have many names; they’re called fellows, volunteers or supernumeraries, depending on the facility.

The role was originally created as part of a regional programme that allows foreign doctors to train in South African hospitals. These trainees’ salaries are covered by their home governments and they’re not guaranteed a work visa through the Department of Home Affairs or accreditation from the Health Professions Council of South Africa (HPCSA) once they are qualified. Only 3% of the 5 772 doctors added to the government’s payroll between January and May were not South African citizens.

In recent years, so many South African doctors have accepted such unpaid positions that some provincial health departments advertise such “opportunities” and plan their budgets accordingly.

Spotlight was unable to quantify South Africa’s unpaid trainee specialist workforce. Only two of the eight medical schools surveyed between April and July provided trainee data and requests for the HPCSA’s list of active training codes for specialists and sub-specialists went unanswered. A training code is a non-negotiable prerequisite for sitting specialist exit exams regardless of funding source or employment status of the trainee. When cross-referenced with provincial payroll data, such a list could help estimate the extent to which the health system relies on unpaid expertise.

Anecdotal evidence suggests however that the trend started around 2020 in the Western Cape, where many interviewees say they wouldn’t mind working for the state. These days, Gauteng and KwaZulu-Natal’s cohorts of unpaid citizen specialists appear to be increasing too.

Interviews with numerous local supernumeraries suggest they often endure toxic hierarchies, bullying and administrative neglect, but they prefer to suffer in silence, terrified that seniors will fail them in expensive tests.

Specialist exams are officially set by the Colleges of Medicine (CMSA), but there are usually only a few qualified specialist examiners for each academic circuit. So, in reality, trainees are often being examined by their own department heads or a close colleague.

Pride, debt and resentment

The cutthroat race to build a standout CV starts as soon as medical students graduate. It’s no longer enough to gain experience as a medical officer and then to apply for a job as a registrar a couple of years later, there simply aren’t enough paid positions for either.

Any job posting can draw hundreds of applications from equally qualified candidates.

The resulting competition is harsh, and requirements ever shifting and often unstated.

Naeema Govender*, an aspiring anaesthesiologist in Gauteng, says it took her a couple of failed interviews to figure out how to decode a government job ad.

Experience in intensive care and internal medicine, she says, are now de facto requirements for anyone applying for a job as an anaesthesia registrar (or trainee-specialist) whether the advert says so or not, and “anaesthesia experience” really means a minimum of two years’ experience.

In highly competitive fields such as urology, registrar candidates are now expected to have completed two out of three major specialist exams (usually written during training) before they even apply.

Pulling shifts for free ends up being a good way to get an edge over others.

After a string of unsuccessful interviews for paid jobs, Meera Patel*, another anaesthesiologist-in-training, says she accepted a supernumerary post at Steve Biko Academic Hospital in Tshwane out of sheer desperation.

“I used to tell anyone who would listen that I would never subject myself to it,” she says. The extra experience did help Patel to get a paid registrar job in the Western Cape, but it left her feeling deep resentment for having to compromise her principles and work without pay to crack the system.

In Johannesburg, Govender says she also reluctantly took an unpaid position to beef up her CV. She’s still conflicted about the exploitation she felt forced into.

“I don’t know if I should be proud or ashamed,” she tells Spotlight.

Paranormal planning

The unpaid trainee specialist workforce does little to eventually increase the number of qualified specialists available to the public at government hospitals, so private healthcare appears to be the overall winner.

Once doctors are qualified specialists, they often flee to the private sector or emigrate. This is perhaps illustrated by the fact that 30% of the 22 405 doctors employed by the state are under the age of 35.

The trend has ultimately turned the public sector clinical platform into a subsidised training ground for private healthcare, argues Bernhard Gaede, an associate professor and head of the Department of Family Medicine at the University of KwaZulu-Natal.

There also seems to be an element of privatisation-by stealth unfolding.

Trainees are increasingly being supported by foundations or private hospital groups to fill a growing niche for sub-specialists, says Marthinus Dicks, a member of the South African Medical Association’s (SAMA) subcommittee for registrars.

At the Groote Schuur Hospital unit where Dicks is training to be a clinical haematologist, he says he’s one of only two who are paid a government salary. He also logged unpaid hours before he was offered a paid post.

He worries that the private money is taking pressure off the government to fulfil its training role. At the same time, he knows his already high workload would be much heavier without his three fellowship-supported colleagues. “It’s just not a life I want to imagine,” he says.

Between the free labour, private funding and foreign trainees, there’s little incentive for cash-strapped health provincial health departments to create permanent posts, according to a SAMA submission to the ministerial advisory committee on health staff.

The unpaid trainee specialist workforce isn’t mentioned in the health department’s health staffing reform plan, which lapses in 2030. The document does outline a five-year plan to improve clinical supervision, boost specialist retention and to develop a broader network of clinical support for trainees by 2025.

A progress report was submitted to Health Minister Dr Aaron Motsoaledi in March but critics say the plan is unlikely to have made a difference because the government lacks the high-quality data on public and private sector personnel that would be needed for implementation.

South Africa needs a Workforce Intelligence Authority that collates and cleans workforce data to be used for planning, suggests governance expert Professor Alex van den Heever. In July, he presented a draft policy brief to SAMA which also proposes ring-fencing training funds to protect salaries from provincial mismanagement and extending training subsidies and accreditation to private health facilities.

Without structural changes to address waste and mismanagement, Van Den Heever argues, simply giving provinces more money to counteract austerity will make no difference.

In the meantime, the government now deliberately budgets for clinical gaps to be filled by volunteers, says Sharon Twum-Boafo, head of SAMA’s registrar subcommittee.

“It’s ludicrous,” she says, “without the volunteers, many hospitals would simply not have enough doctors to cover 24-hour rosters.”

A legal void

Unpaid trainee specialists carry a heavy workload with few administrative and legal protections.

Since they lack a payroll number, they’re locked out of the blanket indemnity for healthcare workers employed by the state. Instead, government compels them to buy expensive private malpractice cover just to log hours for free in public hospitals.

Once they’re in the facility, Spotlight is told that it is possible they might be pressured to perform unsupervised, high-risk procedures far beyond their insured scope.

Speaking to Spotlight, several of these phantom physicians described their fear of being held personally liable for costs in potential lawsuits. Some are privately insured for millions of rands, which means that they would make for more lucrative targets than the government, where mediation often leads to lower payouts.

Ruan Vlok, head of SAMA’s employment law unit, agrees that unpaid specialists might become litigation lightning rods.

“It could become an easy making money machine for attorneys,” he says.

There are long term risks too.

Private insurance premiums are tied to clinical outcomes, so a pattern of bad events could drive up a doctor’s insurance premiums, or even render them uninsurable, the ultimate career-ending risk for a specialist.

Unfinished business

Some unpaid trainees face another tough reality.

They are often summoned to fill critical service gaps left by paid, full-time consultants who have vanished to moonlight in the private sector.

Dual practise is allowed within certain parameters, but enforcement of the rules is patchy across provinces and facilities. Money is one of the factors driving moonlighting among the state’s contracted specialists, whose salaries have not kept pace with inflation. A SAMA report estimates that in 2022, doctors were earning about as much as they were in 2013.

In order to save money, provincial health departments have limited the number of paid overtime hours that consultants can log. In this case, says Vlok, doctors are fully within their rights to refuse to work for free.

Ironically, this is when those who choose to work for free become extra useful in hospitals.

Yet should the phantom doctors  themselves attempt to pull a paid shift to survive, they could be threatened with disciplinary action, heavy fines, or the immediate deactivation of their training numbers.

Under HPCSA and university rules, trainee registrars are legally barred from doing private paid work. Worse still, when a crisis occurs, these supernumeraries find themselves locked in dual contracts with universities and hospitals, with little protection from either.

An uneasy peace

The rights of the health system’s unpaid workforce have never been challenged in court, Vlok says, in part because doctors fear that any litigation would lead to them being targeted or failed in their exit exams.

Because supernumeraries aren’t officially employees, they’re also excluded from recourse through the country’s labour dispute resolution body, the Commission for Conciliation, Mediation and Arbitration and the Bargaining Council, leaving them with no mechanism for redress.

Local supernumeraries technically sign away they rights by agreeing to work without pay, but Vlok argues the state is taking advantage of a vulnerable group because the public sector is the only route to specialisation.

The regulations that allow foreign trainees to work in South Africa do not cater to or even make provision for South African citizens, Vlok says. In his view, the Labour Relations Act and the Basic Conditions of Employment Act should take legal precedence, under which he believes unpaid trainees clearly meet the criteria of an employee.

“I don’t use this word lightly,” he says, “this is abuse.”

It’s unclear how much longer the strained peace will hold.

One exhausted trainee specialist told Spotlight: “We have to fix the medical system, it’s broken. Who is going to look after us when we’re old?”

*Spotlight granted the doctors quoted in this article anonymity because of the risk of reprisals from provincial health departments and the hospitals where they are working.

*This article was first published by Spotlight – health journalism in the public interest. Sign up to the Spotlight newsletter.

Understanding the Night-time Rise in Intraocular Pressure Could Lead to Glaucoma Treatment

Norepinephrine-induced RHOB is a key regulator of circadian intraocular pressure rhythm

Photo by Cottonbro on Pexels

Glaucoma is an eye disease that causes progressive damage to the optic nerve, leading to loss of sight. One major risk factor is an increase in intraocular pressure (IOP), or the pressure inside the eye. This pressure fluctuates throughout the day and is known to rise at night. However, the detailed molecular mechanisms on why this happens have not been fully understood.

Using human cells and mouse models, researchers at Kyushu University have found a new molecular pathway that explains why IOP increases at night. The neurotransmitter norepinephrine (also known as noradrenaline) increases the levels of a molecule called RHOB in the eye’s drainage system called the trabecular meshwork. This weakens the eye’s ‘cleaning function’, resulting in increased IOP. The team expects these findings will lead to the development of new approaches for the early detection of glaucoma, as well as new treatments for controlling IOP by targeting RHOB. Their results were published in the journal Communications Biology.

IOP is maintained by balancing fluid production and fluid drainage within the eye. As with many bodily functions, it is regulated by the circadian clock. In the case of the eye, IOP increases at night. Elevated IOP is a key factor in identifying the onset of glaucoma, but because pressure tends to be lower during the day, regular checkups can potentially miss these warning signs.

Because the circadian clock regulates IOP, disruptions to a person’s internal clock can lead to increased risk of glaucoma. This is why there is a higher risk of glaucoma in the elderly whose body clocks are desynchronising.

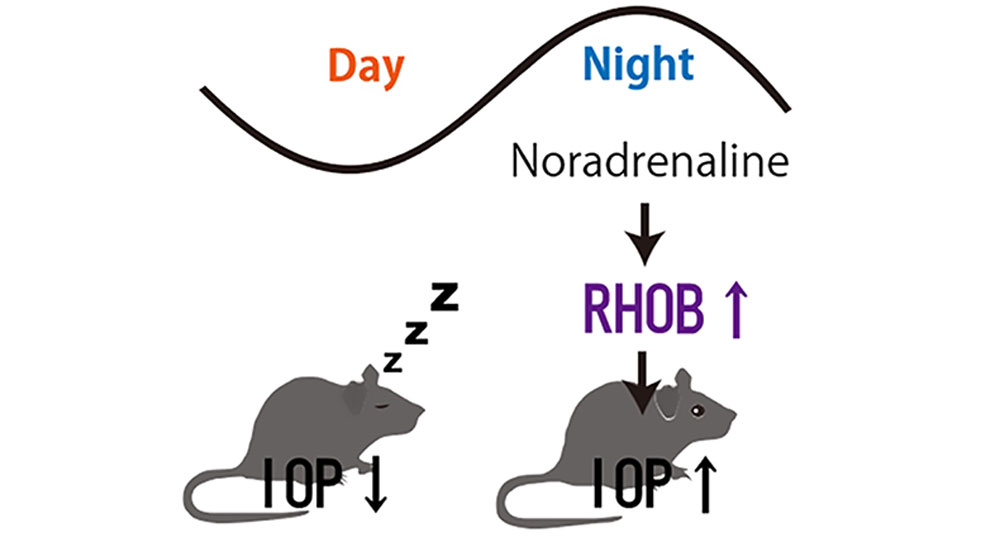
Fig.1. Graphical abstract of the research results
Using mice, researchers found that norepinephrine released from the sympathetic nervous system increases RHOB levels and suppresses the eye’s drainage system, thereby contributing to the rise in intraocular pressure at night.

“Previous studies have found that signals from the sympathetic nervous system contribute to the nighttime rise in eye pressure, but that underlying process was not well understood,” explains first author of the study, Associate Professor Keisuke Ikegami from Kyushu University’s Faculty of Agriculture. “Most of the fluid in the eye is drained through a tissue called the trabecular meshwork. These cells also help keep the drainage pathway clear by taking up and removing small particles and waste. We also know that norepinephrine is a chemical that is released by the sympathetic nervous system. We decided to investigate how norepinephrine can change the function of fluid drainage in the eye and whether it can explain why eye pressure increases at night.”

The team began by exposing human and mouse trabecular meshwork cells to norepinephrine and compared changes in their genetic activity. They identified 18 genes that increased in both systems and focused on one called RHOB. RHOB is a molecule that is involved in controlling cell shape, movement, and intracellular transport.

Norepinephrine increased RHOB in the trabecular meshwork cells, and when RHOB was removed from human cells, their ability to take up and clear particles increased. In contrast, increasing RHOB reduced the cleaning activity and fluid movement in the eye. Testing in mice, the team used eye drops that inhibit a chemical pathway that controls RHOB activity, the RHO-ROCK pathway. The results showed that the eye drops reduced the nighttime rise in eye pressure.

While these results are not intended for immediate clinical application, they have identified the RHOB pathway as a new potential target for suppressing nocturnal increase in IOP. While ROCK inhibitors are used in glaucoma treatments today, further verification is needed to determine the most effective time of day for administration and how they alter IOP rhythm.

“Loss of vision from glaucoma occurs slowly, so early detection is crucial. We hope our work will lead to new treatment regimens and strategies for administering medicines to achieve the greatest effect,” concludes Ikegami.

Source: Kyushu University

UP-led International Team Looks to Nature to Outsmart Antibiotic Resistance

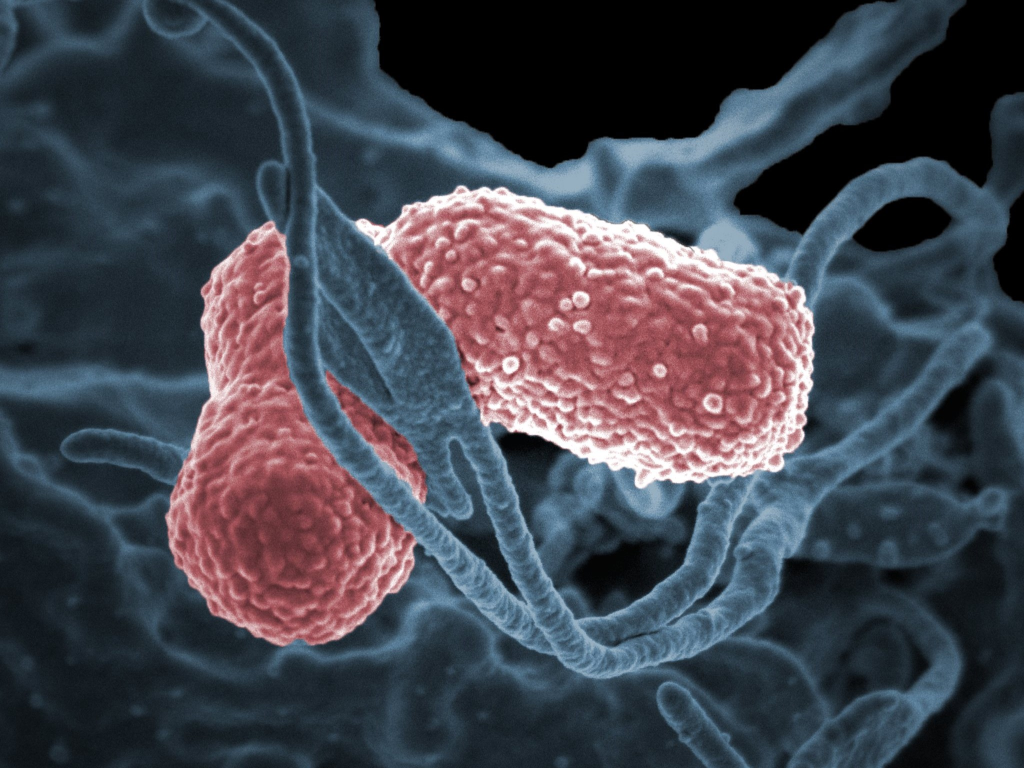
A human neutrophil interacting with Klebsiella pneumoniae (pink), a multidrug–resistant bacterium that causes severe hospital infections. Credit: National Institute of Allergy and Infectious Diseases, National Institutes of Health

What if part of the answer to antibiotic resistance has been growing in plants, fungi and microorganisms all along? Scientists say hundreds of thousands of natural compounds remain largely unexplored as researchers race to protect some of the world’s most important antibiotics.

An international team of scientists led by the University of Pretoria (UP) is calling for a renewed search of the natural world for molecules that could disarm antibiotic-resistant bacteria and potentially make existing medicines effective again.

Researchers from UP, the University of Oxford in the UK, the National University of Lesotho, Kwame Nkrumah University of Science and Technology in Ghana, and the University of North Texas Health Science Center in the US collaborated on a major review of beta-lactam (β-lactam) antibiotics and the bacterial enzymes that destroy them.

Published in Natural Product Reports, the paper highlights a largely untapped opportunity. More than 400 000 naturally occurring compounds have been catalogued, yet only a small fraction has been investigated for their ability to inhibit β-lactamases, enzymes that can render important antibiotics ineffective.

“Antibiotic resistance is often presented as a search for the next completely new antibiotic, but there is another important possibility: protecting the medicines we already have,” said Professor Vinesh Maharaj, Director of UP’s Biodiscovery Centre, Acting Dean of the Faculty of Natural and Agricultural Sciences, and co-author of the paper. “Nature has already provided some of the compounds that have transformed infectious-disease treatment. We should not underestimate what remains to be discovered in the enormous chemical diversity of plants and microorganisms.”

The stakes are high. β-lactam antibiotics, including penicillins, cephalosporins and carbapenems, account for an estimated 60% to 65% of the antibiotic market. But bacteria have evolved increasingly sophisticated defences against them.

Among the most important are β-lactamases. These enzymes effectively break open the part of the antibiotic that allows it to work. More than 2 000 unique β-lactamases have been identified, including enzymes capable of undermining some of medicine’s last-line antibiotics.

The review cites estimates that bacterial antimicrobial resistance (AMR) directly caused approximately 1.14 million deaths in 2021. South Asia and sub-Saharan Africa together accounted for around 47% of global fatalities associated with bacterial AMR, while AMR is projected to cause about 8.2 million deaths annually by 2050 if current trends continue.

For co-author Dr Phanankosi Moyo, a biochemist and natural-product drug discovery scientist in UP’s Department of Plant and Soil Sciences, this makes the search particularly important for Africa.

“Sub-Saharan Africa carries a disproportionate burden of antimicrobial resistance, so this is not an abstract future problem for our region,” Dr Moyo said. “We need new antibiotics, but we also need smarter ways of extending the life of the antibiotics we have. Natural products give us an extraordinary starting library of chemical structures, and modern science now gives us far better tools to find the useful ones.”

Making existing antibiotics work again

There is already a powerful precedent.

Clavulanic acid, one of medicine’s best-known resistance blockers, is itself a natural product. Originally isolated from the bacterium Streptomyces clavuligerus, it has little antibacterial activity of its own. Instead, it blocks certain β-lactamases and protects an antibiotic from destruction.

Combined with amoxicillin, it became the widely used antibiotic treatment amoxicillin-clavulanic acid, a combination commonly marketed under the brand name Augmentin®. Its success demonstrated an important principle: scientists do not always have to replace an antibiotic. Sometimes they can disable the bacteria’s defence and allow the existing drug to work again.

The international team reviewed how scientists are trying to apply that principle to newer and more difficult forms of resistance.

Among the toughest targets are metallo-β-lactamases such as NDM, VIM and IMP. These enzymes use zinc to break down antibiotics and are resistant to the inhibitors used against many other β-lactamases.

Yet the natural world is producing intriguing leads. In one study examined in the review, a natural-product-derived compound called CS-23 inhibited NDM-1 and reduced the amount of the antibiotic meropenem needed to stop an NDM-1-producing strain of E. coli by 32-fold, restoring its effectiveness in the experimental system.

The review also highlights carnosic acid as the first reported natural product to inhibit NDM-1 through an allosteric mechanism. Instead of targeting the enzyme where it usually performs its chemical reaction, the compound acts elsewhere on it, offering researchers another possible route for disabling bacterial resistance.

Searching nature with new tools

The researchers argue that scientists now need to widen the search beyond familiar sources. Potential hunting grounds include Streptomyces and other microorganisms, fungi, plants, marine organisms and even lichens.

They can also search far more efficiently than previous generations. Modern approaches including metabolomics, structural biology, medicinal chemistry, computational screening, biocatalysis and synthetic biology can help identify promising molecules, understand how they work and modify them into better drug candidates.

“The next important β-lactamase inhibitor may not arrive as a ready-made medicine,” Prof Maharaj said. “Nature may give us the starting structure, and then chemistry, microbiology, structural biology and computational science can help us turn that starting point into something clinically useful.”

The international collaboration brings together expertise in natural-product chemistry, microbiology, phytomedicine, biochemistry and antibiotic-resistance research across Africa, the UK and the US.

There are still significant hurdles. A compound that works in a laboratory may struggle to enter bacterial cells, be unstable, lack sufficient selectivity or prove difficult to manufacture at scale. The researchers say promising natural compounds therefore need to be developed alongside medicinal chemistry and other modern drug-discovery approaches.

Finding broad-spectrum inhibitors capable of blocking several classes of β-lactamases at once is a particularly ambitious long-term goal.

“We have been in this race with bacteria since the first antibiotics were introduced,” Dr Moyo said. “The difference today is that we understand resistance at a molecular level and have technologies earlier generations could not have imagined.”

Much of the chemical diversity of plants and microorganisms has yet to be explored. This research shows that nature not only offers a simple cure for antibiotic resistance, but that it may still contain valuable starting points for protecting some of the medicines on which modern healthcare depends.

Harnessing artificial intelligence and metabolomics for discovery

Researchers at UP’s Biodiscovery Centre are working with collaborators to combine artificial intelligence, metabolomics and experimental screening to systematically sift through the centre’s in-house repository of approximately 11 000 plant samples in search of novel β-lactamase inhibitors.

By integrating computational prioritisation with chemical profiling and biological testing, the team aims to narrow this vast natural-product resource to the most promising candidates and accelerate the discovery of compounds that can overcome bacterial resistance mechanisms and help restore the effectiveness of existing β-lactam antibiotics.

Can nature help outsmart antibiotic resistance?

  • 400 000 naturally occurring compounds have been catalogued
  • 60% to 65% of the antibiotic market
  • 2 000 unique β-lactamases
  • 1.14 million deaths in 2021 due to AMR
  • 47% of global fatalities associated with bacterial AMR occur in South Asia and sub-Saharan Africa
  • 8.2 million deaths annually by 2050 if current trends continue

GLP-1 RAs Will Not Solve Diabetes

“South Africa’s diabetes epidemic will not be solved by the next pharmaceutical breakthrough. It will be solved by fundamentally reshaping how healthcare is organised and paid for”

– Lungile Kasapato, CEO of PPO Serve.

Diabetes is now South Africa’s leading killer, accounting for more deaths than HIV and TB combined. Global headlines celebrate GLP-1 receptor agonists (RAs) as a breakthrough for metabolic disease and obesity. But this narrative ignores a fundamental reality: for most South Africans, these drugs are inaccessible. Priced between R3 000 and R6 000 per month, they remain unaffordable. Even as cheaper generics become widely available, they won’t solve the problem alone. Without the clinical infrastructure to support treatment, and the social support to access healthy food, access means little.

“We’re pushing an incomplete solution,” says Lungile Kasapato, CEO of PPO Serve, a healthcare management company implementing value-based care in South Africa for over a decade. “GLP-1 RAs offer real benefits – sustained weight loss, reduced inflammation, lower cardiac risk, protection against comorbidities. For someone facing diabetes, these outcomes matter. But we’re acting as if a drug alone can solve a system failure. It can’t. A medication prescribed into a broken healthcare system is just a product. It’s not a national health strategy.”

The scale of the crisis is staggering. Forty percent of low-income South Africans’ diet consists of ultra-processed foods. Across the broader population, nearly 30% have undiagnosed hypertension. Most discover their condition only after complications like strokes or heart attacks emerge. By the time they reach treatment, the system can only manage disease with medications, never addressing what caused it in the first place. When a GLP-1 RA is prescribed in this fractured environment, initial sustained progress stalls because the infrastructure to maintain results was never built.

“This fragmentation isn’t accidental,” says Kasapato. “It’s structural. Fee-for-service rewards volume, not health. A provider, working alone, gets paid for each visit, test, or procedure – regardless of whether the patient’s health improves. With no teamwork or incentive to coordinate, follow-ups become inconsistent and inadequate. Every encounter is transactional, continuity is impossible, and no one is accountable for the patient actually getting better. As long as we pay for activity instead of results, we won’t fix the system or build the infrastructure these medications need.”

PPO Serve’s The Value Care Team, implemented in partnership with the Government Employees Medical Scheme (GEMS), demonstrates what a different payment structure creates. GPs, nurses, dietitians, and care coordinators work together, sharing accountability for patient outcomes rather than billable procedures. Coordination becomes the norm, and prevention becomes profitable, meaning early intervention can stop complications before they escalate. Medication works better because the system supports it, including addressing the social issues that drive obesity in the first place. This is what reshaping incentives creates.

“The real choice isn’t just about drug access,” says Kasapato. “It’s about payment models, and the system it creates. Cheaper GLP-1 RAs could be available tomorrow – generics are already arriving. But availability achieves little without the organisation to deploy them. The conversation must progress from funding medications to funding the teams and systems that make them work. South Africa’s diabetes epidemic will not be solved by the next pharmaceutical breakthrough. It will be solved by fundamentally reshaping how healthcare is organised and paid for.”

A Less-intensive Drug Combination is More Effective in Treating AML, Trial Shows

Acute myeloid leukaemia patients receiving azacitidine plus venetoclax tolerated treatment better, spent less time in the hospital and were more likely to reach stem cell transplantation

Photo by Ivan S

Investigators from the Mass General Brigham Cancer Institute have found that adults with newly diagnosed acute myeloid leukaemia (AML) receiving a less-intensive combination of azacitidine and venetoclax had more than twice as much time before treatment failed, the leukemia returned or worsened, or they died, compared with patients receiving intensive chemotherapy. Published in The New England Journal of Medicine, the findings could change the initial treatment approach for many patients with AML.

“Less-intensive treatment does not necessarily mean less-effective treatment,” said lead author Amir T. Fathi, MD, director of the Leukemia Program at the Mass General Brigham Cancer Institute. “Our goal is to optimally treat acute myeloid leukemia while reducing serious complications and the amount of time patients spend in the hospital.”

The less-intensive combination is already used in older patients or those unable to tolerate intensive chemotherapy. The PARADIGM trial tested whether it could work as well – or better – for patients who could receive intensive chemotherapy, including younger patients.

The phase 2 clinical trial randomly assigned 172 adults eligible for intensive chemotherapy at nine U.S. centres to azacitidine plus venetoclax or intensive chemotherapy. Nearly three-quarters had harder-to-treat forms of AML.

Patients receiving the combination went 14.5 months before treatment failed, the leukaemia returned or worsened, or they died, compared with 6.2 months for those receiving intensive chemotherapy.

Treatment brought leukaemia into a remission state in 78% of patients receiving the combination and 53% of those receiving intensive chemotherapy. Patients receiving the combination also had fewer serious infections and bleeding problems. In the first 30 days, patients spent 12.5 days in the hospital with the combination versus 27.3 days with intensive chemotherapy. More patients receiving the gentler combination then proceeded to stem cell transplantation: 60%, compared with 40% of those receiving intensive chemotherapy.

“For decades, intensive chemotherapy has been the standard upfront treatment for patients considered able to tolerate it,” Fathi said. “Our findings suggest that some of these patients may do better with a less-intensive approach.”

The trial was not designed to show whether either treatment helped patients live longer. Future studies should test less-intensive treatments in excluded groups, including patients younger than 60 with NPM1-mutated AML and those with FLT3-mutated AML.

Source: Mass General Brigham

DRC’s Ebola Epidemic Could be the Worst in History: 4 Things that Could Help End it

Yap Boum, Mbarara University of Science and Technology and Marie Roseline Belizaire, Universidad de Alcalá

The Democratic Republic of Congo’s fight against Ebola has reached a tipping point. It can accelerate what it has been doing to bring the latest outbreak under control, or risk allowing it to persist as the worst Ebola epidemic ever recorded.

As at 1 September 2026, more than 6186 confirmed cases and 3007 deaths have been reported since May 2026 when it was first declared. It is the deadliest Ebola outbreak in the history of the DRC. The outbreak is being driven by the Bundibugyo strain of the virus that causes Ebola disease. There is currently no licensed vaccine or specific treatment for Bundibugyo.

The outbreak is thought to have originated in the high-mobility mining area of Mongbwalu in Ituri, north-east DRC, in late April 2026, before spreading through interconnected communities and healthcare networks to Rwampara and Bunia – health zones in the Ituri province – and subsequently Uganda.

The response to the outbreak has been nationally led by the government of the DRC, with Africa Centres for Disease Control, the World Health Organization and other partners supporting the expansion of surveillance, laboratory capacity, treatment centres, infection prevention and control, vaccination, logistics, community engagement and safe and dignified burials.

Significant progress has been achieved, including interruption of transmission in Uganda through decisive national leadership and close collaboration with communities.

However, in the DRC, insecurity, population mobility, delayed detection, gaps in financing and supplies, and insufficient community ownership have continued to sustain transmission.

The response is therefore not yet sufficient to interrupt transmission in the DRC. This underscores the need to bring surveillance, testing, treatment, vaccination and community engagement closer to the village level.

As public health experts with expertise in Ebola who have been at the forefront of containing the latest outbreak in DRC, it is our view that more is required.

What’s required is informed by the four factors that have made this epidemic difficult to control:

  • the DRC’s difficult geographical and humanitarian environment
  • highly mobile populations
  • low trust and poor community engagement
  • the incomplete scientific arsenal against the Bundibugyo virus.

The four factors

First, this is an outbreak occurring in an exceptionally difficult environment. The affected areas are vast, remote and, in many places, insecure. Short journeys can take a day or more on bad roads, particularly during the rainy season (which is now).

Second, populations are highly mobile. Mining communities, motorcycle transport, displacement and cross-border movement connect villages and health zones that are difficult to monitor. The outbreak has been concentrated in several interconnected areas, particularly in Ituri, about 2,886km from Kinshasa, the DRC capital. Bunia, the main urban hub in Ituri, is connected to surrounding transmission areas. Movement of people is important in the response.

Third, trust and community engagement remain challenges. When people are afraid, when health facilities have closed after health workers have died, or when families have experienced Ebola without seeing an effective response, they may delay or avoid getting help. This directly affects surveillance. Current investigations by our team suggest that a substantial proportion of cases are being identified outside established contact lists. The response therefore cannot depend only on traditional contact tracing.

Fourth, unlike Ebola caused by the Zaire species, the Bundibugyo virus has no licensed vaccine or specific treatment. Clinical research is therefore part of the response itself.

The DRC has launched Ebola vaccination in Kisangani. The first injections were administered to health workers and other frontline responders. More than 50 000 doses have been received. The International Coordinating Group on Vaccine Provision has approved 70 000 doses of Ervebo for use in the country. Around 20 000 doses will be used in a clinical trial to assess its effectiveness against the Bundibugyo strain.

The response thus far

It is important to recognise how much has been achieved in only three months – between 15 May and 15 August 2026.

More than 20 Ebola treatment and isolation facilities have been established or supported. At the height of the crisis in late May 2026, treatment capacity was overwhelmed, with bed occupancy exceeding 200%. In late August, occupancy had fallen to around 66%.

Laboratory capacity has expanded dramatically, with 22 laboratories operating across the five affected provinces. Before there was only one in Kinshasa with the capacity to detect Bundibugyo. This has helped reduce turnaround time between sample collection and result, from over a week to just hours.

Safe and dignified burials have also improved substantially, with the vast majority now taking place within 24 hours.

These improvements matter. They are signs that the response can change the trajectory of an epidemic when resources, coordination and technical capacity come together.

There are also encouraging epidemiological signals. The effective reproduction number has fallen substantially from the very high levels (Rt 4.0) observed in May. The average number of people that each patient infects has fallen from four to just over one.

The scale of resources mobilised for the outbreak is substantial, with approximately US$1.72 billion in pledges, including US$118.5 million committed by African countries. Around US$867 million (about half of the pledges) has reportedly been released.

The continental response plan launched on 27 June 2026 by Africa CDC and WHO was designed around a simple principle: one plan, one budget, one team, one monitoring and evaluation framework, with communities at the centre.

What’s required

The next phase must centre on the villages. Local representatives, health workers and leaders should become active partners in surveillance, early detection, referral, risk communication and community protection.

Digital tools can support this, but technology must serve the community rather than replace it.

Commercial motorcycle riders, who connect communities across enormous distances, must be engaged as partners in the response rather than being treated simply as a risk.

Vaccination must be brought closer to communities. Research must be done where the epidemic is occurring. Clinical trials of vaccines and therapeutics must proceed with urgency and scientific rigour.

Rebuilding trust

Essential health services must continue alongside Ebola control.

The same applies to the reopening of schools. This must happen with infection-prevention measures, including training teachers, providing hygiene facilities, developing clear referral mechanisms, and adapting communication about the epidemic for school children and families.

Humanitarian and Ebola responses must also be integrated. A community facing insecurity, displacement and disease cannot be expected to navigate separate systems for each crisis.

Finally, Ebola doesn’t respect borders. The collaboration between the DRC and Uganda shows what regional solidarity can look like. It’s about joint surveillance, moving diagnostic capacity closer to border communities, sharing information and coordinated action. The DRC-Uganda lessons must be extended to South Sudan, the Republic of Congo and other neighbouring countries as agreed in Bangui, Central African Republic, in mid August.

Yap Boum, Professor in the faculty of Medicine, Mbarara University of Science and Technology and Marie Roseline Belizaire, Researcher, School of Medicine, Universidad de Alcalá

This article is republished from The Conversation under a Creative Commons license. Read the original article.

Cancer Drug Reduces Atherosclerosis Inflammation and Plaque

Source: Wikimedia CC0

A new Yale study has identified a promising therapeutic avenue for atherosclerosis, a condition caused by inflammation and plaque buildup in arteries.

Martin Schwartz, PhD, Robert W. Berliner Professor of Medicine (Cardiology) and the study’s principal investigator, investigates how the mechanical forces from blood flow and pressure affect the cells lining the arteries and how cell responses to forces contribute to cardiovascular disease. Atherosclerosis predominantly impacts regions of the arteries that bend or branch, creating disturbances in blood flow dynamics that activate cells’ inflammatory pathways and eventually lead to plaque buildup.

In a study published August 31 in Proceedings of the National Academy of Sciences, Schwartz’s team, led by associate research scientist Divyesh Joshi, PhD, has now found that a protein complex called Polycomb Repressive Complex 2 (PRC2) is associated with disturbed blood flow, and that it inhibits anti-inflammatory mechanisms in the arteries that mitigate atherosclerosis.

By blocking PRC2, the team successfully reduced harmful plaque in animal models of the disease.

“By inhibiting PRC2, we boost protective pathways that reduce inflammation and could protect people from plaque rupture in atherosclerosis,” Schwartz says.

What causes atherosclerosis?

Atherosclerotic plaques are present in nearly all adults in developed countries. They are usually asymptomatic because a protective fibrous cap forms over the plaques. But if the cap weakens and ruptures, it triggers the formation of a blood clot that can lead to a heart attack or stroke. Plaques vulnerable to rupture tend to have a thinner cap or exhibit heightened inflammation.

Scientists believe there are three types of factors driving atherosclerosis. The first are metabolic risk factors, including elevated cholesterol and blood sugar. Inflammation is another – individuals with autoimmune or other inflammatory diseases are at a higher risk for the disease.

An important but overlooked third factor, Schwartz says, is the biomechanics of blood flow through the arteries. In places where the arteries are straight tubes, the blood flow activates protective, anti-inflammatory genes. Where arteries curve sharply, disturbing blood flow, there are fewer of these protective factors and increased inflammation.

Protein complex suppresses protective genes

The cells lining the arteries, called vascular endothelial cells, have receptors that detect blood flow. Previous research in Schwartz’s laboratory has shown that blocking those receptors can inhibit inflammatory processes and enhance protective ones. In the new study, the researchers investigated the underlying mechanisms of the inflammation associated with disturbed blood flow.

First, they used previously published datasets to investigate genes that interact with anti-inflammatory genes in endothelial cells, and then identified those that promote disease. These analyses revealed that genes associated with PRC2, a protein complex that inhibits gene expression, were strongly associated with suppression of certain anti-inflammatory genes.

“PCR2 is understood to be pro-inflammatory in vascular endothelial cells,” Joshi says.

The researchers also studied gene expression in human endothelial cells exposed to normal and disturbed blood flow. These experiments confirmed that genes associated with PRC2 are upregulated during disturbed blood flow where inflammation tends to be higher.

However, when the researchers treated endothelial cells with tazemetostat, a drug that inhibits PRC2 and was previously used to treat cancer, they found that inflammatory signals were reduced. The findings suggest targeting PRC2 could be a treatment for atherosclerosis.

A new avenue for treating atherosclerosis

To explore PRC2 inhibition as a therapeutic avenue, the researchers developed animal models of the disease and tested the effects of tazemetostat. They found that the drug slowed plaque growth and reduced the amount of vulnerable plaque.

“It takes an unstable plaque and turns it into a more stable form that is no longer at risk of rupture,” Schwartz says.

Since conducting the study, the manufacturers of tazemetostat have withdrawn it from the market due to emerging evidence that patients who take the drug have a slightly increased risk of secondary cancers. But there are other PRC2-inhibiting drugs that may be similarly useful for treating atherosclerosis, the researchers note.

“This is a potential path forward to treating patients,” Schwartz says.

By Isabella Backman

Source: Yale School of Medicine

Are Antibiotics an Effective Treatment for Chronic Low Back Pain?

Photo by Sasun Bughdaryan on Unsplash

There has been considerable interest in prescribing antibiotics for chronic low back pain from disc herniation, stemming from the hypothesis that low-grade bacterial infections within spinal discs may contribute to persistent symptoms, particularly in cases involving Modic changes, which are bone marrow abnormalities visible on MRI.

A new randomised clinical trial investigated whether the antibiotic amoxicillin-clavulanate could effectively reduce chronic low back pain in patients with disc herniation. Researchers conducted a double-blind, placebo-controlled study involving 170 participants over a 12-month period to assess improvements in pain intensity and disability.

The trial found that taking amoxicillin-clavulanate for 90 days provided no significant reduction in pain or disability compared to a placebo. These findings suggest that the routine prescription of antibiotics for back issues is ineffective and potentially harmful due to the risk of side effects and the global threat of antimicrobial resistance.

Clinical experts advise against this approach, noting that current evidence does not support using these drugs even when traditional treatments have failed. Consequently, the study reinforces the need for evidence-based management and cautions against relying on unproven pharmaceutical interventions for complex spinal conditions.

Listen to the podcast for a deep dive into the results!

SAHBA 2026: Beyond Clinical Excellence

As a healthcare professional, you face career decisions that go far beyond clinical practice. Whether you are building your career, exploring new opportunities, starting a private practice or growing an established one, SAHBA empowers you with the insights, connections and practical guidance to move forward with confidence.

As a PPS initiative, SAHBA helps healthcare professionals build rewarding, future-ready careers through learning, mentorship and networking opportunities designed around their evolving needs.


Four learning pillars. One personalised journey.

Every SAHBA event is built around four key areas of professional growth:

Clinical leadership

Explore the future of healthcare, clinical excellence and leadership.

Opportunities beyond clinical practice

Discover new ways to apply your expertise through leadership, entrepreneurship and other professional pathways.

Private practice

Gain practical guidance on joining, starting and managing a successful practice.

Practice growth

Learn how to strengthen operations, enhance patient experience and grow sustainably.


Women in Medicine Forum 2026

12–13 September 2026

Career clarity. Practice power. Financial freedom.

Join one of South Africa’s leading gatherings of women healthcare professionals for two days focused on leadership, career growth, entrepreneurship, financial empowerment and well-being.

Engage with industry leaders and peers through keynote presentations, workshops, mentorship conversations and practical learning experiences.

Leave with fresh perspectives, meaningful connections and actionable insights to support your next chapter.

Register now : https://www.sahbacademy.co.za/women-in-medicine-forum/


SAHBA Symposium 2026

6 – 8 November 2026

The SAHBA Symposium is SAHBA’s flagship annual event for healthcare professionals who want to build a career that extends beyond clinical excellence.

Explore career development, private practice, business growth, wealth creation and innovation through expert-led sessions, practical workshops and curated networking opportunities.

Create your own pathway and leave with a clear plan to help shape your future.

Register now: https://www.sahbacademy.co.za/sahba-symposium/

Wherever you are in your professional journey, SAHBA provides the guidance, connections and opportunities to help you build a career and practice with confidence.

“This One was Brought by God Himself” – the Doctor Helping People See Again in Rural KZN

Dr Hennie Hamilton with his wife Sylivia and son near their home in Ingwavuma in northern KwaZulu-Natal. (Photo: Halden Krog/Spotlight)

By Sue Segar for Spotlight

As a young doctor working in rural KwaZulu-Natal, Hennie Hamilton lived with a Zulu family for four years, an experience which, he says, changed him forever. Twenty-three years later, he’s still working in the area as medical manager at Mosvold Hospital and doing cataract surgery on patients from five rural hospitals.

In the corner of a small ward in a rural hospital in northern KwaZulu-Natal, an elderly woman with a plastic shield covering her left eye sits up in bed. Her daughter, seated on a chair beside the bed, is holding her hand.

There’s silence, an air of quiet anticipation as a tall doctor leans over the woman and, in deep concentration, slowly removes the eye shield and the eye pad underneath it.

Next, the doctor gently eases her eye open and looks closely into her face to see her response. “Uya bona, Mama?” (Can you see, Mama?) Dr Hennie Hamilton asks the woman, keeping a hand on her shoulder.

The woman, Duduzile Phakathi from Mthubathuba, flickers her eyes. Her grip tightens on her daughter’s hand. “Yebo,” she answers, almost inaudibly, and her face breaks into a smile as she focuses, incredulously, on the tall man in front of her. “Ngiyabonga,” (Thank you) she says. The room erupts into excited chatter as mother and daughter start praying out loud, pouring blessings onto the doctor.

Eye patients from five hospitals – and further

It’s not yet 07:00, and Hamilton, medical manager at Mosvold Hospital in the mountain town of Ingwavuma, is already walking the wards. Every Monday, this quietly spoken man performs cataract surgery on patients from all over the uMkhanyakude district of KwaZulu-Natal. Besides coming from the area served by Mosvold Hospital, patients are referred to him from the other four hospitals in the district – Manguzi, Bethesda, Mseleni and Hlabisa. Tuesdays are for opening the eyes and checking the surgery has been effective.

After losing her sight to cataracts, Duduzile Phakati is overjoyed to see again and get back to caring for her chickens. (Photo: Halden Krog/Spotlight)

As a shaft of morning sunlight beams into the room and onto the faces of the two women, Hamilton, dressed in a black embroidered African work tunic called a Dashiki, explains what he’s doing. He speaks with a strong Afrikaans accent, despite his English last name.

“This patient had what is known as a dense cataract and was completely blind. We operated on her right eye in June, and yesterday we did her left eye. Today, we’re opening the eye and checking whether the operation has been a success,” he says.

A cataract, he explains, is an opacity, or cloudiness, of the lens in the eye, which blocks the passage of light and causes a person’s vision to blur or dim. “It normally happens in old age. Sometimes it arises from diabetes or injuries or trauma, or it can be caused by medication. Some people are born with it, but 95 percent of the patients we see have it because of old age.”

He continues: “Most people will eventually get a cataract. The big difference in this area is that people present very late. In rural areas like this, 20 percent of the patients we operate on are already blind in both eyes. People just wait for longer before they finally come for help.”

Cataract surgery, he says, is a short, painless procedure which involves numbing the eye using eyedrops and an injection; making an incision in the cornea; creating a small “tunnel” on the white of the eye; removing the cataract lens through the tunnel; and then, by folding and inserting it through the incision, replacing the inside of the lens with an artificial lens, made from synthetic material. The incision self-seals and needs no stitches and patients experience an improvement in their vision shortly after the procedure.

“Brought by God himself”

Phakathi’s daughter, Dorothy Mbonambo, says her mother who has diabetes, has been struggling with her eyes for some time. “She was a very busy woman, who loved looking after, and selling her chickens.” But she became totally blind in February, and suddenly she couldn’t do anything for herself.

“We had to feed her, bathe her, and dress her at home, where we all live together. We did not anticipate this at all, and we had to adapt. My mother was really struggling,” says Mbonambo.

Translating for her mother, she continues: “My mother is excited that she can see again. She loves to count her money from selling chickens. It has been frustrating not to be able to do that. She can’t wait to get back to her business, to her normal life.”

Mbonambo says the family was determined to get their mother to Mosvold Hospital for the surgery. “We knew about Dr Hamilton because people talk about this man who came here when he was young, and speaks isiZulu and does the eyes and other operations too.”

Still holding her beaming mother’s hand, Mbonambo points to Hamilton, saying: “This one was brought by God himself.”

“Before, everything was blank”

Next, Hamilton walks into another ward, bigger than the last, where seven more women who had cataract surgery the day before, are recovering. Similar scenes play out as he removes the eye shields for each woman.

Primrose Gina who works as a porter at Mseleni Hospital, says she started struggling with her eyes about three years ago. As the condition of her eyes worsened, it became increasingly difficult to see, and she was told it was cataracts.

After three years of struggling with her vision, Primrose Gina celebrates a new beginning following cataract surgery. (Photo: Halden Krog/Spotlight)

As Hamilton opens her eyes, she lets out an exhilarated shout and tells him she can see.

Gwendolin Mthethwa, a teacher from Ndumo, says her eyes still feel “cloudy” after her operation. This, Hamilton explains, is because, besides the cataract, she also has glaucoma in both eyes.

“Glaucoma is a disease of the optic nerve at the back of the eye which is caused by a build-up of fluid pressure inside the eye, causing damage to the nerve, often due to natural drainage systems being faulty.

“The difference between glaucoma and cataracts is that, with glaucoma, if the damage has happened to the nerve, we cannot reverse it,” Hamilton explains. “We can only try and prevent it from getting worse. But for a cataract, a patient can go from blindness to normal vision again.”

A busy day in the life of a medical manager

It’s nearly 08:00 and Hamilton has already seen eight eye patients. As he strides through the large female ward, the room erupts into song as nurses and some patients gather in the communal ward. “Every morning, we pray together, to connect with the Lord before we start our duties,” a nurse explains.

Next up is a meeting with the hospital’s CEO, Dr Bernard Mung’omba. As part of the hospital’s senior leadership team, Hamilton is closely involved in audits for the provincial health department and overall hospital decisions. As medical manager, he oversees medical care for patients – supervising the doctors, allied health professionals and all other departments including the pharmacy and the hospital’s social workers.

The 186-bed hospital employs 17 doctors and serves seven clinics and a community health centre in the uMkhanyakhude district. The area is characterised by poverty, with many people relying on grants and government work opportunities and living in mostly rural homesteads. Unemployment, teenage pregnancy and substance abuse are big challenges.

As a rural hospital, Hamilton says, “we do bits of everything”. “Last night, I was on call and at 23:30, was in theatre doing a caesarean section.” As medical manager, he says he plays less of a frontline than an advisory role, helping with emergencies from ectopic pregnancy to premature babies, and appendicitis. “We also deal with many diabetic and hypertensive-related emergencies like heart failure, and see many strokes, among older people,” he says.

“The spectrum is extremely wide. We’re a team of people with different strengths and we all rely on one another,” he says.

But it’s the eye operations which he says he finds most rewarding. “Ag, I love it … it gives me so much joy,” he says. “The patients often bless me. They say, ‘may God bless you’. I’m often in tears in the morning when I open their eyes.”

A long history

Mosvold Hospital was founded in 1908 by Christian missionaries and started out as a small stone rondavel. It was taken over by Scandinavian missionaries in the 1930s. The hospital is named after a Norwegian nurse, Esther Mosvold, who worked there in the 1940s, fell in love with the area, and raised money through her wealthy shipping family to expand the hospital. In 1978, the then Natal provincial government took over the hospital and the mission doctors slowly departed.

Hamilton shows us the original stone clinic next to an old chapel which, he says, resignedly, is now used for storage; and a house once lived in by missionaries, which is now the admin office. He points to a site where the provincial government is building a children’s ward and a lodge for mothers to stay while visiting children in hospital; and, on the other side of the hospital, a complex of 40 bachelor flats being built for staff at a cost of R400 million. The project should be completed next year, he says, adding it will be a “gamechanger” for Mosvold. “Mothers visiting their children in hospital currently sleep on mattresses on the floor.”

On our tour, we visit the ward where Hamilton’s eldest child was born in 2007. “It’s grown so much since then,” he says. Around us, the different departments – therapy, dental, radiography, and the pharmacy – are all bustling. In the children’s ward, manager Noziphe Gumbi says they’re seeing way fewer burn wounds this year. “We’ve really focused on outreaches to educate people on the dangers of burns among children,” she says.

Hamilton says he has seen many changes at Mosvold over the years, the biggest being the number of staff. “We’ve almost doubled the number of doctors, so we can spend much more time with patients. There was a time when there were only four doctors. Now, with 16, sometimes 17 doctors, we don’t have to run, run, run like we used to,” he says. “When I arrived, we were only white doctors, now I’m the only white doctor here which helps a lot in terms of language and knowing the people.”

A life in medicine

Hamilton was born in Johannesburg and studied medicine at Pretoria University. In 1997, he started his internship at McCord Hospital, then a mission hospital, in Durban. In 1998, he moved to Bethesda Hospital where, he learnt how to be “an all-round doctor”. He went on to complete qualifications in obstetrics and orthopaedics and trained to do cataract surgery at Edendale Hospital.

He worked at Bethesda at a time when HIV was “completely overwhelming”, he says. A large part of his work was supporting HIV patients clinically and he started a home-based care programme there. In 2003, he met his wife, Sylvia, a Swiss nurse, who, having previously worked in northern KwaZulu-Natal, had returned to start a home-based care programme at Mosvold. They married four months after meeting, and Hamilton moved to Mosvold in 2003, eventually becoming medical manager in 2015.

Why he stayed

“While I was working at McCord’s Hospital in 1997, I met another doctor, Colin Pfaff, who was working at Manguzi Hospital, who was living with a Zulu family,” Hamilton recalls. “When Colin told me about his experience, something just jumped in me. I believe it was God. I realised this was what I wanted to do.”

Less than a year later, while working at Bethesda Hospital, Hamilton moved in with the Nhlekos. “I lived in a mud hut with no running water or electricity. The house was about six kilometres from Bethesda and I’d cycle up and down the mountain to work every day. I became part of the family. In the evenings, I’d sit in the kitchen with my gogo. I learnt to speak fluent isiZulu.

“It was an amazing time, even though it was only for four years. It was the most beautiful place on earth,” he says.

Hamilton shuts his eyes and says: “This experience changed me forever. I was raised very much in an Afrikaner setting. During my high school, our family moved to a farm in the Free State. We lived completely separate from black people, eating from different plates, using separate toilets. There was always this issue of race which I just accepted.”

He continues: “Living with an isiZulu family completely changed that. They gave me a Zulu name, Sandiso, which means spreading God’s grace. People still call me ‘Mgilitsha’, the clan name for the Nhlekos. I learnt to see all people as people, to trust, and to love. It was a heart thing, the most life-changing part of my life.”

This article was first published by Spotlight – health journalism in the public interest. Sign up to the Spotlight newsletter.